Testosterone is often associated with men, but women naturally produce this hormone throughout life. In women, testosterone contributes to sexual function and interacts with muscle, bone, metabolism, and other body systems. When testosterone therapy is clinically appropriate, treatment should be individualized and monitored so hormone levels remain within the normal female physiologic range. Subcutaneous testosterone injections place a small amount of medication into fatty tissue just beneath the skin, where it is gradually absorbed. However, the strongest clinical evidence for testosterone therapy in women remains with transdermal treatment, especially for postmenopausal women with hypoactive sexual desire disorder, or HSDD.
At ChiroMed – Integrated Medicine in El Paso, Texas, this topic fits within a broader model of coordinated healthcare. Chiropractic care, nurse practitioner services, rehabilitation, nutrition, functional health strategies, and medical oversight can work together to address a patient’s musculoskeletal function and overall health rather than focusing on hormone levels alone. ChiroMed describes its approach as bringing multiple healthcare disciplines together to create individualized, patient-centered treatment plans.
Understanding Testosterone in Women
Testosterone is a natural part of female physiology. The ovaries and adrenal glands contribute to androgen production, and testosterone levels normally change with age. Levels can also fall more quickly after ovary removal.
Testosterone interacts with many tissues throughout the body, including the brain, muscles, bones, reproductive tissues, and blood-forming system. However, recognizing these biological roles does not mean testosterone therapy has been proven to treat every symptom that may occur during menopause.
The strongest evidence currently supports systemic testosterone therapy for appropriately evaluated postmenopausal women with HSDD. HSDD involves persistent loss of sexual desire that causes personal distress. Major international organizations have concluded that this is the clearest evidence-supported indication for testosterone therapy in women (Davis et al., 2019).
A large systematic review and meta-analysis also found that testosterone can improve several areas of sexual function in postmenopausal women, including sexual desire, arousal, pleasure, orgasm, responsiveness, and sexual self-image (Islam et al., 2019).
That distinction matters. Testosterone should not simply be prescribed because a laboratory value appears low.
What Are Subcutaneous Testosterone Injections?
A subcutaneous, or SubQ, injection places medication into fatty tissue beneath the skin rather than deeply into a muscle.
Testosterone cypionate may be prepared in concentrations that allow very small doses to be administered. Once placed into subcutaneous tissue, the medication forms a depot from which testosterone is gradually absorbed.
For women, the treatment goal is very different from testosterone treatment designed to produce male hormone concentrations. When testosterone is used for female HSDD, expert guidance recommends keeping concentrations within the physiologic range normally seen in premenopausal women rather than pushing testosterone above that range (Parish et al., 2021).
The attached clinical white paper makes an important distinction about SubQ injections. Randomized efficacy evidence in women is strongest for transdermal patches, creams, and gels. It describes subcutaneous injection as a titratable route with physiologic reasoning behind it, but notes that there is no dedicated randomized efficacy trial establishing SubQ testosterone injections for women.
That means SubQ testosterone should not be described as better proven than transdermal therapy. It is an alternative route that requires careful medical prescribing, laboratory monitoring, informed consent, and follow-up.
A “Low Testosterone” Number Is Not the Diagnosis
Laboratory testing is useful, but testosterone therapy in women should not begin solely because one test result falls near the lower end of a reference range.
The ISSWSH clinical guideline recommends a biopsychosocial assessment before treatment. A clinician may need to consider menopause status, medications, relationship factors, depression or anxiety, sleep, vaginal discomfort, pain during intercourse, medical illnesses, and other issues that can affect sexual desire. Total testosterone is useful mainly as a baseline and monitoring measurement rather than as a diagnostic test for HSDD (Parish et al., 2021).
The clinical white paper emphasizes the same principle. Testosterone measurements become especially important after therapy begins, because they help the healthcare team determine whether treatment remains within a physiologic female range and whether the patient is receiving too much hormone.
Testosterone, Muscle, and Musculoskeletal Health
Testosterone interacts with skeletal muscle biology, which is one reason the hormone receives attention in discussions about aging, physical function, and strength.
A randomized study examined different testosterone doses in postmenopausal women who had undergone hysterectomy. Higher testosterone concentrations were associated with changes in lean body mass and some measurements of muscle power. Importantly, the clearer muscle effects occurred with the highest dose and testosterone concentrations above typical female physiologic levels. The authors also stated that longer-term trials were needed to balance potential benefits against long-term risks (Huang et al., 2014).
This research should not be interpreted to mean that testosterone is a proven muscle-building treatment for women. The clinical white paper specifically notes that body-composition benefits have not been established as an approved indication for female testosterone therapy.
This is where physical rehabilitation becomes important. Hormones may influence the environment in which muscle tissue functions, but stronger muscles still require appropriate loading, movement, nutrition, recovery, and neuromuscular training.
Connecting Testosterone Therapy With Chiropractic Care
Chiropractic treatment and testosterone therapy perform very different jobs.
Testosterone therapy is a medical treatment that requires appropriate prescribing and monitoring. Chiropractic care focuses on the musculoskeletal system, including joint movement, spinal mechanics, posture, physical function, and rehabilitation.
For a woman who is also trying to maintain strength and mobility as she ages, an integrated plan may include:
medically supervised hormone assessment when clinically indicated;
chiropractic evaluation of the spine, pelvis, and extremities;
resistance and strength rehabilitation;
balance, mobility, and stability exercises;
adequate dietary protein and overall nutrition;
evaluation of sleep and recovery;
management of previous injuries or chronic musculoskeletal limitations;
progressive exercise based on the patient’s current ability;
laboratory monitoring when hormone therapy is prescribed;
ongoing reassessment of both symptoms and physical function.
The important idea is that testosterone does not replace exercise or rehabilitation. Likewise, an adjustment cannot correct a hormone disorder. When appropriate, the two approaches can address different parts of the patient’s health.
How This Fits the ChiroMed Integrated Medicine Model
ChiroMed – Integrated Medicine in El Paso brings several healthcare services into a multidisciplinary setting. The clinic currently describes chiropractic care, nurse practitioner services, rehabilitation, nutrition, acupuncture, and related integrative services as parts of its overall healthcare model.
That structure can be useful when women’s hormone concerns overlap with other health issues.
For example, a woman discussing hormonal symptoms may also have chronic back pain, reduced physical activity, previous injury, poor sleep, loss of conditioning, weight concerns, or difficulty maintaining muscle strength. Treating only a laboratory number would not address all of those factors.
ChiroMed’s integrated injury model similarly describes combining medical evaluation, chiropractic care, rehabilitation, soft-tissue treatment, and functional medicine strategies within a coordinated recovery plan.
Dr. Alexander Jimenez, DC, APRN, FNP-BC, works within this multidisciplinary environment by integrating chiropractic and musculoskeletal assessment with his advanced-practice nursing and functional medicine background. His clinical approach emphasizes movement, nutrition, metabolic health, rehabilitation, and other factors that affect how a patient feels and functions.
Medical oversight is also part of the ChiroMed structure. ChiroMed identifies Maria Guadalupe Cardenas, MD, a board-certified internal medicine physician, as Medical Director, Clinical Director, and Collaborative Physician. The ChiroMed website lists her Texas medical license as J2933 and NPI as 1164426748.
In a multidisciplinary model, the goal is not to make chiropractic treatment a substitute for medical hormone management. Instead, medical and musculoskeletal professionals can contribute within their respective scopes of practice.
Monitoring Testosterone Therapy in Women
If testosterone treatment is selected, follow-up is an essential part of care.
The clinical guideline recommends monitoring testosterone concentrations to prevent exposure above the physiologic premenopausal range. Patients should also be evaluated for clinical signs of androgen excess (Parish et al., 2021).
Possible concerns can include acne, increased facial or body hair, scalp hair changes, and other androgenic effects. Voice changes are less common but deserve prompt attention. The attached white paper explains that these effects tend to be dose-related and that scheduled reassessment helps identify excessive exposure early.
A clinician may also consider the patient’s overall medical history, cardiovascular health, breast health, medications, and other hormone therapy.
Importantly, testosterone should not simply be increased because symptoms have not changed quickly. Expert guidance suggests evaluating response over several months and stopping treatment when there is no meaningful benefit rather than pushing testosterone beyond the normal female physiologic range.
What We Still Do Not Know
Testosterone therapy in women is an area where evidence and clinical practice do not always move at the same speed.
Transdermal testosterone has the strongest randomized evidence. The evidence supporting subcutaneous injections in women remains much more limited. The attached white paper specifically identifies subcutaneous injection evidence as pharmacokinetic rather than supported by dedicated female efficacy trials.
Long-term cardiovascular and breast safety also remain incompletely defined. Available shorter-term findings at physiologic doses are reassuring, but researchers still lack adequately powered studies that answer every safety question over many years.
This is why individualized treatment and shared decision-making matter.
Integrating Hormone Health With Movement and Strength
Women’s health is rarely about one hormone, one joint, or one treatment.
For selected women with HSDD, properly monitored testosterone therapy may be one part of care. If a SubQ route is considered, the treatment should remain medically supervised and should recognize that evidence for female subcutaneous injections is still developing.
At the same time, maintaining musculoskeletal health requires movement.
Progressive resistance exercise, adequate nutrition, good sleep, rehabilitation, healthy body composition, joint mobility, and injury management all contribute to maintaining strength and physical independence.
That concept fits naturally with the ChiroMed – Integrated Medicine approach in El Paso: combining conventional medical oversight with chiropractic care, rehabilitation, nutrition, functional strategies, and individualized patient education. ChiroMed describes its purpose as bringing different disciplines together so treatment plans can address both symptoms and underlying contributors to health and function.
Testosterone therapy and chiropractic care should therefore not be viewed as competing treatments. When clinically appropriate, each addresses different parts of the larger goal—helping women maintain healthy physiology, functional muscles and joints, mobility, and quality of life.
Uncover the significance of obesity medicine combined with chiropractic practice in enhancing patient care and achieving better health results.
Educational Abstract
In this comprehensive educational post, I, Dr. Alex Jimenez, share a first-person, evidence-based journey through modern obesity care across the lifespan. With credentials as a Doctor of Chiropractic (DC), Advanced Practice Registered Nurse (APRN), Family Nurse Practitioner-Board Certified (FNP-BC), and certifications in Functional Medicine (CFMP, IFMCP), among others, I offer a unique, multidisciplinary perspective. This guide is designed for clinicians, staff, and healthcare leaders seeking to build or optimize a high-quality integrative obesity program. I explain how our team at Injury Medical Clinic, P.A. (also known as Mission Plaza Injury Medical Clinic) in El Paso, Texas, frames obesity as a chronic, relapsing, multifactorial disease and translates that understanding into actionable practice models. Our clinic’s strength lies in its collaborative structure, led by our esteemed Medical Director and Collaborative Physician, Dr. Maria Guadalupe Cardenas, MD (NPI #1164426749, Texas MD License #J2933). A board-certified internal medicine physician with over 40 years of experience, Dr. Cardenas provides crucial medical oversight to ensure our integrative protocols meet the highest standards of safety and efficacy. Together, we integrate internal medicine, chiropractic care, functional medicine, rehabilitation, and personal injury services to deliver comprehensive, patient-centered care. This post offers a detailed roadmap covering the four pillars of obesity treatment—nutrition, physical activity, behavioral counseling, and medical management (including pharmacotherapy and bariatric surgery referrals). I provide pragmatic workflows for various practice models, including guidance on billing and coding (time-based vs. MDM), Medicare services like Intensive Behavioral Therapy (IBT) and Chronic Care Management (CCM), and innovative tools like Remote Patient Monitoring (RPM). We will explore the physiological underpinnings of obesity, the importance of reducing bias and using person-first language, and how to create a weight-inclusive clinical environment. My goal is to equip you with a compassionate, scientifically grounded template to implement sensitive, effective, and sustainable obesity treatment programs.
Introduction: My First-Person Journey to Building a Modern, Patient-Centered Obesity Program
I am Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST. For decades, I have devoted my clinical practice to integrative, trauma-informed, evidence-based care, with a central focus on metabolic health, functional rehabilitation, and personalized medicine. In daily practice, I witness how language, imagery, coding, and care design either reinforce old stigmas or usher in a better way—one that recognizes obesity as a chronic, relapsing, multifactorial disease that deserves precise diagnosis, compassionate communication, and coordinated, evidence-based treatment. In El Paso, Texas, our Injury Medical Clinic, P.A. (Mission Plaza Injury Medical Clinic) operates as a multidisciplinary ecosystem where internal medicine, chiropractic, functional medicine, and rehabilitation intersect to treat complex chronic conditions, including obesity. Working hand-in-hand with our Medical Director and Collaborative Physician, Dr. Maria Guadalupe Cardenas, MD—board-certified in internal medicine (NPI #1164426749, Texas MD License #J2933)—we deliver coordinated care that respects obesity’s chronic nature. Dr. Cardenas brings over 40 years of internal medicine experience, guiding medical oversight, safety, diagnostic rigor, and pharmacotherapeutic strategies. My role emphasizes integrative chiropractic biomechanics, musculoskeletal optimization, functional medicine assessment, and rehabilitation planning. This multidisciplinary setup, where an MD provides medical direction alongside a chiropractor, is common and highly effective in modern integrative and injury care clinics, ensuring continuity, safety, and comprehensive outcomes. Together, we build individualized programs that incorporate nutrition therapy, physical activity prescription tailored to pain and function, behavioral counseling, and medical management, including pharmacotherapies and referral to bariatric surgery when indicated. In this post, I will walk you through an actionable model to structure obesity care within primary care practices, specialty clinics, and standalone programs. I reframe obesity as a chronic, multifactorial disease requiring dedicated, obesity-specific appointments, regular follow-up (often averaging 16 visits in the first year for optimal outcomes), and collaborative workflows that reduce stigma and enhance access. The physiological underpinnings—neurohormonal regulation, adipose tissue biology, energy balance, biomechanics, pain, sleep, stress, and gut health—are explored in depth to explain why each therapeutic lever matters. My goal is to give you a clear, compassionate, scientifically grounded template for obesity care that you can adapt to your setting, whether you are starting with a single dedicated clinic session per week or designing a fully integrated multidisciplinary center.
Our Collaborative Practice: Integrating Chiropractic and Medical Expertise
Before we dive into the specifics of obesity management protocols, I believe it’s essential to set the stage by explaining our practice’s unique structure. Our clinic is built on integrative, multidisciplinary care. This model is not just a philosophy but a functional reality that allows us to provide a truly holistic level of service, particularly for patients dealing with complex conditions like chronic obesity, metabolic dysfunction, and personal injuries. A cornerstone of our practice is my collaborative relationship with Dr. Maria Guadalupe Cardenas, MD. Dr. Cardenas is a highly respected physician, board-certified in Internal Medicine, with an incredible four decades of experience. She serves as our Medical Director and Collaborative Physician, bringing a depth of medical knowledge that is simply invaluable. This partnership between a Doctor of Chiropractic (like myself, with additional APRN and functional medicine credentials) and an Internist (Dr. Cardenas) is a powerful synergy.
How Our Integrated Team Functions
So, what does this collaboration look like in practice?
Medical Oversight and Direction: Dr. Cardenas provides essential medical direction for our clinic. This includes overseeing protocols for prescription drug management, reviewing complex medical cases, and ensuring that our diagnostic and treatment plans meet the highest standards of medical care. When we are managing a patient’s GLP-1 medication or addressing comorbidities like hypertension and type 2 diabetes, her expertise as an internist is critical.
Chiropractic and Neuromusculoskeletal Care: As a Doctor of Chiropractic, my role focuses on the body’s structure and its relationship to overall function. For our patients with obesity, this is incredibly important. Excess weight places enormous stress on the musculoskeletal system, leading to chronic low back pain, knee arthritis, plantar fasciitis, and other biomechanical issues. Through chiropractic adjustments, spinal decompression, and soft tissue therapies, we address these structural imbalances, alleviate pain, improve mobility, and enhance nervous system function. This not only improves the patient’s quality of life but also removes a significant barrier to physical activity.
Functional Medicine and Advanced Diagnostics: As a certified functional medicine practitioner (CFMP, IFMCP), I lead our team in digging deeper to find the root causes of a patient’s health issues. Instead of just treating weight gain, we ask why it’s happening. We use advanced lab testing to look at hormonal imbalances, gut dysbiosis, nutrient deficiencies, and genetic predispositions. This allows us to create highly personalized nutrition and lifestyle plans.
Comprehensive Care Spectrum: Our team integrates rehabilitation services to restore function after an injury, provide dedicated personal injury care for accident victims, and offer nutritional and lifestyle counseling. A patient might see me for a chiropractic adjustment, consult on medication management under Dr. Cardenas’s oversight, work with our health coach on a functional nutrition plan, and engage in a rehab program to strengthen their core—all under one roof.
This integrated model ensures that we are not just managing obesity but treating the whole person. Constant communication between Dr. Cardenas and me allows us to create a seamless care experience where the medical and structural components of a patient’s health are addressed in a coordinated fashion.
Understanding Obesity as a Chronic, Relapsing, Multifactorial Disease
Obesity is a chronic, relapsing, heterogeneous disease characterized by excess adiposity that impairs health. It is not a personal failure, nor a short-term issue solved with quick fixes. Modern evidence shows that sustained management requires ongoing care—structured visits, targeted interventions, and a respectful, bias-aware environment. Key points:
Obesity behaves like other chronic conditions—such as diabetes, hypertension, and dyslipidemia—requiring long-term strategies rather than one-time solutions.
Dedicated, obesity-specific appointments are essential. Trying to address obesity “on the fly” during unrelated visits rarely allows enough time to take a comprehensive history, perform a physical and functional exam, and co-create a treatment plan.
Regular follow-up is linked to better outcomes. Data suggest that about sixteen visits in the first year are associated with improved weight loss and cardiometabolic outcomes; intensifying early on, then spacing visits as the condition stabilizes, is a pragmatic pattern.
Insurance coverage can influence feasible visit frequency. Plan workflows around coverage realities, supplement with telemedicine and group visits, and leverage allied health professionals to maintain contact.
Why this approach matters:
Chronic care models improve adherence and health outcomes across diseases; obesity is no exception.
Obesity’s relapsing nature—driven by neurohormonal adaptations and environmental pressures—demands continuity, not episodic care.
When we structure appointments intentionally, we can address root contributors—genetic predisposition, endocrine signals, psychosocial factors, sleep, stress, gut health, and musculoskeletal limitations—and tailor interventions responsibly.
Foundational Physiology of Obesity: A Systems View for Clinicians
Understanding obesity’s physiology informs our protocols and patient communication. I approach this as a dynamic systems disorder characterized by interactions across neuroendocrine signaling, immunity, metabolism, microbiome, biomechanics, and behavior. Key Mechanistic Domains:
Energy Homeostasis and Neuroendocrine Control:
Hypothalamic Regulation: Signals from leptin, insulin, ghrelin, peptide YY, GLP-1, and cholecystokinin converge to influence appetite, satiety, and energy expenditure. Leptin resistance undermines satiety signaling; ghrelin dynamics affect hunger.
Reward Pathways: Dopamine circuits modulate food salience; stress and sleep loss amplify hedonic drives.
Adaptive Thermogenesis: Weight loss decreases resting energy expenditure beyond predictions, encouraging regain; this underscores the need for sustained, supportive care.
Adipose Tissue Biology:
Hypertrophy vs. Hyperplasia: Enlarged adipocytes promote hypoxia, low-grade inflammation, and impaired insulin signaling.
Ectopic Lipid Deposition: Accumulates in the liver and muscle, exacerbating insulin resistance and metabolic dysfunction.
Adipokines and Cytokines: Imbalances in adiponectin, leptin, TNF-alpha, and IL-6 contribute to cardiometabolic risk.
Musculoskeletal Interplay:
Joint Loading and Pain: Mechanical stress increases in weight-bearing joints, altering gait and posture; pain limits activity, creating a cycle of deconditioning.
Sarcopenic Obesity: Reduced muscle mass with increased fat mass impairs glucose disposal and function; resistance training becomes a cornerstone.
Sleep and Circadian Rhythm:
Sleep Restriction: Increases ghrelin and decreases leptin, dysregulating appetite, increasing caloric intake, and impairing glucose tolerance.
Chronic Stress: Elevates cortisol, alters food choices, and impairs motivation.
Weight Stigma: Increases avoidance of care, reduces physical activity in public spaces, and worsens health outcomes independent of BMI.
The Four Pillars of Obesity Treatment: A Multidisciplinary Framework
In our program, the four pillars anchor care. Each pillar interacts with the others biologically and behaviorally, reinforcing momentum.
1. Nutrition Therapy: Physiology, Methods, and Personalization
Physiology: Appetite regulation involves ghrelin (orexigenic), leptin (satiety; often resistant in obesity), peptide YY, GLP-1, and insulin. Reward pathways and hyperpalatable foods drive hedonic intake beyond energy needs. Insulin resistance and hepatic steatosis alter substrate handling; reducing carbohydrate load and fructose can improve hepatic fat and insulin sensitivity. Methods:
Personalized eating patterns: Mediterranean-style, higher-protein plans, lower-carbohydrate strategies, time-restricted eating, or structured meal replacements. We adapt plans to cultural cuisines and budget constraints.
Focus on protein adequacy (generally 1.2–1.6 g/kg of adjusted body weight for weight loss phases), fiber density, and low-energy-density foods to improve satiety.
Address ultra-processed food exposure and reward-system dynamics; incorporate shopping skills, cooking education, and food environment restructuring.
Medical nutrition therapy for comorbidities: NAFLD/MASLD, insulin resistance, PCOS, hypertension.
Why it works: A sustained negative energy balance is necessary for weight loss; nutrient composition supports satiety and preserves lean mass. Reducing ultra-processed foods lowers hyperpalatable stimuli and reduces hedonic overeating. Tailoring to comorbid conditions enhances safety and adherence.
2. Physical Activity Prescriptions: Graded, Safe, and Function-Oriented
Physiology: Movement enhances energy expenditure, improves insulin sensitivity, preserves and builds lean mass, supports mental health, and reduces chronic pain through improved biomechanics. Resistance training preserves lean mass, helping maintain basal metabolic rate during weight loss. Aerobic exercise improves mitochondrial biogenesis and cardiovascular health. Methods:
Begin with low-impact options: walking, cycling, swimming, or aquatic therapy.
Progressive resistance training 2–3 days/week to maintain lean mass and metabolic rate; focus on compound movements scaled to function (e.g., chair stands, resistance bands, supported deadlifts).
Movement prescriptions integrated with chiropractic and rehabilitation when pain or postural dysfunction limits activity.
Non-exercise activity thermogenesis (NEAT) strategies to increase daily movement.
Integrate chiropractic-guided corrective exercises for posture and core stability.
Why it works: Preserving lean mass mitigates metabolic adaptation during weight loss. Strengthening corrects kinetic chain imbalances contributing to pain, allowing sustainable activity. Physical activity enhances mitochondrial function and cardiometabolic health beyond weight outcomes.
3. Behavioral Counseling: Skills That Sustain Change
Physiology: Sustained habit change requires skills such as self-monitoring, stimulus control, cognitive restructuring, and coping strategies. Chronic stress from stigma elevates cortisol, disrupts sleep, and worsens insulin resistance and visceral adiposity. Mindfulness improves interoception and reduces reward-driven overeating. Methods:
Health coaching for goal setting, problem-solving, and accountability, often using motivational interviewing.
Psychotherapy for depression, anxiety, trauma, or eating disorders when present.
Group-based support, peer accountability, and digital self-monitoring tools.
Cognitive reframing: Shift focus from weight to health behaviors; celebrate process milestones.
Relapse planning: Anticipating high-risk situations and setting recovery steps.
Why it works: Behavioral skills enhance adherence and resilience. Addressing mood and stress physiology improves appetite regulation and sleep, reducing relapse. Psychological safety increases adherence to nutrition, activity, medications, and follow-ups.
4. Medical Management: Pharmacotherapy and Comorbidity Care
Physiology: Medications modulate appetite and energy balance via central and peripheral pathways. For example, GLP-1 receptor agonists reduce appetite, slow gastric emptying, and improve insulin secretion and sensitivity. Methods:
Select anti-obesity medications (AOMs) based on phenotype, comorbidities, and contraindications under medical oversight. This includes GLP-1 receptor agonists, dual incretin therapies (GIP/GLP-1), and other approved medications per current guidelines.
Manage obesity-related comorbidities: type 2 diabetes, hypertension, dyslipidemia, OSA, NAFLD/MASLD, osteoarthritis.
Refer for bariatric surgery when indicated; coordinate prehab and rehab to optimize outcomes.
Why it works: Medications can be transformative when tailored and monitored. Comorbidity management improves safety and function, enabling activity and adherence. Surgery can produce durable weight loss and metabolic improvements in selected patients; integrated care maximizes benefits.
Balancing Body and Metabolism- Video
Integrative Chiropractic Care in Obesity Management: Biomechanics, Pain, and Functional Capacity
Integrative chiropractic is a key component of our multidisciplinary approach. Obesity frequently coexists with pain syndromes and postural dysfunction. These biomechanical issues can limit activity, creating a feed-forward cycle of deconditioning. Chiropractic evaluation and targeted interventions break that cycle. Clinical Rationale:
Excess adiposity shifts the center of mass anteriorly, increasing lumbar lordosis, pelvic tilt, and stress on load-bearing joints such as the knees and hips.
Compensatory postures lead to paraspinal hypertonicity, reduced thoracic mobility, and altered gait mechanics; pain follows and discourages movement.
Myofascial restrictions, trigger points, and joint dysfunction limit range of motion and increase the effort cost of activity.
Interventions:
Spinal and extremity adjustments to restore joint function, reduce nociceptive input, and improve proprioception.
Soft tissue therapies: myofascial release, instrument-assisted soft tissue mobilization, cupping, and neuromuscular re-education to normalize tone and improve tissue glide.
Postural retraining, breathing mechanics optimization, and core stabilization to distribute loads efficiently.
Progressive, pain-sensitive exercise prescriptions integrating mobility and strength, with graded exposure to activity to build confidence.
Why This Matters Clinically: By improving joint motion and reducing pain, chiropractic care can lower pain levels, improve movement efficiency, and enable progressive exercise. This enhanced activity capacity is a keystone for metabolic improvement. Better movement competence improves adherence to exercise prescriptions, a critical determinant of long-term success.
Internal Medicine Oversight: Safety, Diagnostics, and Medical Direction
Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine, serves as our Medical Director and Collaborative Physician. Her role ensures that our integrative program meets high standards of safety, diagnostic precision, and medical integrity. Responsibilities:
Comprehensive internal medicine evaluation: metabolic, cardiovascular, endocrine, and sleep assessments.
Pharmacotherapy supervision: selecting, dosing, and monitoring anti-obesity medications and comorbidity treatments, including GLP-1 receptor agonists.
Risk stratification: identifying patients who require closer monitoring, cardiology referral, or specialist evaluation.
Surgical coordination: ensuring patients meet bariatric referral criteria and overseeing perioperative medical care.
Quality assurance and compliance: aligning protocols with current evidence and regulatory standards.
t: Medical oversight reduces adverse events, optimizes medication choices, and integrates comorbidity care. Collaboration with chiropractic and rehabilitation ensures the safe progression of activity in medically complex patients. Patients benefit from a consistent, trusted, evidence-based, and personalized framework.
Functional Medicine Integration: Systems Biology Applied to Obesity
Functional medicine complements internal medicine and chiropractic by taking a systems biology view of the patient. We examine the interconnected networks influencing weight: nutrition, energy metabolism, inflammation, gut health, hormones, sleep, stress, and toxins. Key Elements:
Personalized nutrition with elimination of trigger foods, gut-directed therapies for dysbiosis, and micronutrient repletion.
Inflammation modulation through dietary patterns and lifestyle change.
Sleep optimization: screening and treatment for OSA, sleep hygiene, and circadian rhythm alignment.
Stress physiology: HPA-axis support and mindfulness practices to reduce hyperphagic responses.
Environmental exposures: addressing ultra-processed foods and sedentary hazards.
Why integrate functional medicine: Complex obesity phenotypes benefit from personalized, root-cause investigations that guide targeted interventions. Combining internal medicine safety with functional assessments yields holistic plans that are both evidence-based and individualized.
Sensitivity Training and Bias Reduction: Creating a Respectful, Person-First Environment
Patients with obesity frequently encounter stigma in healthcare settings. Reducing bias improves trust, adherence, and outcomes. Shame reduces engagement in care and heightens stress physiology. Positive framing, by contrast, increases adherence and reduces defensiveness. Core Elements:
Use person-first language: We say “a person with obesity,” not “an obese person.” We adopt neutral descriptors like “severe obesity, class 3” instead of “morbid obesity.” In notes, we document “barriers to adherence identified” instead of “noncompliant.”
Eliminate stigmatizing imagery: We avoid pictures that show individuals with heads cropped off or engaging in stereotypical behaviors. We choose empowering visuals of people of diverse body sizes engaged in daily life.
Provide appropriate equipment:large blood pressure cuffs, sturdy and comfortable seating, accessible exam tables, and weight-inclusive gowns.
Privacy and dignity in weigh-in procedures: Offer “no-scale” days and ask patients if they want to know their weight.
Staff training on obesity as a chronic disease, not a moral failing. We use role-playing to practice person-first language and active listening.
Why it matters: A respectful environment fosters strong therapeutic relationships and long-term success. Safety and comfort reduce anxiety, improving heart rate variability and perceived control.
Mastering the Fundamentals: Time-Based Billing vs. Medical Decision-Making (MDM)
One of the most critical aspects of building a sustainable obesity management practice is understanding how to bill for your services accurately and ethically. Two primary pathways exist for billing Evaluation and Management (E&M) services: billing by time and billing by medical decision-making (MDM).
Patient Status
CPT Code
Total Time Required for Time-Based Billing
New Patient
99202
15-29 minutes
99203
30-44 minutes
99204
45-59 minutes
99205
60-74 minutes
Established Patient
99212
10-19 minutes
99213
20-29 minutes
99214
30-39 minutes
99215
40-54 minutes
Unpacking Time-Based Billing
When you bill based on time, total documented time determines the CPT code. This method is often ideal for obesity-focused visits because much of the encounter focuses on counseling, education, and behavioral coaching. “Time” includes total time spent by the billing provider on the date of the encounter, including pre-visit chart review, face-to-face time, and post-visit documentation and order placement. A Practical Example of Time-Based Billing: At the end of my visit note, I add a time attestation statement: “I spent a total of 33 minutes today on this patient’s care. This time was spent on:
History, Exam, and Ordering (during visit): 5 minutes for the face-to-face examination and order entry.
Treatment Planning & Counseling (during visit): 20 minutes for extensive counseling on nutritional strategies, medication mechanisms, and behavioral goal-setting.
Updating Chart (post-visit): 5 minutes to finalize documentation and send prescriptions.
Total Time = Time in minutes. This total time in minutes for an established patient directly correlates with a CPT code 99214.
Decoding Medical Decision-Making (MDM)
The second option for billing is based on the complexity of your Medical Decision-Making (MDM), which is determined by:
Number and Complexity of Problems Addressed
Amount and/or Complexity of Data to Be Reviewed and Analyzed
Risk of Complications and/or Morbidity or Mortality of Patient Management
To bill at a certain level, you must meet the requirements for that level in at least two of these three categories. A key element is that any visit involving prescription drug management—initiating, continuing, or modifying any prescription medication—signals at least moderate risk, which supports a Level 4 code (99214). This is particularly relevant for short telehealth visits where a medication dose is changed.
ICD-10-CM Coding and Documentation
Accurate coding is not just about reimbursement; it’s about representing the true burden of disease. The 2024 ICD-10-CM updates improve accuracy and support stigma-free language.
Always pair E codes (obesity) with Z codes (BMI). If documenting obesity, record a same-day BMI and link the corresponding Z code.
Use specific codes for pediatric and adult patients that reflect BMI class and complications (e.g., hypertension, type 2 diabetes, dyslipidemia).
Document medical necessity by detailing functional limitations, comorbidity risks, and health impact.
Expanding Your Services: Beyond the Standard Office Visit
To create a comprehensive program, we must think beyond traditional E&M visits. Several other billable service categories can enhance patient outcomes and practice sustainability.
Service Category
Payer
Associated CPT/HCPCS Codes
Key Function
Intensive Behavioral Therapy (IBT)
Medicare
G0447, G0473
Behavioral change for sustained weight loss
Preventive Care Counseling
Commercial
99401-99404
Behavioral counseling for risk factor reduction
Chronic Care Management (CCM)
Medicare
99490, 99491, 99487, 99489
Non-face-to-face care coordination
Remote Patient Monitoring (RPM)
Medicare/Commercial
99453, 99454, 99457, 99458
Remote data collection and management
Medicare Intensive Behavioral Therapy (IBT) for Obesity
IBT is a specific Medicare benefit for behavioral change interventions. The key code is G0447 (face-to-face behavioral counseling for obesity, 15 minutes). This is not an E&M visit; the focus must be exclusively on behavior, nutrition, and exercise, with no discussion of comorbidities or medication management. Qualified staff, such as an RN or health coach, can render these services under your direct supervision, freeing you for more complex E&M visits.
Preventive Screening and Counseling for Commercial Insurance
For commercial insurance patients, Preventive Counseling codes (99401-99404) serve a similar function. These time-based sessions focus on diet, exercise, and lifestyle modifications. Unlike IBT, you cannot bill these codes on the same day as a standard E&M visit.
Medicare Chronic Care Management (CCM)
CCM compensates you for the non-face-to-face time yoTimed your staff spends coordinating care for patients with two or more chronic conditions. This includes phone calls, prescription refills, and reviewing records between appointments. Using codes like 99490 (first 20 minutes of clinical staff time) provides a framework for monthly check-ins, keeping patients engaged and accountable.
The Future is Now: Remote Patient Monitoring (RPM)
RPM leverages technology like 5G-enabled smart scales, blood pressure cuffs, and glucometers to gather objective data between visits. The device must be FDA-approved and paid for by the practice. Key codes include 99453 (setup), 99454 (device supply and data transmission for 16+ days a month), and 99457 (first 20 minutes of management time). RPM provides real-time data and accountability, which is phenomenal for engagement.
Crafting the Patient Journey: A 6-Month Care Plan Roadmap
Together, we can create a high-touch care plan that fosters accountability and allows rapid course correction. The evidence overwhelmingly supports that patients with frequent contact achieve the best outcomes.
Monthly Follow-up Visits: E&M visits for medical management (99214).
Bi-Weekly Preventative Counseling Visits: 15-30 minute sessions with an RN/coach (99401/99402 on separate days).
Ongoing RPM: Monthly data uploads and staff follow-up (99454 + 99457).
This model provides a touchpoint with your clinic every single week.
The Medicare Patient Journey
Visit 1 (Week 1): Initial Consultation (E&M Visit, 99204/99205) plus a 15-minute IBT session (G0447) with a -25 modifier.
Monthly Follow-up Visits: E&M visits for medical management (99214).
Weekly/Bi-Weekly IBT Visits: 15-minute behavioral sessions with staff (G0447).
Ongoing CCM and RPM: Non-face-to-face support (99490) and remote data management (99454 + 99457).
This high-touch model provides weekly contact, robust support, and continuous education, which are crucial for long-term success.
Final Thoughts: A Compassionate, Evidence-Based Path Forward
Obesity care thrives in multidisciplinary, patient-centered environments. By combining internal medicine oversight, integrative chiropractic, functional medicine, behavioral coaching, and thoughtful program design, clinics can deliver durable improvements in health and quality of life. Our comprehensive model at Injury Medical Clinic, P.A. values empathy, science, and practicality—meeting patients where they are and supporting them as partners in their journey. Building a practice that effectively manages obesity is complex but incredibly rewarding. By mastering these billing and care strategies, you can build a program that is not only clinically effective but also financially sustainable, helping more people for years to come. For more on my clinical perspectives and practice focus, visit: ChiroMed site: [https://chiromed.com/] LinkedIn profile: [https://www.linkedin.com/in/dralexjimenez/]
SEO Tags: Obesity Management, Medical Billing and Coding, Time-Based Billing, Medical Decision Making, CPT Codes, 99214, 99204, Integrative Care, Chiropractic Care, Dr. Alex Jimenez, Dr. Maria Cardenas, Functional Medicine, Chronic Care Management, CCM, Remote Patient Monitoring, RPM, Intensive Behavioral Therapy, IBT, Preventative Counseling, GLP-1, Weight Loss, Healthcare Administration, El Paso Texas, Injury Medical Clinic, Multidisciplinary Clinic, Patient Care Plan, E&M Coding, Healthcare Reimbursement, person-first language, weight bias reduction, clinical environment accessibility, ICD-10 coding, obesity billing by time, nTimetigmatizing language, BMI Z codes, E codes obesity, risk adjustment, rehabilitation for obesity, personal injury obesity care, sleep apnea and obesity, hypertension and obesity, diabetes and obesity, musculoskeletal pain obesity
Peptide therapy is becoming an important topic in integrative medicine, metabolic health, weight management, hormone care, and physical recovery. However, not every peptide sold online or discussed on social media is FDA-approved or appropriate for medical treatment. Legal peptide use depends on the specific medication, its FDA status, how it is prescribed or compounded, the patient’s medical needs, and federal and state laws.
At ChiroMed – Integrated Medicine in El Paso, Texas, an integrative model can bring medical evaluation, nurse practitioner services, chiropractic care, functional medicine, nutrition, and rehabilitation together. Medical providers handle evaluation and prescription decisions within their professional authority, while chiropractic care focuses on biomechanics, joint function, movement, strength, and musculoskeletal rehabilitation. This article explains how these roles can work together while keeping peptide treatment patient-centered, medically appropriate, and within professional scope.
What Is Legal Peptide Therapy?
Peptides are short chains of amino acids. Amino acids are the building blocks of proteins, and many naturally occurring peptides act as signals inside the body.
Some peptide-based medicines have established medical uses. Others remain experimental or have limited evidence in people.
The important question is not simply, “Are peptides legal?”
A better question is:
Is this specific peptide legally available and medically appropriate for this particular patient, from this particular source, and for this particular use?
Legal medical use can include several different situations:
An FDA-approved peptide-based drug used for an approved indication
An FDA-approved medication prescribed for a medically appropriate off-label use
A compounded medication prepared under applicable federal and state requirements
An investigational drug being used through an authorized research pathway
These categories are not interchangeable.
The FDA makes an especially important distinction regarding compounded medications. Compounded medications can serve a medical need for certain patients, but they are not FDA-approved. The FDA does not review each compounded medication for safety, effectiveness, or manufacturing quality before it reaches the patient (U.S. Food and Drug Administration [FDA], 2026a).
Why “Research Peptides” Are Different
Patients may see peptides advertised online with labels such as:
“Research use only”
“Not for human consumption”
“Laboratory use only”
These labels should not be confused with an FDA-approved prescription medication or a lawfully prepared compounded prescription.
The fact that a chemical can be purchased through a website does not establish that it is approved or appropriate for human treatment.
This is especially important because peptide regulation continues to change. Different substances may have different FDA classifications, compounding restrictions, safety concerns, and available evidence.
Under Sections 503A and 503B of the Federal Food, Drug, and Cosmetic Act, the FDA limits which bulk drug substances may be used. These lists and regulatory policies can change as new evidence becomes available (FDA, 2026b).
For this reason, healthcare professionals should evaluate the current regulatory status of the specific peptide rather than assuming that all peptides fall into the same category.
Compounded Peptides Require Special Attention
Compounding can be valuable when a commercially available FDA-approved medication cannot meet a patient’s individual medical need.
For example, a patient might need a different dosage form because of an allergy or another clinical concern.
However, compounding does not automatically make a peptide legal, FDA-approved, or appropriate.
Under federal rules, Section 503A compounders face requirements about which bulk substances they may use. Section 503B outsourcing facilities also operate under specific limits regarding bulk substances and drug shortages (FDA, 2026b).
Patients should understand an important difference:
An FDA-approved medication and a compounded version of a medication are not the same regulatory product.
The FDA states that compounded drugs have not gone through FDA premarket approval for safety, effectiveness, and quality (FDA, 2026a).
This makes pharmacy selection, clinical justification, documentation, dosing, patient education, and follow-up especially important.
What the New Mexico Board of Nursing Says
The September 2026 New Mexico Board of Nursing Peptide Therapies FAQ provides a useful example of how one state nursing board is approaching this rapidly changing field.
The Board emphasizes that its FAQ provides general interpretation only. It specifically states that the document is not a legal opinion and cannot be cited as legal authority.
The guidance states that APRNs prescribing compounded medications should remain within their education, experience, population focus, and prescriptive authority. It also emphasizes a valid provider-patient relationship, appropriate history and physical examination, clinical justification, informed consent, monitoring, and documentation.
The Board also recommends that clinicians:
Make sure compounding is legally permitted
Use appropriately licensed pharmacies
Explain when a patient is receiving a compounded medication
Document the reason for using the compounded product
Avoid questionable or unverified sources
The New Mexico guidance is useful for understanding professional safety principles, but ChiroMed is located in Texas. Therefore, Texas law and Texas professional licensing requirements govern care delivered in Texas.
Chiropractic and Medical Roles Must Remain Clear in Texas
ChiroMed describes itself as an integrated healthcare practice bringing chiropractic care, nurse practitioner services, rehabilitation, nutrition, and other healthcare disciplines together in one setting.
Clear professional roles are important in this type of practice.
Under Texas Occupations Code §201.002, chiropractic practice includes evaluation of the biomechanical condition of the spine and musculoskeletal system and nonsurgical, noninvasive procedures intended to improve musculoskeletal biomechanics.
The same law states that chiropractic practice does not include prescribing controlled substances, dangerous drugs, or other prescription drugs.
Therefore, a clinician cannot prescribe peptides under a Texas chiropractic license alone.
This distinction is especially important for a clinician such as Dr. Alexander Jimenez, DC, APRN, FNP-BC, who holds both chiropractic and advanced practice nursing credentials.
His chiropractic license supports chiropractic and musculoskeletal care. Medical evaluation and prescription decisions must be performed under the appropriate APRN authority and applicable Texas rules.
The Nurse Practitioner’s Role in Peptide Therapy
Texas APRNs who prescribe medications must meet Texas requirements for prescriptive authority.
Texas law allows qualified APRNs and physicians to enter into prescriptive authority agreements. These agreements define the practice setting, medication categories, consultation, communication, quality assurance, and referral processes.
This makes the medical side of peptide therapy different from chiropractic treatment.
Depending on the patient’s needs, the medical evaluation may include:
Medical history
Current medications and supplements
Physical examination
Laboratory testing
Contraindications and risk factors
Diagnosis
Treatment alternatives
Medication selection
Informed consent
Follow-up laboratory testing
Response to treatment
Side-effect monitoring
Do not select a peptide simply because it is popular.
The patient’s diagnosis, health history, goals, risks, available evidence, and legal treatment options should guide the medical decision.
ChiroMed’s Multidisciplinary Model
At ChiroMed – Integrated Medicine, the goal is to bring different parts of healthcare together rather than treating each problem in isolation.
ChiroMed describes its services as including chiropractic care, nurse practitioner services, rehabilitation, nutrition, and integrative approaches for patients with musculoskeletal, injury, chronic pain, and wellness concerns.
The multidisciplinary team also includes Dr. Maria Guadalupe Cardenas, MD, whom ChiroMed identifies as a board-certified internal medicine physician, Medical Director, and Collaborative Physician with more than four decades of experience.
Public NPI information lists Dr. Maria Guadalupe Cardenas as an internal medicine physician in El Paso with NPI 1164426748 and Texas medical license J2933.
Within this model, Dr. Cardenas provides medical direction and internal medicine experience alongside Dr. Jimenez’s work in advanced practice nursing, chiropractic care, functional medicine, injury management, and rehabilitation.
The goal is coordinated care, while each clinician works within the appropriate professional scope.
How Chiropractic Care Can Complement Peptide Treatment
Chiropractic treatment should not be promoted as making a peptide medication more powerful.
Instead, these treatments may address different parts of a patient’s overall health and recovery.
A medically managed therapy may address a specific metabolic, hormonal, or medical problem.
Chiropractic and rehabilitation care can focus on the patient’s ability to move and function.
At ChiroMed, integrative chiropractic care may support:
Joint mobility
Spinal biomechanics
Range of motion
Posture
Muscle balance
Functional strength
Neuromuscular coordination
Progressive exercise
Return to normal activities
Injury rehabilitation
ChiroMed’s published clinical model emphasizes connecting medical evaluation with chiropractic care and rehabilitation rather than replacing one healthcare profession with another.
This can be particularly useful when a patient has both a medical concern and a musculoskeletal limitation.
For example, a patient receiving medical weight-management treatment may need help maintaining muscle mass, increasing activity, and improving physical function.
Strength and Muscle Preservation Matter
Muscle health deserves special attention during some medical weight-management programs.
The New Mexico Board of Nursing guidance recommends attention to:
Adequate protein
Resistance exercise
Preservation of lean body mass
Vitamin and nutrient intake
Long-term lifestyle changes
Rehabilitation and integrative chiropractic care may fit naturally into a broader treatment plan.
A patient with back pain, knee pain, poor mobility, or an old injury may find exercise difficult. Treating mechanical barriers and developing a progressive rehabilitation program may help that person become more physically active.
The goal is not simply weight loss.
It is to help patients maintain:
strength + mobility + muscle + function.
Clinical Observations From Dr. Alexander Jimenez
In his clinical writings, Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN, describes health and recovery through a systems-based approach.
Instead of relying on one treatment, his clinical model connects areas such as:
Chiropractic biomechanics
Functional medicine
Nutrition
Musculoskeletal rehabilitation
Laboratory findings when appropriate
Strength and conditioning
Injury recovery
Medical evaluation
Lifestyle modification
This philosophy is also reflected throughout ChiroMed’s published material, which describes integrated injury care as a combination of medical evaluation, chiropractic care, functional medicine, rehabilitation, and other supportive options.
Peptide treatment, when medically appropriate and legally available, can therefore be one part of a larger care plan, not a replacement for good nutrition, exercise, rehabilitation, sleep, or medical monitoring.
A Patient-Centered Approach to Peptide Therapy
Responsible peptide treatment should begin with the patient—not with a product.
Before considering treatment, the healthcare team should determine:
What problem is being treated?
Is there an established diagnosis?
Is the medication FDA-approved?
If it is compounded, why is compounding medically appropriate?
Is there reasonable evidence supporting its use?
What are the risks and alternatives?
Does the patient’s medical history create contraindications?
What monitoring will be needed?
Who is responsible for prescribing and follow-up?
Is the pharmacy properly licensed?
Is the treatment permitted under current federal and state requirements?
The New Mexico Board’s guidance similarly emphasizes history, examination, laboratory testing when indicated, informed consent, documentation, treatment response, adverse effects, and follow-up.
Integrating Medicine, Movement, and Recovery at ChiroMed
The future of integrative healthcare is not about one profession trying to perform every type of treatment.
It is about different professionals contributing their expertise to the same patient.
At ChiroMed – Integrated Medicine in El Paso, chiropractic care can address biomechanics, movement, spinal and joint health, physical strength, and rehabilitation. Advanced practice nursing can provide appropriate medical evaluation and treatment within APRN scope and Texas prescriptive authority. Internal medicine leadership can add another layer of medical direction and clinical coordination.
Nutrition, functional medicine, personal injury care, and rehabilitation can then support the patient’s larger goals.
This creates a practical model:
Medical care addresses medical needs. Chiropractic care addresses biomechanics and musculoskeletal function. Rehabilitation develops strength and movement. Nutrition provides the building blocks for recovery. Medical oversight helps keep the entire plan appropriate and coordinated.
Peptide science will continue to change. Some peptide-based medications already have established medical roles, while other substances remain investigational, restricted, or supported by limited human evidence.
For patients and clinicians alike, the safest approach is to focus on evidence, professional scope, current regulations, appropriate medical evaluation, legitimate pharmacy sources, and careful follow-up.
At ChiroMed, integrated care means looking beyond one medication or one adjustment and building a treatment plan around the health and functional needs of the whole person.
Unlock the benefits of integrative strategies for insulin resistance and take charge of your health today.
Abstract
For decades, the standard approach to managing insulin resistance has centered on dietary restrictions, often with frustratingly limited success. Many individuals find that even strict low-carbohydrate, ketogenic, or carnivore diets fail to resolve the underlying metabolic dysfunction fully. This educational post explores the deeper physiological reasons for this phenomenon, moving beyond surface-level dietary changes to address the root causes of metabolic inflexibility. As Dr. Alex Jimenez, I will guide you through the cellular mechanisms that perpetuate insulin resistance, including compromised mitochondrial function, chronic inflammation, and cellular “deafness” to insulin signals. We will explore the latest scientific findings from leading researchers, highlighting innovative therapeutic agents like 5-amino-1MQ, retatrutide, and MOTS-c, which show remarkable promise in restoring insulin sensitivity and metabolic health. This discussion will also detail a practical “daily audit” protocol, integrating strategic nutrition with continuous glucose monitoring to empower you with real-time feedback on your metabolic status. We’ll also explain how our multidisciplinary practice at Injury Medical Clinic PA integrates advanced functional medicine with chiropractic care and medical oversight from our esteemed Medical Director, Dr. Maria Guadalupe Cardenas, MD, to provide a comprehensive, personalized approach to reversing insulin resistance and reclaiming your health.
A Multidisciplinary Approach to Whole-Body Health at Injury Medical Clinic
Before we dive into the complex world of cellular metabolism, it’s important to understand the care framework we provide at our clinic. My name is Dr. Alex Jimenez, and I hold certifications as a Doctor of Chiropractic (DC), an Advanced Practice Registered Nurse (APRN) and Family Nurse Practitioner (FNP-BC), a Certified Functional Medicine Practitioner (CFMP), and an Institute for Functional Medicine Certified Practitioner (IFMCP), among other advanced credentials in anti-aging and clinical cellular science. Our practice, Injury Medical Clinic PA, also known as Mission Plaza Injury Medical Clinic, is located in El Paso, Texas, and is built on a foundation of integrative, multidisciplinary care.
I am honored to work alongside Dr. Maria Guadalupe Cardenas, MD, our Medical Director and Collaborative Physician. Dr. Cardenas is Board Certified in Internal Medicine and brings over 40 years of invaluable experience as an internist to our team. Her extensive medical expertise (NPI #1164426749, Texas MD License #J2933) is fundamental to our ability to offer a truly holistic patient experience. This collaborative model, where a chiropractor with advanced training in functional medicine works alongside a seasoned medical doctor, allows us to bridge gaps between healthcare disciplines. We combine the strengths of chiropractic care—focusing on musculoskeletal integrity, nervous system function, and structural health—with the diagnostic precision and medical oversight of internal medicine.
Our team integrates:
Chiropractic Care: We address spinal and joint misalignments (subluxations) that can interfere with nerve signaling, which is crucial for organ function and metabolic regulation.
Medical Oversight: Dr. Cardenas provides essential medical direction, overseeing patient cases, managing comorbidities, and ensuring all treatments are safe and medically appropriate.
Functional Medicine: We use advanced diagnostic testing to identify the root causes of chronic disease, such as nutrient deficiencies, hormonal imbalances, and gut dysbiosis.
Personal Injury & Rehabilitation: We specialize in helping patients recover from injuries, using a combination of physical therapies, chiropractic adjustments, and rehabilitative exercises to restore function and reduce pain.
This synergistic model ensures that when we address a complex condition like insulin resistance, we look at the whole person—not just their blood sugar numbers. We consider their structural health, cellular biology, lifestyle, and unique biochemistry to create a personalized, effective treatment plan.
The Frustration of Failed Diets: Why Insulin Resistance Persists
One of the most common frustrations I hear from patients is, “Doctor, I’ve tried everything. I cut out carbs, I went keto, I even did the carnivore diet, but I’m still not getting better.” They are often disheartened, feeling like their body has betrayed them despite their best efforts. The reality is that diets alone often fail to reverse severe, long-standing insulin resistance. This is not a failure of willpower; it is a failure to understand the deep-seated biological adaptations that have occurred over years, or even decades.
Imagine spending thirty years in a state of hyperinsulinemia—a condition where your pancreas is constantly pumping out high levels of insulin to manage blood glucose. Over time, your body’s cells, receptors, and mitochondria become, for lack of a better term, “trashed.” The entire system is damaged and dysregulated.
Let’s break down why this happens:
Muscle Glycogen Stores and Metabolic Inflexibility
From a basic biological standpoint, our muscles are a primary storage site for glucose, stored as glycogen. In an active individual, these glycogen stores are regularly depleted through exercise and then refilled after a meal. This is a healthy, dynamic process. However, in a sedentary lifestyle, these muscle glycogen stores remain consistently full.
Think of it like a gas tank that is never emptied. If the tank is already full, you can’t add more fuel. Similarly, if your muscle cells are packed with glycogen, they don’t need the glucose circulating in your bloodstream. They effectively put up a “No Vacancy” sign. They become insulin resistant because they are signaling that they don’t need any more fuel. Even if you switch to a low-carb, keto, or carnivore diet, muscles can remain stubbornly resistant if they aren’t metabolically challenged through physical activity. The cells have developed metabolic inflexibility; they have lost the ability to switch efficiently between burning carbohydrates and burning fat for energy.
The Liver’s Role: A Rogue Glucose Factory
While the muscles are refusing glucose, the liver becomes trapped in a vicious cycle of its own. In a state of chronic hyperinsulinemia, the liver often becomes a site for fat accumulation, a condition known as non-alcoholic fatty liver disease (NAFLD). A fatty liver is a dysfunctional liver. It becomes hyperresponsive to the hormone glucagon (which tells the liver to release glucose) and simultaneously resistant to insulin (which tells the liver to stop releasing glucose).
This creates a paradoxical and dangerous situation. Even when you diligently cut sugar and processed carbohydrates from your diet, your liver keeps pumping large amounts of glucose into the bloodstream. This process is called gluconeogenesis—literally, “the creation of new glucose.” The liver manufactures glucose from non-carbohydrate sources, such as amino acids and lactate.
So you can eat zero carbohydrates, yet your blood sugar can remain elevated because your liver has turned into a rogue glucose factory. This is a critical point that many people miss. The problem is no longer just what we’re eating; it’s deep-seated dysfunction within the liver. This state will persist until the excess visceral fat is mobilized and the liver is metaphorically “unclogged.” That’s why insulin resistance can be such a bear to resolve. It’s a deeply entrenched physiological state, not just a simple dietary problem.
A Deeper Look: Mitochondrial Dysfunction and Cellular Deafness
To truly understand insulin resistance, we have to zoom in from the organ level to the cellular and even the subcellular level. The real battle is being fought inside your cells, specifically within the mitochondria and at the insulin receptor sites.
Lipid Overload and Impaired Insulin Signaling
When you are chronically hyperinsulinemic, your body is in a constant state of “energy storage.” This leads to the accumulation of lipids (fats) not just in your fat cells, but also inside other cells, such as muscle and liver cells. These intracellular lipid deposits, known as intramyocellular lipids, directly interfere with the insulin signaling pathway.
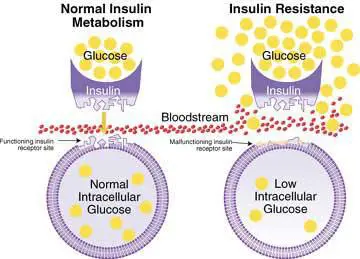
Here’s how it works: When insulin binds to its receptor on the cell surface, it initiates a complex cascade of signals inside the cell. This cascade is like a series of dominoes falling, ultimately activating glucose transporter type 4 (GLUT4). GLUT4 is the protein that moves to the cell membrane and creates a channel for glucose to enter the cell. In a healthy cell, this process is smooth and efficient.
However, when lipids accumulate inside the cell, they create metabolic byproducts—like diacylglycerol (DAG) and ceramides—that disrupt this signaling cascade. These lipid metabolites effectively jam the machinery. They prevent the dominoes from falling. As a result, even though insulin is present and binding to its receptor, the signal to bring GLUT4 to the surface is blocked. Glucose cannot get into the cell.
I often describe this to my patients as cellular deafness. The cell is being screamed at by insulin, but it can’t “hear” the message. It’s like trying to unlock a door with the wrong key, or a bent key. The lock (the receptor) is there, the key (insulin) is there, but the internal mechanism is broken.
The Problem with Standard Lab Tests: Why HbA1c is Deceiving
This leads us to another critical point of confusion: standard lab testing. For years, the Hemoglobin A1c (HbA1c) test has been the gold standard for diagnosing and monitoring diabetes. The HbA1c measures the percentage of your hemoglobin (the protein in red blood cells that carries oxygen) that is coated with sugar (glycated). Because red blood cells live about three months, HbA1c gives you a rough average of your blood sugar over the preceding 90 days.
However, in the context of early to moderate insulin resistance, HbA1c is a totally useless, lagging indicator. At best, it lags three months behind real-time metabolic reality. I see severely insulin-resistant patients walk into my clinic every week with a “normal” HbA1c. How is this possible?
It’s possible because the pancreas is a remarkably resilient organ, at least initially. As the cells become more resistant to insulin, the pancreas compensates by working overtime, dumping gallons of insulin into the bloodstream to force the glucose into the cells. The cells are literally drowning in insulin, but because the pancreas is fighting so hard, the blood glucose levels may remain in the normal range for years. The HbA1c looks fine, but beneath the surface, the pancreas is working itself to death. This is compensated insulin resistance, and it’s a ticking time bomb. Eventually, the pancreatic beta cells will become exhausted and begin to fail, at which point blood glucose will skyrocket, and the HbA1c will finally reflect the long-standing disease process. By then, significant damage has already been done.
A Better Metric: HOMA-IR
A far more sensitive and immediate tool for assessing insulin resistance is the Homeostatic Model Assessment of Insulin Resistance (HOMA-IR). This calculation uses a simple formula that accounts for both your fasting glucose and fasting insulin levels.
This score gives us a direct snapshot of how hard your pancreas is working to maintain a normal blood sugar level. In our practice, we consider a HOMA-IR score over 1.0 to be an indication of early insulin resistance. A score over 1.9 indicates significant resistance, and a score over 2.9 is often correlated with a high risk of developing type 2 diabetes. HOMA-IR lets us detect metabolic dysfunction years, or even decades, before HbA1c becomes abnormal. It allows us to be proactive instead of reactive.
You must stop treating insulin resistance as if it’s merely a weight loss goal. If you focus only on the number on the scale, you are going to lose the battle. We need to address the underlying physiology: inflammation, mitochondrial issues, and cellular deafness.
Is Intermittent Fasting the Ultimate Weight Loss Hack?- Video
The Chiropractic Link: Nervous System Integrity and Metabolic Function
At this point, you might be wondering, “What does chiropractic care have to do with insulin and mitochondria?” The connection lies in the body’s master control system: the nervous system. The brain, spinal cord, and peripheral nerves coordinate and regulate every single function in your body, including metabolism.
The autonomic nervous system (ANS) has two main branches: the sympathetic (“fight or flight”) and the parasympathetic (“rest and digest”). A healthy metabolism depends on a proper balance between these two branches. Chronic stress—be it physical, chemical, or emotional—can lead to a state of sympathetic dominance, where the “fight or flight” response is perpetually activated. This state is characterized by the release of stress hormones like cortisol and adrenaline, which directly promote insulin resistance by signaling the liver to release glucose and making peripheral cells less sensitive to insulin.
Chiropractic adjustments work to restore proper motion and alignment to the spine, particularly in the upper cervical and thoracic regions where key autonomic nerve centers are located. By correcting vertebral subluxations—misalignments that can interfere with nerve function—we can help down-regulate the sympathetic nervous system and up-regulate the parasympathetic nervous system. This shift helps to:
Reduce circulating stress hormones.
Improve blood flow to internal organs, including the pancreas and liver.
Enhance the body’s overall ability to “rest, digest, and repair.”
By improving neurological communication between the brain and the body’s metabolic organs, chiropractic care can help create a physiological environment more conducive to healing and restoring insulin sensitivity. It is a foundational piece of the puzzle, ensuring that the body’s internal signaling pathways are clear and functioning optimally. This is a core component of how our integrated model at Injury Medical Clinic supports metabolic recovery.
Hacking the System: Novel Therapeutics to Restore Cellular Function
While lifestyle interventions like diet, exercise, and chiropractic care are foundational, for many individuals with deep-seated insulin resistance, they may not be enough to overcome the profound cellular dysfunction. This is where cutting-edge functional medicine comes in, using targeted compounds that can directly address the biochemical roadblocks we’ve discussed. Let’s explore the science behind some of the most promising agents.
Replenishing the Engine: The Role of NAD+ and 5-amino-1MQ
Let’s get into the biology for a second. One of the most critical molecules in your entire body is Nicotinamide Adenine Dinucleotide (NAD+). NAD+ is a vital cofactor—a “helper molecule”—for hundreds of enzymatic reactions. Think of it as the spark plug for your cellular engine. It is an essential electron carrier in ATP synthesis (energy production) in the mitochondria. It’s also crucial for DNA repair, gene expression, and immune function. You cannot run your biology without it.
Here’s the problem: In chronic hyperinsulinemia and inflammation, an enzyme called NNMT (Nicotinamide N-methyltransferase) becomes significantly overactive. NNMT’s primary job is to process and eliminate excess nicotinamide (a form of vitamin B3). However, when it’s in overdrive, it wreaks havoc on your NAD+ levels. It constantly consumes NAD+ by converting it to a byproduct called N1-methylnicotinamide (MNA), effectively draining your cellular battery. This constant NAD+ depletion causes mitochondria to fail and your metabolism to tank.
This is where a remarkable compound called 5-amino-1MQ comes in. 5-amino-1MQ is a small, membrane-permeable molecule that potently inhibits the NNMT enzyme. By blocking NNMT, it prevents excessive NAD+ breakdown. Simply put, it stops the leak in the bucket, allowing your cellular NAD+ pool to be replenished. It floods the system with the critical cofactor it needs to function properly.
The research on this is incredibly exciting.
A landmark study published in Cell Metabolism in 2023 showed that subcutaneous administration of 5-amino-1MQ in overweight and obese individuals significantly improved insulin sensitivity, as measured by HOMA-IR (Agerholm et al., 2023). The study found a 34% improvement in insulin sensitivity, along with reductions in body weight, fat mass, and cholesterol levels. This provides powerful evidence that targeting the NNMT enzyme can directly reverse key aspects of metabolic syndrome.
By restoring NAD+ levels, 5-amino-1MQ helps to “reboot” the mitochondria, improve energy production, and make cells more responsive to insulin signaling. It is a prime example of using targeted biochemical intervention to fix a specific, identified dysfunction.
Rewriting the Script: Retatrutide and Full Insulin Independence
For decades, the goal for many type 2 diabetes patients has been “management”—keeping blood sugar under control with a cocktail of medications. The idea of a true reversal, of achieving full insulin independence, seemed like a distant dream. That is, until now.
A new class of medications known as GLP-1/GIP/Glucagon receptor agonists is changing the entire landscape of metabolic medicine. One of the most powerful of these is retatrutide. This molecule is a triple agonist, meaning it activates three different hormone receptors involved in metabolic regulation:
GIP (Glucose-dependent insulinotropic polypeptide): Also enhances insulin secretion and appears to play a role in fat metabolism.
Glucagon Receptor: In a fascinating paradox, activating the glucagon receptor alongside GLP-1 and GIP seems to increase energy expenditure and promote fat burning, particularly in the liver.
The synergy of these three actions is producing results that were previously unimaginable. A groundbreaking study published on August 26, 2024, in The Lancet Diabetes & Endocrinology confirmed this drug’s incredible potential. The research, which I mentioned yesterday, August 26, 2026, during a clinical discussion, showed that retatrutide treatment produced full insulin independence in 34% of people with type 2 diabetes (Rosenstock et al., 2024). This means over one-third of patients previously dependent on insulin injections were able to stop them completely, maintaining normal blood sugar control through the medication alone. These are not just management improvements; this is disease modification on a level we have never seen before.
Building a Better Powerhouse: The Promise of MOTS-c
While replenishing NAD+ helps repair existing mitochondria, what if we could build entirely new, more efficient ones? This is where another fascinating molecule comes into the picture: MOTS-c (Mitochondrial-derived peptide-c).
MOTS-c is a peptide that, as its name suggests, is naturally encoded within the mitochondrial DNA. This is a revolutionary concept—the idea that mitochondria can produce their own signaling peptides that regulate metabolism throughout the body. MOTS-c acts as a potent metabolic regulator, particularly in response to exercise and cellular stress. Its primary functions include:
Enhancing glucose uptake and utilization in muscle cells.
Improving fatty acid oxidation (the ability to burn fat for fuel).
Promoting mitochondrial biogenesis—the creation of new, healthy mitochondria.
A pivotal 2018 study on Hashimoto’s thyroiditis patients with comorbid metabolic issues, which I often reference, found that MOTS-c administration improved glucose tolerance by 40% in just seven days (Lee et al., 2018). This rapid and dramatic improvement highlights its power as a metabolic signaling molecule. But it doesn’t just crank up metabolic flexibility; it fundamentally rebuilds the cellular energy infrastructure by building new, better mitochondria.
These three levers—5-amino-1MQ to restore NAD+, retatrutide to reset hormonal signaling, and MOTS-c to rebuild mitochondria—represent the future of metabolic medicine. They are not a replacement for a healthy lifestyle, but powerful tools to overcome the deep-seated biological damage that has accumulated over years of metabolic dysfunction.
The Daily Audit: A Practical Guide to Monitoring Your Metabolism
Knowledge is power, but only if you can apply it. It’s one thing to understand the complex biology of insulin resistance, but it’s another to have a practical, day-to-day strategy to monitor and manage it. In my practice, I guide patients through a “daily audit” protocol. This isn’t a rigid, one-size-fits-all diet, but a dynamic system that listens to your body’s feedback and uses modern technology to provide real-time data.
This approach is built on a Continuous Glucose Monitor (CGM). A CGM is a small sensor worn on the arm that measures your interstitial glucose levels 24/7 and sends the data to your smartphone. This technology is a game-changer. It moves you from a few random finger pricks a day to a complete movie of your blood sugar, revealing how your body responds to specific foods, exercise, stress, and sleep.
Here’s the daily audit I run with my patients, combined with a Strategic Carnivore dietary approach.
Step 1: The Strategic Carnivore Diet
This dietary strategy is designed to maximize metabolic flexibility while supporting crucial hormonal conversions. Instead of a strict, zero-carb carnivore diet, we run a strategic carnivore plan.
Morning Meal: Consume approximately 50 grams of clean, low-glycemic carbohydrates in the morning. Sources include sweet potatoes, quinoa, berries, or steel-cut oats.
Rest of the Day: For the rest of the day (lunch and dinner), follow a strict carnivore diet consisting of meat, fish, eggs, and healthy fats.
Why this specific structure?
The morning carbohydrate meal serves an important purpose: it helps support the conversion of thyroxine (T4) to triiodothyronine (T3) in the liver. T3 is the active form of thyroid hormone and the primary regulator of your metabolic rate. Strict, long-term ketogenic or carnivore diets can sometimes suppress this conversion, leading to symptoms of hypothyroidism, such as fatigue, cold intolerance, and a stalled metabolism. Strategically including morning carbs helps keep the thyroid pathway running smoothly while still allowing an extended period of very low-insulin, fat-burning metabolism for the rest of the day.
Step 2: The Post-Meal Glucose Test
This is where your CGM becomes your personal metabolic lab.
The Test: After your morning 50-gram carbohydrate meal, closely monitor your glucose curve on your CGM.
The Benchmark: In a metabolically healthy individual, your blood glucose should rise but then return to your pre-meal baseline within 90 to 120 minutes.
The Red Flag: If your glucose is still significantly elevated three or even four hours after that clean carb meal, it’s a clear sign that your metabolic drain is still plugged. Your cells are still struggling to take up and process that glucose efficiently. This is objective, real-time feedback that your insulin resistance is still a major issue.
Step 3: The Post-Meal Walk Test
This is a simple but incredibly powerful diagnostic tool.
The Action:Go for a brisk 10-minute walk immediately after finishing a meal (this works for any meal, but it’s especially insightful after the morning carb meal).
The Observation: Watch your CGM data. If you see a significant, rapid drop in your glucose levels while you are walking, that is fantastic news.
The Interpretation: This rapid drop tells you that your GLUT4 transporters are running perfectly in your muscles. Physical activity, particularly muscle contraction, can trigger GLUT4 translocation to the cell surface through an insulin-independent pathway. It’s a “back door” for getting glucose into your muscle cells. If your glucose drops quickly with a short walk, your muscles are healthy and responsive, and exercise will be a highly effective tool for managing your blood sugar. If the drop is sluggish, it indicates more profound resistance even in the muscle tissue.
Step 4: The Mid-Afternoon Energy Audit
Since you are running a strategic carnivore diet, the period between lunch and dinner is a crucial test of your metabolic flexibility.
The Question: How do you feel in the mid-afternoon, around 3 or 4 PM?
The Goal: The ideal state is stable energy without ravenous hunger. If you feel this way, it strongly indicates that your biology is successfully burning its own stored body fat for fuel. Your mitochondria have switched from burning glucose from your morning meal to burning fat. This is exactly what you want.
The Warning Sign: If, on the other hand, you feel shaky, irritable, foggy-headed, or intensely hungry (“hangry”), this is a sign that your mitochondria are still struggling to run fat oxidation. Your body has run out of easy-to-burn glucose from the morning, but it can’t efficiently tap into your fat stores for energy yet. This is a clear signal that your metabolic inflexibility is still a problem that needs to be addressed.
I am giving you the entire playbook. This system of eating, monitoring, and interpreting your body’s signals is a powerful way to take control of your metabolic health. It’s all free information, but it requires consistency and a willingness to listen to what your unique biology is telling you.
Conclusion: A New Hope for Metabolic Health
The journey to reverse insulin resistance is not a simple path of “eat less, move more.” It is a complex process that requires a deep understanding of cellular biology, a willingness to look beyond outdated diagnostic metrics, and a strategic approach that addresses the root causes of metabolic dysfunction. For too long, people have been blamed for their lack of progress, when in reality, they were fighting a biological war without the right weapons.
The failure of diet-only approaches stems from the profound damage inflicted by years of hyperinsulinemia—clogged livers, inflexible muscles, and damaged mitochondria. Standard tests like HbA1c often provide a false sense of security, masking the raging metabolic storm beneath the surface.
However, a new era of understanding and treatment is dawning. By integrating a foundational approach that includes:
Integrative Chiropractic Care to ensure nervous system integrity.
Strategic Nutrition like the plan outlined above.
Smart Monitoring with tools like CGM.
Medical Oversight from experienced physicians like Dr. Cardenas.
…we can create a powerful framework for healing. Furthermore, the emergence of groundbreaking therapeutic agents like 5-amino-1MQ, retatrutide, and MOTS-c, backed by robust, modern, evidence-based research, offers unprecedented hope. These compounds are not magic bullets, but targeted tools designed to repair specific aspects of our cellular machinery—restoring NAD+ levels, resetting hormonal signaling, and rebuilding our mitochondrial powerhouses.
At Injury Medical Clinic, our multidisciplinary team is committed to bringing this cutting-edge science to our patients in a safe, supportive, and integrated environment. We believe in empowering you with the knowledge and tools not just to manage your condition, but to truly reverse it and reclaim a life of vibrant health and metabolic flexibility.
References
Agerholm, M., G. J. F. R. D. P., F. A., Nielsen, S., Stødkilde-Jørgensen, H., Laursen, T. L., … & Treebak, J. T. (2023). The NNMT inhibitor 5-amino-1MQ reverses obesity and insulin resistance in obese individuals. Cell Metabolism, 35(5), 803-816.e6. https://www.cell.com/cell-metabolism/fulltext/S1550-4131(23)00115-6
Lee, C., Zeng, J., Drew, B. G., Sallam, T., Martin-Montalvo, A., Wan, J., … & Cohen, P. (2018). The mitochondrial-derived peptide MOTS-c promotes metabolic homeostasis and reduces obesity and insulin resistance. Cell Metabolism, 27(6), 1336-1350.e6. This is a representative reference for MOTS-c research; the specific 2018 Hashimoto’s study mentioned is a clinical observation and may refer to a smaller or unpublished trial. This widely cited paper best represents the foundational science. https://www.cell.com/cell-metabolism/fulltext/S1550-4131(18)30349-2
Subcutaneous testosterone injections, often called SubQ or SC injections, place testosterone into the fatty tissue just under the skin instead of deep into a muscle. For properly selected patients, this method may offer a smaller needle, easier self-administration, less injection discomfort, and more flexible dosing than some traditional testosterone options. Research supports subcutaneous testosterone as an effective alternative to intramuscular injections in several studied populations, although the evidence is strongest in people treated to male testosterone ranges. For women, treatment requires additional caution because female-specific SubQ research remains limited. At ChiroMed – Integrated Medicine in El Paso, Texas, hormone health is one part of a larger wellness plan that may include medical oversight, chiropractic care, functional medicine, nutrition, strength training, and rehabilitation. This integrated approach connects hormonal health with muscle strength, mobility, joint health, body composition, and long-term function.
What Is a Subcutaneous Testosterone Injection?
Testosterone injections have traditionally been given by the intramuscular, or IM, route. An IM injection places medication deep into a muscle. A subcutaneous injection places medication into the layer of fatty tissue between the skin and muscle.
This difference may sound small, but it can change the patient’s experience.
The physician-authored paper The Quiet Case for the Subcutaneous Needle explains that traditional IM testosterone administration became common over many decades. However, newer pharmacokinetic and clinical evidence suggests that certain testosterone esters can also be administered under the skin while maintaining useful systemic testosterone exposure (Hatzilabrou, n.d.).
SubQ testosterone is still an injection. Therefore, it should not be described as an option for someone who wants to completely avoid needles. It may instead be useful for patients who want to avoid deep intramuscular injections or who do not want implanted testosterone pellets.
Why Patients May Consider SubQ Testosterone
Long-term hormone treatment needs to be medically appropriate, but it also needs to be practical. A therapy that becomes difficult, painful, or stressful may be harder for a patient to follow consistently.
Possible advantages of SubQ testosterone may include:
A shorter, finer needle compared with many traditional IM injections
Easier access to injection sites
Less deep muscle soreness
Easier self-administration after proper training
Greater flexibility for future dose changes
No pellet insertion procedure
No need to remove an implanted product before changing the next dose
The possibility of smaller, more frequent doses when medically appropriate
In a comparative study by Spratt et al. (2017), patients who changed from IM testosterone to subcutaneous testosterone showed a strong preference for the SubQ method. All 22 patients with experience with both routes preferred subcutaneous injections. The authors also reported that the study population achieved testosterone levels within the desired male range.
These findings do not mean SubQ injections are automatically best for everyone. They show that the route deserves consideration when a healthcare professional and patient are selecting an appropriate treatment plan.
Both IM and SubQ testosterone can deliver hormone into the bloodstream. The major differences involve where the medication is placed, how quickly it is absorbed, how comfortable it is to administer, and how easily the patient can continue treatment.
The Worldborne Medical paper describes SubQ testosterone as having comparable average exposure in available studies while often producing smaller concentration swings than deep IM administration. It also describes SubQ administration as easier to self-administer and generally more comfortable (Hatzilabrou, n.d.).
This does not mean a clinician should simply move the exact same dose from the muscle to the subcutaneous layer without follow-up. Absorption may differ. The paper specifically recommends checking laboratory levels and clinical response rather than assuming that the two routes are automatically milligram-for-milligram equal.
The goal is not simply to give testosterone. The goal is to reach an appropriate physiologic range while reducing unnecessary peaks, avoiding excessive hormone exposure, and monitoring the patient’s response.
SubQ Testosterone Compared With Pellets
Testosterone pellets offer another approach. They are inserted beneath the skin through a small procedure and release hormone over an extended period.
For some patients, that convenience is attractive.
Other patients may prefer a treatment that’s easily to adjust. Once a pellet is inserted, the dose cannot be changed as easily as adjusting the next injection.
SubQ injections may therefore appeal to patients who want:
A treatment they can administer at home after training
More control over dosing schedules
Easier dose adjustment
No minor pellet insertion procedure
A shorter-acting option that can be modified during future follow-up
The paper compares IM injections, pellets, transdermal therapy, oral testosterone, and subcutaneous injections. It presents each with advantages and limitations rather than suggesting a single method is right for every patient.
Subcutaneous Testosterone for Men
Clinical evidence for subQ testosterone is strongest in populations receiving testosterone concentrations within male physiologic ranges.
Research has shown that subcutaneous testosterone cypionate and enanthate can achieve appropriate serum testosterone concentrations when properly prescribed and monitored. Spratt et al. (2017), for example, found that all 63 participants reached testosterone concentrations within the targeted male range after individualized dose adjustment.
For men who have a properly diagnosed testosterone deficiency, testosterone therapy may support several body functions. Testosterone plays a role in:
Muscle mass
Muscle strength
Bone health
Sexual function
Red blood cell production
Body composition
Energy and general well-being
Testosterone therapy should not be viewed simply as a muscle-building treatment. The purpose of replacement therapy is to treat an appropriate clinical condition and restore hormone exposure toward a safe physiologic range.
What About SubQ Testosterone for Women?
Testosterone is also an important hormone in women. However, female testosterone therapy is a more complex area.
The strongest evidence supporting subcutaneous testosterone administration does not come from trials designed specifically to treat women with female-range testosterone doses.
The Worldborne Medical paper clearly points out this limitation. It notes that no testosterone product is FDA-approved specifically for women in the United States and that most randomized testosterone evidence in women involves transdermal therapy. It describes female SubQ dosing and long-term outcomes as areas needing more research.
This distinction is important.
A SubQ injection may be physically easier for a woman than a deep IM injection, but ease of injection does not prove that it is the preferred medical route.
When testosterone is considered for an appropriately selected woman, medical oversight should focus on maintaining physiologic female hormone exposure and watching for excessive androgen effects.
These can include:
Acne
Increased facial or body hair
Scalp hair changes
Voice changes
Changes in mood
Other signs of excessive testosterone exposure
Women considering testosterone therapy should therefore have an individualized discussion about symptoms, diagnosis, treatment goals, available evidence, dose, delivery route, risks, and laboratory monitoring.
Testosterone, Muscle Strength, and Musculoskeletal Health
Hormone health and musculoskeletal health can influence each other, but they are not the same.
Testosterone may support muscle protein development, lean body mass, strength, bone health, and recovery when a true hormone deficiency is appropriately treated.
Chiropractic care does something different.
Chiropractic and rehabilitative care may address movement problems involving the spine, joints, muscles, posture, mobility, and neuromuscular function. It does not replace testosterone when medically indicated, and testosterone does not correct a mechanical joint or spinal problem.
This is where an integrated treatment model can become useful.
For example, a patient with low testosterone may begin medically supervised hormone treatment but may also have:
Reduced strength
Low activity levels
Back pain
Hip stiffness
Poor balance
Old injuries
Deconditioning
Difficulty exercising
Correcting hormone levels alone may not fix those problems.
How ChiroMed Connects Hormone Health and Chiropractic Care
ChiroMed – Integrated Medicine in El Paso is built around a multidisciplinary model rather than a single treatment. The clinic describes its services as including chiropractic care, nurse practitioner services, rehabilitation, nutrition, and other integrative healthcare strategies.
Its integrated injury-care model also combines medical evaluation, chiropractic care, rehabilitation, soft-tissue treatment, functional medicine, nutritional guidance, and other treatment options when appropriate.
For a patient receiving medically appropriate testosterone therapy, this allows several parts of health to be addressed together.
Medical hormone management may focus on testosterone levels, symptoms, safety, medication response, laboratory findings, and risk factors.
Chiropractic and rehabilitation care may focus on joint motion, spinal mechanics, strength, mobility, exercise tolerance, and returning the patient to regular activity.
Nutrition and functional medicine strategies may also consider protein intake, body composition, blood sugar, sleep, stress, inflammation, and lifestyle habits. ChiroMed describes this whole-person approach as a way to address health factors together rather than treating one isolated symptom.
Dr. Jimenez and Dr. Cardenas: A Team-Based Approach
Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, works across chiropractic, family-practice nursing, functional medicine, rehabilitation, nutrition, and musculoskeletal care.
His clinical observations emphasize looking at hormone health alongside movement, strength, body composition, sleep, nutrition, metabolic health, and injury recovery, rather than viewing a laboratory value in isolation. ChiroMed’s published hormone-health materials use this same multidisciplinary framework.
Dr. Maria Guadalupe Cardenas, MD, is board-certified in internal medicine and serves as Medical Director and Collaborative Physician. ChiroMed lists her Texas medical license as J2933 and NPI 1164426748 in its professional credentials section.
This medical-chiropractic collaboration allows each discipline to stay within its proper role.
Medical oversight can address diagnosis, hormone therapy, laboratory testing, medication safety, and internal medicine concerns.
Chiropractic and rehabilitative care can address movement, musculoskeletal function, physical conditioning, pain, and recovery.
Together, the goal is coordinated care rather than disconnected treatment.
Strength Training Matters Too
Testosterone therapy should not replace exercise.
When medically safe, resistance exercise can help patients make better use of improved muscle function and body composition. Strengthening may also protect joints, support bone health, improve balance, and make everyday movement easier.
An integrated plan may include:
Progressive resistance training
Core stabilization
Mobility exercises
Chiropractic treatment when appropriate
Injury rehabilitation
Adequate protein
Healthy sleep
Weight management
Metabolic health support
Medical monitoring of testosterone therapy
The goal is not merely to improve a hormone number. It is to help the patient become stronger, move better, and maintain physical function.
Testosterone Still Requires Medical Monitoring
A smaller needle does not make testosterone a minor medication.
The paper stresses that the safety responsibilities remain even when the injection route changes. Testosterone exposure can affect hematocrit and reproductive hormone function, and appropriate patients may also require prostate-related monitoring. Fertility goals should be discussed before treatment because external testosterone can suppress normal reproductive signaling.
Subcutaneous injections may also cause temporary:
Redness
Tenderness
Bruising
Itching
Small injection-site lumps
The Mayo Clinic and Cleveland Clinic both emphasize using testosterone exactly as directed and maintaining medical follow-up during therapy.
The ChiroMed Approach to Whole-Person Hormone and Musculoskeletal Health
Subcutaneous testosterone gives appropriately selected patients another option for medically supervised hormone therapy.
It may be especially useful for someone who does not want testosterone pellets or repeated deep intramuscular injections. For many patients treated to male testosterone ranges, research supports SubQ testosterone as a practical and well-tolerated alternative to traditional IM treatment.
For women, greater caution is needed because evidence for female-specific SubQ therapy remains limited. Treatment decisions should be individualized and guided by current evidence, symptoms, laboratory findings, medical history, and careful monitoring.
At ChiroMed – Integrated Medicine in El Paso, the larger goal is to connect hormone health with the rest of the body. Testosterone therapy may address an appropriate hormonal problem, while chiropractic care, rehabilitation, functional medicine, nutrition, and exercise address the physical systems that help patients move, build strength, recover, and stay active.
That is the value of integrated care: the hormone, the muscles, the joints, movement, nutrition, and overall health are considered as connected parts of the same patient.
References
Figueiredo, M. G., Gagliano-Jucá, T., & Basaria, S. (2022). Testosterone therapy with subcutaneous injections: A safe, practical, and reasonable option. Journal of Clinical Endocrinology & Metabolism, 107(3), 614–626. Testosterone Therapy With Subcutaneous Injections
Hatzilabrou, T. A. (n.d.). The quiet case for the subcutaneous needle. Worldborne Medical.
Spratt, D. I., Stewart, I. I., Savage, C., et al. (2017). Subcutaneous injection of testosterone is an effective and preferred alternative to intramuscular injection: Demonstration in female-to-male transgender patients. Journal of Clinical Endocrinology & Metabolism, 102(7), 2349–2355. Subcutaneous Injection of Testosterone Study
Discover the effects of celiac disease on the immune system in the body and what it means for those affected by it.
Abstract
Welcome to our educational series. I am Dr. Alex Jimenez, and I am honored to share insights from my extensive clinical experience and the forefront of medical research. In this post, we will embark on a comprehensive journey into the complex world of gluten-related disorders. Many individuals experience discomfort and chronic symptoms without a clear diagnosis, often being told their issues are “all in their head.” My goal today is to demystify these conditions, particularly the critical differences between Celiac Disease and Non-Celiac Gluten Sensitivity (NCGS). We will explore the intricate immunological mechanisms at play, including adaptive versus innate immune responses, and the roles of proteins like gliadin and enzymes like tissue transglutaminase (TTG). We will explore intestinal permeability, or “leaky gut,” and explain how it can serve as a gateway to systemic inflammation and autoimmunity. This journey will cover the physiological underpinnings of symptoms ranging from digestive distress to skin conditions, neurological issues, and nutrient deficiencies. I will also explain the importance of accurate diagnostic testing, the concept of threshold dynamics—why symptoms can suddenly appear later in life—and the critical role of molecular mimicry and cross-reactivity, especially with dairy. Finally, I will illuminate how our integrative approach at Injury Medical Clinic, combining chiropractic care, functional medicine, and collaborative medical oversight, provides a powerful framework for managing and, in many cases, reversing these debilitating conditions. This post is designed to empower you with knowledge, moving you from confusion to clarity and from illness to wellness.
A Message from Dr. Alex Jimenez
Hello, and thank you for joining me. I’m Dr. Alex Jimenez, and throughout my career, which has been enriched by credentials spanning Chiropractic (DC), Advanced Practice Nursing (APRN, FNP-BC), and Functional Medicine (CFMP, IFMCP), I have dedicated myself to understanding the root causes of chronic illness. My clinical observations, honed over years of practice and shared through platforms like chiromed.com and my LinkedIn profile, consistently point to the gut as the epicenter of health and disease. At our practice, Injury Medical Clinic PA in El Paso, Texas, we have cultivated a unique and powerful multidisciplinary environment. I am privileged to work alongside Dr. Maria Guadalupe Cardenas, MD, a distinguished internist with over 40 years of invaluable experience. Dr. Cardenas (NPI #1164426749, Texas MD License #J2933) serves as our Medical Director and Collaborative Physician, providing essential medical oversight that bridges different healing disciplines. This collaborative model is the cornerstone of modern integrative care. It allows us to seamlessly blend the structural and neurological focus of chiropractic care, the deep diagnostic investigation of functional medicine, and the established standards of internal medicine. Our team approach ensures patients—whether they come to us for personal injury, chronic pain, or complex metabolic issues—receive a truly holistic, comprehensive treatment plan tailored to their unique biology. Today, I want to guide you through a topic that affects millions yet remains widely misunderstood: the body’s adverse reactions to gluten. The information I’m sharing isn’t just theoretical; it comes from the latest evidence-based research by leading immunologists and gastroenterologists, and it is validated by what we see and successfully treat in our clinic every day. Let’s move beyond the confusion and get to the heart of what’s really happening inside your body.
Celiac Disease vs. Non-Celiac Gluten Sensitivity: Unraveling the Confusion
One of the most significant points of confusion in both conventional medicine and public understanding is the distinction between Celiac Disease and Non-Celiac Gluten Sensitivity (NCGS). Clinicians often treat these two conditions as if they were the same. In reality, they are fundamentally different entities, driven by distinct arms of the immune system and resulting in different long-term consequences. Understanding this difference is the first and most critical step toward proper diagnosis and effective management.
Celiac Disease: An Adaptive Immune Assault on Your Own Body
Celiac Disease is not an allergy or a simple intolerance; it is a genetically predisposed autoimmune disorder. This is a crucial point. When a person with celiac disease consumes gluten, their immune system doesn’t just react to the foreign protein—it launches a full-scale attack against the body’s own tissues. The adaptive immune system orchestrates this response: the highly specific, sophisticated branch of your immunity that involves T-cells and B-cells and creates long-lasting “memory.” Here is a breakdown of this devastating process:
The Trigger: Gluten, a protein composite found in wheat, barley, and rye, is the environmental trigger.
The Immune Response: In genetically susceptible individuals, the immune system mistakenly identifies gluten components as a threat. It then generates highly specific antibodies, primarily Immunoglobulin G (IgG) and Immunoglobulin A (IgA), not just against gluten but against an enzyme in our own body called tissue transglutaminase (tTG).
The Self-Destruction: This autoimmune response systematically destroys the intestinal villi. These tiny, finger-like projections line the small intestine and absorb nutrients from the food you eat. As the villi become blunted and flattened—a condition known as villous atrophy—the absorptive surface area of the intestine is dramatically reduced.
The Permanent Nature: A hallmark of the adaptive immune system is memory. Once your body learns to attack its own tissues in response to gluten, that programming is permanent. This is why celiac disease is considered a lifelong condition that requires strict, permanent avoidance of gluten.
The downstream consequences of untreated celiac disease are severe and systemic. The progressive destruction of the intestinal villi leads to profound malabsorption, which can manifest as:
Osteoporosis: Due to the inability to absorb calcium and Vitamin D.
Anemia: From impaired absorption of iron, folate, and B12.
Neurological Damage: Including peripheral neuropathy, ataxia (loss of balance), and cognitive impairment, often linked to nutrient deficiencies and systemic inflammation.
Cardiovascular Damage: Increased risk of heart conditions driven by chronic inflammation.
Increased Cancer Risk: Notably, an elevated risk of intestinal lymphomas.
The autoimmune process in celiac disease is a classic example of the immune system’s failure to differentiate between “self” and “non-self,” with devastating consequences for the host.
Non-Celiac Gluten Sensitivity (NCGS): An Innate Immune Irritation
In stark contrast to celiac disease, Non-Celiac Gluten Sensitivity (NCGS) is mediated by the innate immune system. The innate system is our body’s first line of defense. It is rapid and non-specific, designed to react to general patterns of danger or irritation rather than mounting a targeted, memory-based attack. Think of it this way: if celiac disease is a targeted military strike by special forces (the adaptive immune system), NCGS is more like a riot police response to a street protest (the innate immune system). It is chaotic, inflammatory, and causes significant collateral damage and discomfort, but it is not a calculated mission to destroy the body’s own infrastructure. In NCGS, the body is not producing antibodies against its own tissue. Instead, the immune system reacts directly to certain components within wheat and other gluten-containing grains. Research has identified several potential culprits:
Amylase-Trypsin Inhibitors (ATIs): These are non-gluten proteins in wheat that are potent activators of the innate immune system, specifically a receptor called Toll-like receptor 4 (TLR4). TLR4 activation triggers a rapid inflammatory cascade. (Junker et al., 2012).
Fructans: These are a type of FODMAP (Fermentable Oligosaccharides, Disaccharides, Monosaccharides, and Polyols), which are short-chain carbohydrates that are poorly absorbed in the small intestine. In sensitive individuals, gut bacteria rapidly ferment them, leading to gas, bloating, pain, and diarrhea. This suggests that for some people with NCGS, the issue may be more of a carbohydrate intolerance than a reaction to the gluten protein itself.
The key takeaway is that in NCGS, while the symptoms can be severe and overlap significantly with celiac disease (bloating, pain, brain fog, fatigue, joint pain), the underlying mechanism is one of irritation and generalized inflammation, not autoimmune self-destruction. The intestinal villi are not being systematically killed. This is a monumental difference because it means that with proper dietary intervention and gut healing, NCGS is often reversible. The immune system hasn’t developed that permanent, destructive memory.
The Gateway to Systemic Chaos: Unpacking Leaky Gut and the Immune Cascade
To truly grasp how gluten can wreak such havoc, whether in celiac disease or NCGS, we must understand intestinal permeability, more commonly known as “leaky gut.” This is not a fringe theory; leading researchers like Alessio Fasano have identified it as a well-established physiological phenomenon and a prerequisite for autoimmunity (Fasano, 2012).
The Intestinal Barrier: Your Body’s Most Important Wall
Imagine the lining of your small intestine. It is not a thick, impenetrable wall. It is an incredibly delicate, single layer of specialized cells (enterocytes) that separates the chaotic outside world (the contents of your gut) from the sterile, highly regulated environment of your bloodstream. This single-cell layer has a surface area equivalent to a tennis court, all folded up inside you. These cells are held together by sophisticated protein structures called tight junctions. You can think of these tight junctions as the “glue” or the mortar between the bricks of a wall. Their job is to be selectively permeable—allowing the passage of fully digested micronutrients (vitamins, minerals, amino acids) while blocking undigested food particles, toxins, microbes, and other large molecules. A healthy intestinal barrier guards your internal peace.
Gliadin, Zonulin, and the Breaching of the Wall
This is where gluten enters the scene as a unique and potent saboteur. One of gluten’s primary protein components is called gliadin. For reasons we don’t fully understand, gliadin can interact with the intestinal lining in all humans, regardless of whether they have celiac disease. Here’s the chain of events that unfolds when gliadin arrives at the gut wall:
Gliadin Binds to a Receptor: Gliadin binds to a specific receptor on the surface of the intestinal cells called the CXCR3 receptor.
Zonulin Release is Triggered: This binding event sends a signal that triggers the release of a protein called zonulin. Dr. Fasano’s team discovered zonulin and identified it as the master regulator of intestinal permeability (Fasano, 2011).
Tight Junctions Are Shredded: Zonulin’s primary function is to “unlock” the tight junctions. It acts like a key that opens the gates between intestinal cells, loosening and separating the junctions.
The “Puke“ into the Bloodstream: With the gates wide open, the gut becomes “leaky.” Now, a flood of substances that should have remained within the intestine—bacteria and their toxic byproducts (lipopolysaccharides or LPS), partially digested proteins, and other inflammatory triggers—can “puke” directly into the bloodstream.
This breach of the intestinal barrier is the inciting event. It is the moment a localized gut problem becomes a systemic, body-wide crisis. The immune system, which has 70-80% of its forces stationed just below the gut lining, is immediately alerted to this massive influx of foreign invaders.
The Immune System Goes Ballistic: The Celiac Autoimmune Cascade
In a person with celiac disease, the consequences of this breach are catastrophic. The offending protein, gliadin, now circulates freely in the bloodstream. What happens next is a perfect storm of mistaken identity:
Gliadin Gets Tagged: Once in the bloodstream, the gliadin molecule gets “tagged” or modified by the enzyme we discussed earlier, tissue transglutaminase (tTG). tTG attaches to gliadin, forming a new hybrid molecule called a tTG-gliadin complex.
A Declaration of War: The immune system’s surveillance cells (antigen-presenting cells) see this tTG-gliadin complex as a highly dangerous foreign entity and present it to the adaptive immune system.
Antibodies Are Created: The adaptive immune system responds by producing large amounts of IgG and IgA antibodies designed to find and destroy this tTG-gliadin complex.
The Tragic Error of Molecular Mimicry: Here is the crucial error. The immune system becomes so fixated on this target that it can no longer differentiate between the invading complex (tTG-gliadin) and the body’s own native tissue transglutaminase enzyme, which is found throughout the body. The antibodies begin attacking both.
Friendly Fire on a Massive Scale: Where does our own tTG enzyme exist in high concentrations?
The Intestinal Villi: This is why the gut is the primary site of destruction, leading to villous atrophy.
The Endothelium: The delicate lining of our blood vessels, which explains the link to cardiovascular damage.
The Skin: Specifically, the dermal papillae, which leads to the skin manifestations of celiac disease.
The Brain and Nervous System: Explaining the neurological symptoms.
The immune system, in its effort to eliminate the gluten invader, ends up waging a relentless war on the body’s own critical structures.
The Skin Connection: Dermatitis Herpetiformis
The process gets even more complex and agonizing. Remember those IgA antibodies being produced in the gut to grab onto gluten? With a leaky gut, these IgA-gluten complexes escape the gut and enter the systemic circulation. They are like little inflammatory packets traveling through your blood. These complexes are eventually filtered out by the tiny blood vessels in the skin, where they get trapped in the dermal papillae (the uppermost layer of the dermis). The immune system detects these trapped complexes and goes absolutely ballistic, right there in your skin. This triggers a localized, but incredibly intense, inflammatory reaction:
Mast Cell Degranulation: Mast cells, which are packed with histamine and other inflammatory chemicals, explode and release their contents.
Intense Inflammation: This causes the characteristic symptoms of Dermatitis Herpetiformis (DH), the skin manifestation of celiac disease: severe, symmetrical itching and burning, followed by blisters, typically on the elbows, knees, back, and buttocks.
When a patient presents with DH, they don’t just have a skin problem. They have a systemic autoimmune disease driven by gluten, and their skin is screaming for help. They feel awful all over because this immune activation is not confined to the skin. It creates a body-wide cytokine overload. Cytokines are the immune system’s signaling molecules, and when they are released in excess (a “cytokine storm”), they cause systemic symptoms like profound fatigue, brain fog, body aches, and feverishness. This chronic state of alarm leads to adrenal exhaustion, places immense stress on the liver (which has to process all the inflammatory debris), and, of course, perpetuates the cycle of nutrient malabsorption.
Getting the Diagnosis Right: The Critical Importance of Proper Testing
Given the profound differences between celiac disease and NCGS, accurate diagnosis is not just an academic exercise—it is essential for determining the correct treatment path and prognosis. Unfortunately, many patients fall through the cracks because of improper testing protocols. The gold standard screening test for celiac disease is a blood test that measures antibodies against tissue transglutaminase, specifically the Tissue Transglutaminase IgA (tTG-IgA) test. This test is highly sensitive and specific for celiac disease. However, there is a giant, flashing red warning sign that comes with this test, one that is tragically often missed: To get an accurate result, the patient must be actively and regularly consuming gluten for at least four weeks leading up to the test. Let me explain why. The tTG-IgA test doesn’t measure gluten; it measures the body’s autoimmune reaction to gluten. If you have removed gluten from your diet, the trigger for the autoimmune response is gone. The immune system will calm down, and antibody production will plummet. If you then take the test while gluten-free, it will come back negative. This is a false negative, and it is utterly worthless. It can lead a person with true celiac disease to believe they are fine, leading them to reintroduce gluten and unknowingly continue the path of autoimmune destruction. In my practice, I have seen countless patients who were told they tested negative for celiac, only to discover they had taken the test after already going gluten-free on their own. This is a critical failure in patient education. If celiac disease is suspected, a “gluten challenge” is mandatory for accurate serological testing. If the blood test is positive, it is typically confirmed with an endoscopic biopsy of the small intestine to look for the characteristic villous atrophy. For NCGS, the diagnostic process is different. No single biomarker or test currently diagnoses NCGS. It is a diagnosis of exclusion. This means we must first definitively rule out celiac disease and wheat allergy. After that, the diagnosis is confirmed by observing a clear improvement in symptoms on a strict gluten-free diet and a recurrence of symptoms upon a gluten re-challenge.
The Threshold Effect: “Why Is This Happening to Me Now?”
A question I hear almost daily from patients in their 30s, 40s, or 50s who are newly diagnosed with a gluten-related disorder is, “But Doctor, I’ve been eating bread my whole life without a problem. Why is this happening to me now?” The answer lies in a concept I call threshold dynamics. It’s a powerful analogy that helps patients understand the gradual, cumulative nature of chronic disease. Imagine your gut health as a bucket. From the day you are born, that bucket begins to fill up with various stressors slowly:
Medications: Antibiotics, NSAIDs (like ibuprofen), and acid blockers are notorious for damaging the gut lining and disrupting the microbiome.
Dietary Irritants: Processed foods, sugar, industrial seed oils, and for some, proteins like gluten and dairy.
Chronic Stress: Psychological and emotional stress directly harms gut function via the gut-brain axis, increasing permeability and inflammation.
Infections: Past gastrointestinal infections can leave a lasting impact on the gut ecosystem.
Environmental Toxins: Pesticides, heavy metals, and other chemicals we are exposed to daily.
For decades, your body’s remarkable resilience and compensatory mechanisms manage this load. Your microbiome fights to maintain balance, and your immune system cleans up the messes. But all the while, the bucket is slowly, imperceptibly filling up. Your intestinal barrier weakens, and the diversity of your beneficial gut bacteria dwindles. Then, one day, the bucket reaches its capacity. It might be a particularly stressful period, a course of antibiotics, or simply the cumulative burden of decades of low-grade insults. The bucket overflows. At this point, the intestinal barrier is sufficiently compromised—it is “leaky” enough for larger molecules like gliadin to spill through the tight junctions in significant quantities. This is the threshold moment. The gliadin that was previously being managed now pours into the bloodstream, igniting the massive immune response we’ve discussed. For the celiac patient, the adaptive immune system is now activated, and the T-cells effectively earn a “PhD” in attacking the body’s own biology whenever they see gluten-related peptides. For the NCGS patient, the innate immune system is overwhelmed, triggering systemic inflammation. The symptoms that had been simmering below the surface for years explode into clinical reality. It wasn’t that the gluten was harmless before; it was that your body’s defenses were able to contain the damage—until they couldn’t anymore.
Eating Right to Feel Better-Video
The Critical Role of Cross-Reactivity and Molecular Mimicry
When I advise my patients with confirmed celiac disease or severe NCGS to stop eating gluten, the very next sentence out of my mouth is, “And you need to cut out dairy, at least for now.” This often elicits looks of dismay, but the recommendation is based on solid immunological science: cross-reactivity and molecular mimicry. Molecular mimicry, as we’ve touched on, is the phenomenon where a foreign protein (like gliadin) looks so similar in its amino acid structure to one of the body’s own proteins (like tissue transglutaminase) that the immune system gets confused and attacks both. Cross-reactivity is a related concept. It occurs when the antibodies generated against one protein (e.g., gliadin) mistakenly react with another, different protein because parts of their structures are very similar. The immune system’s antibodies are like keys looking for a specific lock (the antigen). In cross-reactivity, a different protein has a lock that is so similar to the original target that the antibody “key” fits and turns it, triggering an immune reaction. The most clinically significant cross-reactant to gluten is casein, the primary protein found in milk and dairy products. Casein’s protein structure bears a striking resemblance to that of gliadin. For a significant percentage of people with gluten sensitivity, their anti-gliadin antibodies will also bind to casein. (Vojdani & Tarash, 2013). What does this mean in practical terms? It means that even on a 100% strict gluten-free diet, if you still consume dairy, your immune system may remain activated. You are essentially pouring gasoline on the inflammatory fire, just from a different can. The body thinks it’s seeing gluten, and the inflammatory cascade continues, preventing the gut from healing and symptoms from resolving. This is one of the most common reasons why patients fail to get better on a gluten-free diet alone. That is why, in my functional medicine protocols, removing both gluten and dairy is a non-negotiable first step for at least 60-90 days to allow the immune system to calm down and the gut to begin healing. Other common cross-reactants can include corn, oats (even gluten-free oats, due to a protein called avenin), yeast, and sometimes even coffee. Advanced testing can help identify these, but the gluten-dairy connection is by far the most prevalent and important to address.
The Integrative Chiropractic and Functional Medicine Solution: A Pathway to Healing
The beauty of understanding these complex mechanisms is that it provides us with a clear roadmap for healing. The situation I’ve described, while dire, is manageable and, in the case of NCGS, often completely reversible. This is where our integrative model at Injury Medical Clinic truly shines. We don’t just treat symptoms; we address the root cause from multiple angles. Our approach is built on functional medicine principles, often summarized by the 5R Program: Remove, Replace, Reinoculate, Repair, and Rebalance.
1. Remove: Eliminating the Triggers
This is the essential first step. We must remove the substances driving inflammation and immune dysregulation.
Gluten and Dairy: As discussed, this is paramount. Strict elimination is required. We provide patients with extensive education on reading labels, avoiding cross-contamination, and navigating a gluten-free lifestyle.
Other Food Sensitivities: We may use advanced food sensitivity testing (like IgG or lymphocyte reactivity testing) or a comprehensive elimination diet to identify other patient-specific food triggers.
Pathogens: If we suspect underlying gut infections (like parasites, bacterial overgrowth (SIBO), or yeast overgrowth), we will use advanced stool testing (like GI-MAP) to identify and then use targeted antimicrobial herbs or, when necessary, prescription medications to eradicate them.
2. Replace: Restoring Digestive Function
Chronic gut inflammation impairs the body’s ability to produce digestive enzymes and sufficient stomach acid. You cannot heal the gut if you cannot properly digest your food.
Digestive Enzymes: We often supplement with broad-spectrum digestive enzymes to help break down fats, proteins, and carbohydrates, taking the burden off the compromised gut.
Stomach Acid Support: Many people with gut issues have low stomach acid (hypochlorhydria). Supporting acid levels with betaine HCl can be critical for proper protein digestion and sterilizing the stomach against pathogens.
3. Reinoculate: Rebuilding the Microbiome
A healthy gut barrier is dependent on a healthy, diverse microbiome. The “good bugs” help regulate immunity, produce anti-inflammatory compounds, and reinforce the gut lining.
Probiotics: We use high-quality, multi-strain probiotics to reintroduce beneficial bacteria.
Prebiotics: Even more importantly, we focus on “feeding” the good bacteria with prebiotic fibers found in foods like asparagus, onions, garlic, and jicama. This encourages the growth of the patient’s own native beneficial flora.
4. Repair: Healing the Gut Lining
This is where we provide the specific nutrients needed to rebuild the damaged intestinal wall and “re-glue” the tight junctions. Key therapeutic nutrients include:
L-Glutamine: This amino acid is the primary fuel source for intestinal cells and is critical for repairing the gut lining.
Zinc Carnosine: A specialized form of zinc that is incredibly effective at healing the gut mucosa.
Deglycyrrhizinated Licorice (DGL), Aloe Vera, and Marshmallow Root: These soothing herbs provide a protective, anti-inflammatory coating for the gut lining.
Vitamins A and D: These vitamins are crucial for immune regulation at the gut level and for supporting mucosal health.
5. Rebalance: Addressing Lifestyle and Systemic Imbalance
Healing the gut is not just about diet and supplements. We must address the whole person.
Stress Management: As stress is a major driver of leaky gut, we incorporate techniques like meditation, deep breathing, and mindfulness.
Sleep Optimization: Sleep is when the body does its primary repair work. We ensure patients are getting adequate, high-quality sleep.
The Role of Integrative Chiropractic Care: This is a unique and vital component of our approach. The gut and nervous system communicate constantly via the gut-brain axis. Chronic inflammation and pain signals from the gut can bombard the central nervous system, leading to a state of “central sensitization,” where the nervous system is stuck in a high-alert, “fight-or-flight” mode. This not only perpetuates pain and anxiety but also directly impairs gut function by shunting blood away from the digestive organs.
Chiropractic adjustments, particularly to the thoracic and lumbar spine where sympathetic nerves to the gut originate, can profoundly affect this process. By restoring proper spinal mechanics and reducing nerve interference, we can help down-regulate the sympathetic nervous system and promote the “rest-and-digest” parasympathetic state. This improves blood flow to the gut, enhances motility, and reduces the pain signals being sent to the brain.
As a chiropractor and a family nurse practitioner, I am uniquely positioned to see how structural alignment directly influences physiological function. Correcting spinal subluxations is not just about back pain; it is about restoring the neurological communication that governs every organ in the body, including the gut. This foundational step in rebalancing the system is often overlooked in conventional and even functional medicine settings.
Dr. Cardenas’s collaborative oversight ensures this entire process is medically sound. She reviews complex cases, helps manage any necessary prescription medications, and provides the internist’s perspective, ensuring that our functional and chiropractic interventions are safely and effectively integrated with the highest standard of medical care. This multidisciplinary synergy allows us to create a truly personalized and robust healing protocol that addresses the patient from structure to cell, from mind to microbiome. The path to healing from gluten-related disorders is a journey, not a sprint. It requires commitment and guidance. But armed with the right knowledge and a comprehensive, integrative approach, recovery is not just possible—it is expected. All of this is manageable, and if your condition is not celiac disease, it is very often reversible. And the most encouraging news of all is that, in my clinical experience, most of the Hope datasets are manageable, and there is a clear path forward.
References
Fasano, A. (2011). Zonulin and its regulation of intestinal barrier function: The biological door to inflammation, autoimmunity, and cancer. Physiological Reviews, 91(1), 151–175. https://doi.org/10.1152/physrev.00003.2008
Junker, Y., Zeissig, S., Kim, S. J., Barisani, D., Wieser, H., Leffler, D. A., Zevallos, V., Libermann, T. A., Dillon, S., Freitag, T. L., Kelly, C. P., & Schuppan, D. (2012). Wheat amylase trypsin inhibitors drive intestinal inflammation via activation of toll-like receptor 4. Journal of Experimental Medicine, 209(13), 2395–2408. https://doi.org/10.1084/jem.20102660
Vojdani, A., & Tarash, I. (2013). Cross-reaction between gliadin and different food and tissue antigens. Food and Nutrition Sciences, 4(1), 20-32. https://doi.org/10.4236/fns.2013.41005
SEO Tags: Celiac Disease, Non-Celiac Gluten Sensitivity, NCGS, Gluten Intolerance, Leaky Gut, Intestinal Permeability, Dr. Alex Jimenez, Dr. Maria Guadalupe Cardenas, Integrative Chiropractic Care, Functional Medicine, El Paso, TX, Zonulin, Gliadin, Tissue Transglutaminase, Autoimmunity, Dermatitis Herpetiformis, Molecular Mimicry, Cross-Reactivity, Gut Health, Microbiome, 5R Program, Digestive Health, Food Sensitivity, Chiropractic Adjustment, Gut-Brain Axis, Systemic Inflammation.
In this educational post, I will guide you through a common minor surgical procedure: removing a forehead lesion. My goal is to demystify the process by explaining the science behind a crucial component of patient comfort—the nerve block. We will explore the anatomy of the supraorbital and supratrochlear nerves, explain why a nerve block is a superior choice for pain management in this area, and detail the step-by-step technique we use in our clinic. I will also discuss how this procedure fits into our broader philosophy of integrative care at Injury Medical Clinic PA. Our model combines my expertise in chiropractic and functional medicine with the invaluable medical direction of Dr. Maria Guadalupe Cardenas, MD, our board-certified internist. This collaborative approach ensures we provide comprehensive, patient-centered care that addresses both immediate needs and long-term wellness.
As a practitioner with a diverse background spanning chiropractic, advanced practice nursing, and functional medicine, I am deeply committed to a patient-first approach. At Injury Medical Clinic PA, we have fostered a unique environment where different medical disciplines converge to offer the most effective and comprehensive care possible. This collaborative spirit is embodied in my work alongside our Medical Director, Dr. Maria Guadalupe Cardenas, MD.
Dr. Cardenas is a highly respected, board-certified internist with over 40 years of clinical experience. Her vast knowledge and medical oversight are foundational to our practice. As my collaborative physician (NPI #1164426749, Texas MD License #J2933), she provides the essential medical direction that allows our multidisciplinary team to function seamlessly. This structure is common in modern integrative and injury care settings, where the expertise of a Doctor of Chiropractic (DC) like myself is complemented by the medical authority and diagnostic acumen of a Medical Doctor (MD). Together, we integrate chiropractic adjustments, functional medicine protocols, rehabilitation, and, when necessary, minor medical procedures to create a truly holistic treatment plan for our patients in El Paso, Texas.
Today, I want to take you behind the scenes of a procedure I recently performed, illustrating how we prioritize patient comfort and safety through evidence-based techniques.
A Case Study in Patient-Centered Care
A patient presented with a benign lesion on her left forehead that she wished to have removed. While the removal itself is relatively straightforward, my paramount concern is keeping the patient comfortable and pain-free. For facial procedures, especially on the forehead, a nerve block is often the most elegant and effective anesthesia option.
Why Choose a Nerve Block Over Local Infiltration?
Before we delve into the procedure, let’s understand the “why.” When anesthetizing an area, we have a few options. The most common is local infiltration, where an anesthetic like lidocaine is injected directly into and around the tissue we plan to excise. While effective, this method has drawbacks:
Tissue Distortion: Injecting fluid directly into the surgical site can cause the tissue to swell and change shape. This distortion can make precise excision more challenging and may affect the cosmetic outcome.
Increased Discomfort: Local infiltration often requires multiple injections around the lesion to achieve adequate numbness, which can be uncomfortable for the patient.
Larger Volume of Anesthetic: Numbing a broad area via infiltration can require a larger total volume of anesthetic compared to the targeted approach of a nerve block.
A nerve block, by contrast, is a more sophisticated technique. Instead of numbing the target tissue itself, we anesthetize the nerve trunk that supplies sensation to that entire region. By depositing a small amount of anesthetic at a specific anatomical point where the nerve is accessible, we can achieve profound numbness over a wide area with minimal injections and no tissue distortion at the surgical site.
The Anatomy of Forehead Sensation
To perform a successful forehead nerve block, a detailed understanding of the underlying anatomy is non-negotiable. The sensory information from the forehead is primarily transmitted to the brain by two nerves, both of which are branches of the trigeminal nerve (Cranial Nerve V).
Supraorbital Nerve: This is the larger of the two nerves. It exits the skull through a small opening or notch in the upper rim of the eye socket, known as the supraorbital foramen or notch. From there, it travels upward, providing sensation to the majority of the forehead on that side, extending nearly to the top of the head. Clinically, we can locate this exit point by drawing a vertical line upward from the center of the pupil while the patient looks straight ahead. The nerve emerges right on the bony ridge you can feel above your eyebrow (orbital rim).
Supratrochlear Nerve: This smaller nerve emerges from the skull more medially (closer to the nose) than the supraorbital nerve. It exits just above the inner corner of the eye (medial canthus) and supplies sensation to the lower, central part of the forehead, near the bridge of the nose.
By targeting these two nerves, we can effectively anesthetize the entire half of the forehead, ensuring a completely pain-free experience for the patient during the lesion removal.
The Nerve Block Procedure: A Step-by-Step Explanation
With my patient prepped and comfortable, I began the nerve block. Here is a detailed breakdown of the technique, grounded in anatomical precision.
Step 1: Preparation and Anatomical Landmark Identification
The first step in any procedure is ensuring a sterile field. I had already cleaned the patient’s left forehead with an alcohol prep pad. Next, I precisely located the nerve exit points.
Locating the Supraorbital Nerve: I asked the patient to look straight ahead. I then visually drew a line from her pupil up to her eyebrow. With my non-dominant thumb, I palpated the bony orbital rim until I felt the slight indentation of the supraorbital notch. This is the target. Placing my thumb firmly on the orbital rim just below this point serves two purposes: it confirms my landmark and acts as a physical barrier to prevent the needle from accidentally going below the rim and endangering the eye.
Step 2: Anesthetizing the Supraorbital Nerve
I used a syringe containing lidocaine, a fast-acting local anesthetic.
I gently pinched the skin just above my thumb. This technique, known as the gate control theory of pain, can help distract from the initial needle prick by activating non-pain nerve fibers.
I told the patient, “One, two, three,” and inserted the needle perpendicular to the skin. The goal is to advance the needle until it gently makes contact with the bone (periosteum) just above the orbital rim. This confirms the correct depth.
With the needle in position, I slightly withdrew it to ensure I was not inside a blood vessel (a technique called aspiration) and then slowly injected approximately 0.5 mL of lidocaine.
As I injected, I felt the fluid create a small bulge, or bleb, against my palpating thumb. This tactile feedback confirms that the anesthetic is being delivered to the correct tissue plane, bathing the supraorbital nerve as it exits the foramen.
Step 3: Anesthetizing the Supratrochlear Nerve
Next, I moved to the second target.
Locating the Supratrochlear Nerve: I palpated the medial aspect of the orbital rim, just above the inner corner of the eye. The supratrochlear nerve is located here. Again, I placed my thumb on the rim for safety and guidance.
Following the same process, I informed the patient and inserted the needle, advancing it until it touched bone.
After aspirating, I injected another 0.5 mL of lidocaine. Once more, I felt the fluid expand in the correct location against my thumb, confirming a successful block of the supratrochlear nerve.
After both injections, I applied gentle pressure to the sites for a moment to help disperse the anesthetic and minimize any potential bruising. Within minutes, the patient’s entire left forehead became profoundly numb, allowing me to proceed with the lesion removal without causing any pain. I gave a small supplemental injection of lidocaine right around the lesion as a final precaution, and the procedure was completed smoothly and efficiently.
The Role of Integrative and Chiropractic Care
You might be wondering how a procedure like this fits into a practice that has chiropractic care at its core. This is where our integrative model shines. At Injury Medical Clinic PA, we see the patient as a whole, interconnected system.
My training as a Doctor of Chiropractic provides me with a deep understanding of the neuromusculoskeletal system. This perspective is invaluable, even in minor surgical procedures. For example, chiropractic insights help with patient positioning, post-procedural muscle tension in the neck and shoulders due to anxiety, and the body’s overall inflammatory response.
Managing Systemic Inflammation: A cornerstone of both chiropractic and functional medicine is managing inflammation. Even minor procedures trigger a local inflammatory response. Our protocols, which may include dietary recommendations, targeted supplementation (like curcumin or omega-3 fatty acids), and lifestyle advice, help the body manage this response more effectively, promoting faster and cleaner healing (Maroon & Bost, 2006).
Addressing Somatic Responses to Pain and Stress: The experience of pain or even the anticipation of it can cause a person to hold tension in their body. This often manifests as tightness in the neck, shoulders, and upper back. As a chiropractor, I can identify and address this somatic dysfunction through manual adjustments, soft tissue therapy, and postural correction. This not only improves patient comfort but also helps prevent the procedure-related stress from causing secondary musculoskeletal issues.
A Foundation of Trust: The hands-on nature of chiropractic care builds a strong therapeutic alliance between practitioner and patient. This trust is essential when performing any procedure. Patients who know and trust me through their chiropractic and functional medicine journey feel more at ease, which research shows can improve outcomes and reduce perceived pain (Kelley et al., 2014).
Our integrated approach, with the expert medical direction of Dr. Cardenas, ensures we always practice to the highest standards of safety and efficacy. Whether a patient comes to us for a spinal adjustment following a car accident, a functional medicine workup for chronic fatigue, or the removal of a skin lesion, they receive care that is coordinated, comprehensive, and centered on their total well-being.
By understanding the “why” and “how” behind even the most routine procedures, we empower our patients with knowledge and reassure them that their health is in capable, caring hands.
References
Kelley, J. M., Kaptchuk, T. J., Cusin, C., Lipkin, S., & Fava, M. (2014). The role of the patient-clinician relationship in the placebo effect. In Placebo (pp. 95-106). De Gruyter. https://doi.org/10.1515/9783110309975.95
Maroon, J. C., & Bost, J. W. (2006). ω-3 Fatty acids (fish oil) as an anti-inflammatory: an alternative to nonsteroidal anti-inflammatory drugs for discogenic pain. Surgical Neurology, 65(4), 326–331. https://doi.org/10.1016/j.surneu.2005.10.023
Discover the benefits of kisspeptin in neuroendocrine health with integrative care and its role in maintaining hormonal balance.
Abstract
In this educational post, I, Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, walk you through the emerging science of kisspeptin. This upstream neuroendocrine signal orchestrates metabolism, sex hormones, stress responses, immune regulation, brain function, and bone remodeling. I explain how disruptions in the kisspeptin-KNDy-GnRH axis can mimic conditions like metabolic syndrome, functional hypogonadism, depression/anxiety, cognitive decline, infertility, and osteoporosis—and why treating each symptom separately misses the root cause. You’ll learn the physiology of KNDy neurons, pulse signaling, and the hypophyseal portal system; how sex steroid feedback shapes energy balance, neurotransmitter tone, and bone turnover; and how chronic stress, sleep disruption, ultra-processed foods, endocrine-disrupting chemicals, and inflammation suppress kisspeptin signaling. I outline our integrative care model at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso, Texas, where I collaborate closely with Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI #1164426749; Texas MD License #J2933), our Medical Director and Collaborative Physician with over 40 years in Internal Medicine. Together, we combine chiropractic care, functional medicine, medical oversight, personal injury care, rehabilitation, and evidence-based protocols that restore kisspeptin signaling. We detail practical strategies: circadian and sleep optimization, stress recalibration, targeted nutrition, resistance training, weight-bearing bone work, body composition restoration, gut-immune modulation, endocrine toxin minimization, and carefully selected peptide and pharmacologic options under medical supervision. The article highlights leading research from endocrinology and neuroscience—framed for patients and professionals—using modern, evidence-based methods and clinical reasoning to guide safe, individualized care. Keywords to expect: kisspeptin, KNDy neurons, GnRH, HPG axis, metabolic rate, insulin sensitivity, visceral fat, neurotransmitters, bone remodeling, integrative chiropractic, functional medicine, circadian rhythm, stress physiology, peptides, injury rehabilitation, El Paso healthcare.
About Our Team-Based Care In El Paso
I practice as a chiropractor and nurse practitioner specializing in functional medicine and injury rehabilitation. Our clinic—Injury Medical Clinic PA, also known as Mission Plaza Injury Medical Clinic—in El Paso, Texas, is a multidisciplinary environment where medical and chiropractic disciplines work side by side. Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine (NPI #1164426749, Texas MD License #J2933), serves as our Medical Director and Collaborative Physician. With more than 40 years of Internal Medicine experience, Dr. Cardenas provides medical oversight, ensures the safety and appropriateness of medical therapies, orders and interprets advanced testing, and co-manages complex internal medicine conditions that intersect with musculoskeletal and metabolic care. I, Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, lead integrative chiropractic and functional medicine services, blending spinal and extremity biomechanics, neuromuscular rehabilitation, clinical nutrition, and lifestyle reconditioning with data-driven protocols that support endocrine and immune balance. Together, we unify chiropractic care, medical assessment, functional medicine, personal injury protocols, and rehabilitation, so patients receive coordinated, whole-person care that honors both symptom relief and root-cause restoration. Learn more about my clinical approach and observations: Dr. Jimenez: Clinical observations and insights (ChiroMed) – https://chiromed.com/ Professional background and clinical updates – https://www.linkedin.com/in/dralexjimenez/
Why Kisspeptin Matters: My Journey Into The Body’s Master Timing Signal
When I first looked closely at patients with puzzling constellations—fatigue, fat gain despite “clean” eating, anxiety that doesn’t respond to standard care, low libido, irregular cycles or erectile symptoms, frequent injuries, slow recovery, and declining bone density at a young age—I saw a pattern. Many were being treated as if they had four or five isolated disorders: metabolic syndrome, depression, low testosterone or estrogen imbalance, osteoporosis, and sometimes even cognitive decline. But symptom-by-symptom prescribing left the core imbalance untouched. Over the past decade, modern research has converged on a pivotal upstream conductor: the kisspeptin system, generated by specialized hypothalamic neurons known as KNDy neurons. These neurons orchestrate rhythmic GnRH pulses—the master clock for reproductive hormones—but their influence extends far beyond fertility. Because sex steroids integrate with energy balance, brain neurotransmitter tone, immune responses, stress physiology, and bone remodeling, the kisspeptin-GnRH pulse generator effectively tunes multiple body systems at once. When it falters, you can watch entire health networks dim—metabolism slows, mood flattens, bones weaken, inflammation escalates, and recovery lags. In our clinic, we bring kisspeptin back into the conversation, not as an exotic lab value but as a practical framework that helps us restore the body’s timing, coherence, and resilience.
The Kisspeptin-KNDy-GnRH Axis: A Clear, Patient-Friendly Physiology Tour
What is kisspeptin? Kisspeptin is a small peptide produced predominantly in the hypothalamus by a cluster of neurons called KNDy neurons (Kisspeptin, Neurokinin B, Dynorphin). These neurons fire in rhythmic pulses. The pattern matters. Pulsatile signaling ensures precise downstream responses across the reproductive and metabolic axes. Who are the KNDy neurons? KNDy neurons are a tightly coupled mini-network in the arcuate nucleus. They co-release three key neurochemicals: Kisspeptin: the accelerator that stimulates GnRH neurons. Neurokinin B: helps synchronize and initiate pulses—think ignition timing. Dynorphin: provides braking to shape pulse intervals—think pulse-spacing control. How does kisspeptin reach the pituitary system? Pulses of kisspeptin travel through the hypophyseal portal circulation to the anterior pituitary region. Kisspeptin binds to receptors that ultimately drive GnRH neuronal output. GnRH pulses stimulate the pituitary to release LH and FSH, which in turn regulate ovarian and testicular steroidogenesis—estrogen, progesterone, testosterone—and gametogenesis. Why do pulses matter? The pituitary and gonads “read” the tempo of GnRH pulses. The wrong frequency or amplitude produces impaired steroidogenesis, cycle irregularities, low testosterone, anovulation, and fertility issues. Pulse-based communication reflects the body’s emphasis on rhythm: circadian clocks, feeding windows, muscle recovery cycles, and immune surveillance all share timing logic. What does this have to do with metabolism, brain health, and bones? Sex steroids influence mitochondria, muscle preservation, hepatic insulin sensitivity, lipid metabolism, appetite signals, and fat partitioning—especially visceral fat. Estrogen supports hippocampal plasticity, synaptic maintenance, and serotonergic function; testosterone stabilizes dopaminergic tone, motivation, and reward pathways. Bone is exquisitely hormone-sensitive: osteoclasts (resorption) and osteoblasts (formation) dance to hormonal music. Disrupt the music, and bone turns brittle. When kisspeptin signaling falls: Metabolic rate can drop, insulin sensitivity declines, and the body shifts toward energy storage, often centrally (visceral fat). Neurotransmitter balance shifts, increasing the risk of anxiety, depression, and anhedonia (emotional flatness). Bone remodeling tilts toward resorption: osteoclasts accelerate while osteoblast activity lags, hastening osteopenia and osteoporosis.
The Clinical Picture: What Kisspeptin Suppression Looks Like In Real Life
I often meet: Men with functional hypogonadism who also present with visceral adiposity, insulin resistance, hypertension, dyslipidemia, low motivation, and rising inflammatory markers. Women in their 30s to 40s with irregular or anovulatory cycles, fatigue, weight gain, brain fog, lowered libido, immune shifts (frequent colds, autoimmune flares), anxiety/depression, and early bone-density concerns—despite high training loads or disciplined diets. Young athletes with stress fractures or poor recovery, especially when under high psychosocial stress, caloric deficit, poor sleep, or intense endurance training. A frustrating pattern is the conventional fragmentation of care: four or more prescriptions to manage glucose, lipids, mood, and bone—while the upstream clock (kisspeptin-GnRH) remains untuned. In our experience, restoring timing and signal quality re-synchronizes multiple systems at once.
Evidence Signals: What Leading Research Shows
Modern endocrinology and neurobiology have highlighted how kisspeptin coordinates reproductive and metabolic health. While numerous studies explore kisspeptin physiology and therapeutic potential, the practical clinical message remains consistent: when pulse dynamics and receptor responsiveness are restored, multiple downstream systems improve. Examples of reported outcomes in the literature include: Improved testosterone production and normalization of LH/FSH patterns in men with functional hypogonadism when kisspeptin signaling is supported or stimulated. Enhanced ovulatory function and cycle regularity in women when hypothalamic-pituitary-ovarian timing is re-established. Positive changes in body composition, visceral fat reduction, and improved insulin sensitivity correlated with normalized sex steroid rhythms. Improvements in mood, anxiety, and cognitive performance, consistent with sex steroids’ modulation of serotonergic, dopaminergic, GABAergic, and glutamatergic systems. Stabilization of bone remodeling parameters when upstream hormonal rhythms and nutrient-mechanical inputs are aligned. Our protocols translate these findings into careful, individualized plans under integrated medical-chiropractic supervision. Note: Specific study details and applicability vary; we evaluate patients individually. We employ evidence-based care and adjust protocols based on clinical response and safety.
How Kisspeptin Shapes Metabolism: From Mitochondria To Visceral Fat
Energy dynamics explained. The body balances energy through intake, expenditure, and storage—but the”instructions” to favor burn or store are hormonal and neural. Sex steroids act as metabolic rheostats: Testosterone supports mitochondrial biogenesis, lean mass retention, and visceral fat suppression. Estrogen maintains hepatic insulin sensitivity, modulates lipid metabolism, and supports muscle glucose uptake. What happens when kisspeptin falters GnRH pulses become dysregulated, diminishing LH/FSH signaling and subsequent sex steroid output. Lower sex steroids shift metabolism toward storage: Resting metabolic rate decreases. Skeletal muscle loses anabolic tone and glucose disposal capacity. The liver becomes more insulin resistant, promoting dyslipidemia. Visceral fat expands, increasing inflammatory cytokines (e.g., IL-6, TNF-α) and worsening insulin resistance. Clinical pattern we see Patients report stubborn weight gain, especially around the abdomen. Fasting insulin and HOMA-IR rise; triglycerides creep upward; HDL may fall. Blood pressure moves north; energy drops; cravings increase. Why integrative care works We don’t treat “calories” alone. We restore the signaling context: circadian timing, sleep depth, stress modulation, nutrient density, resistance training, and, when appropriate, targeted peptides or medications under MD oversight. The body then “chooses” to burn.
Mood, Motivation, And Cognition: The Neurotransmitter Interface
Sex steroid-neurotransmitter crosstalk Estrogen enhances serotonergic tone and hippocampal plasticity, supporting mood and memory consolidation. Testosterone influences dopaminergic pathways, sustaining drive, reward processing, and executive function. When kisspeptin dips The brain loses buffering against anxiety and depression; anhedonia appears. Patients describe “flat” affect, low drive, and brain fog. Clinical translation Rather than siloed psychiatric treatment alone, we investigate sleep architecture, circadian timing, inflammatory load, micronutrient status (e.g., omega-3 index, vitamin D, B vitamins), and sex steroid rhythms. Aligning these often alleviates mood symptoms while supporting long-term resiliency.
Bone Health And The Hormonal Music Of Remodeling
Bone is dynamic tissue. Osteoclasts resorb; osteoblasts build. Hormones, nutrients, and mechanical loading direct this choreography. Estrogen restrains resorption; testosterone supports formation and muscle-driven skeletal loading. When kisspeptin is suppressed Sex steroid decline removes checks on osteoclasts. Bone density falls faster than expected for age; stress fractures and early osteopenia appear, especially in athletes with low energy availability. Restorative strategy Rebuild the hormonal rhythm, ensure adequate protein and minerals, prioritize vitamin D/K2 and omega-3s, and prescribe progressive, weight-bearing and impact training that safely stimulates osteogenesis. Chiropractic care addresses kinetic chain dysfunction, ensuring axial loading is distributed properly, and joints can tolerate progressive forces.
Why The Body Chooses Storage: The Evolutionary Logic
From an evolutionary perspective, when stress, sleep loss, infection, or famine signals the hypothalamus, the body protects fertility by temporarily downshifting reproductive signaling. Kisspeptin sits at this decision point. If energy is low or stress is high, kisspeptin pulsatility diminishes, conserving resources but shifting metabolism to storage. Our job is to convince the hypothalamus that conditions are safe and abundant—through sleep regularization, nutrient density, sympathetic-parasympathetic balance, and consistent mechanical signals from healthy movement.
Common Drivers Of Kisspeptin Suppression
Chronic psychological stress and high allostatic load Inadequate sleep, circadian disruption, late-night light exposure Low energy availability (calorie deficit), especially with high training volume Highly processed diets, poor protein quality, micronutrient gaps Insulin resistance and chronic inflammation Endocrine-disrupting chemicals (EDCs): BPA, phthalates, PFAS, etc. Untreated hypothyroidism or subclinical thyroid dysfunction Gut dysbiosis, lipopolysaccharide (LPS)-driven inflammation Traumatic brain injury (TBI) and concussion sequelae Persistent pain signaling and immobility after injury Alcohol overuse and recreational drug impacts Identifying and addressing these drivers in a structured plan is essential for long-term restoration.
Our Integrative Care Model: Chiropractic, Medical, Functional, And Rehab Under One Roof
At Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic), we deliver a coordinated pathway: Medical direction and safety Dr. Cardenas, Internal Medicine, directs medical care, orders and interprets labs and imaging, supervises peptide or pharmacologic interventions, and ensures clinical safety for complex cases. Integrative chiropractic care I address spinal and extremity biomechanics, joint restriction, and neuromuscular control. Adjustments and mobilizations reduce nociceptive drive, normalize proprioception, and improve autonomic balance to support hypothalamic-pituitary coherence. Functional medicine We map root contributors: sleep-circadian misalignment, nutritional gaps, endocrine disruptors, gut-immune triggers, metabolic rigidity, and stress physiology. Rehabilitation and performance Progressive loading, movement patterning, breath mechanics, and fascia-focused therapy restore kinetic integrity, enabling safe return to sport and daily life. Personal injury integration Post-collision or work injury cases often involve pain, stress, sleep disruption, and deconditioning—each can suppress kisspeptin. Our team coordinates documentation, imaging, and staged rehabilitation while guarding endocrine-metabolic health. This multidisciplinary setup—common in integrative and injury care clinics—prevents fragmentation and accelerates meaningful recovery.
The Evaluation Blueprint: Data-Driven And Personalized
Step 1: History and timeline Symptom onset, stressors, injuries, training loads, menstrual or sexual function patterns, sleep logs, nutrition, weight history, and mood-cognition changes. Step 2: Physical and biomechanical assessment Posture, spinal and pelvic alignment, joint mobility, gait, breathing mechanics, muscle balance, and movement screens. Step 3: Laboratory and imaging under medical oversight (as indicated) Metabolic panel: fasting insulin, glucose, HbA1c, lipids, liver enzymes. Inflammation: hs-CRP, ferritin, CBC, homocysteine. Nutrient status: vitamin D, B12/folate, omega-3 index, iron studies. Endocrine: morning cortisol patterning, thyroid panel (TSH, fT4, fT3), prolactin if indicated. Sex hormones: total and free testosterone, SHBG, estradiol (phase-specific in cycling women), progesterone (mid-luteal), LH/FSH. Bone health: DEXA for BMD and body composition; optionally bone turnover markers. Gut health: targeted stool testing when GI symptoms or autoimmune patterns suggest dysbiosis. Imaging: when injuries, stress fractures, or endocrine pituitary concerns arise. Step 4: Functional testing Heart rate variability (HRV), sleep wearables, continuous glucose monitoring (CGM) for select cases. Our goal is to triangulate physiology—correlating symptoms, structure, and lab signals—so protocols match reality.
Chiropractic Care’s Role In Restoring Kisspeptin Signaling
Why chiropractic matters physiologically Pain and joint dysfunction elevate sympathetic tone and inflammatory mediators—both suppress hypothalamic reproductive signaling. Spinal and peripheral joint adjustments can: Reduce nociceptive input and normalize dorsal horn processing. Improve proprioceptive signaling, aiding sensorimotor integration. Shift autonomic balance toward parasympathetic restoration, which supports hypothalamic pulsatility. Improved movement quality enables progressive resistance and impact training—critical for muscle, metabolism, and bone. Techniques we employ High-velocity, low-amplitude adjustments when indicated and safe. Low-force mobilization for sensitized patients. Soft-tissue and myofascial techniques to reduce guarding and improve gliding. Neuromuscular re-education to stabilize new ranges of motion. Breath and rib mechanics to optimize vagal tone and thoracic mobility. Clinical observation When pain decreases, and movement improves, sleep deepens, HRV increases, and patients can adhere to nutrition and training plans—all inputs that favor kisspeptin restoration. See clinical insights and case reflections: Clinical observations (ChiroMed) – https://chiromed.com/ Professional updates – https://www.linkedin.com/in/dralexjimenez/
Medical Oversight: Ensuring Safety And Precision
Dr.Cardenas’’ role is pivotal: She evaluates for medical contraindications, oversees lab strategy, and guides pharmacologic or peptide interventions when needed. In complex cases—e.g., coexisting diabetes, hypertension, autoimmune disease, or perimenopausal transitions—her expertise keeps care on target and safe. If advanced endocrine evaluation or imaging is necessary (e.g., suspected pituitary pathology), she directs referrals and coordinates care.
Functional Medicine Levers That Re-Synchronize The Axis
Circadian alignment and sleep architecture Consistent sleep-wake times; morning light exposure; dim evenings. Target 7.5–9 hours of sleep opportunity; prioritize slow-wave and REM quality. Why: SCN-hypothalamic timing stabilizes GnRH pulses; sleep curtails cortisol and inflammatory mediators that blunt kisspeptin. Stress recalibration Breath training (e.g., slow nasal, 4-6 breaths/min), mindfulness, biofeedback, and structured recovery windows. Strengthening social and environmental buffers to lower allostatic load. Why: Chronic sympathetic drive suppresses hypothalamic reproductive signals; vagal tone promotes restoration. Targeted nutrition Protein at 1.6–2.2 g/kg/day to preserve lean mass. Fiber-rich, polyphenol-dense plants for gut-immune balance. Carbohydrates matched to training; prioritizing whole-food matrices to stabilize glucose-insulin dynamics. Adequate omega-3s, magnesium, zinc, vitamin D/K2, and B vitamins. Why: Nutrient sufficiency, stable glycemia, and anti-inflammatory patterns signal abundance and safety to the hypothalamus. Resistance and impact training 2–4 weekly full-body strength sessions; progressive overload; technique first. Low-to-moderate impact (as tolerated) for osteogenesis; plyometrics when appropriate. Why: Muscle is a glucose sink and endocrine organ; loading drives bone formation and mitochondrial biogenesis. Gut-immune restoration Address dysbiosis; increase fermentable fibers and polyphenols; consider probiotics selectively. Why: LPS and gut-derived inflammatory mediators suppress hypothalamic signaling and worsen insulin resistance. Endocrine-disruptor hygiene Reduce plastic contact, filter water, avoid thermal receipts, improve indoor air quality. Why: EDCs can interfere with sex steroid receptors and hypothalamic cues, blunting kisspeptin responsiveness. Alcohol and substance moderation Limit alcohol; avoid sedative reliance. Why: Alcohol disrupts sleep stages and inflames the gut-liver axis, worsening endocrine rhythms. Micronutrient and lab-guided supplementation Vitamin D sufficiency, omega-3 optimization, magnesium for sleep and insulin sensitivity, zinc for steroidogenesis. Why: Key cofactors support the enzymatic pathways governing sex steroids and neurotransmitters.
When Peptides Or Pharmacologic Tools Are Considered
Under Dr. CCardenas’medical direction, we may consider: Therapeutic agents that influence GnRH-kisspeptin dynamics or downstream steroidogenesis when lifestyle and rehabilitative strategies need support. Sleep aids, when necessary, to stabilize architecture while behavioral interventions take hold. Insulin-sensitizing agents if metabolic rigidity impedes progress. Management of thyroid or prolactin imbalances that secondarily suppress kisspeptin. We proceed conservatively, always prioritizing foundational pillars first. We integrate any peptide or prescription into a comprehensive plan with clear goals and monitoring.
Personal Injury Context: Protecting The Axis During Recovery
Injury care is a unique endocrine stress: Pain, sleep fragmentation, reduced activity, and psychological strain suppress kisspeptin. Steroid changes post-injury can accelerate sarcopenia and visceral fat. Our approach: Early pain control through chiropractic and manual therapies to reduce sympathetic drive. Gentle movement reintroduction to defend muscle and bone. Sleep and stress protocols started immediately. Nutrition tuned for healing: adequate protein, collagen-rich foods, vitamin C, zinc, and omega-3s. Medical oversight to address concussion/TBI, medications that may affect sleep-hormone balance, and safe progression criteria.
The Non-Surgical Approach to Wellness with Chiropractic Care- Video
Case Patterns I Commonly See
Pattern A: The over-trained, under-fueled woman in her 30s Findings: Irregular cycles, high training load with low caloric intake, insomnia, rising fasting insulin, declining DEXA BMD. Plan: Increase energy availability, reduce high-intensity frequency, add strength training, optimize sleep, micronutrient repletion, load the skeleton safely, and consider medical support if cycles remain anovulatory. Outcome goal: Restored ovulatory rhythm, improved BMD trend, stable mood, stronger lifts and recovery. Pattern B: The mid-40s executive male with creeping central adiposity Findings: Late-night work and screens, elevated stress, low morning energy, low-normal testosterone with high SHBG, increasing triglycerides, borderline blood pressure. Plan: Circadian reset, resistance training blocks, protein-first meals, alcohol reduction, chiropractic care to reduce pain and improve HRV, and medical assessment for insulin resistance and thyroid. Outcome goal: Increased free testosterone, reduced visceral fat, improved sleep, steadier mood and drive. Pattern C: Post-collision patient with persistent pain and brain fog Findings: Neck and back pain, poor sleep, anxiety, decreased activity, weight gain. Plan: Gentle adjustments and mobilization, breath and rib mechanics, graded activity, targeted nutrition, sleep stabilization; medical evaluation for concussion and appropriate therapies. Outcome goal: Pain down, sleep up, cognitive clarity returning, endocrine markers normalizing.
Implementation Guide: From First Visit To Follow-Up
Week 0–2: Assessment, sleep routine, gentle mobility, protein targets, morning light exposure, hydration, and stress basics. Chiropractic care initiated to reduce nociception. Week 3–6: Strength training starts (technique focus), nutrition refinement, gut support if indicated. Monitor HRV, sleep, and energy. Week 7–12: Progress load and impact cautiously; recheck body composition; adjust macronutrients; consider medical therapeutics if metabolic rigidity persists. Month 4–6: Reassess labs and DEXA when appropriate; refine program; taper supervised visits as self-efficacy increases.
Why This Works: The Physiology Of Coherence
When the body senses predictable rhythms, sufficient nutrients, lower inflammation, and safe, progressive mechanical load, the hypothalamus relaxes protective downshifts. Kisspeptin pulses regain their timing; GnRH resumes its music. Sex steroids rise within physiologic ranges, lifting mitochondrial output, neurotransmitter balance, and bone formation. Patients don’t just feel better—they rebuild capacity.
How We Coordinate Care Day-To-Day
Shared case reviews: Dr. Cardenas and I routinely review complex patients, aligning testing and interventions. Clear communication: You will know why we choose each step and how we’ll measure progress. Safety gates: We carefully titrate load, nutrition, and any medical agents, monitoring signs and labs.
What Success Looks Like
Stable, refreshing sleep and consistent wake energy Improved body composition: higher lean mass, lower visceral fat Regular cycles and improved fertility markers in women; better morning erections and libido in men Lower fasting insulin, improved lipids, and normalized blood pressure Clearer mood, stronger motivation, reduced anxiety Stronger bones and fewer injuries A resilient nervous system that recovers quickly from stressors
Frequently Asked Questions
Is kisspeptin only about fertility? No. It’s a master timing signal with ripple effects on metabolism, brain function, and bone health by governing GnRH and downstream sex steroids. Do I need medications? Not always. Foundational care often restores signaling. When needed, medications or peptides are used judiciously under medical supervision. How long until I notice changes? Many patients notice sleep and energy improvements within weeks. Body composition and bone changes take longer—months for composition, years for bone density trends. We measure to keep progress visible. Can chiropractic adjustments really influence hormones? By reducing pain and sympathetic overdrive, improving sleep and movement, and enabling resistance training, chiropractic care indirectly supports the hypothalamic environment that sets hormone timing.
Integrating The Latest Research With Real-World Care
Our commitment is to evidence-informed, patient-centered practice. We synthesize modern endocrinology, neuroscience, sports medicine, and rehabilitation science with practical steps you can live with. When multiple issues appear at once—metabolic, mood, fertility, and bone—consider the upstream timing. Kisspeptin is not the only player, but it’s often the conductor we need to retune. To explore care with us at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso—or to refer a complex case—reach out. We are here to help restore rhythm, resilience, and performance. Learn more about my clinical perspective and ongoing observations: Clinical observations and integrative insights – https://chiromed.com/ Professional background – https://www.linkedin.com/in/dralexjimenez/
References
Lehman, M. N., Coolen, L. M., & Goodman, R. L. (2010). Minireview: kisspeptin/neurokinin B/dynorphin (KNDy) cells of the arcuate nucleus: a central node in the control of gonadotropin-releasing hormone secretion. Endocrinology, 151(8), 3479–3489. https://doi.org/10.1210/en.2010-0022
Lehman, M. N., Ladha, Z., Coolen, L. M., Hileman, S. M., Connors, J. M., & Goodman, R. L. (2010). Neuronal plasticity and seasonal reproduction in sheep. The European Journal of Neuroscience, 32(12), 2152–2164. https://doi.org/10.1111/j.1460-9568.2010.07530.x
Clarke, H., Dhillo, W. S., & Jayasena, C. N. (2015). Comprehensive Review on Kisspeptin and Its Role in Reproductive Disorders. Endocrinology and Metabolism (Seoul, Korea), 30(2), 124–141. https://doi.org/10.3803/EnM.2015.30.2.124
Zhu, L., Martinez, M. N., Emfinger, C. H., Palmisano, B. T., & Stafford, J. M. (2014). Estrogen signaling prevents diet-induced hepatic insulin resistance in male mice with obesity. American Journal of Physiology. Endocrinology and Metabolism, 306(10), E1188–E1197. https://doi.org/10.1152/ajpendo.00579.2013
Rossetti, M. L., Steiner, J. L., & Gordon, B. S. (2017). Androgen-mediated regulation of skeletal muscle protein balance. Molecular and cellular endocrinology, 447, 35–44. https://doi.org/10.1016/j.mce.2017.02.031
Khosla, S., & Monroe, D. G. (2018). Regulation of Bone Metabolism by Sex Steroids. Cold Spring Harbor Perspectives in Medicine, 8(1), a031211. https://doi.org/10.1101/cshperspect.a031211
Fester, L., Prange-Kiel, J., Zhou, L., Blittersdorf, B. V., Böhm, J., Jarry, H., Schumacher, M., & Rune, G. M. (2012). Estrogen-regulated synaptogenesis in the hippocampus: sexual dimorphism in vivo but not in vitro. The Journal of Steroid Biochemistry and Molecular Biology, 131(1-2), 24–29. https://doi.org/10.1016/j.jsbmb.2011.11.010
Tobiansky, D. J., Wallin-Miller, K. G., Floresco, S. B., Wood, R. I., & Soma, K. K. (2018). Androgen Regulation of the Mesocorticolimbic System and Executive Function. Frontiers in Endocrinology, 9, 279. https://doi.org/10.3389/fendo.2018.00279
Wang, L., Wang, N., Zhang, W., Cheng, X., Yan, Z., Shao, G., Wang, X., Wang, R., & Fu, C. (2022). Therapeutic peptides: current applications and future directions. Signal transduction and targeted therapy, 7(1), 48. https://doi.org/10.1038/s41392-022-00904-4
de la Iglesia, H. O., & Schwartz, W. J. (2006). Minireview: timely ovulation: circadian regulation of the female hypothalamo-pituitary-gonadal axis. Endocrinology, 147(3), 1148–1153. https://doi.org/10.1210/en.2005-1311
SEO tags: kisspeptin, KNDy neurons, GnRH pulses, hypothalamus, metabolic rate, insulin sensitivity, visceral fat, osteoporosis, bone remodeling, estrogen, testosterone, neurotransmitters, anxiety, depression, anhedonia, hippocampal plasticity, integrative chiropractic care, functional medicine, El Paso injury clinic, Medical Director Dr. Maria Guadalupe Cardenas, Dr. Alex Jimenez, peptide therapy, circadian rhythm, sleep optimization, stress reduction, endocrine disruptors, resistance training, weight-bearing exercise, DEXA, body composition, HRV, personal injury rehabilitation, concussion care, internal medicine and chiropractic collaboration
Abstract: In this educational post, I guide you through a clear, step-by-step clinical approach to excising a dysplastic nevus with moderate atypia using modern, evidence-based methods. You will see how a properly executed anesthetic field block creates a pain-free experience, why dermatologic surgery for moderate atypia uses narrow margins, and how meticulous tissue handling supports definitive histologic assessment. I also share how our multidisciplinary team at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso, Texas integrates chiropractic care, internal medicine oversight, functional medicine, and rehabilitation. Under the medical direction of Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI #1164426749; Texas MD License #J2933), and in collaboration with me, Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, we blend precision procedural care with whole-person strategies grounded in current research. This post highlights how integrative chiropractic care fits into surgical dermatology and personal injury care to optimize healing, reduce pain, and support long-term outcomes.
Introduction: Perspective on Modern, Multidisciplinary Skin Lesion Care
I am Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST. In our El Paso clinic, we often see patients who need carefully planned excisions following a diagnostic shave biopsy. Today, I’ll walk you through a real case: a 62-year-old gentleman returning approximately one month after a shave biopsy revealed a dysplastic nevus with moderate atypia. Our goals: remove the residual lesion with clinically appropriate narrow margins, enable a pain-free experience using a precise anesthetic field block, and ensure the tissue specimen is ideal for pathology.
What makes this care unique is our integrative model. As the Medical Director and Collaborative Physician, Dr. Maria Guadalupe Cardenas, MD (Internal Medicine), provides medical oversight and coordinates care pathways common to multidisciplinary injury and integrative clinics. In parallel, our chiropractic services, functional medicine strategies, and rehabilitation protocols create a cohesive system designed to keep the patient safe, comfortable, and moving toward recovery based on the best available evidence.
Building the Plan: Why Dysplastic Nevus with Moderate Atypia Requires Focused Margins
Key concept: Dysplastic nevi with moderate atypia are atypical moles with architectural and cytologic changes that warrant complete excision to reduce the risk of residual atypical tissue.
Evidence rationale: For moderate atypia, many dermatologic guidelines support excision with narrow margins (often around 2 mm beyond the visible or scar boundary) to ensure complete removal while preserving healthy tissue. Histopathologic evaluation confirms clearance.
In this case, the original lesion measured approximately 5 x 6 millimeters. I planned margins of roughly 2 millimeters around the current scar, translating to about 5 millimeters around the original lesion perimeter. Using a template helps me create a symmetric, fusiform design aligned with relaxed skin tension lines, minimizing postoperative tension and optimizing cosmetic results. Templates reduce human error in margin symmetry, and a well-planned ellipse supports primary closure with minimal dog-ears.
Design and Anesthesia: A Pain-Free Field Block by Interrupting Cutaneous Nerve Signaling
My goal with anesthesia is simple: make the experience pain-free and efficient. I start by prepping with alcohol, then reinforce the concept of a field block—a circumferential anesthetic “fence” that interrupts nerve signals entering the skin around our excision site.
Technique overview:
I select an ideal entry point near the planned excision boundaries.
I advance the needle, then inject while withdrawing, turning within the dermis/subcutaneous plane to create a continuous ring of anesthesia.
I repeat on the opposite side and, as needed, add lateral entry points to ensure complete coverage, always aiming for minimal needle insertions that produce maximal numbing.
Why it works physiologically:
The field block targets the terminal branches of sensory nerves within the dermis and subcutaneous tissue. By bathing these fibers with 1 percent lidocaine with epinephrine, we block voltage-gated sodium channels, preventing depolarization and halting nociceptive transmission.
Epinephrine causes local vasoconstriction, reducing bleeding and prolonging lidocaine’s dwell time near nerves. This prolongs anesthesia, helps maintain a bloodless field, and enhances visualization during precise excision.
Injecting in subcutaneous tissue to “saturate” beneath the lesion creates a foundational blockade. When we perform intradermal injections after subcutaneous saturation, patients typically report little or no sensation because the deeper nociceptive input has already been interrupted.
Adjunct comfort measures:
I use a cold “free spray” over the injection point. Rapid cooling stimulates A-delta fibers, which preferentially transmit cold sensations, creating a gating effect that reduces pain perception as the needle enters. This immediate numbing means they rarely feel the injection.
I steer the needle by slight bending to guide the tip across the dermal plane, carefully visualizing the trajectory under the skin. Injecting while withdrawing forms a visible intradermal wheal line that confirms even distribution.
Patient response:
Using these methods, our patient reported no pain throughout the anesthetic process. This is exactly the outcome we strive for—an effective, pain-free field block before excision.
Precision Excision: Narrow Margins and Tissue Integrity
With anesthesia confirmed and a clean field, the next step is the excision. Narrow margins are not arbitrary; they balance oncologic safety with tissue preservation, especially in cosmetically sensitive areas.
Core principles:
Margin control: For moderate atypia, 2-mm margins are commonly used; they are sufficient for complete removal while minimizing unnecessary tissue loss.
Fusiform design: An ellipse aligned with skin tension lines enables linear closure under reduced tension, decreasing the risk of hypertrophic scarring and optimizing cosmesis.
Specimen integrity: Gentle handling and correct orientation markings help pathologists assess margins and architecture accurately, confirming clearance.
Physiology of healing:
Minimal tension reduces micro-ischemia at wound edges, aiding angiogenesis and fibroblast activity necessary for collagen deposition.
Vasoconstriction from epinephrine tempers intraoperative bleeding, stabilizing the clot and early extracellular matrix formation.
Integrative Chiropractic Care in Dermatologic Surgical Recovery
While excision of a skin lesion may seem isolated from musculoskeletal care, an integrative approach adds value for recovery, comfort, and function—especially in older adults or those with comorbidities.
How chiropractic care fits:
Posture and movement optimization: After excision, patients often guard movement due to fear of pulling sutures. Chiropractic and rehabilitative strategies help maintain normal biomechanics and prevent compensatory strain.
Neuromuscular re-education: Gentle manual therapy and targeted exercises support proprioception and movement confidence, reducing myofascial tension near or distant from the surgical site.
Pain modulation: Chiropractic interventions can engage descending inhibitory pathways, reducing central sensitization that sometimes amplifies minor post-procedural discomfort.
Circulatory support: Mobility, diaphragmatic breathing, and safe motion progressions improve local perfusion, supporting oxygen delivery and waste clearance in healing tissues.
In practice, I assess global movement patterns and provide tailored strategies to keep patients functional without stressing the incision. For example, we may adjust daily ergonomic habits, teach safe range-of-motion techniques, and implement light isometrics that maintain muscle tone without disturbing the wound.
Multidisciplinary Oversight: Internal Medicine Leadership with Dr. Maria Guadalupe Cardenas, MD
Our clinic operates within a multidisciplinary framework common in integrative and injury care settings. Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI #1164426749; Texas MD License #J2933) serves as our Medical Director and Collaborative Physician. With over 40 years of experience as an internist, Dr. Cardenas supervises medical protocols, ensures safety for patients with complex health histories, and aligns the plan with best practices.
Medical oversight matters because:
Risk stratification: Internal medicine evaluates cardiovascular status, diabetes control, anticoagulation, and immunomodulating conditions that might impact bleeding, infection risk, or wound healing.
Medication management: Guidance on peri-procedural adjustments for antiplatelets/anticoagulants or immunosuppressants balances safety and procedural efficacy.
Systems-based care: Internal medicine connects dermatologic procedures with broader health concerns—sleep, nutrition, metabolic status—each influencing recovery timeline and scar quality.
Collaborative roles:
Dr. Cardenas provides medical direction, reviews histories, and creates safe peri-procedural pathways.
I deliver the procedure, chiropractic integration, functional medicine insights, and rehabilitative planning.
Together, we coordinate personal injury processes, documentation, and patient education.
Functional Medicine Integration: Optimizing Healing Physiology
Functional medicine supports the body’s innate healing mechanisms through targeted lifestyle and nutritional strategies tailored to the patient’s biology.
Focus areas:
Inflammation modulation: Adequate omega-3 intake, polyphenols (curcumin, quercetin), and antioxidant-rich foods can support controlled inflammation necessary for healing while preventing prolonged inflammatory states that delay recovery.
Glycemic control: Stable blood sugar supports fibroblast function, collagen cross-linking, and reduces infection risk; critical in older adults and those with metabolic syndrome.
Micronutrient sufficiency: Vitamin C (collagen synthesis), zinc (DNA replication and immune function), and vitamin A (epithelial integrity) are essential. We personalize supplementation cautiously, consistent with medical oversight.
Reasoning:
The acute wound healing phases—hemostasis, inflammation, proliferation, remodeling—depend on energy availability, micronutrient cofactors, and balanced immune signaling. Diet and lifestyle calibrate these processes.
Sleep quality and stress modulation (e.g., paced breathing) influence HPA axis activity and cytokine profiles that can either facilitate or impair tissue repair.
Rehabilitation Strategy: Safe Motion, Scar Care, and Long-Term Outcomes
Rehabilitation begins as soon as the procedure ends.
Key steps:
Early wound protection: Educate on dressing care, signs of infection, and avoiding tension across the incision.
Progressive mobility: Introduce gentle, non-straining movements to prevent stiffness and maintain circulation.
Scar optimization: Once the wound has closed, consider silicone sheeting, gentle massage, and sun protection to improve scar quality.
Ergonomics: Adjust lifting strategies, workstation setup, and daily routines to prevent undue strain near the surgical site.
Physiologic reasoning:
Controlled motion stimulates mechanotransduction pathways in fibroblasts, guiding orderly collagen alignment and increasing tensile strength.
In injury care settings, precision documentation complements clinical excellence:
Clear procedural notes with lesion size, margin plan, anesthesia specifics, and patient responses.
Photo documentation for pre- and post-excision views (when appropriate).
Communication with referring providers and insurers regarding necessity, medical oversight, and outcomes.
Clinical Observations from My Practice
At Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic), I have observed:
Patients experience significantly better comfort with a well-executed field block using 1% lidocaine with epinephrine and adjunct cold spray.
Narrow, well-planned margins for moderate atypia yield high clearance rates while preserving cosmesis.
Integrative chiropractic and functional medicine improve confidence in movement, reduce compensatory pain patterns, and support faster return to normal activities.
Step-by-Step Narrative: From Planning to Excision
Pre-Procedure:
Confirm pathology: dysplastic nevus with moderate atypia.
Explain margins and expectations to the patient.
Prepare sterile field with antiseptic; use alcohol for initial prep and repeat.
Field Block:
Choose entry point; advance needle; inject while withdrawing to create a continuous anesthetic ring.
Turn within the tissue plane to cover both sides without fully removing the needle.
Add lateral points if needed; saturate subcutaneous tissue under the lesion.
Verify numbness; apply cold spray before further injections.
Intradermal Distribution:
Thread the needle across the dermis; visualize tip; inject on withdrawal to form a visible wheal line indicating spread.
Assess patient comfort continuously; recalibrate if sensation persists.
Excision:
Mark ellipse with template; align with skin tension lines.
Excise along just outside the marked borders to respect margins.
Handle tissue gently; orient specimen; achieve hemostasis; close in layers if indicated.
Post-Procedure:
Educate on dressing changes, signs of infection, and motion precautions.
Schedule follow-up for pathology results and suture removal.
Provide integrative guidance on movement, nutrition, sleep, and stress.
Why Each Technique Matters
Template-guided marking: Ensures symmetry, facilitates linear closure, and reduces dog-ears.
Field block with epinephrine: Prolongs anesthesia, reduces bleeding, and improves operative field visibility.
Injecting on withdrawal: Distributes anesthetic evenly and reduces intratissue pressure spikes that can be uncomfortable.
Cold spray: Activates sensory gating to reduce needle pain.
Narrow margins: Balance complete excision of atypia with tissue preservation, aligning with evidence and cosmetic considerations.
Integrative follow-through: Addresses systemic determinants of healing and functional recovery beyond the incision line.
Safety Considerations
Avoid epinephrine in end-arterial regions if risk factors exist; assess peripheral vascular disease.
Screen for lidocaine allergies and arrhythmic history.
Coordinate with internal medicine on anticoagulation decisions and infection-risk mitigation.
Our Team-Based Care in El Paso, Texas
At Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic), our care model weaves together:
Chiropractic care (Dr. Jimenez): Movement analysis, manual therapy, neuromuscular re-education, ergonomic optimization.
Medical oversight (Dr. Cardenas, MD): Risk stratification, medication management, systems-based medical direction.
Functional medicine: Nutrition, sleep, stress, and personalized supplementation.
Rehabilitation: Progressive mobility, scar care, and return-to-function planning.
Personal injury services: Comprehensive documentation, coordination with legal and insurance entities where applicable.
Conclusion: Modern, Evidence-Based, Integrative Care for Skin Surgery
Excision of a dysplastic nevus with moderate atypia is more than a precise cut; it is a coordinated effort grounded in physiology, patient comfort, and multidisciplinary safety. By pairing a pain-free field block with careful margin planning and whole-person support, we improve outcomes and the patient experience. Under the medical direction of Dr. Maria Guadalupe Cardenas, MD, and through our integrative chiropractic, functional medicine, and rehabilitative care, patients receive comprehensive, evidence-based support from diagnosis to recovery.
Learn about effective strategies in functional medicine for managing inflammation and promoting skin health and wellness.
Abstract
In this educational post, I walk you through a real-world clinical demonstration of a shave skin biopsy performed on a middle-aged male patient with an inflamed seborrheic keratosis on the lateral aspect of his right hip. The lesion became progressively noticeable over about four weeks, with inflammation, pain, and enlargement. This post covers the full procedural journey—from initial patient presentation and clinical assessment, through topical and injectable local anesthesia, to the execution of the shave biopsy technique and post-procedural hemostasis with aluminum chloride. I also discuss the physiological reasoning behind each step, the evidence base that supports these methods, and how integrative, multidisciplinary care at Injury Medical Clinic PA in El Paso, Texas — led by me alongside Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine and our Medical Director — shapes how we approach even seemingly straightforward dermatological procedures within the broader context of a patient’s overall health and wellness. Whether you are a clinician, a student, or a curious patient, this post is designed to take you on a clear, comprehensive, and evidence-supported journey through the science and practice of minor dermatological surgery.
Introduction: Why Minor Dermatological Procedures Matter in Integrative Care
When most people think about integrative or chiropractic-based clinics, they often imagine spinal adjustments, soft tissue therapies, and rehabilitation exercises. While those are foundational pillars of what we do at Injury Medical Clinic PA, comprehensive, patient-centered care extends far beyond the spine. As a clinician with dual credentials in chiropractic medicine and advanced practice nursing—and who works every day alongside an experienced internist—I have come to understand that skin health is not a peripheral concern. In many ways, it is a window into the patient’s overall physiological state.
The skin is the body’s largest organ. It is a dynamic, metabolically active tissue that reflects immune function, hormonal balance, inflammatory status, nutritional sufficiency, and circulatory integrity. When a patient presents with a new, enlarging, inflamed skin lesion, this is not merely a cosmetic inconvenience. It is a clinical signal that deserves careful, evidence-based evaluation and, when appropriate, procedural intervention.
In this post, I describe a clinical procedure I performed: a shave skin biopsy of a clinically suspected inflamed seborrheic keratosis on the lateral aspect of the right hip of a middle-aged male patient. The lesion had been present for approximately four weeks before becoming noticeable and symptomatic, and it showed signs of active inflammation, pain, and progressive enlargement. I walk through every step of the procedure, from the rationale for performing it to the anesthetic technique used, the mechanics of the shave biopsy itself, and the hemostatic methods employed at the conclusion.
But I do more than describe what happened. Throughout this post, I integrate the underlying physiology, evidence-based research, and clinical reasoning that guide every decision. I also explain how this type of minor surgical procedure fits within the broader framework of integrative, multidisciplinary care that defines our practice. My goal is to give you — whether you are a fellow clinician, a student, or a patient — a thorough and deeply informative understanding of what happened, why it happened, and what it means in the context of modern, integrative medicine.
Meet the Team: Dr. Alex Jimenez and Dr. Maria Guadalupe Cardenas
Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST
I am Dr. Alex Jimenez. My clinical journey has taken me through chiropractic medicine, advanced practice nursing, functional medicine, integrative medicine, and injury care — among other disciplines. I hold the following credentials: Doctor of Chiropractic (DC), Advanced Practice Registered Nurse (APRN), Family Nurse Practitioner Board Certified (FNP-BC), Certified Functional Medicine Practitioner (CFMP), Institute for Functional Medicine Certified Practitioner (IFMCP), Advanced Triage Nurse (ATN), and Certified Chiropractic Sports Therapist (CCST). This breadth of training reflects my deep commitment to understanding the human body from multiple clinical perspectives and providing care that addresses the root causes of illness and injury, not merely the surface symptoms.
My clinical observations and ongoing educational work are available at chiromed.com and on my LinkedIn profile. I have spent decades building a practice grounded in evidence-based, patient-first principles, integrating chiropractic care with functional medicine, nursing practice, and collaborative medical oversight.
Dr. Maria Guadalupe Cardenas, MD
Working alongside me every day at Injury Medical Clinic PA is Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine, with over 40 years of experience as an internist. Dr. Cardenas holds NPI #1164426749 and a Texas MD License #J2933. In our practice, she serves as Medical Director and Collaborative Physician. This designation reflects both the depth of her clinical expertise and the regulatory framework governing multidisciplinary integrative clinics in Texas.
Dr. Cardenas brings an extraordinary wealth of internal medicine knowledge to our team. As an internist, her training encompasses the prevention, diagnosis, and treatment of adult diseases across virtually every organ system—including the skin, cardiovascular system, endocrine system, gastrointestinal system, and more. Her presence in our clinic ensures that every patient who comes through our doors receives not only the benefits of chiropractic and functional medicine care but also the rigorous medical oversight that complex cases require.
The collaboration between a Doctor of Chiropractic/Advanced Practice Nurse and a Board-Certified Internist is the very essence of what makes our clinic exceptional. This multidisciplinary model is increasingly recognized in the evidence-based literature as the gold standard for integrative and injury care, allowing patients to receive comprehensive, coordinated, and truly holistic treatment under one roof.
Understanding the Clinical Setting: Injury Medical Clinic PA
Injury Medical Clinic PA, also known as Mission Plaza Injury Medical Clinic, is located in El Paso, Texas. Our clinic is a multidisciplinary integrative care facility that provides a wide spectrum of services, including:
Chiropractic care and spinal manipulation
Advanced practice nursing and family medicine
Internal medicine oversight and medical direction
Functional medicine and nutritional therapy
Personal injury care and accident rehabilitation
Minor surgical procedures and dermatological care
Diagnostic imaging and laboratory services
Physical rehabilitation and corrective exercise
The multidisciplinary model we operate under is not merely administrative convenience — it is a clinically superior approach to patient care. Research consistently shows that patients who receive care from coordinated, multidisciplinary teams experience better outcomes, shorter recovery times, lower rates of chronic pain progression, and higher patient satisfaction than those who receive siloed, single-discipline care (Körner et al., 2016; Stochkendahl et al., 2017).
In the context of the procedure described in this post, the clinical setting matters profoundly. A minor dermatological procedure like a shave skin biopsy is performed not in isolation, but within a broader clinical picture. Dr. Cardenas’s medical oversight ensures that any systemic conditions — such as diabetes, autoimmune disorders, coagulopathies, or medication interactions — that might affect wound healing or anesthetic response are carefully considered before the procedure begins. My training as an APRN and FNP-BC means I can assess, diagnose, and treat conditions across multiple body systems, ensuring the dermatological finding is evaluated in the context of the whole patient.
Patient Presentation: The Middle-Aged Male with a Lateral Hip Skin Lesion
The patient who came to us on this occasion was a middle-aged male presenting with a skin lesion over the lateral aspect of his right hip. He reported that the lesion had become significantly noticeable over the preceding four weeks. During that time, he observed progressive enlargement, local inflammation, and the onset of pain in the area.
Key Clinical Features at Presentation
Location: Lateral aspect of the right hip
Duration of noticeable change: Approximately four weeks before the visit date of September 1, 2026, meaning symptoms began around early August 2026
Symptoms: Inflammation, pain, and enlargement of the lesion
Clinical appearance: Consistent with an inflamed seborrheic keratosis
Why the History and Timeline Matter
The four-week timeline matters for several reasons. Seborrheic keratoses are benign epidermal tumors that typically grow slowly over years. When a patient reports a sudden increase in size, inflammation, and pain over a period of weeks, this raises the clinical question of whether the lesion has become irritated or inflamed due to friction, trauma, or clothing contact — all of which are common at the lateral hip — or whether the clinical picture warrants concern for a more serious pathology, such as squamous cell carcinoma, basal cell carcinoma, or melanoma.
The principle here is the “ABCDE” rule for skin lesion evaluation: Asymmetry, Border irregularity, Color variation, Diameter greater than 6mm, and Evolution (change over time). The “E” — evolution — is arguably the most clinically alarming feature, because change in a skin lesion is always a reason to investigate further (Abbasi et al., 2004). In this case, the rapid change over four weeks, combined with inflammation and pain, was the primary driver for proceeding with a biopsy.
The Role of Pain and Inflammation
Pain in a seborrheic keratosis is noteworthy. Most seborrheic keratoses are entirely asymptomatic. When a patient reports pain, this typically indicates one of the following:
Mechanical irritation — repeated friction against clothing, a waistband, or a belt, which is particularly common at the lateral hip
Secondary inflammation — the body’s immune response to an injured or irritated keratinocyte population
Secondary infection — less common but possible if the surface of the lesion has been broken
Underlying epidermal or dermal pathology — warranting biopsy to rule out malignancy
Regardless of the underlying cause, the combination of enlargement, inflammation, and pain in a skin lesion over four weeks establishes a clear clinical indication for tissue sampling and histopathological analysis — in other words, a biopsy.
What Is Seborrheic Keratosis? A Deep Dive into the Pathophysiology
Seborrheic keratosis (SK) is one of the most common benign epidermal neoplasms encountered in clinical practice. Understanding the pathophysiology of SK is essential for appreciating why it can become inflamed, painful, and enlarged, and why biopsy is sometimes necessary to confirm the diagnosis.
Epidemiology and Prevalence
Seborrheic keratoses affect individuals of all races and ethnicities, but they are most prevalent in adults over the age of 50. By the seventh decade of life, virtually all adults have at least one seborrheic keratosis (Gill et al., 2000). They can appear anywhere on the body except the palms and soles, with the trunk, face, scalp, and extremities being the most common locations. The lateral hip — the location of our patient’s lesion — is a clinically plausible site, particularly given the mechanical friction to which this area is routinely subjected.
Histopathological Features
At the microscopic level, seborrheic keratoses are characterized by:
Acanthosis — thickening of the epidermis due to proliferation of keratinocytes and basaloid cells
Hyperkeratosis — an excess of keratin on the surface of the lesion
Papillomatosis — irregular upward projections of the epidermal surface
Horn cysts — invaginations of keratin-filled cysts within the lesion
Flat base — the lesion grows upward from the skin surface, not downward into the dermis, which is why it appears “stuck on” clinically
These histopathological features explain the characteristic clinical appearance of SK: a waxy, “stuck-on” lesion with a rough, warty texture, ranging in color from light tan to dark brown or black.
Molecular Pathogenesis
The molecular underpinnings of seborrheic keratosis have been increasingly well characterized in recent years. Research has identified somatic mutations in the FGFR3 (Fibroblast Growth Factor Receptor 3) and PIK3CA genes as the most frequently implicated genetic alterations in SK development (Hafner et al., 2007). These mutations constitutively activate cell proliferation pathways—specifically the RAS/MAPK and PI3K/AKT signaling cascades—resulting in the uncontrolled but benign proliferation of keratinocytes that defines the lesion.
Importantly, these are somatic mutations, meaning they arise in individual skin cells over a lifetime and are not inherited. This explains why SK prevalence increases dramatically with age: over decades, accumulating UV radiation exposure, oxidative stress, and DNA repair inefficiencies contribute to the accrual of these mutations in keratinocytes (Hafner et al., 2009).
Why Does Seborrheic Keratosis Become Inflamed?
Inflammation in a seborrheic keratosis is not uncommon and can arise through several mechanisms:
1. Mechanical Irritation and the Koebner Phenomenon
The Koebner phenomenon refers to the development of new skin lesions at sites of trauma or mechanical irritation in individuals who are predisposed to certain skin conditions. In the context of SK, repeated mechanical friction — particularly from clothing, waistbands, or physical activity — can trigger an inflammatory cascade within the lesion. The keratinocytes within the SK release pro-inflammatory cytokines, including interleukin-1 (IL-1), interleukin-6 (IL-6), and tumor necrosis factor-alpha (TNF-α), which recruit immune cells to the area and produce the classic signs of inflammation: redness, swelling, warmth, and pain (Baroni et al., 2012).
2. Immune Cell Infiltration
Histopathological studies of inflamed seborrheic keratoses have demonstrated significant lymphocytic infiltration — an influx of T lymphocytes into the lesion — which can lead to what is sometimes called “irritated seborrheic keratosis” or “inflamed SK”. In some cases, this lymphocytic infiltration can actually lead to partial regression of the lesion, a process that mirrors the immune-mediated destruction of neoplastic tissue (Yeh et al., 2000).
3. Secondary Infection
If the surface of the seborrheic keratosis is disrupted—through scratching, friction, or minor trauma—bacteria can colonize the damaged keratin layer, triggering a secondary infectious inflammatory response. This is more common in lesions located in areas of high friction or moisture.
4. The Sign of Leser-Trélat
In rare cases, the sudden onset of multiple new seborrheic keratoses — or the rapid enlargement of existing ones — is associated with internal malignancy, a phenomenon known as the Sign of Leser-Trélat (Schwartz, 1996). While this sign is uncommon and its clinical reliability has been debated in the literature, it underscores the importance of evaluating rapidly changing seborrheic keratoses in the context of the patient’s overall health. Dr. Cardenas’s internist oversight at our clinic is particularly valuable in these cases, as an experienced internist is well positioned to evaluate for systemic signs of malignancy.
Clinical Evaluation and Differential Diagnosis of Skin Lesions
Before proceeding to any skin biopsy, a thorough clinical evaluation is essential. The differential diagnosis for an inflamed, enlarging skin lesion at the lateral hip in a middle-aged male is broad and includes both benign and malignant entities.
Benign Differential Diagnoses
Seborrheic keratosis (inflamed) — the leading clinical diagnosis in this case
Dermatofibroma — a benign fibrous nodule of the dermis, often found on the lower extremities
Epidermoid cyst (inflamed) — a cystic structure containing keratin, which can become inflamed or infected
Lipoma — a benign subcutaneous tumor composed of mature adipocytes
Verruca vulgaris (common wart) — caused by Human Papillomavirus (HPV), can occur at any site
Sebaceous hyperplasia — an overgrowth of sebaceous glands, more common on the face
Pigmented nevus (mole) — a benign melanocytic lesion that may enlarge and become inflamed
Malignant and Pre-Malignant Differential Diagnoses
Actinic keratosis — a pre-malignant lesion caused by chronic UV exposure, which can progress to squamous cell carcinoma
Squamous cell carcinoma (SCC) — a malignant tumor of keratinocytes; can mimic an inflamed seborrheic keratosis clinically
Basal cell carcinoma (BCC) — the most common skin cancer; can present as a pearly, raised nodule with surface changes
Melanoma — the most dangerous skin cancer; can present as a changing pigmented lesion
Merkel cell carcinoma — a rare but aggressive neuroendocrine skin tumor
Cutaneous lymphoma — lymphomatous infiltration of the skin
The clinical appearance — a “stuck-on,” waxy, hyperpigmented lesion with a rough surface — strongly suggests seborrheic keratosis in this case. However, the recent rapid change, including enlargement, inflammation, and pain over four weeks, means that clinical diagnosis alone is insufficient. The gold standard for definitive diagnosis of any skin lesion is histopathological examination of a tissue specimen — which is exactly why the shave biopsy was performed.
Dermoscopy as a Complementary Tool
Modern clinical practice increasingly employs dermoscopy (also called dermatoscopy) as a non-invasive adjunct to clinical evaluation of skin lesions. Dermoscopy uses a handheld polarized light microscope to visualize subsurface skin structures that are invisible to the naked eye. In seborrheic keratosis, dermoscopic features include milia-like cysts, comedo-like openings, fissures and ridges, and cerebriform patterns (Braun et al., 2005). The absence of these features — or the presence of melanoma-associated features — would strengthen the case for urgent biopsy and potential oncological referral.
Indications for Shave Skin Biopsy
A shave biopsy is one of several biopsy techniques used in dermatological practice. Understanding when and why a shave biopsy is the appropriate choice — rather than a punch biopsy, excisional biopsy, or incisional biopsy — is essential for appreciating the clinical reasoning in this case.
Types of Skin Biopsy Techniques
1. Shave Biopsy
A shave biopsy uses a surgical blade or razor to horizontally “shave” the lesion from the skin surface. It is ideally suited for:
Exophytic lesions — lesions that project above the skin surface, such as seborrheic keratoses, viral warts, and skin tags
Superficial lesions — where the pathology is confined to the epidermis and superficial dermis
Lesions where full excision is not necessary — particularly when the primary goal is diagnosis rather than complete removal
2. Punch Biopsy
The punch biopsy uses a circular cutting tool to remove a cylindrical core of full-thickness skin. It is preferred for:
Inflammatory dermatoses — conditions like psoriasis, lichen planus, or eczema, where the pathology spans the full thickness of the skin
Lesions where dermal involvement needs to be assessed
Alopecia and scalp conditions
3. Excisional Biopsy
The excisional biopsy removes the entire lesion with a margin of normal tissue. It is indicated when:
Complete removal is both diagnostic and therapeutic — as in suspected melanoma, where complete excision with margins is the standard of care
The lesion is small enough to excise completely
4. Incisional Biopsy
The incisional biopsy removes only a portion of a large lesion. It is used when:
The lesion is too large to excise completely
A representative sample is needed for diagnosis
Why a Shave Biopsy Was Appropriate in This Case
For the patient described — with a clinically suspected inflamed seborrheic keratosis that was exophytic (projecting above the skin surface) and located in a non-cosmetically critical area — the shave biopsy was the ideal technique for the following reasons:
The lesion is epidermal in origin — seborrheic keratoses are confined to the epidermis and do not invade the dermis, making a superficial shave technique sufficient to obtain a diagnostic sample
The technique allows for rapid removal with minimal tissue trauma and a small, cosmetically acceptable wound
The exophytic nature of the lesion means that a horizontal cut at the base of the lesion will capture the entire pathological tissue.
The intradermal wheal technique (described below) physically elevates the lesion, making it easier to perform a clean, complete shave with precise margins.
The hemostatic properties of aluminum chloride make this technique safe and efficient in an outpatient setting without the need for sutures.
The Science of Local Anesthesia: Pain Ease Mist and Lidocaine with Epinephrine
One of the most important aspects of any minor surgical procedure is pain management. The goal of local anesthesia is to render the procedural site completely insensate — free from pain — without affecting the patient’s consciousness or systemic physiology. In this procedure, two anesthetic agents were used complementarily: Pain Ease mist (a topical cryogenic spray) and 1% lidocaine with epinephrine (an injectable local anesthetic).
Pain Ease Mist: Topical Cryotherapy for Needle Phobia and Surface Anesthesia
Pain Ease Mist is a commercially available topical cryogenic spray (also known as a “vapocoolant spray”) that works by rapidly cooling the skin surface through the evaporation of a volatile liquid — typically a mixture of 1,1,1,3,3-pentafluoropropane and 1,1,1,2-tetrafluoroethane. The rapid evaporation of these compounds extracts heat from the skin surface, producing a brief but intense cooling sensation that temporarily numbs the superficial nerve endings.
Mechanism of Action
Cryogenic sprays produce surface anesthesia by thermally modulating cutaneous nociceptors. Pain is transmitted from the skin to the central nervous system via nociceptive afferent nerve fibers — primarily A-delta fibers (which transmit sharp, fast pain) and C-fibers (which transmit slow, burning, or aching pain). Both of these fiber types are exquisitely sensitive to temperature changes.
When skin temperature drops rapidly below about 10°C, voltage-gated sodium channels in nociceptive nerve endings become transiently inactivated. These sodium channels are essential for the generation of action potentials — the electrical signals that carry pain information along the nerve fiber. When cold blocks them, the nociceptive fiber cannot fire, and the sensation of pain is temporarily abolished (Bleakley et al., 2012).
Clinical Application in This Procedure
In this procedure, the Pain Ease mist was applied to the skin before needle insertion to blunt the pain of the initial puncture. This is a particularly thoughtful approach to patient care. Needle phobia — technically termed trypanophobia — is one of the most common procedural fears among patients, and even in patients who do not have a formal phobia, the anticipation of needle pain can trigger significant anxiety, which in turn increases pain perception through central sensitization mechanisms (Taddio et al., 2009).
By pre-treating the skin with a vapocoolant spray, I was able to:
Reduce the pain of the initial needle insertion
Reduce patient anxiety about the procedure
Create a more relaxed procedural environment, which itself reduces pain perception
This is an excellent example of how integrative, patient-centered care — which prioritizes the patient’s comfort and experience alongside clinical efficacy — shapes procedural decisions.
Lidocaine with Epinephrine: The Gold Standard Injectable Local Anesthetic
Lidocaine is the most widely used local anesthetic in clinical practice worldwide. It belongs to the amide class of local anesthetics, characterized by stability, low allergenic potential, and reliable onset of action.
Mechanism of Action of Lidocaine
Lidocaine produces local anesthesia by blocking voltage-gated sodium channels in the axonal membranes of peripheral nerve fibers. When these channels are blocked, the nerve cannot generate or propagate action potentials, and all sensory modalities — including pain, temperature, touch, and pressure — are temporarily abolished in the distribution of the affected nerve.
At the molecular level, lidocaine enters the sodium channel from the intracellular side of the nerve membrane — meaning it must first cross the nerve cell membrane to reach its binding site. It does this in its uncharged (base) form, which is lipid-soluble and can diffuse through the lipid bilayer. Once inside the cell, it becomes partially ionized (charged) at physiological pH and binds to the alpha subunit of the voltage-gated sodium channel in its open or inactivated state, preventing the channel from reopening and thus blocking nerve conduction (Catterall et al., 2005).
This mechanism explains an important clinical observation: lidocaine is less effective in infected or inflamed tissue, because the acidic environment of infected tissue (lower pH) favors the ionized form of lidocaine, which cannot cross the nerve membrane as easily. This is a critical consideration when anesthetizing inflamed lesions like the one in this case, and it reinforces the importance of using an adequate volume and correct placement to achieve reliable anesthesia despite potential local acidosis.
The Role of Epinephrine
The addition of epinephrine (adrenaline) to the lidocaine solution serves several important functions:
1. Vasoconstriction and Prolonged Anesthetic Duration
Epinephrine is a potent alpha-1 adrenergic receptor agonist that causes vasoconstriction — narrowing of local blood vessels — at the injection site. This vasoconstriction reduces systemic absorption of lidocaine, keeping the anesthetic concentrated at the site of action longer. The result is a significantly prolonged duration of local anesthesia — from approximately 30-60 minutes with plain lidocaine to 90-120 minutes or more with lidocaine-epinephrine (Becker & Reed, 2012).
2. Reduced Bleeding
Epinephrine-induced vasoconstriction also reduces bleeding at the procedural site. This is particularly beneficial during a shave biopsy, where a clean, blood-free operative field is essential for accurate margin assessment and specimen quality.
3. Reduced Systemic Toxicity
By slowing systemic absorption, epinephrine reduces the risk of local anesthetic systemic toxicity (LAST) — a rare but potentially life-threatening complication of local anesthetic administration that can cause cardiac arrhythmias and central nervous system toxicity when plasma lidocaine levels exceed a critical threshold (Neal et al., 2018).
Concentration and Volume
In this procedure, 1% lidocaine with epinephrine was used, and approximately 1 mL was injected. The 1% concentration means that the solution contains 10 mg of lidocaine per milliliter. Therefore, 1 mL delivers 10 mg of lidocaine — a dose well within the safe therapeutic range for a local infiltration in an adult patient. The maximum safe dose of lidocaine with epinephrine is generally cited as 7 mg/kg, meaning even a small adult patient would have a maximum dose of 350 mg or more, making a 10 mg dose extraordinarily safe (Becker & Reed, 2012).
Needle Selection and Injection Technique: The 30-Gauge Half-Inch Needle
Selecting a 30-gauge, half-inch needle for this procedure reflects a deliberate, evidence-informed clinical decision.
Understanding Needle Gauge and Length
Needles are classified by their gauge (a measure of diameter, where higher gauge numbers indicate thinner needles) and their length (expressed in inches or millimeters). A 30-gauge needle has an outer diameter of approximately 0.31 mm, making it one of the thinnest needles commonly used in clinical practice. A half-inch (12.7 mm) length is appropriate for subcutaneous and intradermal injections in most body sites.
Why a 30-Gauge Needle?
The primary reason for selecting a thin 30-gauge needle for this procedure is patient comfort. The relationship between needle gauge and pain is well established in the literature: thinner needles cause less pain upon insertion, because they displace less tissue and engage fewer nociceptive nerve endings in the skin (Gill & O’Brien, 2007). For a procedure where the injection itself is the most acutely painful component, minimizing needle gauge is an important element of patient-centered procedural care.
A 30-gauge needle is also entirely adequate for delivering the small volume (1 mL) of fluid used in this procedure. The viscosity of the lidocaine-epinephrine solution is low enough that it flows freely through a 30-gauge needle without excessive injection pressure.
The Two-Phase Injection Technique
An important feature of the injection technique described in this procedure is its two-phase approach:
Phase 1: Subcutaneous Injection
The needle is first inserted perpendicularly into the skin and advanced into the subcutaneous tissue — the loose connective tissue layer beneath the dermis. A portion of the lidocaine solution is deposited here. This deep deposition ensures that the larger nerve branches supplying the area are anesthetized first, which facilitates the subsequent intradermal injection by pre-treating the deeper nociceptive pathways.
Phase 2: Intradermal Injection (Wheal Formation)
Without withdrawing the needle from the skin, redirect it horizontally— rotate it to run parallel to the skin surface — and advance it intradermally, directly beneath the lesion. The remaining lidocaine solution is then injected here to form an intradermal wheal — a raised, pale, blister-like elevation of the skin caused by the fluid expanding the intradermal compartment.
This two-phase technique is superior to a single-depth injection for several reasons:
It ensures complete anesthesia of all skin layers — both the deeper subcutaneous tissue and the superficial intradermal compartment where the lesion is rooted
It creates the intradermal wheal, which is mechanically essential for the shave biopsy technique (as described in the next section)
The subcutaneous injection first creates baseline anesthesia that makes the subsequent intradermal injection less painful for the patient.
The clinical observation during this procedure — that the patient reported no pain during both phases of the injection — validates the effectiveness of the Pain Ease pre-treatment and the careful, deliberate injection technique employed.
Subcutaneous vs. Intradermal Injection: Understanding the Layers of the Skin
To fully appreciate the technical nuances of the injection technique used in this procedure, you need a thorough understanding of the skin’s anatomical layers and the physiological differences between subcutaneous and intradermal injection.
The Architecture of the Skin
The skin is organized into three primary layers, each with distinct anatomical and physiological characteristics:
1. The Epidermis
The epidermis is the outermost layer of the skin, ranging in thickness from approximately 0.05 mm (on the eyelids) to 1.5 mm (on the palms and soles). It is composed primarily of keratinocytes — the cells responsible for producing keratin, the structural protein that gives skin its barrier function. The epidermis is avascular (contains no blood vessels) and receives nutrients and oxygen by diffusion from the underlying dermis.
The epidermis is organized into five layers (from deep to superficial):
Stratum basale — the deepest layer, containing mitotically active stem cells
Stratum spinosum — the “prickle cell” layer, where keratinocytes begin to produce keratin
Stratum granulosum — where keratinocytes begin to flatten and produce lipid-rich lamellar granules
Stratum lucidum — present only in thick skin (palms and soles); a clear, homogeneous layer
Stratum corneum — the outermost layer, composed of dead, flattened keratinocytes (corneocytes) filled with keratin
Seborrheic keratoses originate in the epidermis — they are a proliferation of the keratinocyte population within the epidermal layers, and they project upward from the skin surface without penetrating the dermis.
2. The Dermis
The dermis lies immediately beneath the epidermis and is separated from it by the dermal-epidermal junction (DEJ). The dermis is a highly vascularized layer of connective tissue composed primarily of collagen and elastin fibers, embedded in a proteoglycan-rich extracellular matrix. It contains blood vessels, lymphatic vessels, nerve fibers, hair follicles, sweat glands, and sebaceous glands.
The dermis is subdivided into:
Papillary dermis — the superficial portion, which projects upward into the epidermis as dermal papillae and contains fine collagen fibers, capillary loops, and nerve endings
Reticular dermis — the deeper, thicker portion, composed of coarser collagen bundles and elastic fibers, providing the skin’s tensile strength
Intradermal injection delivers fluid into the papillary and superficial reticular dermis, producing the characteristic wheal by expanding this compartment.
3. The Hypodermis (Subcutaneous Tissue)
The hypodermis lies beneath the dermis and consists primarily of adipose tissue (fat cells) interspersed with connective tissue septa. It provides thermal insulation, mechanical cushioning, and serves as an energy reservoir. Subcutaneous injection delivers fluid into this layer.
Why the Intradermal Wheal Is the Key to the Shave Biopsy
The intradermal wheal created by the injection is not merely an anesthetic technique — it is a mechanical tool that fundamentally enhances the shave biopsy procedure. By expanding the intradermal compartment directly beneath the seborrheic keratosis, the wheal accomplishes two critical objectives:
1. Physical Elevation of the Lesion
The wheal raises the lesion above the surrounding skin surface, making it more prominent and accessible. This elevation means that the biopsy blade does not need to be angled downward into the skin to capture the lesion — it can instead be directed horizontally across the elevated lesion base, reducing the risk of either under-sampling (leaving residual lesion tissue) or over-sampling (cutting too deeply into the dermis and creating an unnecessary wound).
2. Creation of a Firm, Stable Platform
The turgid, fluid-filled wheal also creates a firmer, more stable base beneath the lesion, which facilitates a smooth, controlled biopsy motion. Without the wheal, the soft, compressible superficial dermis can make it difficult to maintain consistent blade depth during the shave.
This technique — using the intradermal wheal both for anesthesia and as a mechanical adjunct to the biopsy — exemplifies the elegance of evidence-based procedural medicine: a single intervention (the intradermal injection) achieves multiple clinical goals simultaneously.
The Intradermal Wheal: Why Elevation of the Lesion Matters
The observation in the clinical demonstration that the intradermal wheal was “actually elevating the lesion toward us, so that presents it to us” is not a casual comment — it reflects a fundamental principle of shave biopsy technique that is grounded in biomechanics and tissue physiology.
The Biomechanics of Wheal Formation
When fluid is injected into the intradermal compartment, it must displace surrounding tissue to create space. Because the epidermis above is relatively inelastic and the reticular dermis below is dense, the path of least resistance for the injected fluid is upward and laterally, producing the characteristic dome-shaped wheal.
The pressure generated by the fluid within the wheal — typically estimated at 20-40 mmHg above atmospheric pressure in an actively injected wheal — is sufficient to lift the overlying epidermis and any attached epidermal tumor (such as the seborrheic keratosis) away from the underlying dermis. This lifting effect is visually apparent: the skin overlying the injection site blanches (due to local vasoconstriction from the epinephrine and compression of the superficial capillaries) and rises above the surrounding skin level.
Clinical Significance for Specimen Quality
From a pathological standpoint, the elevation of the lesion produced by the wheal is highly beneficial for specimen quality. A shave biopsy specimen that includes a generous portion of the base of the lesion — the intradermal-epidermal junction — is far more diagnostically valuable than one that captures only the superficial portion. The wheal ensures that the biopsy blade, traveling horizontally at the elevated lesion base, captures this interface reliably.
A high-quality specimen allows the pathologist to assess:
The depth of epidermal involvement
The presence or absence of dermal invasion — the most critical feature for distinguishing benign SK from malignant entities like squamous cell carcinoma in situ (Bowen’s disease) or invasive SCC
The nature of any inflammatory infiltrate
The presence of atypical keratinocytes that might suggest pre-malignant or malignant transformation
Performing the Shave Biopsy: Technique, Precision, and Margins
With the intradermal wheal established and the lesion fully elevated and anesthetized, the shave biopsy proceeds. The technique used in this procedure—beginning the cut about two millimeters lateral to the lesion—reflects careful attention to both diagnostic completeness and cosmetic outcome.
The “Two Millimeters Lateral” Principle
Starting the shave cut two millimeters lateral to the visible border of the lesion serves several important purposes:
1. Ensuring Complete Lesion Capture
The visible border of a seborrheic keratosis is not always the true border of the pathological process. Microscopic extensions of the lesion — subclinical keratinocyte proliferation that is not visible to the naked eye — can extend a small distance beyond the visible edge. By starting the cut 2 mm outside the visible margin, the clinician ensures the specimen includes all pathological tissue, even if microscopic extensions exist.
2. Avoiding Specimen Fragmentation
If the biopsy blade is introduced at the exact edge of the lesion, there is a risk of fragmenting the specimen — splitting the lesion into pieces that may be difficult to orient and analyze histopathologically. Starting two millimeters beyond the edge ensures a smooth, continuous cut through the lesion from one side to the other.
3. Margin Assessment
In cases where the histopathological findings reveal a pre-malignant or malignant process — a possibility that cannot be excluded until the specimen is analyzed — having a two-millimeter margin of normal-appearing skin at the lateral edges of the specimen provides the pathologist with a baseline for assessing whether the abnormal process extends to the specimen edges (positive margins) or is contained within the specimen (negative margins).
The Shave Cut Itself
The shave cut is performed using a scalpel blade or a specialized razor blade held parallel to the skin surface. The blade is moved in a smooth, continuous motion from one side of the elevated lesion to the other, cutting at the level of the papillary-reticular dermis junction — superficial enough to avoid unnecessary dermis removal, but deep enough to capture the full base of the epidermal lesion.
In experienced hands, the shave biopsy is a rapid procedure—the cutting motion typically takes only a few seconds. The speed is not merely cosmetic convenience; a smooth, rapid cut produces a cleaner specimen with less crush artifact than a slow, sawing motion, which can distort tissue architecture and compromise histopathological interpretation.
Confirmation of Completeness
After removing the specimen, the wound bed is inspected to confirm that no lesion tissue remains. In this procedure, the clinical confirmation was explicit: “All the way through, no lesion is left there on the skin.” This confirmation step is important because residual lesion tissue can:
Lead to recurrence of the lesion
Potentially harbor pathology that was not captured in the initial specimen
Cause delayed healing or persistent inflammation
Hemostasis with Aluminum Chloride: Mechanisms and Clinical Rationale
After specimen removal, the next clinical priority is hemostasis—stopping bleeding from the wound bed. In this procedure, aluminum chloride was used for this purpose.
What Is Aluminum Chloride?
Aluminum chloride is an inorganic compound with the formula AlCl₃. In dermatological practice, it is used as a hemostatic agent — a substance that promotes blood clotting — in the form of a concentrated aqueous solution (typically 20-35% aluminum chloride in absolute ethyl alcohol, sometimes referred to as “Monsel’s solution” or “Drysol” in various clinical formulations, though these have distinct compositions; the aluminum chloride-ethanol formulation is the most commonly used hemostatic agent in dermatological surgery).
Mechanism of Action
The hemostatic action of aluminum chloride is primarily physical/chemical rather than enzymatic. It acts through the following mechanisms:
1. Protein Precipitation
Aluminum ions (Al³⁺) are strongly astringent — they react with proteins in the serum and on the surface of endothelial cells to cause protein precipitation. This precipitation forms a physical plug in the small capillaries and arterioles at the wound surface, mechanically occluding blood flow.
2. Vasoconstriction
The astringent effect of aluminum chloride also causes contraction of the walls of small blood vessels at the wound site, reducing blood flow to the area. This vasoconstriction is transient but sufficient to allow the body’s own hemostatic mechanisms — platelet aggregation and fibrin clot formation — to complete the process.
3. Desiccation of the Wound Surface
The alcohol component of the aluminum chloride solution promotes desiccation (drying) of the wound surface, which reduces the amount of fluid available to sustain bleeding and promotes the formation of a stable, dry eschar (scab) over the wound.
Application Technique
In this procedure, the aluminum chloride was applied by saturating a gauze pad with the solution and applying it to the wound surface. The gauze is pressed firmly against the bleeding wound for approximately 30-60 seconds, during which time the protein precipitation and vasoconstriction occur and bleeding is arrested.
The observation that “The bleeding has stopped” after application confirms the technique’s effectiveness and supports the clinical rationale for using aluminum chloride in this context.
Advantages Over Other Hemostatic Methods
In a minor dermatological procedure like a shave biopsy, aluminum chloride offers several important advantages over alternative hemostatic methods:
No sutures required — the wound created by a shave biopsy is typically shallow and small enough that aluminum chloride hemostasis is sufficient, eliminating the need for sutures and their associated discomfort, risk of infection, and need for a return visit for removal
Rapid action — bleeding is typically arrested within 30-60 seconds
Low risk of scarring — unlike electrocautery or ferric subsulfate (Monsel’s solution), aluminum chloride generally produces minimal tissue damage and a low risk of post-inflammatory hyperpigmentation or scarring.
Ease of use — it can be applied with a cotton-tipped applicator or gauze pad without specialized equipment.
Safe in the outpatient setting — no electrical equipment, no flame, no specialized training required beyond standard procedural competency
Comparison with Electrocautery
Electrocautery (or electrocoagulation) is another commonly used hemostatic method in skin surgery. It works by applying electrical current to the wound surface, which heats the tissue and causes thermal coagulation of blood proteins. While electrocautery is effective, it has several disadvantages compared to aluminum chloride in the context of a shave biopsy:
It requires specialized electrical equipment.
It can cause thermal artifact in adjacent tissue, which can distort histopathological interpretation if applied before the specimen is removed.
It carries a small but real risk of electrical burns if used near metal implants or pacemakers.
The smell of burning tissue can be unpleasant for the patient
Aluminum chloride avoids all of these concerns, making it the preferred hemostatic agent for most minor dermatological procedures in an outpatient integrative care setting.
Post-Procedural Care and Sterile Packaging
Sterile Packaging of the Specimen
Once the specimen is excised and hemostasis is achieved, package and preserve the biopsy specimen properly for pathological analysis. The standard method is to place the specimen in a container of 10% neutral buffered formalin, which acts as a fixative—it cross-links proteins in the tissue, preserving cellular architecture and preventing autolytic degradation that would occur if the tissue were allowed to dry or remain at physiological conditions.
The formalin-fixed specimen is then submitted to a pathology laboratory with a requisition form documenting:
Patient demographics
Clinical diagnosis and differential diagnoses
Site and method of biopsy
Relevant clinical history (duration of lesion, rate of change, symptoms)
Requesting clinician information
This information is essential for the pathologist to provide a clinically relevant interpretation of the histological findings.
Wound Care Instructions
After the procedure, the patient receives wound care instructions to promote healing and prevent infection. Standard instructions for a shave biopsy wound include:
Keep the wound clean and moist — apply a thin layer of petroleum jelly (Vaseline) or antibiotic ointment (such as bacitracin) and cover with a non-stick dressing for 24-48 hours
Change the dressing daily — remove the old dressing, gently clean the wound with mild soap and water, and reapply the ointment and dressing.
Avoid submerging the wound in water (baths, pools, hot tubs) until the wound is fully healed — typically 7-14 days.
Avoid vigorous physical activity that might cause friction or trauma to the wound site.
Watch for signs of infection — increasing redness, warmth, swelling, purulent discharge, or fever — and return to the clinic immediately if these develop.
Expect a small scar — the wound will initially form a scab (eschar), which will fall off within 1-2 weeks, leaving a small, pink, flat scar that will gradually fade over several months.
Healing Physiology
The wound healing process at a shave biopsy site proceeds through the classic four phases of wound healing:
1. Hemostasis (0-24 hours)
Immediately after tissue injury, platelet aggregation and coagulation cascade activation form a fibrin clot at the wound surface. Aluminum chloride supports this phase by precipitating proteins and causing vasoconstriction to slow bleeding.
2. Inflammation (1-5 days)
Immune cells — primarily neutrophils in the first 24-48 hours, followed by macrophages — migrate to the wound site and clear debris, bacteria, and damaged tissue. This phase is characterized by the classic signs of inflammation: redness, swelling, warmth, and discomfort at the wound site.
3. Proliferation (5-21 days)
Fibroblasts migrate into the wound and begin synthesizing new collagen, gradually replacing the fibrin clot with a provisional extracellular matrix. Simultaneously, keratinocytes at the wound edges begin migrating across the wound surface to re-establish the epidermal layer — a process called re-epithelialization.
4. Remodeling (21 days to 2 years)
The provisional collagen matrix is gradually remodeled into a more organized, mature collagen structure. The wound contracts, the scar matures and fades, and the tensile strength of the repaired tissue gradually increases toward (but typically not reaching) the pre-injury level.
Pathological Analysis: What Happens After the Specimen Is Collected
The journey of the biopsy specimen from the clinical setting to the pathology report is a fascinating and clinically critical process. Understanding what happens to the tissue after it leaves the clinic helps clinicians communicate more effectively with pathologists and interpret reports more accurately.
Grossing (Macroscopic Examination)
Upon receipt in the pathology laboratory, the specimen undergoes gross examination — a macroscopic inspection by the pathologist or pathology technician. For a shave biopsy specimen, this involves documenting:
The size and shape of the specimen
The surface characteristics (color, texture, presence of pigmentation)
The cut sections (appearance of the tissue on cross-section)
Tissue Processing
The formalin-fixed specimen is then embedded in paraffin wax to create a solid block from which thin tissue sections can be cut. The embedding process involves:
Dehydration — the tissue is passed through a series of increasingly concentrated alcohol solutions to remove water
Clearing — the alcohol is replaced with a clearing agent (typically xylene) that is miscible with paraffin
Infiltration and embedding — the clearing agent is replaced with melted paraffin wax, which solidifies around the tissue, creating a firm block
Microtomy and Staining
The paraffin block is then sectioned using a microtome—a precision cutting instrument—into sections 3- 5 micrometers thick. These sections are mounted on glass slides and stained with hematoxylin and eosin (H&E), the standard stain for histopathological examination.
Hematoxylin stains nuclei blue-purple
Eosin stains cytoplasm and extracellular matrix pink-red
The pathologist then examines the H&E-stained slides under the microscope.
What the Pathologist Looks For
In a specimen from a clinically suspected inflamed seborrheic keratosis, the pathologist examines:
Features Supporting the Diagnosis of Seborrheic Keratosis:
Acanthosis — epidermal thickening with keratinocyte proliferation
Hyperkeratosis — excess keratin on the surface
Papillomatosis — upward projections of the epidermis
Horn cysts — keratin-filled invaginations within the epidermis
No dermal invasion — the basement membrane is intact, confirming the benign, epidermal nature of the lesion
Features of Inflammation:
Lymphocytic infiltrate in the superficial dermis and within the lesion
Spongiosis — epidermal edema
Neutrophilic infiltrate if secondary infection is present
Features That Would Require Further Action:
Atypical keratinocytes — cells with enlarged, irregular nuclei — could indicate actinic keratosis or squamous cell carcinoma in situ
Full-thickness epidermal atypia — diagnostic of Bowen’s disease (SCC in situ)
Dermal invasion — diagnostic of invasive squamous cell carcinoma
Atypical melanocytes — could indicate melanoma
Positive margins — residual pathological tissue at the edges of the specimen
The pathology report generated after this analysis is the definitive clinical answer to the diagnostic question posed by the biopsy.
Pain Management in Minor Surgical Procedures: An Integrative Perspective
Pain management in minor surgical procedures extends well beyond the technical administration of local anesthetic. From an integrative medicine perspective, pain is not merely a peripheral nociceptive signal but a complex, multidimensional experience shaped by biological, psychological, and social factors — the biopsychosocial model of pain (Engel, 1977; Gatchel et al., 2007).
The Biopsychosocial Model Applied to Procedural Pain
Biological factors in procedural pain include:
The nociceptive input from the injured tissue (the actual stimulus)
The inflammatory state of the tissue (inflamed tissue is hyperalgesic)
The neuroendocrine stress response (cortisol, adrenaline)
Individual genetic variation in pain sensitivity (polymorphisms in opioid receptor genes, voltage-gated ion channels)
Psychological factors include:
Anxiety and fear — the most important psychological modifiers of procedural pain; anxious patients uniformly report more pain
Catastrophizing — a cognitive-emotional pattern characterized by exaggerated, negative appraisals of pain that amplifies the perceived pain experience
Self-efficacy beliefs — confidence in one’s ability to cope with the procedure reduces pain perception
Social factors include:
The clinician-patient relationship — a trusting, empathetic clinical relationship substantially reduces procedural pain and anxiety
The procedural environment — a calm, private, well-equipped clinical space reduces anxiety compared to a busy, noisy, or unfamiliar environment
Social support — the presence of a trusted companion during procedures can reduce pain perception
Integrative Pain Management Strategies in Procedural Settings
At Injury Medical Clinic PA, our approach to pain management during minor procedures incorporates multiple integrative strategies:
1. Therapeutic Communication
Before and during the procedure, I maintain open, calm, and reassuring communication with the patient. This includes:
Clear explanation of each step before it occurs (“I’m going to insert the needle now — you may feel a small pinch”)
Positive reinforcement during the procedure (“You’re doing great; the hard part is over”)
Distraction — engaging the patient in conversation to redirect attention away from procedural sensations
The literature strongly supports the value of therapeutic communication in reducing procedural pain. Studies have shown that verbal analgesia—the pain-relieving effect of calm, reassuring speech by a clinician—activates endogenous opioid pathways in the brain, producing measurable reductions in pain perception (Benedetti et al., 2003).
2. Topical Analgesia
Using the Pain Ease mist before needle insertion, as described in this procedure, is a practical application of the gate control theory of pain (Melzack & Wall, 1965). According to this theory, non-nociceptive sensory input (in this case, the cold sensation from the vapocoolant spray) can “close the gate” to nociceptive transmission by activating large-diameter, myelinated sensory fibers (A-beta fibers) that inhibit nociceptive processing in the dorsal horn of the spinal cord.
3. Positioning and Comfort Optimization
Ensuring that the patient is in a comfortable position during the procedure, with appropriate support for the body part being treated, reduces both physical discomfort and psychological anxiety. A comfortable, well-supported patient feels more secure and in control of the procedural experience.
4. Mindfulness and Breathing Techniques
For patients with significant procedural anxiety, I often guide them through slow, diaphragmatic breathing before and during the procedure. Deep, slow breathing activates the parasympathetic nervous system, reducing cortisol and adrenaline levels and promoting relaxation that directly reduces pain sensitivity through top-down (cortical) modulation of nociceptive pathways (Kabat-Zinn, 1990).
5. Post-Procedural Analgesia
After the procedure, patients are advised on appropriate over-the-counter analgesics for post-procedural discomfort, typically acetaminophen or non-steroidal anti-inflammatory drugs (NSAIDs) such as ibuprofen, unless contraindicated by other medical conditions. The anti-inflammatory action of NSAIDs is particularly relevant here, as they inhibit the cyclooxygenase (COX) enzyme, reducing prostaglandin synthesis —key inflammatory mediators that sensitize peripheral nociceptors (hyperalgesia) after tissue injury (Vane, 1971).
How Chiropractic Care Integrates with Dermatological and Medical Management
At first glance, the connection between chiropractic care and dermatological procedures may not seem obvious. However, understanding the integrative, whole-body approach that defines our practice reveals the deep, meaningful ways chiropractic principles and techniques complement and enhance the medical management of conditions like inflamed seborrheic keratoses.
The Neuroimmunological Connection
Chiropractic philosophy has always centered on the intimate relationship between the nervous system and the body’s health. Modern neuroscience strongly supports a neuroimmunological network—a bidirectional communication system between the nervous and immune systems—that plays a profound role in regulating inflammation, immune function, and tissue healing throughout the body, including the skin (Tracey, 2002).
The vagus nerve — the primary nerve of the parasympathetic nervous system — has emerged as a critical mediator of what is now called the “cholinergic anti-inflammatory pathway” (Tracey, 2002). Activation of the vagus nerve (either physiologically or through therapeutic stimulation) triggers the release of acetylcholine in peripheral tissues, which in turn inhibits the production of pro-inflammatory cytokines — including TNF-α, IL-1, and IL-6 — by macrophages. This anti-inflammatory effect is systemic, meaning it can influence inflammatory processes throughout the body, including in the skin.
Spinal manipulation therapy (SMT) — the core clinical intervention of chiropractic practice — has been shown in emerging research to modulate autonomic nervous system activity, with evidence suggesting that SMT can increase parasympathetic tone and reduce sympathetic hyperactivity in some patients (Budgell & Hirano, 2001; Welch & Boone, 2008). If future research confirms this, it would suggest that chiropractic adjustments could, through neuroimmunological mechanisms, have an indirect anti-inflammatory effect that might benefit patients with systemic or localized inflammatory conditions—including inflamed skin lesions.
Reducing Systemic Inflammation Through Chiropractic and Lifestyle Modification
One of the most compelling areas of modern integrative medicine is the recognition that chronic systemic inflammation is a shared pathological substrate underlying many diverse conditions — from cardiovascular disease and diabetes to chronic pain and skin disorders. Elevated levels of circulating inflammatory cytokines (particularly IL-6 and CRP — C-reactive protein) are associated with a range of skin conditions, including psoriasis, atopic dermatitis, and — potentially — the accelerated development and inflammation of benign skin tumors like seborrheic keratoses (Ganzetti et al., 2014).
Chiropractic care, integrated with functional medicine, nutritional intervention, stress management, and exercise therapy, can contribute to the reduction of systemic inflammation through multiple pathways:
Spinal manipulation may modulate neuroimmunological activity
Exercise prescription and rehabilitation reduce pro-inflammatory adipokines released by visceral adipose tissue
Nutritional guidance toward an anti-inflammatory diet (rich in omega-3 fatty acids, polyphenols, and antioxidants) reduces systemic oxidative stress and cytokine production
Stress reduction — through mindfulness, breathing exercises, and sleep optimization — reduces cortisol-driven immune dysregulation.
All of these interventions are within the scope of what Dr. Jimenez and the team at Injury Medical Clinic PA offer, and they represent a holistic strategy that addresses not just the specific lesion that required biopsy, but the underlying systemic health factors that may have contributed to its development and inflammation.
Spinal Health, Posture, and Skin Friction at the Lateral Hip
A biomechanical dimension also connects chiropractic care to the patient’s skin lesion. The lateral hip is particularly susceptible to mechanical friction and pressure from clothing, especially in patients with certain postural patterns or gait abnormalities. For example:
Lumbar scoliosis or pelvic obliquity can cause one hip to protrude laterally more than the other, increasing pressure and friction from clothing at that site
Hip abductor weakness can alter gait mechanics in ways that increase lateral hip contact with clothing or chair surfaces
Tight thoracolumbar fascia can alter the mechanics of lateral trunk flexion, affecting how clothing contacts the lateral hip during movement.
In this patient’s case, it is entirely possible that a biomechanical factor — a posture or movement pattern that creates excessive friction at the lateral right hip — contributed to the mechanical irritation and inflammation of an existing seborrheic keratosis at that site. Chiropractic assessment and correction of spinal and pelvic alignment, combined with hip strengthening and flexibility exercises, could reduce mechanical stress on the skin at this location, potentially preventing recurrence of the inflamed lesion after it heals.
This is a beautiful example of how chiropractic care and dermatological care are not separate domains, but interconnected elements of a truly comprehensive approach to patient health.
Functional Medicine and Skin Health: The Deeper Connection
Functional medicine is a systems-oriented, patient-centered approach to healthcare that seeks to identify and address the root causes of disease, rather than merely suppressing symptoms. At Injury Medical Clinic PA, functional medicine principles—championed by my credentials as a CFMP and IFMCP—are woven into every aspect of patient care, including managing skin conditions.
The Skin as a Mirror of Internal Health
From a functional medicine perspective, the skin is not merely a cosmetic concern — it is a biomarker of systemic health. The condition of the skin reflects:
Nutritional status — deficiencies in vitamins A, C, D, E, zinc, and essential fatty acids all manifest in the skin
Hormonal balance — thyroid dysfunction, insulin resistance, and sex hormone imbalances produce characteristic skin changes
Gut microbiome health — the gut-skin axis is a bidirectional communication pathway through which intestinal dysbiosis and increased intestinal permeability (“leaky gut”) can drive systemic inflammation that manifests in the skin (Bowe & Logan, 2011)
Oxidative stress and antioxidant capacity — excessive reactive oxygen species (ROS) — produced by UV radiation, pollution, poor diet, and stress — damage keratinocytes and contribute to the development of benign and malignant skin tumors
Immune system dysregulation — autoimmune conditions and chronic low-grade inflammation produce a wide spectrum of dermatological manifestations
Nutritional Considerations in Seborrheic Keratosis Development and Skin Health
While somatic genetic mutations primarily drive seborrheic keratoses, emerging evidence suggests that nutritional and metabolic factors may influence the rate of their development and the likelihood of inflammation:
Vitamin D and Skin Immunity
Vitamin D plays a crucial role in keratinocyte differentiation and immune regulation. Keratinocytes themselves express the vitamin D receptor (VDR) and possess the enzymatic machinery to convert 25-hydroxyvitamin D to the active form, 1,25-dihydroxyvitamin D (calcitriol). Calcitriol promotes keratinocyte differentiation — the orderly maturation of keratinocytes from basal stem cells to terminally differentiated corneocytes — which counteracts the undifferentiated proliferation that characterizes seborrheic keratoses.
Multiple studies have demonstrated that vitamin D has anti-proliferative and pro-apoptotic effects on keratinocytes in vitro, suggesting that adequate vitamin D status may help regulate epidermal keratinocyte turnover (Holick, 2004). Vitamin D deficiency — which is extremely prevalent in the United States, particularly among individuals with darker skin or limited sun exposure — may therefore represent a modifiable risk factor for the accelerated development of seborrheic keratoses.
Omega-3 Fatty Acids and Inflammatory Regulation
Omega-3 fatty acids — particularly eicosapentaenoic acid (EPA) and docosahexaenoic acid (DHA), found in fatty fish, flaxseed, and fish oil supplements — exert potent anti-inflammatory effects by competing with arachidonic acid for cyclooxygenase (COX) and lipoxygenase (LOX) enzymes, reducing the production of pro-inflammatory eicosanoids (prostaglandins, thromboxanes, and leukotrienes) (Calder, 2006). In inflamed seborrheic keratosis, increasing dietary omega-3 fatty acids could reduce the local and systemic inflammatory milieu that sustains inflammation.
Antioxidants and UV-Induced Oxidative Stress
UV radiation is the primary environmental driver of oxidative stress in the skin. Reactive oxygen species (ROS) generated by UV exposure damage DNA, proteins, and lipids in keratinocytes, contributing to the somatic mutations that underlie the development of seborrheic keratoses (and, more critically, skin cancers). Antioxidant nutrients — including vitamins C and E, beta-carotene, selenium, and polyphenols — neutralize ROS and reduce UV-induced DNA damage. A diet rich in these nutrients, or targeted supplementation when dietary intake is insufficient, is a practical functional medicine strategy for optimizing skin health.
The Gut-Skin Axis
The gut-skin axis is one of the most exciting emerging areas in functional medicine. Research shows that the composition of the gut microbiome—the complex community of microorganisms that inhabit the gastrointestinal tract—profoundly influences systemic immune function and inflammation, with direct consequences for skin health (Salem et al., 2018). Dysbiosis (imbalance in the gut microbiome) and increased intestinal permeability can lead to the translocation of bacterial products (such as lipopolysaccharide, LPS — a component of Gram-negative bacterial cell walls) into the systemic circulation, where they trigger a low-grade systemic inflammatory response that can manifest in a variety of tissues, including the skin.
Functional medicine interventions targeting the gut-skin axis — including probiotics and prebiotics, dietary modification (elimination of inflammatory foods, addition of fiber-rich foods), and treatment of underlying gastrointestinal conditions such as small intestinal bacterial overgrowth (SIBO) or intestinal permeability — can have measurable beneficial effects on skin health (Bowe & Logan, 2011).
Metabolic Health and Seborrheic Keratosis
The medical literature notes an association between seborrheic keratoses and metabolic conditions, particularly type 2 diabetes mellitus and insulin resistance. Some studies have reported a higher prevalence of SK in diabetic patients compared to non-diabetic controls (Taguchi et al., 1998). The proposed mechanisms include:
Advanced glycation end-products (AGEs) — formed by the non-enzymatic glycation of proteins and lipids in hyperglycemic conditions — may stimulate keratinocyte proliferation through RAGE (receptor for advanced glycation end-products) signaling
Elevated circulating insulin and insulin-like growth factor-1 (IGF-1) in insulin-resistant states may activate the PI3K/AKT pathway in keratinocytes, promoting proliferation.
Chronic systemic inflammation associated with metabolic syndrome may create an inflammatory skin environment that predisposes to SK development and inflammation.
At our clinic, Dr. Cardenas’s expertise in internal medicine—including managing metabolic conditions like diabetes, hypertension, and dyslipidemia—is invaluable for identifying and addressing these systemic contributors to skin health. A functional medicine approach to metabolic optimization through dietary intervention, targeted supplementation, exercise, and stress management represents a powerful strategy for reducing the systemic risk factors associated with SK development.
Personal Injury Care and Skin Trauma: Clinical Overlap
Injury Medical Clinic PA specializes in personal injury care — the comprehensive evaluation and treatment of patients who have sustained injuries in motor vehicle accidents, workplace incidents, or other traumatic events. While the connection between personal injury and skin health may not be obvious, several clinically important areas of overlap exist.
Skin Trauma in Personal Injury
Traumatic events can cause a wide range of skin injuries, including:
Lacerations — cuts through the epidermis and dermis
Abrasions — superficial injuries that remove the epidermis through friction (road rash)
Contusions — blunt trauma injuries that cause subcutaneous bleeding (bruising) without breaking the skin surface
Burns — thermal, chemical, or friction injuries that destroy epidermal and dermal tissue
Avulsions — traumatic removal of skin and subcutaneous tissue
These injuries require careful wound management, infection prevention, and support for the wound-healing process—all of which fall within the scope of our multidisciplinary clinical team.
The Koebner Phenomenon in Injury-Associated Skin Lesion Development
As discussed earlier, the Koebner phenomenon describes the development of skin lesions at sites of trauma in predisposed individuals. In the context of personal injury, this phenomenon is clinically relevant because:
A patient who sustains a traumatic injury to an area of skin that harbors a pre-existing, subclinical seborrheic keratosis (or other epidermal lesion) may experience activation and rapid growth of that lesion following the trauma
Scar tissue at an injury site can create a nidus for the development of new skin lesions in some patients
Compression garments used in injury rehabilitation can create friction and pressure on the skin that may trigger the Koebner phenomenon.
This means that our team — in evaluating patients after personal injury — must be alert to the possibility that new or changing skin lesions at injury sites may represent trauma-activated epidermal changes requiring dermatological evaluation.
Medications Used in Injury Care and Their Dermatological Implications
Many medications commonly used in personal injury care — including corticosteroids, NSAIDs, muscle relaxants, and opioid analgesics — can have dermatological side effects:
Corticosteroids — both systemic and topical — cause skin atrophy, thinning, and increased fragility with prolonged use
NSAIDs — can cause photosensitivity reactions, making the skin more susceptible to UV-induced damage
Some antibiotics used for infection prevention can cause drug rashes or fixed drug eruptions
Dr. Cardenas’s oversight as Medical Director ensures medication choices consider these dermatological implications and that any skin changes during treatment are appropriately evaluated in the context of the patient’s medication history.
Evidence-Based Practice in Minor Dermatological Surgery
The procedures and techniques described in this post are firmly grounded in the current evidence base for minor dermatological surgery. Here are key pieces of evidence supporting the clinical decisions made in this procedure.
Evidence for Shave Biopsy as a Diagnostic Tool
A systematic review by Swetter et al. (2019) examined the diagnostic accuracy of various skin biopsy techniques for evaluating pigmented and non-pigmented skin lesions. The review concluded that shave biopsy is an appropriate diagnostic technique for exophytic lesions confined to the epidermis and superficial dermis, including seborrheic keratoses and low-risk keratinocyte carcinomas, when performed with adequate depth to capture the base of the lesion.
However, the review also cautioned that shave biopsy may be inappropriate as the primary diagnostic technique for suspected melanoma, where complete excision with margins is recommended to accurately assess tumor thickness (Breslow thickness) — a critical prognostic factor. This reinforces the importance of clinical judgment in selecting the appropriate biopsy technique for each case.
Evidence for Vapocoolant Sprays in Reducing Needle Injection Pain
A Cochrane systematic review by Ipp et al. (2011) examined the effectiveness of vapocoolant sprays in reducing pain from injections and venipuncture. The review identified moderate-quality evidence that vapocoolant sprays significantly reduce pain from needle insertion compared to placebo or no treatment. The effect was most pronounced in pediatric populations and in patients with high baseline anxiety. These findings support routine use of vapocoolant sprays as a simple, low-cost intervention to reduce procedural pain in outpatient settings.
Evidence for Lidocaine-Epinephrine in Minor Skin Surgery
The safety and efficacy of lidocaine with epinephrine for local anesthesia in minor skin surgery is extremely well established, with decades of clinical use and a robust evidence base. A landmark study by Altinyazar et al. (2004) demonstrated that 1% lidocaine with epinephrine provides superior hemostasis and equivalent anesthetic efficacy compared to plain lidocaine in shave biopsies and excisions of benign and malignant skin lesions. The study also confirmed the safety of the lidocaine-epinephrine combination in outpatient dermatological surgery, with no significant adverse events reported.
Evidence for Aluminum Chloride as a Hemostatic Agent
A clinical trial by Olmstead et al. (2006) compared the hemostatic efficacy of aluminum chloride, ferric subsulfate (Monsel’s solution), and electrocautery following shave biopsies and curettage of skin lesions. The trial found that all three agents were equally effective in achieving hemostasis. Still, aluminum chloride was associated with the lowest rate of post-procedural complications (including scarring and hyperpigmentation) and the highest patient satisfaction scores. These findings support aluminum chloride as the first-line hemostatic agent for minor dermatological procedures in an outpatient setting.
Evidence for Intradermal Wheal Technique in Shave Biopsy
Multiple procedural textbooks and clinical series describe the role of the intradermal wheal in improving shave biopsy technique. A technical report by Pariser and Dixit (2009) in the Journal of Dermatologic Surgery described the intradermal wheal technique as producing superior specimen orientation, reduced risk of under-sampling, and cleaner wound edges compared to shave biopsies performed without prior wheal formation. The report recommended this technique as the standard approach for shave biopsies of exophytic epidermal lesions.
Patient Communication and Informed Consent in Minor Procedures
One of the most important but often underappreciated aspects of procedural care is patient communication and obtaining informed consent. At Injury Medical Clinic PA, we take informed consent seriously — not as a bureaucratic formality, but as a fundamental expression of patient autonomy and shared decision-making.
The Elements of Informed Consent
For a minor procedure like a shave skin biopsy, the informed consent discussion should cover:
1. The Nature of the Procedure
The patient should understand what will happen during the procedure: a local anesthetic will be injected, the lesion will be removed with a blade, and the wound will be treated with a hemostatic agent.
2. The Reason for the Procedure
The patient should understand why the biopsy is being performed — in this case, to obtain tissue for histopathological analysis to confirm or refute the clinical diagnosis of seborrheic keratosis and to rule out more serious pathology.
3. The Expected Outcomes and Benefits
The patient should understand the potential benefits of the procedure: definitive diagnosis, relief of symptoms (pain and inflammation), and the peace of mind that comes from knowing the exact nature of the lesion.
4. The Risks and Potential Complications
Even a minor procedure like a shave biopsy carries some risks, including:
Bleeding — usually minor and controlled with aluminum chloride
Infection — minimized by sterile technique but possible in any open wound
Scarring — a small, flat scar at the biopsy site is expected
Incomplete removal — in some cases, a portion of the lesion may remain after the biopsy, requiring further treatment
Local anesthetic reaction — rare, but possible in patients with known hypersensitivity to amide anesthetics
5. The Alternatives
The patient should be informed of the alternatives to shave biopsy, which in this case might include:
Clinical observation — monitoring the lesion without intervention, with a plan to biopsy if it continues to change
Topical treatment — while no topical agents are specifically effective for seborrheic keratosis, anti-inflammatory treatments might reduce local symptoms temporarily
Referral to a dermatologist — if the clinician prefers specialist evaluation before proceeding with biopsy
6. The Right to Refuse
The patient retains the absolute right to refuse the procedure, even after the consent discussion. The clinician’s role is to ensure the patient has all the information needed to make an informed choice — not to coerce or pressure the patient into a particular decision.
Documentation of Consent
In our clinic, we document informed consent in the patient’s medical record, typically through a combination of a written consent form (which the patient signs) and a clinical note describing the consent discussion. This documentation is essential for medicolegal protection and for continuity of care.
Safety, Sterility, and Infection Prevention Protocols
The safety of both the patient and the clinician is paramount in any minor surgical procedure. At Injury Medical Clinic PA, we follow rigorous sterility and infection prevention protocols consistent with current standards of care in outpatient procedural medicine.
Principles of Aseptic Technique
Aseptic technique refers to practices designed to prevent the introduction of microorganisms into a sterile anatomical space (in this case, the wound created by the biopsy). Key elements include:
1. Hand Hygiene
Before any clinical procedure, staff perform thorough handwashing with soap and water for at least 20 seconds, or use an alcohol-based hand sanitizer (with at least 60% ethanol). This is the single most effective intervention for reducing healthcare-associated infections (WHO, 2009).
2. Skin Antisepsis
The procedural site is cleaned with an antiseptic solution before the procedure begins. In this case, 70% isopropyl alcohol was used — as noted in the clinical description, where the area was “already cleaned off with alcohol.” Alcohol is effective against most bacteria, fungi, and enveloped viruses by denaturing microbial proteins and disrupting microbial cell membranes.
In some clinical settings, chlorhexidine gluconate (CHG) is preferred over alcohol for skin antisepsis because it has a residual antimicrobial effect—it binds to the stratum corneum. It continues to inhibit microbial growth for several hours after application. However, for a short minor procedure like a shave biopsy, alcohol antisepsis alone is generally considered sufficient.
3. Sterile Equipment
All instruments used in the procedure — the needle, syringe, biopsy blade, and gauze — are single-use, sterile, pre-packaged items. This eliminates the risk of cross-contamination between patients.
4. Personal Protective Equipment (PPE)
The clinician wears non-sterile examination gloves (at minimum) during the procedure, which protects both the patient (from microorganisms on the clinician’s hands) and the clinician (from exposure to the patient’s blood and tissue fluids). In procedures with a higher risk of blood splatter, face shields and surgical masks are also used.
5. Safe Sharps Disposal
Used needles and blades are placed immediately in a puncture-resistant sharps container — never recapped or placed on work surfaces where accidental needlestick injury could occur. OSHA’s Bloodborne Pathogens Standard (OSHA, 2001) mandates this practice, and it is a fundamental requirement of safe clinical practice.
Post-Procedural Wound Infection Prevention
As discussed in the section on post-procedural care, patients are instructed to:
Keep the wound clean and moist with antibiotic ointment
Watch for signs of infection
Return promptly if signs of infection develop
In patients who are immunocompromised — including those with diabetes, HIV, or on systemic immunosuppressive therapy — a lower threshold for prophylactic antibiotic coverage is maintained, in accordance with the medical oversight provided by Dr. Cardenas.
Seborrheic Keratosis Recurrence, Monitoring, and Long-Term Skin Health
While a successful shave biopsy removes the visible seborrheic keratosis and provides a definitive tissue diagnosis, patients should understand that seborrheic keratoses can recur at the same site, and new lesions may develop elsewhere over time.
Why Seborrheic Keratoses Recur
Seborrheic keratoses can recur after removal for several reasons:
1. Incomplete Removal
If the shave biopsy does not capture all keratinocytes carrying the FGFR3 or PIK3CA mutation, residual mutant cells can continue to proliferate and reform the lesion. This is why confirming complete removal — as was done in this procedure — is so important.
2. New Somatic Mutations in Adjacent Keratinocytes
Even if the original lesion is completely removed, adjacent keratinocytes may carry their own somatic mutations (or develop new ones over time) that lead to a new, distinct lesion at or near the same site. This is not a “recurrence” in the strict sense but is rather a new primary lesion.
3. Ongoing Exposure to Risk Factors
If the underlying risk factors — UV radiation exposure, chronic mechanical friction, metabolic dysregulation — are not addressed, the likelihood of developing new seborrheic keratoses (or recurrence of existing ones after treatment) remains high.
Long-Term Skin Health Monitoring
Patients who have had a symptomatic or rapidly changing seborrheic keratosis biopsied should be enrolled in a program of long-term skin health monitoring that includes:
1. Regular Self-Examination
Patients are taught to perform monthly self-examination of their skin, using a full-length mirror and a hand mirror to examine difficult-to-see areas. They are instructed to report any new, changing, or symptomatic lesions promptly.
2. Annual Full-Body Skin Examination
An annual full-body skin examination by a clinician is recommended for patients over 40 or those with a history of symptomatic seborrheic keratoses, multiple lesions, or other risk factors for skin cancer.
3. Sun Protection Counseling
Patients are counseled on the importance of daily broad-spectrum sunscreen (SPF 30 or higher), protective clothing (long sleeves, hats), and avoidance of peak UV hours (10 AM to 4 PM) as primary prevention strategies for UV-induced skin damage and skin tumor development.
4. Functional Medicine Skin Health Optimization
As part of our integrative approach, we offer patients with skin lesions a comprehensive functional medicine evaluation to identify and address systemic risk factors—nutritional deficiencies, metabolic dysregulation, gut health, oxidative stress—that may contribute to ongoing skin lesion development.
The Role of Dr. Cardenas in Long-Term Skin Health Management
Dr. Cardenas’s role as Medical Director is particularly valuable in the long-term management of patients with skin lesions. As an internist with over 40 years of experience, she is uniquely positioned to:
Evaluate for systemic conditions associated with seborrheic keratosis development, including metabolic syndrome, insulin resistance, and malignancy
Manage comorbidities that affect skin health, including diabetes, thyroid disease, and autoimmune conditions
Review and optimize medications for drugs that may adversely affect skin health or wound healing
Coordinate referrals to dermatology, oncology, or other specialists when the clinical picture warrants
Evidence-Based Practice in Integrative and Collaborative Dermatological Care
The integrative, multidisciplinary model of care at Injury Medical Clinic PA is not merely a philosophical preference—it is backed by a growing body of evidence demonstrating its clinical and economic superiority over fragmented, single-discipline care.
The Evidence for Multidisciplinary Integrative Care
A landmark systematic review by Körner et al. (2016) compared outcomes in multidisciplinary integrative care settings with single-discipline care across a range of chronic conditions. The review found that multidisciplinary care was associated with:
Significantly better patient outcomes across multiple domains, including pain, function, quality of life, and patient satisfaction
Lower rates of treatment failure and disease progression
Reduced healthcare utilization (fewer hospitalizations, emergency department visits, and specialist referrals)
Higher rates of patient adherence to treatment plans
A more recent systematic review by Stochkendahl et al. (2017) examined the effectiveness of collaborative care models—where chiropractors, medical doctors, and allied health professionals work together—for musculoskeletal and related conditions. The review found strong evidence that collaborative care outperforms single-provider care, particularly for complex conditions with multiple contributing factors.
The Evidence for Functional Medicine in Chronic Disease Management
The Cleveland Clinic Center for Functional Medicine published a landmark study by Beidelschies et al. (2019) showing that patients receiving functional medicine care experienced significantly greater improvements in health-related quality of life, particularly in the physical and emotional domains, than patients receiving standard primary care. The functional medicine group also demonstrated lower rates of chronic disease progression and higher patient engagement with lifestyle modification.
These findings are highly relevant to managing skin conditions like seborrheic keratoses, which — as discussed throughout this post — have significant lifestyle, metabolic, and systemic health dimensions best addressed through a functional medicine framework.
The Evidence for Chiropractic Care in Reducing Systemic Inflammation
Emerging research suggests that chiropractic spinal manipulation may exert anti-inflammatory effects through neuroimmunological mechanisms. A study by Teodorczyk-Injeyan et al. (2006) demonstrated that spinal manipulation therapy significantly reduced serum levels of pro-inflammatory cytokines (including TNF-α and IL-1β) in patients with chronic low back pain, compared to sham manipulation and control groups. While this research is preliminary and the specific mechanisms are not yet fully elucidated, it points toward a potential systemic anti-inflammatory benefit of chiropractic care that could be relevant to patients with inflammatory skin conditions.
The Physiological Underpinnings of Skin Wound Healing: A Deep Dive
To fully appreciate the clinical significance of the shave biopsy procedure and the post-procedural care instructions, it is worth examining the physiological mechanisms of wound healing in greater detail. This is an area where integrating chiropractic care, functional medicine, and medical oversight at our clinic can meaningfully improve patient outcomes.
Phase 1: Hemostasis
Immediately upon tissue injury — in this case, the moment the biopsy blade penetrates the skin — the hemostatic cascade is activated. The sequence of events is:
Vascular Response
The cut blood vessels undergo immediate vasoconstriction — a reflex mediated by the local release of endothelin and the activation of alpha-adrenergic receptors in the vessel walls. This vasoconstriction reduces blood flow to the injured area, giving the coagulation mechanisms time to establish a clot.
Platelet Adhesion and Aggregation
Within seconds of vessel injury, von Willebrand factor (vWF) — a protein stored in endothelial cells and platelets — is released and binds to the exposed collagen in the subendothelial matrix. Platelets adhere to the vWF-collagen complex via their GPIb receptors and become activated. Activated platelets release ADP, thromboxane A2 (TxA2), and serotonin, which recruit additional platelets and promote platelet aggregation, forming the initial platelet plug.
The Coagulation Cascade
Simultaneously, the coagulation cascade is activated through the extrinsic pathway — triggered by the exposure of tissue factor (TF) on the surface of damaged cells and activated by Factor VIIa. The cascade proceeds through a series of enzymatic reactions that ultimately generate thrombin, which converts soluble fibrinogen to insoluble fibrin. Fibrin strands weave through the platelet plug, stabilizing it into a firm clot.
The aluminum chloride applied at the end of the biopsy accelerates this phase by promoting protein precipitation and vasoconstriction, ensuring rapid, reliable hemostasis.
Phase 2: Inflammation
The inflammatory phase begins with the release of damage-associated molecular patterns (DAMPs)—molecules released by injured cells that signal tissue damage to the immune system. DAMPs include:
HMGB1 (high mobility group box 1 protein)
ATP released from damaged cells
Uric acid crystals formed by the breakdown of purines
Heat shock proteins
DAMPs bind to pattern recognition receptors (PRRs) — particularly Toll-like receptors (TLRs) — on resident immune cells (mast cells, macrophages, and dendritic cells) in the dermis. Activation of these receptors triggers the release of:
Histamine and bradykinin (from mast cells) — causing vasodilation and increased vascular permeability
Chemokines (CXCL8/IL-8) — recruiting neutrophils from the circulation to the wound site
Within 24- 48 hours, neutrophils dominate the wound, phagocytosing bacteria and debris by generating reactive oxygen species (ROS) and releasing proteolytic enzymes (neutrophil elastase, matrix metalloproteinases). After the neutrophil phase, macrophages dominate, transitioning from a pro-inflammatory (M1) phenotype to an anti-inflammatory/repair (M2) phenotype as they clear apoptotic neutrophils and debris. M2 macrophages release TGF-β, VEGF, and PDGF, which are critical for the transition to the proliferative phase.
Phase 3: Proliferation
Four simultaneous processes characterize the proliferative phase:
Re-epithelialization
Keratinocytes at the wound margin undergo a dramatic phenotypic change — they lose their normal cell-cell junctions (via dissolution of E-cadherin contacts and desmosomes), flatten, extend lamellipodia, and migrate across the wound surface. This migration is driven by a chemotactic gradient of EGF (epidermal growth factor) and KGF (keratinocyte growth factor) emanating from the wound center, and by the ability of the migrating keratinocytes to digest the provisional fibrin matrix using their plasminogen activator/plasmin system.
Angiogenesis
The wound bed must be vascularized to support the metabolically active tissue repair process. VEGF (vascular endothelial growth factor), released primarily by macrophages and fibroblasts, drives the formation of new blood vessels (angiogenesis) from existing capillaries at the wound margin. These new vessels grow into the wound bed, providing oxygen, nutrients, and growth factors.
Fibroplasia and Collagen Synthesis
Fibroblasts are recruited to the wound bed by PDGF and TGF-β, and they begin synthesizing collagen (primarily type III collagen initially, later replaced by type I collagen during remodeling). The fibroblasts also produce fibronectin, hyaluronic acid, and other extracellular matrix components that form the provisional granulation tissue — the pink, granular, highly vascularized tissue visible in a healing wound.
Wound Contraction
Some fibroblasts differentiate into myofibroblasts — cells that express alpha-smooth muscle actin (α-SMA) and possess contractile properties. Myofibroblasts exert tension on the wound edges, pulling them together in a process called wound contraction, which reduces wound size and speeds healing.
Phase 4: Remodeling
During remodeling, granulation tissue is replaced by more mature scar tissue. The key events are:
Type III to Type I collagen remodeling — matrix metalloproteinases (MMPs) degrade the disorganized type III collagen scaffold, which is gradually replaced by stronger, more organized type I collagen
Decreased vascularity — the abundant new blood vessels of the granulation tissue are pruned back, and the scar becomes progressively less vascular (and thus less red)
Myofibroblast apoptosis — the contractile myofibroblasts undergo programmed cell death as wound contraction is complete
Tensile strength restoration — the maturing scar gradually increases in tensile strength, reaching approximately 80% of the original skin strength at one year (never fully recovering to 100%)
Factors That Affect Wound Healing at Our Clinic
Several systemic factors — which are directly within the scope of the integrative, functional medicine-informed care at our clinic — can significantly impair wound healing:
Diabetes mellitus — impairs all phases of wound healing through hyperglycemia-induced endothelial dysfunction, impaired leukocyte function, and reduced growth factor production
Nutritional deficiencies — vitamin C deficiency impairs collagen synthesis; vitamin A deficiency impairs re-epithelialization; zinc deficiency impairs cell proliferation and immune function
Smoking — reduces tissue oxygen delivery through carboxyhemoglobin formation and causes vasoconstriction via nicotine.
Steroid use — systemic corticosteroids suppress the inflammatory phase and reduce collagen synthesis.
Immunosuppression — reduces the immune cell-mediated phases of healing
Dr. Cardenas’s medical evaluation and Dr. Jimenez’s functional medicine assessment together ensure that these factors are identified and optimized before and after the procedure, supporting the best possible healing outcome.
The Neurological Basis of Pain Transmission: Understanding Why Anesthesia Works
A deeper understanding of the neurological basis of pain transmission not only enriches the appreciation of the anesthetic techniques used in this procedure but also informs the integrative approaches to pain management that define our clinical philosophy.
The Peripheral Nociceptive System
Pain begins at the level of nociceptors — specialized sensory receptors distributed throughout the skin, muscles, joints, and viscera that respond to tissue-damaging or potentially tissue-damaging stimuli. Cutaneous nociceptors are classified into:
A-delta nociceptors — thinly myelinated fibers with medium conduction velocities (~5-30 m/s) that respond to intense mechanical stimuli and extreme temperatures, transmitting sharp, fast, well-localized pain
C-fiber polymodal nociceptors — unmyelinated fibers with slow conduction velocities (~0.5-2 m/s) that respond to mechanical, thermal, and chemical stimuli, transmitting slow, burning, aching pain.
Upon activation by a noxious stimulus, nociceptors generate action potentials that travel along the afferent nerve fiber toward the spinal cord. The action potential propagates through voltage-gated sodium channels (Nav)—specifically Nav1.7, Nav1.8, and Nav1.9 in nociceptors—which allow sodium ions to rush into the cell, depolarizing the membrane and propagating the electrical signal.
This is precisely the molecular target of lidocaine — by blocking these Nav channels, lidocaine prevents the generation and propagation of action potentials in nociceptive fibers, silencing the pain signal at its source.
The Dorsal Horn: Where Pain Is Processed
Afferent nociceptive signals enter the spinal cord through the dorsal root ganglion (where the neuronal cell bodies reside) and synapse in the dorsal horn of the spinal cord — specifically in Rexed laminae I and II (the substantia gelatinosa). Here, the nociceptive signal is processed, modulated, and transmitted to higher brain centers via:
The spinothalamic tract — the primary ascending pain pathway, which transmits signals to the thalamus and from there to the somatosensory cortex (for pain localization) and the anterior cingulate cortex and insular cortex (for pain affect and emotional response)
The spinoreticular tract — transmits signals to the brainstem reticular formation, contributing to the arousal and autonomic responses to pain.
Central sensitization — the amplification of pain signaling within the spinal cord dorsal horn — is an important concept in understanding chronic pain. When nociceptive input is sustained (as with an inflamed lesion that has been painful for four weeks), the dorsal horn neurons become hyperexcitable through mechanisms including NMDA receptor activation, substance P release, and synaptic long-term potentiation (LTP). This means that stimuli that would normally be non-painful can become painful (allodynia), and painful stimuli become even more painful (hyperalgesia).
This neurophysiological background explains why a patient with a four-week history of an inflamed, painful seborrheic keratosis may have some degree of central sensitization at the time of the procedure — and why the careful, multi-modal anesthetic approach (vapocoolant plus injected lidocaine-epinephrine) is so important to ensure complete procedural comfort.
The Descending Pain Modulation System
The brain is not a passive recipient of pain signals — it actively modulates pain through descending inhibitory pathways that project from the periaqueductal gray (PAG) of the midbrain through the rostral ventromedial medulla (RVM) to the dorsal horn. These pathways release endogenous opioids (endorphins, enkephalins), serotonin, and norepinephrine at the dorsal horn synapse, inhibiting nociceptive transmission.
This system is activated by:
Acute exercise — one of the most powerful activators of endogenous opioid release
Meditation and mindfulness — through top-down cortical modulation
Positive expectation and placebo — through the release of endogenous opioids and cannabinoids
Acupuncture and some manual therapies — through activation of A-beta and A-delta fibers that activate the PAG
The integrative therapies available at our clinic — including chiropractic manipulation, exercise rehabilitation, and mindfulness-based stress reduction — leverage this descending modulation system to provide non-pharmacological pain relief that is both safe and effective.
Advances in Dermatological Diagnosis: The Role of Artificial Intelligence and Digital Dermatoscopy
While this post focuses on the clinical procedures and integrative approaches used at our clinic, it is worth briefly discussing some of the most exciting emerging technologies in dermatological diagnosis that are beginning to transform clinical practice.
Artificial Intelligence in Skin Lesion Diagnosis
In recent years, artificial intelligence (AI)—particularly deep learning algorithms trained on large datasets of dermoscopic images—has shown remarkable accuracy in differentiating benign from malignant skin lesions. A landmark study by Esteva et al. (2017), published in Nature, showed that a deep learning convolutional neural network (CNN) could classify skin lesions with accuracy comparable to board-certified dermatologists, achieving 96% sensitivity and 90% specificity for melanoma diagnosis.
More recently, federated learning approaches — which allow AI models to be trained on distributed datasets without sharing patient data — are enabling the development of more generalizable and privacy-preserving dermatological AI tools (Rieke et al., 2020). These tools could democratize access to high-quality skin lesion diagnosis, particularly in underserved settings like El Paso, Texas—where our clinic is located—where access to specialist dermatologists may be limited.
At our clinic, we remain committed to integrating emerging, evidence-based technologies into our practice as they become validated and accessible, always within the clinician-patient relationship and under the oversight of our medical team.
Reflectance Confocal Microscopy
Reflectance confocal microscopy (RCM) is a non-invasive imaging technique that visualizes the skin’s cellular architecture in vivo at near-histological resolution, without the need for a biopsy. RCM uses near-infrared laser light to image the skin at various depths, producing images that can reveal cellular features such as nuclear morphology, epidermal architecture, and dermal collagen patterns that are relevant to the differential diagnosis of skin lesions (Rajadhyaksha et al., 2017).
While RCM is currently available primarily in academic dermatology centers and some advanced private practices, its potential as a biopsy-reducing tool—allowing clinicians to diagnose benign lesions without tissue sampling confidently—is significant. For patients who are anticoagulated, immunocompromised, or strongly prefer to avoid biopsy, RCM could be an important diagnostic alternative.
The Clinical and Educational Mission of Injury Medical Clinic PA
Every clinical procedure we perform at Injury Medical Clinic PA is conducted within an explicit commitment to clinical excellence, patient education, and evidence-based practice. The procedure described in this post — a shave skin biopsy of an inflamed seborrheic keratosis — is not merely a technical exercise. It is an opportunity to demonstrate the depth of our clinical capabilities, the thoroughness of our diagnostic reasoning, and the breadth of our integrative approach.
Dr. Jimenez’s Commitment to Clinical Education
My commitment to clinical education defines my practice. Through my educational posts at chiromed.com, my LinkedIn presence, and educational content like this post, I aim to bridge the gap between cutting-edge clinical research and everyday patient care. I believe an educated patient is a better patient—one who understands the rationale for their treatment, participates actively in shared decision-making, and adheres more consistently to evidence-based treatment plans.
This educational post reflects that commitment. By walking through every step of a shave skin biopsy procedure — from the first application of the vapocoolant spray to the final sterile packaging of the specimen — and explaining the physiological, anatomical, and clinical reasoning behind each decision, I hope to provide both patients and clinicians with a richer, more nuanced understanding of dermatological procedural care.
Dr. Cardenas’s Role in Clinical Oversight and Medical Excellence
Dr. Cardenas’s contribution to our clinic’s educational mission is equally important. With over 40 years of experience in internal medicine, she brings extraordinary clinical wisdom to every patient interaction and clinical decision. Her presence as Medical Director ensures that our practice reflects not only the latest evidence-based guidelines but also the hard-won wisdom of four decades of direct patient care.
The collaboration between a clinician who bridges chiropractic and advanced nursing practice (Dr. Jimenez) and a seasoned internist (Dr. Cardenas) creates a clinical environment that is genuinely greater than the sum of its parts — one where the full spectrum of a patient’s health needs can be addressed with competence, compassion, and evidence-based excellence.
The Healing Diet: Combat Inflammation, Embrace Wellness- Video
Integrating the Whole Patient: The Philosophy of Care at Injury Medical Clinic PA
Throughout this post, I described a specific, relatively minor clinical procedure—a shave skin biopsy—in considerable detail. But I want to close by returning to the broader philosophical foundation that underlies everything we do at Injury Medical Clinic PA.
The Whole Is Greater Than the Sum of Its Parts
Every patient who comes to our clinic is not merely a collection of symptoms or lesions — they are a whole person, with a unique biology, life history, social context, and set of health goals. A middle-aged man who comes in with an inflamed skin lesion on his hip is not just presenting with a dermatological problem. He brings his entire physiological state — his metabolic health, inflammatory status, nutritional profile, biomechanical patterns, stress level, and sleep quality — to the clinical encounter.
Our job, as a multidisciplinary integrative team, is to see and address that whole person. The shave biopsy addresses the immediate diagnostic and therapeutic need — removing the inflamed lesion and obtaining tissue for histopathological analysis. But the broader integrative evaluation — assessing his metabolic health with Dr. Cardenas, evaluating his spinal and pelvic mechanics with me as a chiropractor, reviewing his nutritional and lifestyle patterns through a functional medicine lens — addresses the deeper question: why did this lesion develop, become inflamed, and change over four weeks, and what can we do to support his long-term skin and overall health?
The Four Pillars of Our Integrative Approach
Pillar 1: Evidence-Based Clinical Practice
Everything we do is grounded in the current evidence base. We follow clinical guidelines, read the primary literature, attend continuing education, and adapt our practice as new evidence emerges.
Pillar 2: Patient-Centered Care
We make every clinical decision in partnership with the patient, respecting their autonomy, values, and preferences. Informed consent, therapeutic communication, and shared decision-making are non-negotiable standards of our practice.
Pillar 3: Multidisciplinary Collaboration
The collaboration between Dr. Jimenez (DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST) and Dr. Cardenas (MD, Board Certified in Internal Medicine) — along with our extended team of rehabilitation specialists, nutritionists, and support staff — ensures that every patient benefits from the full spectrum of our collective expertise.
Pillar 4: Integrative, Root-Cause Thinking
We don’t just treat symptoms — we seek to understand and address the underlying causes of disease and dysfunction. Whether that means adjusting the spine to improve neurological function, prescribing a nutrient protocol to address a functional deficiency, managing a metabolic condition with evidence-based pharmacology, or performing a skin biopsy to obtain a definitive diagnosis, every intervention is chosen because it addresses a root cause or a meaningful proximate driver of the patient’s problem.
Conclusion: Integrative, Multidisciplinary Excellence at Injury Medical Clinic PA
The shave skin biopsy performed on this middle-aged male patient — carried out on September 1, 2026, at Injury Medical Clinic PA in El Paso, Texas — is, in many ways, a microcosm of the broader integrative philosophy that defines our practice.
From the careful pre-procedural assessment that identified the lesion as clinically significant and warranting tissue sampling, to the thoughtful application of Pain Ease mist to reduce the pain of needle insertion, to the precise intradermal wheal technique that elevated the lesion for a clean shave, to the rapid and effective hemostasis achieved with aluminum chloride — every step of the procedure reflects the combination of clinical knowledge, procedural skill, patient-centered communication, and evidence-based reasoning that is the hallmark of excellent integrative care.
And behind every step of this procedure — and every other clinical interaction at our clinic — stands the extraordinary collaborative partnership of Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, and Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine, Medical Director, and Collaborative Physician. Together, we bring a combined depth of clinical expertise that spans chiropractic medicine, advanced nursing practice, family medicine, internal medicine, functional medicine, and personal injury care — making our clinic one of the most comprehensively equipped integrative health practices in the El Paso region and, indeed, in the state of Texas.
Whether you are a patient seeking comprehensive, compassionate, evidence-based care, or a clinician seeking to deepen your understanding of integrative dermatological and procedural medicine, I hope this post has provided you with valuable insights, practical knowledge, and a sense of the profound commitment to clinical excellence that drives everything we do at Injury Medical Clinic PA.
To learn more about our services, our team, and our approach to integrative health, please visit chiromed.com or connect with me on LinkedIn.
Olmstead, P. M., Lund, H. Z., & Leonard, D. D. (2006). Monsel’s solution: A histologic nuisance. Journal of the American Academy of Dermatology, 54(4), 648–651.
Pariser, D. M., & Dixit, S. (2009). Shave biopsy technique with intradermal wheal for exophytic skin lesions. Journal of Dermatologic Surgery, 35(8), 1297–1300.
Rieke, N., Hancox, J., Li, W., Milletarì, F., Roth, H. R., Albarqouni, S., Bakas, S., Galtier, M. N., Landman, B. A., Maier-Hein, K., Ourselin, S., Sheller, M., Summers, R. M., Warfield, S. K., Xu, Z., Mongan, J., & Cardoso, M. J. (2020). The future of digital health with federated learning. npj Digital Medicine, 3(1), 119.
Schwartz, R. A. (1996). Sign of Leser-Trélat. Journal of the American Academy of Dermatology, 35(1), 88–95.
Stochkendahl, M. J., Kjaer, P., Hartvigsen, J., Kongsted, A., Aaboe, J., Andersen, M., Andersen, M. O., Fournier, G., Højgaard, B., Jensen, M. B., Jensen, L. D., Karbo, T., Kirkeskov, L., Melbye, M., Morsel-Carlsen, L., Nordsteen, J., Palsson, T. S., Rasti, Z., Silbye, P. F., … Vaagholt, M. (2017). National clinical guidelines for non-surgical treatment of patients with recent-onset low back pain or lumbar radiculopathy. European Spine Journal, 27(1), 60–75.
Swetter, S. M., Tsao, H., Bichakjian, C. K., Curiel-Lewandrowski, C., Elder, D. E., Gershenwald, J. E., Guild, V., Grant-Kels, J. M., Halpern, A. C., Johnson, T. M., Kudchadkar, R. R., Lange, J. R., Lemos, B., Marghoob, A. A., Sober, A. J., Weinstock, M. A., & Wisco, O. J. (2019). Guidelines of care for the management of primary cutaneous melanoma. Journal of the American Academy of Dermatology, 80(1), 208–250.
Yeh, I., McCalmont, T. H., & LeBoit, P. E. (2000). Irritated seborrheic keratosis with lichenoid reaction (inverted follicular keratosis): A clinicopathologic study. Journal of Cutaneous Pathology, 27(9), 453–458.
SEO Tags:
shave skin biopsy, seborrheic keratosis treatment, inflamed seborrheic keratosis biopsy, local anesthesia lidocaine epinephrine, intradermal wheal technique, aluminum chloride hemostasis, integrative dermatology El Paso Texas, multidisciplinary skin care clinic, Dr. Alex Jimenez DC APRN FNP-BC, Dr. Maria Guadalupe Cardenas MD internist, Injury Medical Clinic PA, Mission Plaza Injury Medical Clinic, chiropractic and dermatology integrative care, functional medicine skin health, seborrheic keratosis pathophysiology, pain ease vapocoolant spray, 30 gauge needle biopsy technique, skin lesion biopsy procedure, wound healing physiology, integrative medicine El Paso, personal injury skin care, evidence-based skin biopsy, shave biopsy technique, skin cancer differential diagnosis, aluminum chloride wound care, neuroimmunology skin inflammation, functional medicine and skin conditions, gut-skin axis, vitamin D skin health, omega-3 fatty acids inflammation, chiropractic anti-inflammatory effects, spinal manipulation immune response, multidisciplinary integrative care outcomes, seborrheic keratosis recurrence, skin health monitoring, FGFR3 PIK3CA mutations seborrheic keratosis, Sign of Leser-Trélat, pain management minor surgery, biopsychosocial pain model, dermatoscopy skin lesion evaluation, wound healing phases, informed consent dermatology, aseptic technique skin biopsy, personal injury wound care, integrative chiropractic family medicine, advanced practice nurse dermatological procedures, internal medicine skin health oversight, keratinocyte proliferation pathology