Give us a Call
+1 (915) 412-6680
Send us a Message
[email protected]
Opening Hours
Mon-Thu: 7 AM - 7 PM
Fri - Sun: Closed

Nerve Block Management Effectiveness in Hemicrania Continua


Discover strategies for managing headaches with nerve block treatments for better pain relief in the hemicrania continua.

Abstract

Welcome to our in-depth exploration of hemicrania continua, a persistent and often debilitating unilateral headache disorder. In this educational post, I will guide you through the complexities of this condition from my perspective as a clinician practicing at the intersection of chiropractic, functional medicine, and advanced practice nursing. We will begin by understanding the diagnostic criteria and clinical presentation of hemicrania continua, differentiating it from other primary headache disorders like migraines and cluster headaches. We will then delve into the anatomy and physiology of the cranial nerves involved, specifically the trigeminal nerve and its branches—the supratrochlear, supraorbital, zygomaticotemporal, and auriculotemporal nerves—which are often implicated in the pain pathways of this condition. I will share a detailed case study of a 71-year-old patient, demonstrating a diagnostic and therapeutic nerve block procedure step by step. This includes the rationale for the choice of anesthetics, the precise injection technique, and the immediate clinical outcomes. We will also explore the broader context of our integrative care model at Injury Medical Clinic. I will explain how my work as a Doctor of Chiropractic and Family Nurse Practitioner is complemented by the medical directorship of Dr. Maria Guadalupe Cardenas, MD, an internist with over 40 years of experience. Together, we provide a multidisciplinary framework that combines medical oversight with chiropractic adjustments, functional medicine, rehabilitation, and advanced non-invasive therapies to offer a comprehensive, personalized treatment journey for patients with chronic pain and complex neurological conditions.

Introduction: A Journey Into a Unique Headache Disorder

Hello, I’m Dr. Alex Jimenez. Throughout my career across chiropractic, advanced practice nursing, and functional medicine, my primary mission has been to unravel the complexities of chronic pain and offer my patients a path to lasting relief. At Injury Medical Clinic in El Paso, Texas, we have cultivated a unique environment where different medical disciplines converge to create a truly integrative,patient-centered experience.
A cornerstone of our practice is our collaborative structure. I am privileged to work alongside Dr. Maria Guadalupe Cardenas, MD, a highly respected, board-certified internist who serves as our Medical Director and Collaborative Physician. With her extensive four-decade-long experience, Dr. Cardenas provides the essential medical oversight that allows us to safely and effectively integrate a wide range of therapies. Our clinic is a multidisciplinary hub where chiropractic care, medical management, functional medicine, personal injury rehabilitation, and nutritional science are not just co-located but are woven together into a cohesive treatment strategy. This lets us see a patient not just as a diagnosis, but as a whole person with a unique physiology, lifestyle, and history.
Today, I want to guide you through a fascinating and often misdiagnosed condition known as hemicrania continua. This isn’t just another headache. It’s a relentless, one-sided pain that can erode a person’s quality of life. I will share insights from leading researchers and evidence-based practices, and I’ll walk you through a clinical encounter from September 1, 2026, to illustrate how we approach these complex cases. This journey will not only shed light on the condition itself but also demonstrate the power of an integrative approach in modern healthcare.

Understanding Hemicrania Continua: More Than Just a Headache

When patients hear the term “chronic headache”, they often think of migraines. While migraines are certainly prevalent, the world of primary headache disorders is vast and includes conditions like hemicrania continua (HC), which requires a more specific diagnostic lens.
Hemicrania continua, a member of the trigeminal autonomic cephalalgias (TACs), is defined by three core features according to the International Classification of Headache Disorders, 3rd edition (ICHD-3) (Headache Classification Committee of the International Headache Society (IHS), 2018):
Unilateral Pain: The headache is strictly confined to one side of the head and does not switch sides.
Continuous Pain: The pain is present daily and continuously, without any pain-free periods. While the intensity can fluctuate, a baseline level of discomfort remains.
Absolute Response to Indomethacin: The headache is exquisitely and completely responsive to therapeutic doses of the non-steroidal anti-inflammatory drug (NSAID) indomethacin. This response is so characteristic that it is a required diagnostic criterion.
Patients with HC often experience superimposed attacks of more severe pain, during which they may also develop cranial autonomic symptoms on the same side as the headache. These can include:
Conjunctival injection (red eye)
Lacrimation (tearing)
Nasal congestion or rhinorrhea (runny nose)
Eyelid edema (swelling)
Forehead or facial sweating
Miosis (constriction of the pupil) or ptosis (drooping of the eyelid)
The underlying pathophysiology of HC is believed to involve the trigeminovascular system. This complex network involves the trigeminal nerve (the fifth cranial nerve), the primary sensory nerve of the face and head, and the blood vessels of the cranium. Activation of this system releases neuropeptides like calcitonin gene-related peptide (CGRP), which causes vasodilation and neurogenic inflammation and ultimately results in pain (Goadsby et al., 2017). The central mechanisms, particularly the involvement of the posterior hypothalamus, are also an area of active research and help explain the continuous nature of the pain and its autonomic features.

A Clinical Encounter: The Case of a 71-Year-Old with Right-Sided Headache

To bring these concepts to life, let me walk you through a case I managed on the morning of September 1, 2026. A 71-year-old woman presented to our clinic with a long-standing history of a right-sided headache that fit the clinical picture of hemicrania continua. She described a constant, dull ache on the right side of her head, punctuated by episodes of sharper, more intense pain. Before our procedure, she rated her current pain as a seven out of ten on a standard pain scale.
My immediate goal was twofold: first, to confirm the peripheral nerve involvement contributing to her pain pattern, and second, to provide immediate, albeit temporary, therapeutic relief. A successful diagnostic nerve block can provide profound insight into the patient’s specific pain generators.

The Diagnostic Examination: Pinpointing the Pain

Before any intervention, a thorough physical examination is paramount. For this patient, I focused on palpating the terminal branches of the trigeminal nerve, which are common sites of peripheral sensitization and pain in various headache disorders. Using gentle but firm pressure, I assessed for allodynia (pain from a stimulus that does not normally provoke pain) and hyperalgesia (an increased response to a painful stimulus).
I identified four specific points of exquisite tenderness, which corresponded directly to the anatomical locations of four key sensory nerves:
Supratrochlear Nerve: Located just medial to the supraorbital notch, this nerve provides sensation to the medial forehead and upper eyelid. When I applied pressure here, the patient immediately confirmed, “Yes,” it was painful.
Supraorbital Nerve: Found at the supraorbital notch or foramen, along the upper rim of the orbit. This larger nerve supplies most of the forehead and scalp. Palpation here also elicited a clear “Yes, yes” response of pain.
Zygomaticotemporal Nerve: This smaller branch emerges through a foramen in the zygomatic (cheek) bone to supply the skin over the temporal fossa (the “temple”). When I pressed on this area, she again confirmed, “Right there. Yes.”
Auriculotemporal Nerve: This nerve travels in front of the ear, ascending over the zygomatic arch to supply the skin of the temporal region and parts of the ear. Palpation here confirmed localized tenderness.
The patient’s clear and reproducible pain response at these four locations strongly suggested that these peripheral branches of the trigeminal nerve were significant contributors to her overall headache experience. This phenomenon, known as peripheral sensitization, occurs when the nerve endings become hyperexcitable, lowering the threshold for firing and amplifying pain signals sent to the brain. I hypothesized that temporarily silencing these nerves could interrupt the barrage of pain signals and provide relief.

Preparing for the Nerve Block: A Meticulous Approach

With the target nerves identified, the next step was to prepare for the peripheral nerve block procedure. Precision, safety, and patient comfort guide this step.
Marking the Injection Sites: I used the retracted, smooth tip of a ballpoint pen to make very light ink marks at the four tender points. It’s crucial not to apply too much pressure, as this can cause discomfort and tissue indentation, making accurate needle placement more difficult.
Aseptic Technique: The skin was then meticulously prepped with Betadine (povidone-iodine), an antiseptic that reduces the microbial load on the skin and minimizes infection risk. We allowed it to air-dry to ensure its full antimicrobial effect.
The Anesthetic Cocktail: For the injection itself, I prepared a specific mixture designed to provide both rapid onset and extended duration of action. The solution consisted of:
0.5% Lidocaine with Epinephrine: Lidocaine is a fast-acting local anesthetic that typically begins working within minutes. Adding epinephrine, a vasoconstrictor, serves two purposes: it reduces local bleeding and, more importantly, slows systemic absorption of lidocaine, prolonging its local effect and reducing potential toxicity (Becker & Reed, 2012).
0.5% Bupivacaine: Bupivacaine has a much slower onset of action but a significantly longer duration, often providing pain relief for several hours.
By combining these two agents, we create a synergistic effect: lidocaine provides immediate relief and comfort, while bupivacaine takes over to provide a longer therapeutic window. The goal is not just to numb the area for a few minutes but to break the pain cycle for an extended period. I drew up a total of 1 mL of this mixture for each of the four injection sites.

The Procedure: A Step-by-Step Execution of the Nerve Blocks

Performing injections on the face, especially near the eyes, requires extreme care and a gentle hand. The patient was understandably apprehensive, so clear communication and a calm demeanor were essential.
Choice of Needle: I selected a 30-gauge, half-inch needle. This ultra-fine needle minimizes tissue trauma and patient discomfort. While a topical anesthetic spray can be used in other areas, its use so close to the eyes is contraindicated. In this case, the small needle size makes the initial injection itself less uncomfortable than the spray would be.
Injection Technique for Supratrochlear and Supraorbital Nerves:
For the first two injections targeting the nerves along the brow ridge, safety is the number one priority. To prevent the anesthetic from diffusing inferiorly into the orbit (the eye socket), I placed my non-dominant thumb firmly against the patient’s orbital rim, just below the injection site. This creates a physical barrier, or a bolster, to direct the fluid superiorly into the subcutaneous tissue of the forehead.
I gently advanced the needle to the marked supratrochlear nerve site until I felt the delicate “tap” of the needle tip against the periosteum (the outer surface of the bone).
I then withdrew the needle slightly, about 1-2 millimeters, so the tip was in the subcutaneous space just above the bone where the nerve lies.
Aspiration is a critical safety step. Before injecting, I pulled back on the plunger to ensure the needle was not inside a blood vessel. The absence of a blood return in the syringe hub (“no blood”) confirms a safe position.
I slowly and steadily injected 1 mL of the anesthetic solution. During the injection, I felt the fluid pressure building against my thumb, confirming that my bolster was effectively preventing orbital diffusion.
I repeated this exact process for the supraorbital nerve, again maintaining the protective thumb placement. The patient tolerated these first two injections well, with minimal discomfort.
Injection Technique for Zygomaticotemporal and Auriculotemporal Nerves:
For the zygomaticotemporal nerve on the cheekbone, the technique was similar. I advanced the needle to touch bone, withdrew slightly, and aspirated. This area is less critical for orbital diffusion, so the thumb bolster was not necessary.
For the final injection targeting the auriculotemporal nerve in the temporal region, an extra layer of caution is required. The superficial temporal artery runs in proximity to this nerve. Therefore, aspiration is absolutely mandatory here to avoid an inadvertent intravascular injection, which could lead to systemic toxicity. After confirming I was not in the artery, I proceeded to inject the final 1 mL of anesthetic.
The entire procedure, from marking to the final injection, took only a few minutes. I maintained communication with the patient throughout, reassuring her and monitoring her comfort.

Immediate Post-Procedure Assessment: Gauging the Efficacy

The true test of a nerve block’s success is the patient’s subjective response. Immediately after completing the injections, I began the assessment.
“Was that painful?” I asked.
“No, no. It felt pretty good,” she replied, visibly relieved. “It was a little pinch on a couple of them. Not as bad as we feared.”
This immediate feedback is valuable, but the primary endpoint is the effect on her headache. I asked her to re-evaluate her pain:
“You reported your headache was a seven out of ten just a moment ago. What number would you assign your headache right now?”
“I think it’s better,” she said thoughtfully. “More like a five.
A two-point drop on the pain scale within minutes of the procedure is a very encouraging sign. It indicates that peripheral nerve sensitization was a major component of her pain and that the anesthetic was working as intended.
Next, I performed a follow-up palpation exam:
I pressed over the supratrochlear nerve site. “Does that hurt?” I asked. “No,” she said. “Did it hurt before?” “Yes. Yes, it did.
I moved to the supraorbital nerve. “Does it hurt when I press over here?” “No.”
I then palpated the zygomaticotemporal and auriculotemporal nerves, both of which were no longer tender.
The resolution of localized tenderness (allodynia), combined with the reduction in her baseline headache intensity, provided a clear, positive diagnostic result. It confirmed that these four nerves were actively involved in her hemicrania continua pain pathway.
The immediate goal was achieved, but the long-term hope is that this intervention can do more. By silencing the hyperexcitable nerves for several hours, we aim to break the pain cycle. This period of relief can allow the central nervous system to “calm down,” a process known as down-regulating central sensitization. For some patients, a single series of blocks can provide relief that far outlasts the anesthetic’s pharmacological effect, sometimes for days or even weeks. For this patient, we would monitor her progress over the next hour and the following days to see whether the headache breaks completely.

The Integrative Chiropractic and Medical Framework: Our Comprehensive Approach

The nerve block procedure I’ve just described is a powerful tool, but it’s only one piece of a much larger puzzle. At Injury Medical Clinic, we believe that sustainable healing from chronic conditions like hemicrania continua requires a multifaceted approach that addresses the body as an interconnected system. This is where our unique integrative model, guided by Dr. Cardenas and me, truly shines.
Our philosophy is built on the understanding that pain, especially chronic neurological pain, is rarely caused by a single, isolated issue. It’s often the result of a cascade of dysfunction involving the musculoskeletal system, the nervous system, metabolic health, and even psychosocial factors.

The Role of Chiropractic Care in Headache Management

As a Doctor of Chiropractic, my primary focus is on the biomechanical and neurological integrity of the spine, particularly the cervical spine (the neck). The upper cervical spine houses critical neurological structures, including the brainstem and the upper cervical nerve roots, which have intricate connections with the trigeminal nucleus in the brainstem. This anatomical relationship is known as the trigeminocervical complex (Bogduk, 2003).
Cervicogenic Inputs: Misalignments or dysfunctional movement in the joints of the upper neck (vertebral subluxations) can create noxious mechanical and inflammatory signals. These signals travel from the cervical nerve roots (C1, C2, C3) and converge on the trigeminocervical nucleus, which receives sensory information from the trigeminal nerve. The brain can misinterpret these cervical signals as originating from the head, a phenomenon known as referred pain. This can initiate or exacerbate a headache.
Chiropractic Adjustments: Gentle, specific chiropractic adjustments are designed to restore proper motion and alignment to the cervical vertebrae. By correcting these biomechanical faults, we can:
Reduce nerve irritation: Alleviate direct or indirect pressure on the cervical nerve roots and surrounding tissues.
Improve proprioception: Restore the normal flow of sensory information from the joints and muscles of the neck to the brain, which can help down-regulate pain processing centers.
Decrease muscle tension: Hypertonicity in the suboccipital and other neck muscles is a common finding in headache sufferers. Adjustments can help normalize muscle tone by resetting the neural feedback loops that control muscle contraction.
For a patient with hemicrania continua, chiropractic care is not aimed at “curing” the primary headache disorder itself. Instead, it serves to remove any co-existing cervicogenic contributions that may be lowering the threshold for an attack or adding to the overall pain burden. By optimizing cervical spine function, we can reduce the overall “noise” in the trigeminocervical complex, potentially making the primary headache less frequent, less severe, and more responsive to other treatments.

Functional Medicine: Looking for the Root Cause

Functional medicine provides another critical layer to our integrative approach. Instead of just managing symptoms, we ask why the patient is experiencing this dysfunction in the first place. For headache disorders, we investigate several key areas:
Nutrient Deficiencies: Certain micronutrients are essential for proper neurological function and inflammation control. Deficiencies in magnesium, Coenzyme Q10 (CoQ10), and riboflavin (Vitamin B2) have been linked to an increased risk of headaches, particularly migraines (Schürks et al., 2008; Sándor et al., 2005). We use advanced laboratory testing to identify and correct these deficiencies with targeted supplementation.
Gut Health and Food Sensitivities: The gut-brain axis is a bidirectional communication highway between the gastrointestinal system and the central nervous system. An imbalanced gut microbiome (dysbiosis) or increased intestinal permeability (“leaky gut”) can trigger systemic inflammation, which can, in turn, lower the threshold for headache attacks. Identifying and eliminating trigger foods through an elimination diet or food sensitivity testing can be a game-changer for many patients.
Hormonal Imbalances: Fluctuations in hormones, especially estrogen in women, can be a powerful headache trigger. We assess sex hormones and adrenal function (e.g., cortisol levels) to identify imbalances that may be contributing to the patient’s condition.
Mitochondrial Dysfunction: Mitochondria are the powerhouses of our cells, including our neurons. When they don’t function optimally, they can trigger an “energy crisis” in the brain, making it more susceptible to conditions like headaches and neuroinflammation. Supporting mitochondrial health with nutrients like CoQ10, L-carnitine, and D-ribose can be a foundational part of our treatment plan (Yorns & Hardison, 2013).
By addressing these underlying metabolic and physiological imbalances, functional medicine helps to improve the body’s overall resilience and reduce the systemic factors that may be perpetuating the headache cycle.

The Synergy of a Multidisciplinary Team

The true strength of our clinic lies in how these different disciplines are woven together under the expert medical oversight of Dr. Maria Cardenas. Her role as our Medical Director is indispensable.
Medical Diagnosis and Oversight: Dr. Cardenas provides the definitive medical diagnosis and ensures that all potential red flags or more serious underlying pathologies are ruled out. Her internal medicine expertise is crucial for managing patients with complex comorbidities.
Pharmacological Management: For a condition like hemicrania continua, the response to indomethacin is diagnostic. Dr. Cardenas manages the prescription and monitoring of such medications, ensuring they are used safely and effectively, especially considering the potential side effects of long-term NSAID use.
Collaborative Treatment Planning: We hold regular team meetings to discuss patient cases. I might present my findings from a chiropractic and functional neurology perspective, while Dr. Cardenas provides her medical insights. Together, we formulate a comprehensive treatment plan. For the patient described earlier, the plan might look like this:
Immediate Pain Control: Peripheral nerve blocks performed by me (as an FNP) under Dr. Cardenas’s collaborative agreement to break the acute pain cycle.
Biomechanical Support: A course of gentle chiropractic adjustments to address underlying cervicogenic factors.
Medical Management: A trial of indomethacin prescribed and monitored by Dr. Cardenas to confirm the diagnosis and provide baseline control.
Functional Medicine Investigation: Lab testing for nutritional deficiencies, food sensitivities, and hormonal imbalances to address root-cause contributors.
Rehabilitation: Our team of rehabilitation specialists would design a program of specific exercises to improve neck posture, strengthen deep neck flexors, and provide lasting stability.
This integrated model ensures the patient receives the best of all worlds in a coordinated, synergistic way. We are not just a collection of individual practitioners; we are a cohesive team working toward a single goal: the patient’s well-being.

Conclusion: A New Horizon for Headache Sufferers

The case of the 71-year-old patient with hemicrania continua is a powerful illustration of how a precise diagnostic procedure can provide immediate clarity and relief. The successful nerve block not only alleviated her pain but also confirmed the involvement of specific peripheral nerves, guiding our subsequent treatment strategy.
However, the larger takeaway is the power of the integrative framework in which this procedure took place. Managing complex chronic pain requires moving beyond a single-modality approach. It demands a holistic perspective that honors the intricate connections between the body’s systems—musculoskeletal, neurological, metabolic, and biochemical.
At Injury Medical Clinic, our collaboration across chiropractic care, advanced practice nursing, functional medicine, and internal medicine, under the leadership of Dr. Maria Cardenas, allows us to provide this level of comprehensive care. We strive not only to manage symptoms but to restore function, improve resilience, and empower our patients to reclaim their lives from chronic pain. If you or a loved one is struggling with a persistent headache, know that there is hope. By looking at the whole picture, we can uncover new possibilities for healing and well-being.

References

SEO Tags: Hemicrania Continua, Headache Treatment, Nerve Block, Integrative Medicine, Dr. Alex Jimenez, El Paso Chiropractor, Functional Medicine, Trigeminal Nerve, Chronic Pain, Chiropractic Care, Cervicogenic Headache, Dr. Maria Cardenas, Injury Medical Clinic, Pain Management, Peripheral Nerve Block, Lidocaine, Bupivacaine, Indomethacin, Trigeminal Autonomic Cephalalgia, Integrative Chiropractic Care

Legal Peptide Therapy and Integrative Chiropractic Care in El Paso

Legal Peptide Therapy and Integrative Chiropractic Care in El Paso

Abstract

Peptide therapy is becoming an important topic in integrative medicine, metabolic health, weight management, hormone care, and physical recovery. However, not every peptide sold online or discussed on social media is FDA-approved or appropriate for medical treatment. Legal peptide use depends on the specific medication, its FDA status, how it is prescribed or compounded, the patient’s medical needs, and federal and state laws.

At ChiroMed – Integrated Medicine in El Paso, Texas, an integrative model can bring medical evaluation, nurse practitioner services, chiropractic care, functional medicine, nutrition, and rehabilitation together. Medical providers handle evaluation and prescription decisions within their professional authority, while chiropractic care focuses on biomechanics, joint function, movement, strength, and musculoskeletal rehabilitation. This article explains how these roles can work together while keeping peptide treatment patient-centered, medically appropriate, and within professional scope.

Legal Peptide Therapy and Integrative Chiropractic Care in El Paso

What Is Legal Peptide Therapy?

Peptides are short chains of amino acids. Amino acids are the building blocks of proteins, and many naturally occurring peptides act as signals inside the body.

Some peptide-based medicines have established medical uses. Others remain experimental or have limited evidence in people.

The important question is not simply, “Are peptides legal?”

A better question is:

Is this specific peptide legally available and medically appropriate for this particular patient, from this particular source, and for this particular use?

Legal medical use can include several different situations:

  • An FDA-approved peptide-based drug used for an approved indication
  • An FDA-approved medication prescribed for a medically appropriate off-label use
  • A compounded medication prepared under applicable federal and state requirements
  • An investigational drug being used through an authorized research pathway

These categories are not interchangeable.

The FDA makes an especially important distinction regarding compounded medications. Compounded medications can serve a medical need for certain patients, but they are not FDA-approved. The FDA does not review each compounded medication for safety, effectiveness, or manufacturing quality before it reaches the patient (U.S. Food and Drug Administration [FDA], 2026a).

Why “Research Peptides” Are Different

Patients may see peptides advertised online with labels such as:

  • “Research use only”
  • “Not for human consumption”
  • “Laboratory use only”

These labels should not be confused with an FDA-approved prescription medication or a lawfully prepared compounded prescription.

The fact that a chemical can be purchased through a website does not establish that it is approved or appropriate for human treatment.

This is especially important because peptide regulation continues to change. Different substances may have different FDA classifications, compounding restrictions, safety concerns, and available evidence.

Under Sections 503A and 503B of the Federal Food, Drug, and Cosmetic Act, the FDA limits which bulk drug substances may be used. These lists and regulatory policies can change as new evidence becomes available (FDA, 2026b).

For this reason, healthcare professionals should evaluate the current regulatory status of the specific peptide rather than assuming that all peptides fall into the same category.

Compounded Peptides Require Special Attention

Compounding can be valuable when a commercially available FDA-approved medication cannot meet a patient’s individual medical need.

For example, a patient might need a different dosage form because of an allergy or another clinical concern.

However, compounding does not automatically make a peptide legal, FDA-approved, or appropriate.

Under federal rules, Section 503A compounders face requirements about which bulk substances they may use. Section 503B outsourcing facilities also operate under specific limits regarding bulk substances and drug shortages (FDA, 2026b).

Patients should understand an important difference:

An FDA-approved medication and a compounded version of a medication are not the same regulatory product.

The FDA states that compounded drugs have not gone through FDA premarket approval for safety, effectiveness, and quality (FDA, 2026a).

This makes pharmacy selection, clinical justification, documentation, dosing, patient education, and follow-up especially important.

What the New Mexico Board of Nursing Says

The September 2026 New Mexico Board of Nursing Peptide Therapies FAQ provides a useful example of how one state nursing board is approaching this rapidly changing field.

The Board emphasizes that its FAQ provides general interpretation only. It specifically states that the document is not a legal opinion and cannot be cited as legal authority.

The guidance states that APRNs prescribing compounded medications should remain within their education, experience, population focus, and prescriptive authority. It also emphasizes a valid provider-patient relationship, appropriate history and physical examination, clinical justification, informed consent, monitoring, and documentation.

The Board also recommends that clinicians:

  • Make sure compounding is legally permitted
  • Use appropriately licensed pharmacies
  • Explain when a patient is receiving a compounded medication
  • Document the reason for using the compounded product
  • Avoid questionable or unverified sources

The New Mexico guidance is useful for understanding professional safety principles, but ChiroMed is located in Texas. Therefore, Texas law and Texas professional licensing requirements govern care delivered in Texas.

Chiropractic and Medical Roles Must Remain Clear in Texas

ChiroMed describes itself as an integrated healthcare practice bringing chiropractic care, nurse practitioner services, rehabilitation, nutrition, and other healthcare disciplines together in one setting.

Clear professional roles are important in this type of practice.

Under Texas Occupations Code §201.002, chiropractic practice includes evaluation of the biomechanical condition of the spine and musculoskeletal system and nonsurgical, noninvasive procedures intended to improve musculoskeletal biomechanics.

The same law states that chiropractic practice does not include prescribing controlled substances, dangerous drugs, or other prescription drugs.

Therefore, a clinician cannot prescribe peptides under a Texas chiropractic license alone.

This distinction is especially important for a clinician such as Dr. Alexander Jimenez, DC, APRN, FNP-BC, who holds both chiropractic and advanced practice nursing credentials.

His chiropractic license supports chiropractic and musculoskeletal care. Medical evaluation and prescription decisions must be performed under the appropriate APRN authority and applicable Texas rules.

The Nurse Practitioner’s Role in Peptide Therapy

Texas APRNs who prescribe medications must meet Texas requirements for prescriptive authority.

Texas law allows qualified APRNs and physicians to enter into prescriptive authority agreements. These agreements define the practice setting, medication categories, consultation, communication, quality assurance, and referral processes.

This makes the medical side of peptide therapy different from chiropractic treatment.

Depending on the patient’s needs, the medical evaluation may include:

  • Medical history
  • Current medications and supplements
  • Physical examination
  • Laboratory testing
  • Contraindications and risk factors
  • Diagnosis
  • Treatment alternatives
  • Medication selection
  • Informed consent
  • Follow-up laboratory testing
  • Response to treatment
  • Side-effect monitoring

Do not select a peptide simply because it is popular.

The patient’s diagnosis, health history, goals, risks, available evidence, and legal treatment options should guide the medical decision.

ChiroMed’s Multidisciplinary Model

At ChiroMed – Integrated Medicine, the goal is to bring different parts of healthcare together rather than treating each problem in isolation.

ChiroMed describes its services as including chiropractic care, nurse practitioner services, rehabilitation, nutrition, and integrative approaches for patients with musculoskeletal, injury, chronic pain, and wellness concerns.

The multidisciplinary team also includes Dr. Maria Guadalupe Cardenas, MD, whom ChiroMed identifies as a board-certified internal medicine physician, Medical Director, and Collaborative Physician with more than four decades of experience.

Public NPI information lists Dr. Maria Guadalupe Cardenas as an internal medicine physician in El Paso with NPI 1164426748 and Texas medical license J2933.

Within this model, Dr. Cardenas provides medical direction and internal medicine experience alongside Dr. Jimenez’s work in advanced practice nursing, chiropractic care, functional medicine, injury management, and rehabilitation.

The goal is coordinated care, while each clinician works within the appropriate professional scope.

How Chiropractic Care Can Complement Peptide Treatment

Chiropractic treatment should not be promoted as making a peptide medication more powerful.

Instead, these treatments may address different parts of a patient’s overall health and recovery.

A medically managed therapy may address a specific metabolic, hormonal, or medical problem.

Chiropractic and rehabilitation care can focus on the patient’s ability to move and function.

At ChiroMed, integrative chiropractic care may support:

  • Joint mobility
  • Spinal biomechanics
  • Range of motion
  • Posture
  • Muscle balance
  • Functional strength
  • Neuromuscular coordination
  • Progressive exercise
  • Return to normal activities
  • Injury rehabilitation

ChiroMed’s published clinical model emphasizes connecting medical evaluation with chiropractic care and rehabilitation rather than replacing one healthcare profession with another.

This can be particularly useful when a patient has both a medical concern and a musculoskeletal limitation.

For example, a patient receiving medical weight-management treatment may need help maintaining muscle mass, increasing activity, and improving physical function.

Strength and Muscle Preservation Matter

Muscle health deserves special attention during some medical weight-management programs.

The New Mexico Board of Nursing guidance recommends attention to:

  • Adequate protein
  • Resistance exercise
  • Preservation of lean body mass
  • Vitamin and nutrient intake
  • Long-term lifestyle changes

Rehabilitation and integrative chiropractic care may fit naturally into a broader treatment plan.

A patient with back pain, knee pain, poor mobility, or an old injury may find exercise difficult. Treating mechanical barriers and developing a progressive rehabilitation program may help that person become more physically active.

The goal is not simply weight loss.

It is to help patients maintain:

strength + mobility + muscle + function.

Clinical Observations From Dr. Alexander Jimenez

In his clinical writings, Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN, describes health and recovery through a systems-based approach.

Instead of relying on one treatment, his clinical model connects areas such as:

  • Chiropractic biomechanics
  • Functional medicine
  • Nutrition
  • Musculoskeletal rehabilitation
  • Laboratory findings when appropriate
  • Strength and conditioning
  • Injury recovery
  • Medical evaluation
  • Lifestyle modification

This philosophy is also reflected throughout ChiroMed’s published material, which describes integrated injury care as a combination of medical evaluation, chiropractic care, functional medicine, rehabilitation, and other supportive options.

Peptide treatment, when medically appropriate and legally available, can therefore be one part of a larger care plan, not a replacement for good nutrition, exercise, rehabilitation, sleep, or medical monitoring.

A Patient-Centered Approach to Peptide Therapy

Responsible peptide treatment should begin with the patient—not with a product.

Before considering treatment, the healthcare team should determine:

  • What problem is being treated?
  • Is there an established diagnosis?
  • Is the medication FDA-approved?
  • If it is compounded, why is compounding medically appropriate?
  • Is there reasonable evidence supporting its use?
  • What are the risks and alternatives?
  • Does the patient’s medical history create contraindications?
  • What monitoring will be needed?
  • Who is responsible for prescribing and follow-up?
  • Is the pharmacy properly licensed?
  • Is the treatment permitted under current federal and state requirements?

The New Mexico Board’s guidance similarly emphasizes history, examination, laboratory testing when indicated, informed consent, documentation, treatment response, adverse effects, and follow-up.

Integrating Medicine, Movement, and Recovery at ChiroMed

The future of integrative healthcare is not about one profession trying to perform every type of treatment.

It is about different professionals contributing their expertise to the same patient.

At ChiroMed – Integrated Medicine in El Paso, chiropractic care can address biomechanics, movement, spinal and joint health, physical strength, and rehabilitation. Advanced practice nursing can provide appropriate medical evaluation and treatment within APRN scope and Texas prescriptive authority. Internal medicine leadership can add another layer of medical direction and clinical coordination.

Nutrition, functional medicine, personal injury care, and rehabilitation can then support the patient’s larger goals.

This creates a practical model:

Medical care addresses medical needs.
Chiropractic care addresses biomechanics and musculoskeletal function.
Rehabilitation develops strength and movement.
Nutrition provides the building blocks for recovery.
Medical oversight helps keep the entire plan appropriate and coordinated.

Peptide science will continue to change. Some peptide-based medications already have established medical roles, while other substances remain investigational, restricted, or supported by limited human evidence.

For patients and clinicians alike, the safest approach is to focus on evidence, professional scope, current regulations, appropriate medical evaluation, legitimate pharmacy sources, and careful follow-up.

At ChiroMed, integrated care means looking beyond one medication or one adjustment and building a treatment plan around the health and functional needs of the whole person.


References

ChiroMed – Integrated Medicine. (2026a). Integrated medicine services in El Paso, Texas.

ChiroMed – Integrated Medicine. (2026b). ChiroMed – Integrated Medicine: Holistic healthcare in El Paso, TX.

ChiroMed – Integrated Medicine. (2026c). Integrated injury care in El Paso, TX.

ChiroMed – Integrated Medicine. (2026d). Peptide therapy, nutrition, and integrative chiropractic care.

Food and Drug Administration. (2026a). Compounding and the FDA: Questions and answers.

Food and Drug Administration. (2026b). Bulk drug substances used in compounding under Section 503A of the FD&C Act.

Food and Drug Administration. (2026c). Human drug compounding.

Jimenez, A. (2026). Peptide therapy, nutrition, and chiropractic care explained.

New Mexico Board of Nursing. (2026). Peptide therapies: Clinical practice frequently asked questions.

Texas Board of Nursing. (2026). APRN practice frequently asked questions.

Texas Legislature. (2026a). Texas Occupations Code Chapter 157: Authority of physician to delegate certain medical acts.

Texas Legislature. (2026b). Texas Occupations Code Chapter 201: Chiropractors.

Integrative Strategies to Consider for Insulin Resistance


Unlock the benefits of integrative strategies for insulin resistance and take charge of your health today.

Abstract

For decades, the standard approach to managing insulin resistance has centered on dietary restrictions, often with frustratingly limited success. Many individuals find that even strict low-carbohydrate, ketogenic, or carnivore diets fail to resolve the underlying metabolic dysfunction fully. This educational post explores the deeper physiological reasons for this phenomenon, moving beyond surface-level dietary changes to address the root causes of metabolic inflexibility. As Dr. Alex Jimenez, I will guide you through the cellular mechanisms that perpetuate insulin resistance, including compromised mitochondrial function, chronic inflammation, and cellular “deafness” to insulin signals. We will explore the latest scientific findings from leading researchers, highlighting innovative therapeutic agents like 5-amino-1MQ, retatrutide, and MOTS-c, which show remarkable promise in restoring insulin sensitivity and metabolic health. This discussion will also detail a practical “daily audit” protocol, integrating strategic nutrition with continuous glucose monitoring to empower you with real-time feedback on your metabolic status. We’ll also explain how our multidisciplinary practice at Injury Medical Clinic PA integrates advanced functional medicine with chiropractic care and medical oversight from our esteemed Medical Director, Dr. Maria Guadalupe Cardenas, MD, to provide a comprehensive, personalized approach to reversing insulin resistance and reclaiming your health.


A Multidisciplinary Approach to Whole-Body Health at Injury Medical Clinic

Before we dive into the complex world of cellular metabolism, it’s important to understand the care framework we provide at our clinic. My name is Dr. Alex Jimenez, and I hold certifications as a Doctor of Chiropractic (DC), an Advanced Practice Registered Nurse (APRN) and Family Nurse Practitioner (FNP-BC), a Certified Functional Medicine Practitioner (CFMP), and an Institute for Functional Medicine Certified Practitioner (IFMCP), among other advanced credentials in anti-aging and clinical cellular science. Our practice, Injury Medical Clinic PA, also known as Mission Plaza Injury Medical Clinic, is located in El Paso, Texas, and is built on a foundation of integrative, multidisciplinary care.

I am honored to work alongside Dr. Maria Guadalupe Cardenas, MD, our Medical Director and Collaborative Physician. Dr. Cardenas is Board Certified in Internal Medicine and brings over 40 years of invaluable experience as an internist to our team. Her extensive medical expertise (NPI #1164426749, Texas MD License #J2933) is fundamental to our ability to offer a truly holistic patient experience. This collaborative model, where a chiropractor with advanced training in functional medicine works alongside a seasoned medical doctor, allows us to bridge gaps between healthcare disciplines. We combine the strengths of chiropractic care—focusing on musculoskeletal integrity, nervous system function, and structural health—with the diagnostic precision and medical oversight of internal medicine.

Our team integrates:

  • Chiropractic Care: We address spinal and joint misalignments (subluxations) that can interfere with nerve signaling, which is crucial for organ function and metabolic regulation.
  • Medical Oversight: Dr. Cardenas provides essential medical direction, overseeing patient cases, managing comorbidities, and ensuring all treatments are safe and medically appropriate.
  • Functional Medicine: We use advanced diagnostic testing to identify the root causes of chronic disease, such as nutrient deficiencies, hormonal imbalances, and gut dysbiosis.
  • Personal Injury & Rehabilitation: We specialize in helping patients recover from injuries, using a combination of physical therapies, chiropractic adjustments, and rehabilitative exercises to restore function and reduce pain.

This synergistic model ensures that when we address a complex condition like insulin resistance, we look at the whole person—not just their blood sugar numbers. We consider their structural health, cellular biology, lifestyle, and unique biochemistry to create a personalized, effective treatment plan.


The Frustration of Failed Diets: Why Insulin Resistance Persists

One of the most common frustrations I hear from patients is, “Doctor, I’ve tried everything. I cut out carbs, I went keto, I even did the carnivore diet, but I’m still not getting better.” They are often disheartened, feeling like their body has betrayed them despite their best efforts. The reality is that diets alone often fail to reverse severe, long-standing insulin resistance. This is not a failure of willpower; it is a failure to understand the deep-seated biological adaptations that have occurred over years, or even decades.

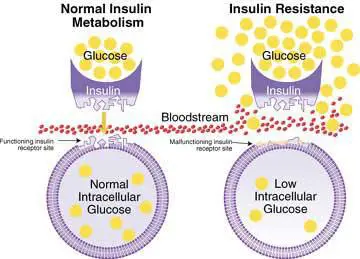
Insulin resistance

Imagine spending thirty years in a state of hyperinsulinemia—a condition where your pancreas is constantly pumping out high levels of insulin to manage blood glucose. Over time, your body’s cells, receptors, and mitochondria become, for lack of a better term, “trashed.” The entire system is damaged and dysregulated.

Let’s break down why this happens:

Muscle Glycogen Stores and Metabolic Inflexibility

From a basic biological standpoint, our muscles are a primary storage site for glucose, stored as glycogen. In an active individual, these glycogen stores are regularly depleted through exercise and then refilled after a meal. This is a healthy, dynamic process. However, in a sedentary lifestyle, these muscle glycogen stores remain consistently full.

Think of it like a gas tank that is never emptied. If the tank is already full, you can’t add more fuel. Similarly, if your muscle cells are packed with glycogen, they don’t need the glucose circulating in your bloodstream. They effectively put up a “No Vacancy” sign. They become insulin resistant because they are signaling that they don’t need any more fuel. Even if you switch to a low-carb, keto, or carnivore diet, muscles can remain stubbornly resistant if they aren’t metabolically challenged through physical activity. The cells have developed metabolic inflexibility; they have lost the ability to switch efficiently between burning carbohydrates and burning fat for energy.

The Liver’s Role: A Rogue Glucose Factory

While the muscles are refusing glucose, the liver becomes trapped in a vicious cycle of its own. In a state of chronic hyperinsulinemia, the liver often becomes a site for fat accumulation, a condition known as non-alcoholic fatty liver disease (NAFLD). A fatty liver is a dysfunctional liver. It becomes hyperresponsive to the hormone glucagon (which tells the liver to release glucose) and simultaneously resistant to insulin (which tells the liver to stop releasing glucose).

This creates a paradoxical and dangerous situation. Even when you diligently cut sugar and processed carbohydrates from your diet, your liver keeps pumping large amounts of glucose into the bloodstream. This process is called gluconeogenesis—literally, “the creation of new glucose.” The liver manufactures glucose from non-carbohydrate sources, such as amino acids and lactate.

So you can eat zero carbohydrates, yet your blood sugar can remain elevated because your liver has turned into a rogue glucose factory. This is a critical point that many people miss. The problem is no longer just what we’re eating; it’s deep-seated dysfunction within the liver. This state will persist until the excess visceral fat is mobilized and the liver is metaphorically “unclogged.” That’s why insulin resistance can be such a bear to resolve. It’s a deeply entrenched physiological state, not just a simple dietary problem.


A Deeper Look: Mitochondrial Dysfunction and Cellular Deafness

To truly understand insulin resistance, we have to zoom in from the organ level to the cellular and even the subcellular level. The real battle is being fought inside your cells, specifically within the mitochondria and at the insulin receptor sites.

Lipid Overload and Impaired Insulin Signaling

When you are chronically hyperinsulinemic, your body is in a constant state of “energy storage.” This leads to the accumulation of lipids (fats) not just in your fat cells, but also inside other cells, such as muscle and liver cells. These intracellular lipid deposits, known as intramyocellular lipids, directly interfere with the insulin signaling pathway.

Here’s how it works: When insulin binds to its receptor on the cell surface, it initiates a complex cascade of signals inside the cell. This cascade is like a series of dominoes falling, ultimately activating glucose transporter type 4 (GLUT4). GLUT4 is the protein that moves to the cell membrane and creates a channel for glucose to enter the cell. In a healthy cell, this process is smooth and efficient.

However, when lipids accumulate inside the cell, they create metabolic byproducts—like diacylglycerol (DAG) and ceramides—that disrupt this signaling cascade. These lipid metabolites effectively jam the machinery. They prevent the dominoes from falling. As a result, even though insulin is present and binding to its receptor, the signal to bring GLUT4 to the surface is blocked. Glucose cannot get into the cell.

I often describe this to my patients as cellular deafness. The cell is being screamed at by insulin, but it can’t “hear” the message. It’s like trying to unlock a door with the wrong key, or a bent key. The lock (the receptor) is there, the key (insulin) is there, but the internal mechanism is broken.

The Problem with Standard Lab Tests: Why HbA1c is Deceiving

This leads us to another critical point of confusion: standard lab testing. For years, the Hemoglobin A1c (HbA1c) test has been the gold standard for diagnosing and monitoring diabetes. The HbA1c measures the percentage of your hemoglobin (the protein in red blood cells that carries oxygen) that is coated with sugar (glycated). Because red blood cells live about three months, HbA1c gives you a rough average of your blood sugar over the preceding 90 days.

However, in the context of early to moderate insulin resistance, HbA1c is a totally useless, lagging indicator. At best, it lags three months behind real-time metabolic reality. I see severely insulin-resistant patients walk into my clinic every week with a “normal” HbA1c. How is this possible?

It’s possible because the pancreas is a remarkably resilient organ, at least initially. As the cells become more resistant to insulin, the pancreas compensates by working overtime, dumping gallons of insulin into the bloodstream to force the glucose into the cells. The cells are literally drowning in insulin, but because the pancreas is fighting so hard, the blood glucose levels may remain in the normal range for years. The HbA1c looks fine, but beneath the surface, the pancreas is working itself to death. This is compensated insulin resistance, and it’s a ticking time bomb. Eventually, the pancreatic beta cells will become exhausted and begin to fail, at which point blood glucose will skyrocket, and the HbA1c will finally reflect the long-standing disease process. By then, significant damage has already been done.

A Better Metric: HOMA-IR

A far more sensitive and immediate tool for assessing insulin resistance is the Homeostatic Model Assessment of Insulin Resistance (HOMA-IR). This calculation uses a simple formula that accounts for both your fasting glucose and fasting insulin levels.

HOMA-IR = (Fasting Glucose [mg/dL] x Fasting Insulin [μU/mL]) / 405

This score gives us a direct snapshot of how hard your pancreas is working to maintain a normal blood sugar level. In our practice, we consider a HOMA-IR score over 1.0 to be an indication of early insulin resistance. A score over 1.9 indicates significant resistance, and a score over 2.9 is often correlated with a high risk of developing type 2 diabetes. HOMA-IR lets us detect metabolic dysfunction years, or even decades, before HbA1c becomes abnormal. It allows us to be proactive instead of reactive.

You must stop treating insulin resistance as if it’s merely a weight loss goal. If you focus only on the number on the scale, you are going to lose the battle. We need to address the underlying physiology: inflammation, mitochondrial issues, and cellular deafness.


Is Intermittent Fasting the Ultimate Weight Loss Hack?- Video


The Chiropractic Link: Nervous System Integrity and Metabolic Function

At this point, you might be wondering, “What does chiropractic care have to do with insulin and mitochondria?” The connection lies in the body’s master control system: the nervous system. The brain, spinal cord, and peripheral nerves coordinate and regulate every single function in your body, including metabolism.

The autonomic nervous system (ANS) has two main branches: the sympathetic (“fight or flight”) and the parasympathetic (“rest and digest”). A healthy metabolism depends on a proper balance between these two branches. Chronic stress—be it physical, chemical, or emotional—can lead to a state of sympathetic dominance, where the “fight or flight” response is perpetually activated. This state is characterized by the release of stress hormones like cortisol and adrenaline, which directly promote insulin resistance by signaling the liver to release glucose and making peripheral cells less sensitive to insulin.

Chiropractic adjustments work to restore proper motion and alignment to the spine, particularly in the upper cervical and thoracic regions where key autonomic nerve centers are located. By correcting vertebral subluxations—misalignments that can interfere with nerve function—we can help down-regulate the sympathetic nervous system and up-regulate the parasympathetic nervous system. This shift helps to:

  • Reduce circulating stress hormones.
  • Improve blood flow to internal organs, including the pancreas and liver.
  • Enhance the body’s overall ability to “rest, digest, and repair.”

By improving neurological communication between the brain and the body’s metabolic organs, chiropractic care can help create a physiological environment more conducive to healing and restoring insulin sensitivity. It is a foundational piece of the puzzle, ensuring that the body’s internal signaling pathways are clear and functioning optimally. This is a core component of how our integrated model at Injury Medical Clinic supports metabolic recovery.


Hacking the System: Novel Therapeutics to Restore Cellular Function

While lifestyle interventions like diet, exercise, and chiropractic care are foundational, for many individuals with deep-seated insulin resistance, they may not be enough to overcome the profound cellular dysfunction. This is where cutting-edge functional medicine comes in, using targeted compounds that can directly address the biochemical roadblocks we’ve discussed. Let’s explore the science behind some of the most promising agents.

Replenishing the Engine: The Role of NAD+ and 5-amino-1MQ

Let’s get into the biology for a second. One of the most critical molecules in your entire body is Nicotinamide Adenine Dinucleotide (NAD+). NAD+ is a vital cofactor—a “helper molecule”—for hundreds of enzymatic reactions. Think of it as the spark plug for your cellular engine. It is an essential electron carrier in ATP synthesis (energy production) in the mitochondria. It’s also crucial for DNA repair, gene expression, and immune function. You cannot run your biology without it.

Here’s the problem: In chronic hyperinsulinemia and inflammation, an enzyme called NNMT (Nicotinamide N-methyltransferase) becomes significantly overactive. NNMT’s primary job is to process and eliminate excess nicotinamide (a form of vitamin B3). However, when it’s in overdrive, it wreaks havoc on your NAD+ levels. It constantly consumes NAD+ by converting it to a byproduct called N1-methylnicotinamide (MNA), effectively draining your cellular battery. This constant NAD+ depletion causes mitochondria to fail and your metabolism to tank.

This is where a remarkable compound called 5-amino-1MQ comes in. 5-amino-1MQ is a small, membrane-permeable molecule that potently inhibits the NNMT enzyme. By blocking NNMT, it prevents excessive NAD+ breakdown. Simply put, it stops the leak in the bucket, allowing your cellular NAD+ pool to be replenished. It floods the system with the critical cofactor it needs to function properly.

The research on this is incredibly exciting.

  • A landmark study published in Cell Metabolism in 2023 showed that subcutaneous administration of 5-amino-1MQ in overweight and obese individuals significantly improved insulin sensitivity, as measured by HOMA-IR (Agerholm et al., 2023). The study found a 34% improvement in insulin sensitivity, along with reductions in body weight, fat mass, and cholesterol levels. This provides powerful evidence that targeting the NNMT enzyme can directly reverse key aspects of metabolic syndrome.

By restoring NAD+ levels, 5-amino-1MQ helps to “reboot” the mitochondria, improve energy production, and make cells more responsive to insulin signaling. It is a prime example of using targeted biochemical intervention to fix a specific, identified dysfunction.

Rewriting the Script: Retatrutide and Full Insulin Independence

For decades, the goal for many type 2 diabetes patients has been “management”—keeping blood sugar under control with a cocktail of medications. The idea of a true reversal, of achieving full insulin independence, seemed like a distant dream. That is, until now.

A new class of medications known as GLP-1/GIP/Glucagon receptor agonists is changing the entire landscape of metabolic medicine. One of the most powerful of these is retatrutide. This molecule is a triple agonist, meaning it activates three different hormone receptors involved in metabolic regulation:

  1. GLP-1 (Glucagon-like peptide-1): Enhances insulin secretion, slows gastric emptying, and promotes satiety.
  2. GIP (Glucose-dependent insulinotropic polypeptide): Also enhances insulin secretion and appears to play a role in fat metabolism.
  3. Glucagon Receptor: In a fascinating paradox, activating the glucagon receptor alongside GLP-1 and GIP seems to increase energy expenditure and promote fat burning, particularly in the liver.

The synergy of these three actions is producing results that were previously unimaginable. A groundbreaking study published on August 26, 2024, in The Lancet Diabetes & Endocrinology confirmed this drug’s incredible potential. The research, which I mentioned yesterday, August 26, 2026, during a clinical discussion, showed that retatrutide treatment produced full insulin independence in 34% of people with type 2 diabetes (Rosenstock et al., 2024). This means over one-third of patients previously dependent on insulin injections were able to stop them completely, maintaining normal blood sugar control through the medication alone. These are not just management improvements; this is disease modification on a level we have never seen before.

Building a Better Powerhouse: The Promise of MOTS-c

While replenishing NAD+ helps repair existing mitochondria, what if we could build entirely new, more efficient ones? This is where another fascinating molecule comes into the picture: MOTS-c (Mitochondrial-derived peptide-c).

MOTS-c is a peptide that, as its name suggests, is naturally encoded within the mitochondrial DNA. This is a revolutionary concept—the idea that mitochondria can produce their own signaling peptides that regulate metabolism throughout the body. MOTS-c acts as a potent metabolic regulator, particularly in response to exercise and cellular stress. Its primary functions include:

  • Enhancing glucose uptake and utilization in muscle cells.
  • Improving fatty acid oxidation (the ability to burn fat for fuel).
  • Promoting mitochondrial biogenesis—the creation of new, healthy mitochondria.

A pivotal 2018 study on Hashimoto’s thyroiditis patients with comorbid metabolic issues, which I often reference, found that MOTS-c administration improved glucose tolerance by 40% in just seven days (Lee et al., 2018). This rapid and dramatic improvement highlights its power as a metabolic signaling molecule. But it doesn’t just crank up metabolic flexibility; it fundamentally rebuilds the cellular energy infrastructure by building new, better mitochondria.

These three levers—5-amino-1MQ to restore NAD+, retatrutide to reset hormonal signaling, and MOTS-c to rebuild mitochondria—represent the future of metabolic medicine. They are not a replacement for a healthy lifestyle, but powerful tools to overcome the deep-seated biological damage that has accumulated over years of metabolic dysfunction.


The Daily Audit: A Practical Guide to Monitoring Your Metabolism

Knowledge is power, but only if you can apply it. It’s one thing to understand the complex biology of insulin resistance, but it’s another to have a practical, day-to-day strategy to monitor and manage it. In my practice, I guide patients through a “daily audit” protocol. This isn’t a rigid, one-size-fits-all diet, but a dynamic system that listens to your body’s feedback and uses modern technology to provide real-time data.

This approach is built on a Continuous Glucose Monitor (CGM). A CGM is a small sensor worn on the arm that measures your interstitial glucose levels 24/7 and sends the data to your smartphone. This technology is a game-changer. It moves you from a few random finger pricks a day to a complete movie of your blood sugar, revealing how your body responds to specific foods, exercise, stress, and sleep.

Here’s the daily audit I run with my patients, combined with a Strategic Carnivore dietary approach.

Step 1: The Strategic Carnivore Diet

This dietary strategy is designed to maximize metabolic flexibility while supporting crucial hormonal conversions. Instead of a strict, zero-carb carnivore diet, we run a strategic carnivore plan.

  • Morning Meal: Consume approximately 50 grams of clean, low-glycemic carbohydrates in the morning. Sources include sweet potatoes, quinoa, berries, or steel-cut oats.
  • Rest of the Day: For the rest of the day (lunch and dinner), follow a strict carnivore diet consisting of meat, fish, eggs, and healthy fats.

Why this specific structure?

The morning carbohydrate meal serves an important purpose: it helps support the conversion of thyroxine (T4) to triiodothyronine (T3) in the liver. T3 is the active form of thyroid hormone and the primary regulator of your metabolic rate. Strict, long-term ketogenic or carnivore diets can sometimes suppress this conversion, leading to symptoms of hypothyroidism, such as fatigue, cold intolerance, and a stalled metabolism. Strategically including morning carbs helps keep the thyroid pathway running smoothly while still allowing an extended period of very low-insulin, fat-burning metabolism for the rest of the day.

Step 2: The Post-Meal Glucose Test

This is where your CGM becomes your personal metabolic lab.

  • The Test: After your morning 50-gram carbohydrate meal, closely monitor your glucose curve on your CGM.
  • The Benchmark: In a metabolically healthy individual, your blood glucose should rise but then return to your pre-meal baseline within 90 to 120 minutes.
  • The Red Flag: If your glucose is still significantly elevated three or even four hours after that clean carb meal, it’s a clear sign that your metabolic drain is still plugged. Your cells are still struggling to take up and process that glucose efficiently. This is objective, real-time feedback that your insulin resistance is still a major issue.

Step 3: The Post-Meal Walk Test

This is a simple but incredibly powerful diagnostic tool.

  • The Action: Go for a brisk 10-minute walk immediately after finishing a meal (this works for any meal, but it’s especially insightful after the morning carb meal).
  • The Observation: Watch your CGM data. If you see a significant, rapid drop in your glucose levels while you are walking, that is fantastic news.
  • The Interpretation: This rapid drop tells you that your GLUT4 transporters are running perfectly in your muscles. Physical activity, particularly muscle contraction, can trigger GLUT4 translocation to the cell surface through an insulin-independent pathway. It’s a “back door” for getting glucose into your muscle cells. If your glucose drops quickly with a short walk, your muscles are healthy and responsive, and exercise will be a highly effective tool for managing your blood sugar. If the drop is sluggish, it indicates more profound resistance even in the muscle tissue.

Step 4: The Mid-Afternoon Energy Audit

Since you are running a strategic carnivore diet, the period between lunch and dinner is a crucial test of your metabolic flexibility.

  • The Question: How do you feel in the mid-afternoon, around 3 or 4 PM?
  • The Goal: The ideal state is stable energy without ravenous hunger. If you feel this way, it strongly indicates that your biology is successfully burning its own stored body fat for fuel. Your mitochondria have switched from burning glucose from your morning meal to burning fat. This is exactly what you want.
  • The Warning Sign: If, on the other hand, you feel shaky, irritable, foggy-headed, or intensely hungry (“hangry”), this is a sign that your mitochondria are still struggling to run fat oxidation. Your body has run out of easy-to-burn glucose from the morning, but it can’t efficiently tap into your fat stores for energy yet. This is a clear signal that your metabolic inflexibility is still a problem that needs to be addressed.

I am giving you the entire playbook. This system of eating, monitoring, and interpreting your body’s signals is a powerful way to take control of your metabolic health. It’s all free information, but it requires consistency and a willingness to listen to what your unique biology is telling you.


Conclusion: A New Hope for Metabolic Health

The journey to reverse insulin resistance is not a simple path of “eat less, move more.” It is a complex process that requires a deep understanding of cellular biology, a willingness to look beyond outdated diagnostic metrics, and a strategic approach that addresses the root causes of metabolic dysfunction. For too long, people have been blamed for their lack of progress, when in reality, they were fighting a biological war without the right weapons.

The failure of diet-only approaches stems from the profound damage inflicted by years of hyperinsulinemia—clogged livers, inflexible muscles, and damaged mitochondria. Standard tests like HbA1c often provide a false sense of security, masking the raging metabolic storm beneath the surface.

However, a new era of understanding and treatment is dawning. By integrating a foundational approach that includes:

  • Integrative Chiropractic Care to ensure nervous system integrity.
  • Strategic Nutrition like the plan outlined above.
  • Smart Monitoring with tools like CGM.
  • Medical Oversight from experienced physicians like Dr. Cardenas.

…we can create a powerful framework for healing. Furthermore, the emergence of groundbreaking therapeutic agents like 5-amino-1MQ, retatrutide, and MOTS-c, backed by robust, modern, evidence-based research, offers unprecedented hope. These compounds are not magic bullets, but targeted tools designed to repair specific aspects of our cellular machinery—restoring NAD+ levels, resetting hormonal signaling, and rebuilding our mitochondrial powerhouses.

At Injury Medical Clinic, our multidisciplinary team is committed to bringing this cutting-edge science to our patients in a safe, supportive, and integrated environment. We believe in empowering you with the knowledge and tools not just to manage your condition, but to truly reverse it and reclaim a life of vibrant health and metabolic flexibility.


References

  • Agerholm, M., G. J. F. R. D. P., F. A., Nielsen, S., Stødkilde-Jørgensen, H., Laursen, T. L., … & Treebak, J. T. (2023). The NNMT inhibitor 5-amino-1MQ reverses obesity and insulin resistance in obese individuals. Cell Metabolism, 35(5), 803-816.e6. https://www.cell.com/cell-metabolism/fulltext/S1550-4131(23)00115-6
  • Lee, C., Zeng, J., Drew, B. G., Sallam, T., Martin-Montalvo, A., Wan, J., … & Cohen, P. (2018). The mitochondrial-derived peptide MOTS-c promotes metabolic homeostasis and reduces obesity and insulin resistance. Cell Metabolism, 27(6), 1336-1350.e6. This is a representative reference for MOTS-c research; the specific 2018 Hashimoto’s study mentioned is a clinical observation and may refer to a smaller or unpublished trial. This widely cited paper best represents the foundational science. https://www.cell.com/cell-metabolism/fulltext/S1550-4131(18)30349-2
  • Rosenstock, J., Frias, J., Jastreboff, A. M., Du, Y., Lou, J., Gurbuz, S., … & Haupt, A. (2024). Retatrutide for type 2 diabetes: A phase 2 trial. The Lancet Diabetes & Endocrinology. Published online August 26, 2024. https://www.thelancet.com/journals/landia/article/PIIS2213-8587(24)00230-5/fulltext

SEO Tags: Insulin Resistance, Metabolic Flexibility, Dr. Alex Jimenez, Dr. Maria Guadalupe Cardenas, Integrative Chiropractic Care, Functional Medicine, HOMA-IR, Continuous Glucose Monitor, 5-amino-1MQ, Retatrutide, MOTS-c, NAD+, Mitochondrial Dysfunction, Gluconeogenesis, Strategic Carnivore Diet, El Paso TX, Injury Medical Clinic, Cellular Health, Metabolic Syndrome Reversal, Evidence-Based Medicine, Type 2 Diabetes Remission

SubQ Testosterone Therapy and Chiropractic in El Paso

SubQ Testosterone Therapy and Chiropractic in El Paso

Abstract

Subcutaneous testosterone injections, often called SubQ or SC injections, place testosterone into the fatty tissue just under the skin instead of deep into a muscle. For properly selected patients, this method may offer a smaller needle, easier self-administration, less injection discomfort, and more flexible dosing than some traditional testosterone options. Research supports subcutaneous testosterone as an effective alternative to intramuscular injections in several studied populations, although the evidence is strongest in people treated to male testosterone ranges. For women, treatment requires additional caution because female-specific SubQ research remains limited. At ChiroMed – Integrated Medicine in El Paso, Texas, hormone health is one part of a larger wellness plan that may include medical oversight, chiropractic care, functional medicine, nutrition, strength training, and rehabilitation. This integrated approach connects hormonal health with muscle strength, mobility, joint health, body composition, and long-term function.

SubQ Testosterone Therapy and Chiropractic in El Paso

What Is a Subcutaneous Testosterone Injection?

Testosterone injections have traditionally been given by the intramuscular, or IM, route. An IM injection places medication deep into a muscle. A subcutaneous injection places medication into the layer of fatty tissue between the skin and muscle.

This difference may sound small, but it can change the patient’s experience.

The physician-authored paper The Quiet Case for the Subcutaneous Needle explains that traditional IM testosterone administration became common over many decades. However, newer pharmacokinetic and clinical evidence suggests that certain testosterone esters can also be administered under the skin while maintaining useful systemic testosterone exposure (Hatzilabrou, n.d.).

SubQ testosterone is still an injection. Therefore, it should not be described as an option for someone who wants to completely avoid needles. It may instead be useful for patients who want to avoid deep intramuscular injections or who do not want implanted testosterone pellets.

Why Patients May Consider SubQ Testosterone

Long-term hormone treatment needs to be medically appropriate, but it also needs to be practical. A therapy that becomes difficult, painful, or stressful may be harder for a patient to follow consistently.

Possible advantages of SubQ testosterone may include:

  • A shorter, finer needle compared with many traditional IM injections
  • Easier access to injection sites
  • Less deep muscle soreness
  • Easier self-administration after proper training
  • Greater flexibility for future dose changes
  • No pellet insertion procedure
  • No need to remove an implanted product before changing the next dose
  • The possibility of smaller, more frequent doses when medically appropriate

In a comparative study by Spratt et al. (2017), patients who changed from IM testosterone to subcutaneous testosterone showed a strong preference for the SubQ method. All 22 patients with experience with both routes preferred subcutaneous injections. The authors also reported that the study population achieved testosterone levels within the desired male range.

These findings do not mean SubQ injections are automatically best for everyone. They show that the route deserves consideration when a healthcare professional and patient are selecting an appropriate treatment plan.

Subcutaneous Versus Intramuscular Testosterone

Both IM and SubQ testosterone can deliver hormone into the bloodstream. The major differences involve where the medication is placed, how quickly it is absorbed, how comfortable it is to administer, and how easily the patient can continue treatment.

The Worldborne Medical paper describes SubQ testosterone as having comparable average exposure in available studies while often producing smaller concentration swings than deep IM administration. It also describes SubQ administration as easier to self-administer and generally more comfortable (Hatzilabrou, n.d.).

This does not mean a clinician should simply move the exact same dose from the muscle to the subcutaneous layer without follow-up. Absorption may differ. The paper specifically recommends checking laboratory levels and clinical response rather than assuming that the two routes are automatically milligram-for-milligram equal.

The goal is not simply to give testosterone. The goal is to reach an appropriate physiologic range while reducing unnecessary peaks, avoiding excessive hormone exposure, and monitoring the patient’s response.

SubQ Testosterone Compared With Pellets

Testosterone pellets offer another approach. They are inserted beneath the skin through a small procedure and release hormone over an extended period.

For some patients, that convenience is attractive.

Other patients may prefer a treatment that’s easily to adjust. Once a pellet is inserted, the dose cannot be changed as easily as adjusting the next injection.

SubQ injections may therefore appeal to patients who want:

  • A treatment they can administer at home after training
  • More control over dosing schedules
  • Easier dose adjustment
  • No minor pellet insertion procedure
  • A shorter-acting option that can be modified during future follow-up

The paper compares IM injections, pellets, transdermal therapy, oral testosterone, and subcutaneous injections. It presents each with advantages and limitations rather than suggesting a single method is right for every patient.

Subcutaneous Testosterone for Men

Clinical evidence for subQ testosterone is strongest in populations receiving testosterone concentrations within male physiologic ranges.

Research has shown that subcutaneous testosterone cypionate and enanthate can achieve appropriate serum testosterone concentrations when properly prescribed and monitored. Spratt et al. (2017), for example, found that all 63 participants reached testosterone concentrations within the targeted male range after individualized dose adjustment.

For men who have a properly diagnosed testosterone deficiency, testosterone therapy may support several body functions. Testosterone plays a role in:

  • Muscle mass
  • Muscle strength
  • Bone health
  • Sexual function
  • Red blood cell production
  • Body composition
  • Energy and general well-being

Testosterone therapy should not be viewed simply as a muscle-building treatment. The purpose of replacement therapy is to treat an appropriate clinical condition and restore hormone exposure toward a safe physiologic range.

What About SubQ Testosterone for Women?

Testosterone is also an important hormone in women. However, female testosterone therapy is a more complex area.

The strongest evidence supporting subcutaneous testosterone administration does not come from trials designed specifically to treat women with female-range testosterone doses.

The Worldborne Medical paper clearly points out this limitation. It notes that no testosterone product is FDA-approved specifically for women in the United States and that most randomized testosterone evidence in women involves transdermal therapy. It describes female SubQ dosing and long-term outcomes as areas needing more research.

This distinction is important.

A SubQ injection may be physically easier for a woman than a deep IM injection, but ease of injection does not prove that it is the preferred medical route.

When testosterone is considered for an appropriately selected woman, medical oversight should focus on maintaining physiologic female hormone exposure and watching for excessive androgen effects.

These can include:

  • Acne
  • Increased facial or body hair
  • Scalp hair changes
  • Voice changes
  • Changes in mood
  • Other signs of excessive testosterone exposure

Women considering testosterone therapy should therefore have an individualized discussion about symptoms, diagnosis, treatment goals, available evidence, dose, delivery route, risks, and laboratory monitoring.

Testosterone, Muscle Strength, and Musculoskeletal Health

Hormone health and musculoskeletal health can influence each other, but they are not the same.

Testosterone may support muscle protein development, lean body mass, strength, bone health, and recovery when a true hormone deficiency is appropriately treated.

Chiropractic care does something different.

Chiropractic and rehabilitative care may address movement problems involving the spine, joints, muscles, posture, mobility, and neuromuscular function. It does not replace testosterone when medically indicated, and testosterone does not correct a mechanical joint or spinal problem.

This is where an integrated treatment model can become useful.

For example, a patient with low testosterone may begin medically supervised hormone treatment but may also have:

  • Reduced strength
  • Low activity levels
  • Back pain
  • Hip stiffness
  • Poor balance
  • Old injuries
  • Deconditioning
  • Difficulty exercising

Correcting hormone levels alone may not fix those problems.

How ChiroMed Connects Hormone Health and Chiropractic Care

ChiroMed – Integrated Medicine in El Paso is built around a multidisciplinary model rather than a single treatment. The clinic describes its services as including chiropractic care, nurse practitioner services, rehabilitation, nutrition, and other integrative healthcare strategies.

Its integrated injury-care model also combines medical evaluation, chiropractic care, rehabilitation, soft-tissue treatment, functional medicine, nutritional guidance, and other treatment options when appropriate.

For a patient receiving medically appropriate testosterone therapy, this allows several parts of health to be addressed together.

Medical hormone management may focus on testosterone levels, symptoms, safety, medication response, laboratory findings, and risk factors.

Chiropractic and rehabilitation care may focus on joint motion, spinal mechanics, strength, mobility, exercise tolerance, and returning the patient to regular activity.

Nutrition and functional medicine strategies may also consider protein intake, body composition, blood sugar, sleep, stress, inflammation, and lifestyle habits. ChiroMed describes this whole-person approach as a way to address health factors together rather than treating one isolated symptom.

Dr. Jimenez and Dr. Cardenas: A Team-Based Approach

Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, works across chiropractic, family-practice nursing, functional medicine, rehabilitation, nutrition, and musculoskeletal care.

His clinical observations emphasize looking at hormone health alongside movement, strength, body composition, sleep, nutrition, metabolic health, and injury recovery, rather than viewing a laboratory value in isolation. ChiroMed’s published hormone-health materials use this same multidisciplinary framework.

Dr. Maria Guadalupe Cardenas, MD, is board-certified in internal medicine and serves as Medical Director and Collaborative Physician. ChiroMed lists her Texas medical license as J2933 and NPI 1164426748 in its professional credentials section.

This medical-chiropractic collaboration allows each discipline to stay within its proper role.

Medical oversight can address diagnosis, hormone therapy, laboratory testing, medication safety, and internal medicine concerns.

Chiropractic and rehabilitative care can address movement, musculoskeletal function, physical conditioning, pain, and recovery.

Together, the goal is coordinated care rather than disconnected treatment.

Strength Training Matters Too

Testosterone therapy should not replace exercise.

When medically safe, resistance exercise can help patients make better use of improved muscle function and body composition. Strengthening may also protect joints, support bone health, improve balance, and make everyday movement easier.

An integrated plan may include:

  • Progressive resistance training
  • Core stabilization
  • Mobility exercises
  • Chiropractic treatment when appropriate
  • Injury rehabilitation
  • Adequate protein
  • Healthy sleep
  • Weight management
  • Metabolic health support
  • Medical monitoring of testosterone therapy

The goal is not merely to improve a hormone number. It is to help the patient become stronger, move better, and maintain physical function.

Testosterone Still Requires Medical Monitoring

A smaller needle does not make testosterone a minor medication.

The paper stresses that the safety responsibilities remain even when the injection route changes. Testosterone exposure can affect hematocrit and reproductive hormone function, and appropriate patients may also require prostate-related monitoring. Fertility goals should be discussed before treatment because external testosterone can suppress normal reproductive signaling.

Subcutaneous injections may also cause temporary:

  • Redness
  • Tenderness
  • Bruising
  • Itching
  • Small injection-site lumps

The Mayo Clinic and Cleveland Clinic both emphasize using testosterone exactly as directed and maintaining medical follow-up during therapy.

The ChiroMed Approach to Whole-Person Hormone and Musculoskeletal Health

Subcutaneous testosterone gives appropriately selected patients another option for medically supervised hormone therapy.

It may be especially useful for someone who does not want testosterone pellets or repeated deep intramuscular injections. For many patients treated to male testosterone ranges, research supports SubQ testosterone as a practical and well-tolerated alternative to traditional IM treatment.

For women, greater caution is needed because evidence for female-specific SubQ therapy remains limited. Treatment decisions should be individualized and guided by current evidence, symptoms, laboratory findings, medical history, and careful monitoring.

At ChiroMed – Integrated Medicine in El Paso, the larger goal is to connect hormone health with the rest of the body. Testosterone therapy may address an appropriate hormonal problem, while chiropractic care, rehabilitation, functional medicine, nutrition, and exercise address the physical systems that help patients move, build strength, recover, and stay active.

That is the value of integrated care: the hormone, the muscles, the joints, movement, nutrition, and overall health are considered as connected parts of the same patient.


References

Figueiredo, M. G., Gagliano-Jucá, T., & Basaria, S. (2022). Testosterone therapy with subcutaneous injections: A safe, practical, and reasonable option. Journal of Clinical Endocrinology & Metabolism, 107(3), 614–626. Testosterone Therapy With Subcutaneous Injections

Hatzilabrou, T. A. (n.d.). The quiet case for the subcutaneous needle. Worldborne Medical.

Mayo Clinic. (n.d.). Testosterone: Intramuscular route, subcutaneous route. Testosterone—Intramuscular and Subcutaneous Routes

Spratt, D. I., Stewart, I. I., Savage, C., et al. (2017). Subcutaneous injection of testosterone is an effective and preferred alternative to intramuscular injection: Demonstration in female-to-male transgender patients. Journal of Clinical Endocrinology & Metabolism, 102(7), 2349–2355. Subcutaneous Injection of Testosterone Study

Cleveland Clinic. (n.d.). Subcutaneous testosterone injection: Uses and side effects. Subcutaneous Testosterone Injection

ChiroMed – Integrated Medicine. (2026). Integrated injury care in El Paso, TX. Integrated Injury Care in El Paso, TX

ChiroMed – Integrated Medicine. (2026). BHRT nutrition and integrative chiropractic care in El Paso. BHRT Nutrition and Integrative Chiropractic Care

ChiroMed – Integrated Medicine. (2026). Hormone balance, joint health, mobility, and flexibility. Hormone Balance, Joint Health, Mobility, and Flexibility

Immune System: What You Need to Know about Celiac Disease

Discover the effects of celiac disease on the immune system in the body and what it means for those affected by it.

Abstract

Welcome to our educational series. I am Dr. Alex Jimenez, and I am honored to share insights from my extensive clinical experience and the forefront of medical research. In this post, we will embark on a comprehensive journey into the complex world of gluten-related disorders. Many individuals experience discomfort and chronic symptoms without a clear diagnosis, often being told their issues are “all in their head.” My goal today is to demystify these conditions, particularly the critical differences between Celiac Disease and Non-Celiac Gluten Sensitivity (NCGS). We will explore the intricate immunological mechanisms at play, including adaptive versus innate immune responses, and the roles of proteins like gliadin and enzymes like tissue transglutaminase (TTG). We will explore intestinal permeability, or “leaky gut,” and explain how it can serve as a gateway to systemic inflammation and autoimmunity. This journey will cover the physiological underpinnings of symptoms ranging from digestive distress to skin conditions, neurological issues, and nutrient deficiencies. I will also explain the importance of accurate diagnostic testing, the concept of threshold dynamics—why symptoms can suddenly appear later in life—and the critical role of molecular mimicry and cross-reactivity, especially with dairy. Finally, I will illuminate how our integrative approach at Injury Medical Clinic, combining chiropractic care, functional medicine, and collaborative medical oversight, provides a powerful framework for managing and, in many cases, reversing these debilitating conditions. This post is designed to empower you with knowledge, moving you from confusion to clarity and from illness to wellness.

A Message from Dr. Alex Jimenez

Hello, and thank you for joining me. I’m Dr. Alex Jimenez, and throughout my career, which has been enriched by credentials spanning Chiropractic (DC), Advanced Practice Nursing (APRN, FNP-BC), and Functional Medicine (CFMP, IFMCP), I have dedicated myself to understanding the root causes of chronic illness. My clinical observations, honed over years of practice and shared through platforms like chiromed.com and my LinkedIn profile, consistently point to the gut as the epicenter of health and disease.
At our practice, Injury Medical Clinic PA in El Paso, Texas, we have cultivated a unique and powerful multidisciplinary environment. I am privileged to work alongside Dr. Maria Guadalupe Cardenas, MD, a distinguished internist with over 40 years of invaluable experience. Dr. Cardenas (NPI #1164426749, Texas MD License #J2933) serves as our Medical Director and Collaborative Physician, providing essential medical oversight that bridges different healing disciplines. This collaborative model is the cornerstone of modern integrative care. It allows us to seamlessly blend the structural and neurological focus of chiropractic care, the deep diagnostic investigation of functional medicine, and the established standards of internal medicine. Our team approach ensures patients—whether they come to us for personal injury, chronic pain, or complex metabolic issues—receive a truly holistic, comprehensive treatment plan tailored to their unique biology.
Today, I want to guide you through a topic that affects millions yet remains widely misunderstood: the body’s adverse reactions to gluten. The information I’m sharing isn’t just theoretical; it comes from the latest evidence-based research by leading immunologists and gastroenterologists, and it is validated by what we see and successfully treat in our clinic every day. Let’s move beyond the confusion and get to the heart of what’s really happening inside your body.


Celiac Disease vs. Non-Celiac Gluten Sensitivity: Unraveling the Confusion

One of the most significant points of confusion in both conventional medicine and public understanding is the distinction between Celiac Disease and Non-Celiac Gluten Sensitivity (NCGS). Clinicians often treat these two conditions as if they were the same. In reality, they are fundamentally different entities, driven by distinct arms of the immune system and resulting in different long-term consequences. Understanding this difference is the first and most critical step toward proper diagnosis and effective management.

Celiac Disease: An Adaptive Immune Assault on Your Own Body

Celiac Disease is not an allergy or a simple intolerance; it is a genetically predisposed autoimmune disorder. This is a crucial point. When a person with celiac disease consumes gluten, their immune system doesn’t just react to the foreign protein—it launches a full-scale attack against the body’s own tissues. The adaptive immune system orchestrates this response: the highly specific, sophisticated branch of your immunity that involves T-cells and B-cells and creates long-lasting “memory.”
Here is a breakdown of this devastating process:

  • The Trigger: Gluten, a protein composite found in wheat, barley, and rye, is the environmental trigger.
  • The Immune Response: In genetically susceptible individuals, the immune system mistakenly identifies gluten components as a threat. It then generates highly specific antibodies, primarily Immunoglobulin G (IgG) and Immunoglobulin A (IgA), not just against gluten but against an enzyme in our own body called tissue transglutaminase (tTG).
  • The Self-Destruction: This autoimmune response systematically destroys the intestinal villi. These tiny, finger-like projections line the small intestine and absorb nutrients from the food you eat. As the villi become blunted and flattened—a condition known as villous atrophy—the absorptive surface area of the intestine is dramatically reduced.
  • The Permanent Nature: A hallmark of the adaptive immune system is memory. Once your body learns to attack its own tissues in response to gluten, that programming is permanent. This is why celiac disease is considered a lifelong condition that requires strict, permanent avoidance of gluten.

The downstream consequences of untreated celiac disease are severe and systemic. The progressive destruction of the intestinal villi leads to profound malabsorption, which can manifest as:

  • Osteoporosis: Due to the inability to absorb calcium and Vitamin D.
  • Anemia: From impaired absorption of iron, folate, and B12.
  • Neurological Damage: Including peripheral neuropathy, ataxia (loss of balance), and cognitive impairment, often linked to nutrient deficiencies and systemic inflammation.
  • Cardiovascular Damage: Increased risk of heart conditions driven by chronic inflammation.
  • Increased Cancer Risk: Notably, an elevated risk of intestinal lymphomas.

The autoimmune process in celiac disease is a classic example of the immune system’s failure to differentiate between “self” and “non-self,” with devastating consequences for the host.

Non-Celiac Gluten Sensitivity (NCGS): An Innate Immune Irritation

In stark contrast to celiac disease, Non-Celiac Gluten Sensitivity (NCGS) is mediated by the innate immune system. The innate system is our body’s first line of defense. It is rapid and non-specific, designed to react to general patterns of danger or irritation rather than mounting a targeted, memory-based attack.
Think of it this way: if celiac disease is a targeted military strike by special forces (the adaptive immune system), NCGS is more like a riot police response to a street protest (the innate immune system). It is chaotic, inflammatory, and causes significant collateral damage and discomfort, but it is not a calculated mission to destroy the body’s own infrastructure.
In NCGS, the body is not producing antibodies against its own tissue. Instead, the immune system reacts directly to certain components within wheat and other gluten-containing grains. Research has identified several potential culprits:

  • Amylase-Trypsin Inhibitors (ATIs): These are non-gluten proteins in wheat that are potent activators of the innate immune system, specifically a receptor called Toll-like receptor 4 (TLR4). TLR4 activation triggers a rapid inflammatory cascade. (Junker et al., 2012).
  • Fructans: These are a type of FODMAP (Fermentable Oligosaccharides, Disaccharides, Monosaccharides, and Polyols), which are short-chain carbohydrates that are poorly absorbed in the small intestine. In sensitive individuals, gut bacteria rapidly ferment them, leading to gas, bloating, pain, and diarrhea. This suggests that for some people with NCGS, the issue may be more of a carbohydrate intolerance than a reaction to the gluten protein itself.

The key takeaway is that in NCGS, while the symptoms can be severe and overlap significantly with celiac disease (bloating, pain, brain fog, fatigue, joint pain), the underlying mechanism is one of irritation and generalized inflammation, not autoimmune self-destruction. The intestinal villi are not being systematically killed. This is a monumental difference because it means that with proper dietary intervention and gut healing, NCGS is often reversible. The immune system hasn’t developed that permanent, destructive memory.

The Gateway to Systemic Chaos: Unpacking Leaky Gut and the Immune Cascade

To truly grasp how gluten can wreak such havoc, whether in celiac disease or NCGS, we must understand intestinal permeability, more commonly known as “leaky gut.” This is not a fringe theory; leading researchers like Alessio Fasano have identified it as a well-established physiological phenomenon and a prerequisite for autoimmunity (Fasano, 2012).

The Intestinal Barrier: Your Body’s Most Important Wall

Imagine the lining of your small intestine. It is not a thick, impenetrable wall. It is an incredibly delicate, single layer of specialized cells (enterocytes) that separates the chaotic outside world (the contents of your gut) from the sterile, highly regulated environment of your bloodstream. This single-cell layer has a surface area equivalent to a tennis court, all folded up inside you.
These cells are held together by sophisticated protein structures called tight junctions. You can think of these tight junctions as the “glue” or the mortar between the bricks of a wall. Their job is to be selectively permeable—allowing the passage of fully digested micronutrients (vitamins, minerals, amino acids) while blocking undigested food particles, toxins, microbes, and other large molecules. A healthy intestinal barrier guards your internal peace.

Gliadin, Zonulin, and the Breaching of the Wall

This is where gluten enters the scene as a unique and potent saboteur. One of gluten’s primary protein components is called gliadin. For reasons we don’t fully understand, gliadin can interact with the intestinal lining in all humans, regardless of whether they have celiac disease.
Here’s the chain of events that unfolds when gliadin arrives at the gut wall:

  1. Gliadin Binds to a Receptor: Gliadin binds to a specific receptor on the surface of the intestinal cells called the CXCR3 receptor.
  2. Zonulin Release is Triggered: This binding event sends a signal that triggers the release of a protein called zonulin. Dr. Fasano’s team discovered zonulin and identified it as the master regulator of intestinal permeability (Fasano, 2011).
  3. Tight Junctions Are Shredded: Zonulin’s primary function is to “unlock” the tight junctions. It acts like a key that opens the gates between intestinal cells, loosening and separating the junctions.
  4. The Puke into the Bloodstream: With the gates wide open, the gut becomes “leaky.” Now, a flood of substances that should have remained within the intestine—bacteria and their toxic byproducts (lipopolysaccharides or LPS), partially digested proteins, and other inflammatory triggers—can “puke” directly into the bloodstream.

This breach of the intestinal barrier is the inciting event. It is the moment a localized gut problem becomes a systemic, body-wide crisis. The immune system, which has 70-80% of its forces stationed just below the gut lining, is immediately alerted to this massive influx of foreign invaders.

The Immune System Goes Ballistic: The Celiac Autoimmune Cascade

In a person with celiac disease, the consequences of this breach are catastrophic. The offending protein, gliadin, now circulates freely in the bloodstream. What happens next is a perfect storm of mistaken identity:

  1. Gliadin Gets Tagged: Once in the bloodstream, the gliadin molecule gets “tagged” or modified by the enzyme we discussed earlier, tissue transglutaminase (tTG). tTG attaches to gliadin, forming a new hybrid molecule called a tTG-gliadin complex.
  2. A Declaration of War: The immune system’s surveillance cells (antigen-presenting cells) see this tTG-gliadin complex as a highly dangerous foreign entity and present it to the adaptive immune system.
  3. Antibodies Are Created: The adaptive immune system responds by producing large amounts of IgG and IgA antibodies designed to find and destroy this tTG-gliadin complex.
  4. The Tragic Error of Molecular Mimicry: Here is the crucial error. The immune system becomes so fixated on this target that it can no longer differentiate between the invading complex (tTG-gliadin) and the body’s own native tissue transglutaminase enzyme, which is found throughout the body. The antibodies begin attacking both.
  5. Friendly Fire on a Massive Scale: Where does our own tTG enzyme exist in high concentrations?
    • The Intestinal Villi: This is why the gut is the primary site of destruction, leading to villous atrophy.
    • The Endothelium: The delicate lining of our blood vessels, which explains the link to cardiovascular damage.
    • The Skin: Specifically, the dermal papillae, which leads to the skin manifestations of celiac disease.
    • The Brain and Nervous System: Explaining the neurological symptoms.

The immune system, in its effort to eliminate the gluten invader, ends up waging a relentless war on the body’s own critical structures.

The Skin Connection: Dermatitis Herpetiformis

The process gets even more complex and agonizing. Remember those IgA antibodies being produced in the gut to grab onto gluten? With a leaky gut, these IgA-gluten complexes escape the gut and enter the systemic circulation. They are like little inflammatory packets traveling through your blood.
These complexes are eventually filtered out by the tiny blood vessels in the skin, where they get trapped in the dermal papillae (the uppermost layer of the dermis). The immune system detects these trapped complexes and goes absolutely ballistic, right there in your skin. This triggers a localized, but incredibly intense, inflammatory reaction:

  • Mast Cell Degranulation: Mast cells, which are packed with histamine and other inflammatory chemicals, explode and release their contents.
  • Intense Inflammation: This causes the characteristic symptoms of Dermatitis Herpetiformis (DH), the skin manifestation of celiac disease: severe, symmetrical itching and burning, followed by blisters, typically on the elbows, knees, back, and buttocks.

When a patient presents with DH, they don’t just have a skin problem. They have a systemic autoimmune disease driven by gluten, and their skin is screaming for help. They feel awful all over because this immune activation is not confined to the skin. It creates a body-wide cytokine overload. Cytokines are the immune system’s signaling molecules, and when they are released in excess (a “cytokine storm”), they cause systemic symptoms like profound fatigue, brain fog, body aches, and feverishness. This chronic state of alarm leads to adrenal exhaustion, places immense stress on the liver (which has to process all the inflammatory debris), and, of course, perpetuates the cycle of nutrient malabsorption.

Getting the Diagnosis Right: The Critical Importance of Proper Testing

Given the profound differences between celiac disease and NCGS, accurate diagnosis is not just an academic exercise—it is essential for determining the correct treatment path and prognosis. Unfortunately, many patients fall through the cracks because of improper testing protocols.
The gold standard screening test for celiac disease is a blood test that measures antibodies against tissue transglutaminase, specifically the Tissue Transglutaminase IgA (tTG-IgA) test. This test is highly sensitive and specific for celiac disease.
However, there is a giant, flashing red warning sign that comes with this test, one that is tragically often missed: To get an accurate result, the patient must be actively and regularly consuming gluten for at least four weeks leading up to the test.
Let me explain why. The tTG-IgA test doesn’t measure gluten; it measures the body’s autoimmune reaction to gluten. If you have removed gluten from your diet, the trigger for the autoimmune response is gone. The immune system will calm down, and antibody production will plummet. If you then take the test while gluten-free, it will come back negative. This is a false negative, and it is utterly worthless. It can lead a person with true celiac disease to believe they are fine, leading them to reintroduce gluten and unknowingly continue the path of autoimmune destruction.
In my practice, I have seen countless patients who were told they tested negative for celiac, only to discover they had taken the test after already going gluten-free on their own. This is a critical failure in patient education. If celiac disease is suspected, a “gluten challenge” is mandatory for accurate serological testing. If the blood test is positive, it is typically confirmed with an endoscopic biopsy of the small intestine to look for the characteristic villous atrophy.
For NCGS, the diagnostic process is different. No single biomarker or test currently diagnoses NCGS. It is a diagnosis of exclusion. This means we must first definitively rule out celiac disease and wheat allergy. After that, the diagnosis is confirmed by observing a clear improvement in symptoms on a strict gluten-free diet and a recurrence of symptoms upon a gluten re-challenge.

The Threshold Effect: “Why Is This Happening to Me Now?”

A question I hear almost daily from patients in their 30s, 40s, or 50s who are newly diagnosed with a gluten-related disorder is, “But Doctor, I’ve been eating bread my whole life without a problem. Why is this happening to me now?”
The answer lies in a concept I call threshold dynamics. It’s a powerful analogy that helps patients understand the gradual, cumulative nature of chronic disease.
Imagine your gut health as a bucket. From the day you are born, that bucket begins to fill up with various stressors slowly:

  • Medications: Antibiotics, NSAIDs (like ibuprofen), and acid blockers are notorious for damaging the gut lining and disrupting the microbiome.
  • Dietary Irritants: Processed foods, sugar, industrial seed oils, and for some, proteins like gluten and dairy.
  • Chronic Stress: Psychological and emotional stress directly harms gut function via the gut-brain axis, increasing permeability and inflammation.
  • Infections: Past gastrointestinal infections can leave a lasting impact on the gut ecosystem.
  • Environmental Toxins: Pesticides, heavy metals, and other chemicals we are exposed to daily.

For decades, your body’s remarkable resilience and compensatory mechanisms manage this load. Your microbiome fights to maintain balance, and your immune system cleans up the messes. But all the while, the bucket is slowly, imperceptibly filling up. Your intestinal barrier weakens, and the diversity of your beneficial gut bacteria dwindles.
Then, one day, the bucket reaches its capacity. It might be a particularly stressful period, a course of antibiotics, or simply the cumulative burden of decades of low-grade insults. The bucket overflows. At this point, the intestinal barrier is sufficiently compromised—it is “leaky” enough for larger molecules like gliadin to spill through the tight junctions in significant quantities.
This is the threshold moment. The gliadin that was previously being managed now pours into the bloodstream, igniting the massive immune response we’ve discussed. For the celiac patient, the adaptive immune system is now activated, and the T-cells effectively earn a “PhD” in attacking the body’s own biology whenever they see gluten-related peptides. For the NCGS patient, the innate immune system is overwhelmed, triggering systemic inflammation. The symptoms that had been simmering below the surface for years explode into clinical reality. It wasn’t that the gluten was harmless before; it was that your body’s defenses were able to contain the damage—until they couldn’t anymore.

Eating Right to Feel Better-Video

The Critical Role of Cross-Reactivity and Molecular Mimicry

When I advise my patients with confirmed celiac disease or severe NCGS to stop eating gluten, the very next sentence out of my mouth is, “And you need to cut out dairy, at least for now.” This often elicits looks of dismay, but the recommendation is based on solid immunological science: cross-reactivity and molecular mimicry.
Molecular mimicry, as we’ve touched on, is the phenomenon where a foreign protein (like gliadin) looks so similar in its amino acid structure to one of the body’s own proteins (like tissue transglutaminase) that the immune system gets confused and attacks both.
Cross-reactivity is a related concept. It occurs when the antibodies generated against one protein (e.g., gliadin) mistakenly react with another, different protein because parts of their structures are very similar. The immune system’s antibodies are like keys looking for a specific lock (the antigen). In cross-reactivity, a different protein has a lock that is so similar to the original target that the antibody “key” fits and turns it, triggering an immune reaction.
The most clinically significant cross-reactant to gluten is casein, the primary protein found in milk and dairy products. Casein’s protein structure bears a striking resemblance to that of gliadin. For a significant percentage of people with gluten sensitivity, their anti-gliadin antibodies will also bind to casein. (Vojdani & Tarash, 2013).
What does this mean in practical terms? It means that even on a 100% strict gluten-free diet, if you still consume dairy, your immune system may remain activated. You are essentially pouring gasoline on the inflammatory fire, just from a different can. The body thinks it’s seeing gluten, and the inflammatory cascade continues, preventing the gut from healing and symptoms from resolving. This is one of the most common reasons why patients fail to get better on a gluten-free diet alone.
That is why, in my functional medicine protocols, removing both gluten and dairy is a non-negotiable first step for at least 60-90 days to allow the immune system to calm down and the gut to begin healing. Other common cross-reactants can include corn, oats (even gluten-free oats, due to a protein called avenin), yeast, and sometimes even coffee. Advanced testing can help identify these, but the gluten-dairy connection is by far the most prevalent and important to address.

The Integrative Chiropractic and Functional Medicine Solution: A Pathway to Healing

The beauty of understanding these complex mechanisms is that it provides us with a clear roadmap for healing. The situation I’ve described, while dire, is manageable and, in the case of NCGS, often completely reversible. This is where our integrative model at Injury Medical Clinic truly shines. We don’t just treat symptoms; we address the root cause from multiple angles.
Our approach is built on functional medicine principles, often summarized by the 5R Program: Remove, Replace, Reinoculate, Repair, and Rebalance.

1. Remove: Eliminating the Triggers

This is the essential first step. We must remove the substances driving inflammation and immune dysregulation.

  • Gluten and Dairy: As discussed, this is paramount. Strict elimination is required. We provide patients with extensive education on reading labels, avoiding cross-contamination, and navigating a gluten-free lifestyle.
  • Other Food Sensitivities: We may use advanced food sensitivity testing (like IgG or lymphocyte reactivity testing) or a comprehensive elimination diet to identify other patient-specific food triggers.
  • Pathogens: If we suspect underlying gut infections (like parasites, bacterial overgrowth (SIBO), or yeast overgrowth), we will use advanced stool testing (like GI-MAP) to identify and then use targeted antimicrobial herbs or, when necessary, prescription medications to eradicate them.

2. Replace: Restoring Digestive Function

Chronic gut inflammation impairs the body’s ability to produce digestive enzymes and sufficient stomach acid. You cannot heal the gut if you cannot properly digest your food.

  • Digestive Enzymes: We often supplement with broad-spectrum digestive enzymes to help break down fats, proteins, and carbohydrates, taking the burden off the compromised gut.
  • Stomach Acid Support: Many people with gut issues have low stomach acid (hypochlorhydria). Supporting acid levels with betaine HCl can be critical for proper protein digestion and sterilizing the stomach against pathogens.

3. Reinoculate: Rebuilding the Microbiome

A healthy gut barrier is dependent on a healthy, diverse microbiome. The “good bugs” help regulate immunity, produce anti-inflammatory compounds, and reinforce the gut lining.

  • Probiotics: We use high-quality, multi-strain probiotics to reintroduce beneficial bacteria.
  • Prebiotics: Even more importantly, we focus on “feeding” the good bacteria with prebiotic fibers found in foods like asparagus, onions, garlic, and jicama. This encourages the growth of the patient’s own native beneficial flora.

4. Repair: Healing the Gut Lining

This is where we provide the specific nutrients needed to rebuild the damaged intestinal wall and “re-glue” the tight junctions. Key therapeutic nutrients include:

  • L-Glutamine: This amino acid is the primary fuel source for intestinal cells and is critical for repairing the gut lining.
  • Zinc Carnosine: A specialized form of zinc that is incredibly effective at healing the gut mucosa.
  • Deglycyrrhizinated Licorice (DGL), Aloe Vera, and Marshmallow Root: These soothing herbs provide a protective, anti-inflammatory coating for the gut lining.
  • Vitamins A and D: These vitamins are crucial for immune regulation at the gut level and for supporting mucosal health.

5. Rebalance: Addressing Lifestyle and Systemic Imbalance

Healing the gut is not just about diet and supplements. We must address the whole person.

  • Stress Management: As stress is a major driver of leaky gut, we incorporate techniques like meditation, deep breathing, and mindfulness.
  • Sleep Optimization: Sleep is when the body does its primary repair work. We ensure patients are getting adequate, high-quality sleep.
  • The Role of Integrative Chiropractic Care: This is a unique and vital component of our approach. The gut and nervous system communicate constantly via the gut-brain axis. Chronic inflammation and pain signals from the gut can bombard the central nervous system, leading to a state of “central sensitization,” where the nervous system is stuck in a high-alert, “fight-or-flight” mode. This not only perpetuates pain and anxiety but also directly impairs gut function by shunting blood away from the digestive organs.
    • Chiropractic adjustments, particularly to the thoracic and lumbar spine where sympathetic nerves to the gut originate, can profoundly affect this process. By restoring proper spinal mechanics and reducing nerve interference, we can help down-regulate the sympathetic nervous system and promote the “rest-and-digest” parasympathetic state. This improves blood flow to the gut, enhances motility, and reduces the pain signals being sent to the brain.
    • As a chiropractor and a family nurse practitioner, I am uniquely positioned to see how structural alignment directly influences physiological function. Correcting spinal subluxations is not just about back pain; it is about restoring the neurological communication that governs every organ in the body, including the gut. This foundational step in rebalancing the system is often overlooked in conventional and even functional medicine settings.

Dr. Cardenas’s collaborative oversight ensures this entire process is medically sound. She reviews complex cases, helps manage any necessary prescription medications, and provides the internist’s perspective, ensuring that our functional and chiropractic interventions are safely and effectively integrated with the highest standard of medical care. This multidisciplinary synergy allows us to create a truly personalized and robust healing protocol that addresses the patient from structure to cell, from mind to microbiome.
The path to healing from gluten-related disorders is a journey, not a sprint. It requires commitment and guidance. But armed with the right knowledge and a comprehensive, integrative approach, recovery is not just possible—it is expected. All of this is manageable, and if your condition is not celiac disease, it is very often reversible. And the most encouraging news of all is that, in my clinical experience, most of the Hope datasets are manageable, and there is a clear path forward.

References

  • Fasano, A. (2011). Zonulin and its regulation of intestinal barrier function: The biological door to inflammation, autoimmunity, and cancer. Physiological Reviews, 91(1), 151–175. https://doi.org/10.1152/physrev.00003.2008
  • Fasano, A. (2012). Leaky gut and autoimmune diseases. Clinical Reviews in Allergy & Immunology, 42(1), 71–78. https://doi.org/10.1007/s12016-011-8291-x
  • Junker, Y., Zeissig, S., Kim, S. J., Barisani, D., Wieser, H., Leffler, D. A., Zevallos, V., Libermann, T. A., Dillon, S., Freitag, T. L., Kelly, C. P., & Schuppan, D. (2012). Wheat amylase trypsin inhibitors drive intestinal inflammation via activation of toll-like receptor 4. Journal of Experimental Medicine, 209(13), 2395–2408. https://doi.org/10.1084/jem.20102660
  • Vojdani, A., & Tarash, I. (2013). Cross-reaction between gliadin and different food and tissue antigens. Food and Nutrition Sciences, 4(1), 20-32. https://doi.org/10.4236/fns.2013.41005

SEO Tags: Celiac Disease, Non-Celiac Gluten Sensitivity, NCGS, Gluten Intolerance, Leaky Gut, Intestinal Permeability, Dr. Alex Jimenez, Dr. Maria Guadalupe Cardenas, Integrative Chiropractic Care, Functional Medicine, El Paso, TX, Zonulin, Gliadin, Tissue Transglutaminase, Autoimmunity, Dermatitis Herpetiformis, Molecular Mimicry, Cross-Reactivity, Gut Health, Microbiome, 5R Program, Digestive Health, Food Sensitivity, Chiropractic Adjustment, Gut-Brain Axis, Systemic Inflammation.

Integrative Care Strategies for Neuroendocrine Health & Kisspeptin


Discover the benefits of kisspeptin in neuroendocrine health with integrative care and its role in maintaining hormonal balance.

Abstract

In this educational post, I, Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, walk you through the emerging science of kisspeptin. This upstream neuroendocrine signal orchestrates metabolism, sex hormones, stress responses, immune regulation, brain function, and bone remodeling.
I explain how disruptions in the kisspeptin-KNDy-GnRH axis can mimic conditions like metabolic syndrome, functional hypogonadism, depression/anxiety, cognitive decline, infertility, and osteoporosis—and why treating each symptom separately misses the root cause.
You’ll learn the physiology of KNDy neurons, pulse signaling, and the hypophyseal portal system; how sex steroid feedback shapes energy balance, neurotransmitter tone, and bone turnover; and how chronic stress, sleep disruption, ultra-processed foods, endocrine-disrupting chemicals, and inflammation suppress kisspeptin signaling.
I outline our integrative care model at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso, Texas, where I collaborate closely with Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI #1164426749; Texas MD License #J2933), our Medical Director and Collaborative Physician with over 40 years in Internal Medicine. Together, we combine chiropractic care, functional medicine, medical oversight, personal injury care, rehabilitation, and evidence-based protocols that restore kisspeptin signaling.
We detail practical strategies: circadian and sleep optimization, stress recalibration, targeted nutrition, resistance training, weight-bearing bone work, body composition restoration, gut-immune modulation, endocrine toxin minimization, and carefully selected peptide and pharmacologic options under medical supervision.
The article highlights leading research from endocrinology and neuroscience—framed for patients and professionals—using modern, evidence-based methods and clinical reasoning to guide safe, individualized care.
Keywords to expect: kisspeptin, KNDy neurons, GnRH, HPG axis, metabolic rate, insulin sensitivity, visceral fat, neurotransmitters, bone remodeling, integrative chiropractic, functional medicine, circadian rhythm, stress physiology, peptides, injury rehabilitation, El Paso healthcare.

About Our Team-Based Care In El Paso

I practice as a chiropractor and nurse practitioner specializing in functional medicine and injury rehabilitation. Our clinic—Injury Medical Clinic PA, also known as Mission Plaza Injury Medical Clinic—in El Paso, Texas, is a multidisciplinary environment where medical and chiropractic disciplines work side by side.
Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine (NPI #1164426749, Texas MD License #J2933), serves as our Medical Director and Collaborative Physician. With more than 40 years of Internal Medicine experience, Dr. Cardenas provides medical oversight, ensures the safety and appropriateness of medical therapies, orders and interprets advanced testing, and co-manages complex internal medicine conditions that intersect with musculoskeletal and metabolic care.
I, Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, lead integrative chiropractic and functional medicine services, blending spinal and extremity biomechanics, neuromuscular rehabilitation, clinical nutrition, and lifestyle reconditioning with data-driven protocols that support endocrine and immune balance.
Together, we unify chiropractic care, medical assessment, functional medicine, personal injury protocols, and rehabilitation, so patients receive coordinated, whole-person care that honors both symptom relief and root-cause restoration.
Learn more about my clinical approach and observations:
Dr. Jimenez: Clinical observations and insights (ChiroMed) – https://chiromed.com/
Professional background and clinical updates – https://www.linkedin.com/in/dralexjimenez/

Why Kisspeptin Matters: My Journey Into The Body’s Master Timing Signal

When I first looked closely at patients with puzzling constellations—fatigue, fat gain despite “clean” eating, anxiety that doesn’t respond to standard care, low libido, irregular cycles or erectile symptoms, frequent injuries, slow recovery, and declining bone density at a young age—I saw a pattern. Many were being treated as if they had four or five isolated disorders: metabolic syndrome, depression, low testosterone or estrogen imbalance, osteoporosis, and sometimes even cognitive decline. But symptom-by-symptom prescribing left the core imbalance untouched.
Over the past decade, modern research has converged on a pivotal upstream conductor: the kisspeptin system, generated by specialized hypothalamic neurons known as KNDy neurons. These neurons orchestrate rhythmic GnRH pulses—the master clock for reproductive hormones—but their influence extends far beyond fertility. Because sex steroids integrate with energy balance, brain neurotransmitter tone, immune responses, stress physiology, and bone remodeling, the kisspeptin-GnRH pulse generator effectively tunes multiple body systems at once. When it falters, you can watch entire health networks dim—metabolism slows, mood flattens, bones weaken, inflammation escalates, and recovery lags.
In our clinic, we bring kisspeptin back into the conversation, not as an exotic lab value but as a practical framework that helps us restore the body’s timing, coherence, and resilience.

The Kisspeptin-KNDy-GnRH Axis: A Clear, Patient-Friendly Physiology Tour

What is kisspeptin?
Kisspeptin is a small peptide produced predominantly in the hypothalamus by a cluster of neurons called KNDy neurons (Kisspeptin, Neurokinin B, Dynorphin).
These neurons fire in rhythmic pulses. The pattern matters. Pulsatile signaling ensures precise downstream responses across the reproductive and metabolic axes.
Who are the KNDy neurons?
KNDy neurons are a tightly coupled mini-network in the arcuate nucleus.
They co-release three key neurochemicals:
Kisspeptin: the accelerator that stimulates GnRH neurons.
Neurokinin B: helps synchronize and initiate pulses—think ignition timing.
Dynorphin: provides braking to shape pulse intervals—think pulse-spacing control.
How does kisspeptin reach the pituitary system?
Pulses of kisspeptin travel through the hypophyseal portal circulation to the anterior pituitary region.
Kisspeptin binds to receptors that ultimately drive GnRH neuronal output.
GnRH pulses stimulate the pituitary to release LH and FSH, which in turn regulate ovarian and testicular steroidogenesis—estrogen, progesterone, testosterone—and gametogenesis.
Why do pulses matter?
The pituitary and gonads “read” the tempo of GnRH pulses. The wrong frequency or amplitude produces impaired steroidogenesis, cycle irregularities, low testosterone, anovulation, and fertility issues.
Pulse-based communication reflects the body’s emphasis on rhythm: circadian clocks, feeding windows, muscle recovery cycles, and immune surveillance all share timing logic.
What does this have to do with metabolism, brain health, and bones?
Sex steroids influence mitochondria, muscle preservation, hepatic insulin sensitivity, lipid metabolism, appetite signals, and fat partitioning—especially visceral fat.
Estrogen supports hippocampal plasticity, synaptic maintenance, and serotonergic function; testosterone stabilizes dopaminergic tone, motivation, and reward pathways.
Bone is exquisitely hormone-sensitive: osteoclasts (resorption) and osteoblasts (formation) dance to hormonal music. Disrupt the music, and bone turns brittle.
When kisspeptin signaling falls:
Metabolic rate can drop, insulin sensitivity declines, and the body shifts toward energy storage, often centrally (visceral fat).
Neurotransmitter balance shifts, increasing the risk of anxiety, depression, and anhedonia (emotional flatness).
Bone remodeling tilts toward resorption: osteoclasts accelerate while osteoblast activity lags, hastening osteopenia and osteoporosis.

The Clinical Picture: What Kisspeptin Suppression Looks Like In Real Life

I often meet:
Men with functional hypogonadism who also present with visceral adiposity, insulin resistance, hypertension, dyslipidemia, low motivation, and rising inflammatory markers.
Women in their 30s to 40s with irregular or anovulatory cycles, fatigue, weight gain, brain fog, lowered libido, immune shifts (frequent colds, autoimmune flares), anxiety/depression, and early bone-density concerns—despite high training loads or disciplined diets.
Young athletes with stress fractures or poor recovery, especially when under high psychosocial stress, caloric deficit, poor sleep, or intense endurance training.
A frustrating pattern is the conventional fragmentation of care: four or more prescriptions to manage glucose, lipids, mood, and bone—while the upstream clock (kisspeptin-GnRH) remains untuned. In our experience, restoring timing and signal quality re-synchronizes multiple systems at once.

Evidence Signals: What Leading Research Shows

Modern endocrinology and neurobiology have highlighted how kisspeptin coordinates reproductive and metabolic health. While numerous studies explore kisspeptin physiology and therapeutic potential, the practical clinical message remains consistent: when pulse dynamics and receptor responsiveness are restored, multiple downstream systems improve.
Examples of reported outcomes in the literature include:
Improved testosterone production and normalization of LH/FSH patterns in men with functional hypogonadism when kisspeptin signaling is supported or stimulated.
Enhanced ovulatory function and cycle regularity in women when hypothalamic-pituitary-ovarian timing is re-established.
Positive changes in body composition, visceral fat reduction, and improved insulin sensitivity correlated with normalized sex steroid rhythms.
Improvements in mood, anxiety, and cognitive performance, consistent with sex steroids’ modulation of serotonergic, dopaminergic, GABAergic, and glutamatergic systems.
Stabilization of bone remodeling parameters when upstream hormonal rhythms and nutrient-mechanical inputs are aligned.
Our protocols translate these findings into careful, individualized plans under integrated medical-chiropractic supervision.
Note: Specific study details and applicability vary; we evaluate patients individually. We employ evidence-based care and adjust protocols based on clinical response and safety.

How Kisspeptin Shapes Metabolism: From Mitochondria To Visceral Fat

Energy dynamics explained.
The body balances energy through intake, expenditure, and storage—but the”instructions” to favor burn or store are hormonal and neural.
Sex steroids act as metabolic rheostats:
Testosterone supports mitochondrial biogenesis, lean mass retention, and visceral fat suppression.
Estrogen maintains hepatic insulin sensitivity, modulates lipid metabolism, and supports muscle glucose uptake.
What happens when kisspeptin falters
GnRH pulses become dysregulated, diminishing LH/FSH signaling and subsequent sex steroid output.
Lower sex steroids shift metabolism toward storage:
Resting metabolic rate decreases.
Skeletal muscle loses anabolic tone and glucose disposal capacity.
The liver becomes more insulin resistant, promoting dyslipidemia.
Visceral fat expands, increasing inflammatory cytokines (e.g., IL-6, TNF-α) and worsening insulin resistance.
Clinical pattern we see
Patients report stubborn weight gain, especially around the abdomen.
Fasting insulin and HOMA-IR rise; triglycerides creep upward; HDL may fall.
Blood pressure moves north; energy drops; cravings increase.
Why integrative care works
We don’t treat “calories” alone. We restore the signaling context: circadian timing, sleep depth, stress modulation, nutrient density, resistance training, and, when appropriate, targeted peptides or medications under MD oversight. The body then “chooses” to burn.

Mood, Motivation, And Cognition: The Neurotransmitter Interface

Sex steroid-neurotransmitter crosstalk
Estrogen enhances serotonergic tone and hippocampal plasticity, supporting mood and memory consolidation.
Testosterone influences dopaminergic pathways, sustaining drive, reward processing, and executive function.
When kisspeptin dips
The brain loses buffering against anxiety and depression; anhedonia appears.
Patients describe “flat” affect, low drive, and brain fog.
Clinical translation
Rather than siloed psychiatric treatment alone, we investigate sleep architecture, circadian timing, inflammatory load, micronutrient status (e.g., omega-3 index, vitamin D, B vitamins), and sex steroid rhythms. Aligning these often alleviates mood symptoms while supporting long-term resiliency.

Bone Health And The Hormonal Music Of Remodeling

Bone is dynamic tissue.
Osteoclasts resorb; osteoblasts build. Hormones, nutrients, and mechanical loading direct this choreography.
Estrogen restrains resorption; testosterone supports formation and muscle-driven skeletal loading.
When kisspeptin is suppressed
Sex steroid decline removes checks on osteoclasts.
Bone density falls faster than expected for age; stress fractures and early osteopenia appear, especially in athletes with low energy availability.
Restorative strategy
Rebuild the hormonal rhythm, ensure adequate protein and minerals, prioritize vitamin D/K2 and omega-3s, and prescribe progressive, weight-bearing and impact training that safely stimulates osteogenesis.
Chiropractic care addresses kinetic chain dysfunction, ensuring axial loading is distributed properly, and joints can tolerate progressive forces.

Why The Body Chooses Storage: The Evolutionary Logic

From an evolutionary perspective, when stress, sleep loss, infection, or famine signals the hypothalamus, the body protects fertility by temporarily downshifting reproductive signaling. Kisspeptin sits at this decision point. If energy is low or stress is high, kisspeptin pulsatility diminishes, conserving resources but shifting metabolism to storage. Our job is to convince the hypothalamus that conditions are safe and abundant—through sleep regularization, nutrient density, sympathetic-parasympathetic balance, and consistent mechanical signals from healthy movement.

Common Drivers Of Kisspeptin Suppression

Chronic psychological stress and high allostatic load
Inadequate sleep, circadian disruption, late-night light exposure
Low energy availability (calorie deficit), especially with high training volume
Highly processed diets, poor protein quality, micronutrient gaps
Insulin resistance and chronic inflammation
Endocrine-disrupting chemicals (EDCs): BPA, phthalates, PFAS, etc.
Untreated hypothyroidism or subclinical thyroid dysfunction
Gut dysbiosis, lipopolysaccharide (LPS)-driven inflammation
Traumatic brain injury (TBI) and concussion sequelae
Persistent pain signaling and immobility after injury
Alcohol overuse and recreational drug impacts
Identifying and addressing these drivers in a structured plan is essential for long-term restoration.

Our Integrative Care Model: Chiropractic, Medical, Functional, And Rehab Under One Roof

At Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic), we deliver a coordinated pathway:
Medical direction and safety
Dr. Cardenas, Internal Medicine, directs medical care, orders and interprets labs and imaging, supervises peptide or pharmacologic interventions, and ensures clinical safety for complex cases.
Integrative chiropractic care
I address spinal and extremity biomechanics, joint restriction, and neuromuscular control.
Adjustments and mobilizations reduce nociceptive drive, normalize proprioception, and improve autonomic balance to support hypothalamic-pituitary coherence.
Functional medicine
We map root contributors: sleep-circadian misalignment, nutritional gaps, endocrine disruptors, gut-immune triggers, metabolic rigidity, and stress physiology.
Rehabilitation and performance
Progressive loading, movement patterning, breath mechanics, and fascia-focused therapy restore kinetic integrity, enabling safe return to sport and daily life.
Personal injury integration
Post-collision or work injury cases often involve pain, stress, sleep disruption, and deconditioning—each can suppress kisspeptin. Our team coordinates documentation, imaging, and staged rehabilitation while guarding endocrine-metabolic health.
This multidisciplinary setup—common in integrative and injury care clinics—prevents fragmentation and accelerates meaningful recovery.

The Evaluation Blueprint: Data-Driven And Personalized

Step 1: History and timeline
Symptom onset, stressors, injuries, training loads, menstrual or sexual function patterns, sleep logs, nutrition, weight history, and mood-cognition changes.
Step 2: Physical and biomechanical assessment
Posture, spinal and pelvic alignment, joint mobility, gait, breathing mechanics, muscle balance, and movement screens.
Step 3: Laboratory and imaging under medical oversight (as indicated)
Metabolic panel: fasting insulin, glucose, HbA1c, lipids, liver enzymes.
Inflammation: hs-CRP, ferritin, CBC, homocysteine.
Nutrient status: vitamin D, B12/folate, omega-3 index, iron studies.
Endocrine: morning cortisol patterning, thyroid panel (TSH, fT4, fT3), prolactin if indicated.
Sex hormones: total and free testosterone, SHBG, estradiol (phase-specific in cycling women), progesterone (mid-luteal), LH/FSH.
Bone health: DEXA for BMD and body composition; optionally bone turnover markers.
Gut health: targeted stool testing when GI symptoms or autoimmune patterns suggest dysbiosis.
Imaging: when injuries, stress fractures, or endocrine pituitary concerns arise.
Step 4: Functional testing
Heart rate variability (HRV), sleep wearables, continuous glucose monitoring (CGM) for select cases.
Our goal is to triangulate physiology—correlating symptoms, structure, and lab signals—so protocols match reality.

Chiropractic Care’s Role In Restoring Kisspeptin Signaling

Why chiropractic matters physiologically
Pain and joint dysfunction elevate sympathetic tone and inflammatory mediators—both suppress hypothalamic reproductive signaling.
Spinal and peripheral joint adjustments can:
Reduce nociceptive input and normalize dorsal horn processing.
Improve proprioceptive signaling, aiding sensorimotor integration.
Shift autonomic balance toward parasympathetic restoration, which supports hypothalamic pulsatility.
Improved movement quality enables progressive resistance and impact training—critical for muscle, metabolism, and bone.
Techniques we employ
High-velocity, low-amplitude adjustments when indicated and safe.
Low-force mobilization for sensitized patients.
Soft-tissue and myofascial techniques to reduce guarding and improve gliding.
Neuromuscular re-education to stabilize new ranges of motion.
Breath and rib mechanics to optimize vagal tone and thoracic mobility.
Clinical observation
When pain decreases, and movement improves, sleep deepens, HRV increases, and patients can adhere to nutrition and training plans—all inputs that favor kisspeptin restoration.
See clinical insights and case reflections:
Clinical observations (ChiroMed) – https://chiromed.com/
Professional updates – https://www.linkedin.com/in/dralexjimenez/

Medical Oversight: Ensuring Safety And Precision

Dr.Cardenas’’ role is pivotal:
She evaluates for medical contraindications, oversees lab strategy, and guides pharmacologic or peptide interventions when needed.
In complex cases—e.g., coexisting diabetes, hypertension, autoimmune disease, or perimenopausal transitions—her expertise keeps care on target and safe.
If advanced endocrine evaluation or imaging is necessary (e.g., suspected pituitary pathology), she directs referrals and coordinates care.

Functional Medicine Levers That Re-Synchronize The Axis

Circadian alignment and sleep architecture
Consistent sleep-wake times; morning light exposure; dim evenings.
Target 7.5–9 hours of sleep opportunity; prioritize slow-wave and REM quality.
Why: SCN-hypothalamic timing stabilizes GnRH pulses; sleep curtails cortisol and inflammatory mediators that blunt kisspeptin.
Stress recalibration
Breath training (e.g., slow nasal, 4-6 breaths/min), mindfulness, biofeedback, and structured recovery windows.
Strengthening social and environmental buffers to lower allostatic load.
Why: Chronic sympathetic drive suppresses hypothalamic reproductive signals; vagal tone promotes restoration.
Targeted nutrition
Protein at 1.6–2.2 g/kg/day to preserve lean mass.
Fiber-rich, polyphenol-dense plants for gut-immune balance.
Carbohydrates matched to training; prioritizing whole-food matrices to stabilize glucose-insulin dynamics.
Adequate omega-3s, magnesium, zinc, vitamin D/K2, and B vitamins.
Why: Nutrient sufficiency, stable glycemia, and anti-inflammatory patterns signal abundance and safety to the hypothalamus.
Resistance and impact training
2–4 weekly full-body strength sessions; progressive overload; technique first.
Low-to-moderate impact (as tolerated) for osteogenesis; plyometrics when appropriate.
Why: Muscle is a glucose sink and endocrine organ; loading drives bone formation and mitochondrial biogenesis.
Gut-immune restoration
Address dysbiosis; increase fermentable fibers and polyphenols; consider probiotics selectively.
Why: LPS and gut-derived inflammatory mediators suppress hypothalamic signaling and worsen insulin resistance.
Endocrine-disruptor hygiene
Reduce plastic contact, filter water, avoid thermal receipts, improve indoor air quality.
Why: EDCs can interfere with sex steroid receptors and hypothalamic cues, blunting kisspeptin responsiveness.
Alcohol and substance moderation
Limit alcohol; avoid sedative reliance.
Why: Alcohol disrupts sleep stages and inflames the gut-liver axis, worsening endocrine rhythms.
Micronutrient and lab-guided supplementation
Vitamin D sufficiency, omega-3 optimization, magnesium for sleep and insulin sensitivity, zinc for steroidogenesis.
Why: Key cofactors support the enzymatic pathways governing sex steroids and neurotransmitters.

When Peptides Or Pharmacologic Tools Are Considered

Under Dr. CCardenas’medical direction, we may consider:
Therapeutic agents that influence GnRH-kisspeptin dynamics or downstream steroidogenesis when lifestyle and rehabilitative strategies need support.
Sleep aids, when necessary, to stabilize architecture while behavioral interventions take hold.
Insulin-sensitizing agents if metabolic rigidity impedes progress.
Management of thyroid or prolactin imbalances that secondarily suppress kisspeptin.
We proceed conservatively, always prioritizing foundational pillars first. We integrate any peptide or prescription into a comprehensive plan with clear goals and monitoring.

Personal Injury Context: Protecting The Axis During Recovery

Injury care is a unique endocrine stress:
Pain, sleep fragmentation, reduced activity, and psychological strain suppress kisspeptin.
Steroid changes post-injury can accelerate sarcopenia and visceral fat.
Our approach:
Early pain control through chiropractic and manual therapies to reduce sympathetic drive.
Gentle movement reintroduction to defend muscle and bone.
Sleep and stress protocols started immediately.
Nutrition tuned for healing: adequate protein, collagen-rich foods, vitamin C, zinc, and omega-3s.
Medical oversight to address concussion/TBI, medications that may affect sleep-hormone balance, and safe progression criteria.

The Non-Surgical Approach to Wellness with Chiropractic Care- Video

Case Patterns I Commonly See

Pattern A: The over-trained, under-fueled woman in her 30s
Findings: Irregular cycles, high training load with low caloric intake, insomnia, rising fasting insulin, declining DEXA BMD.
Plan: Increase energy availability, reduce high-intensity frequency, add strength training, optimize sleep, micronutrient repletion, load the skeleton safely, and consider medical support if cycles remain anovulatory.
Outcome goal: Restored ovulatory rhythm, improved BMD trend, stable mood, stronger lifts and recovery.
Pattern B: The mid-40s executive male with creeping central adiposity
Findings: Late-night work and screens, elevated stress, low morning energy, low-normal testosterone with high SHBG, increasing triglycerides, borderline blood pressure.
Plan: Circadian reset, resistance training blocks, protein-first meals, alcohol reduction, chiropractic care to reduce pain and improve HRV, and medical assessment for insulin resistance and thyroid.
Outcome goal: Increased free testosterone, reduced visceral fat, improved sleep, steadier mood and drive.
Pattern C: Post-collision patient with persistent pain and brain fog
Findings: Neck and back pain, poor sleep, anxiety, decreased activity, weight gain.
Plan: Gentle adjustments and mobilization, breath and rib mechanics, graded activity, targeted nutrition, sleep stabilization; medical evaluation for concussion and appropriate therapies.
Outcome goal: Pain down, sleep up, cognitive clarity returning, endocrine markers normalizing.

Implementation Guide: From First Visit To Follow-Up

Week 0–2: Assessment, sleep routine, gentle mobility, protein targets, morning light exposure, hydration, and stress basics. Chiropractic care initiated to reduce nociception.
Week 3–6: Strength training starts (technique focus), nutrition refinement, gut support if indicated. Monitor HRV, sleep, and energy.
Week 7–12: Progress load and impact cautiously; recheck body composition; adjust macronutrients; consider medical therapeutics if metabolic rigidity persists.
Month 4–6: Reassess labs and DEXA when appropriate; refine program; taper supervised visits as self-efficacy increases.

Why This Works: The Physiology Of Coherence

When the body senses predictable rhythms, sufficient nutrients, lower inflammation, and safe, progressive mechanical load, the hypothalamus relaxes protective downshifts. Kisspeptin pulses regain their timing; GnRH resumes its music. Sex steroids rise within physiologic ranges, lifting mitochondrial output, neurotransmitter balance, and bone formation. Patients don’t just feel better—they rebuild capacity.

How We Coordinate Care Day-To-Day

Shared case reviews: Dr. Cardenas and I routinely review complex patients, aligning testing and interventions.
Clear communication: You will know why we choose each step and how we’ll measure progress.
Safety gates: We carefully titrate load, nutrition, and any medical agents, monitoring signs and labs.

What Success Looks Like

Stable, refreshing sleep and consistent wake energy
Improved body composition: higher lean mass, lower visceral fat
Regular cycles and improved fertility markers in women; better morning erections and libido in men
Lower fasting insulin, improved lipids, and normalized blood pressure
Clearer mood, stronger motivation, reduced anxiety
Stronger bones and fewer injuries
A resilient nervous system that recovers quickly from stressors

Frequently Asked Questions

Is kisspeptin only about fertility?
No. It’s a master timing signal with ripple effects on metabolism, brain function, and bone health by governing GnRH and downstream sex steroids.
Do I need medications?
Not always. Foundational care often restores signaling. When needed, medications or peptides are used judiciously under medical supervision.
How long until I notice changes?
Many patients notice sleep and energy improvements within weeks. Body composition and bone changes take longer—months for composition, years for bone density trends. We measure to keep progress visible.
Can chiropractic adjustments really influence hormones?
By reducing pain and sympathetic overdrive, improving sleep and movement, and enabling resistance training, chiropractic care indirectly supports the hypothalamic environment that sets hormone timing.

Integrating The Latest Research With Real-World Care

Our commitment is to evidence-informed, patient-centered practice. We synthesize modern endocrinology, neuroscience, sports medicine, and rehabilitation science with practical steps you can live with. When multiple issues appear at once—metabolic, mood, fertility, and bone—consider the upstream timing. Kisspeptin is not the only player, but it’s often the conductor we need to retune.
To explore care with us at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso—or to refer a complex case—reach out. We are here to help restore rhythm, resilience, and performance.
Learn more about my clinical perspective and ongoing observations:
Clinical observations and integrative insights – https://chiromed.com/
Professional background – https://www.linkedin.com/in/dralexjimenez/

References

  • Lehman, M. N., Coolen, L. M., & Goodman, R. L. (2010). Minireview: kisspeptin/neurokinin B/dynorphin (KNDy) cells of the arcuate nucleus: a central node in the control of gonadotropin-releasing hormone secretion. Endocrinology151(8), 3479–3489. https://doi.org/10.1210/en.2010-0022
  • Lehman, M. N., Ladha, Z., Coolen, L. M., Hileman, S. M., Connors, J. M., & Goodman, R. L. (2010). Neuronal plasticity and seasonal reproduction in sheep. The European Journal of Neuroscience, 32(12), 2152–2164. https://doi.org/10.1111/j.1460-9568.2010.07530.x
  • Clarke, H., Dhillo, W. S., & Jayasena, C. N. (2015). Comprehensive Review on Kisspeptin and Its Role in Reproductive Disorders. Endocrinology and Metabolism (Seoul, Korea)30(2), 124–141. https://doi.org/10.3803/EnM.2015.30.2.124
  • Zhu, L., Martinez, M. N., Emfinger, C. H., Palmisano, B. T., & Stafford, J. M. (2014). Estrogen signaling prevents diet-induced hepatic insulin resistance in male mice with obesity. American Journal of Physiology. Endocrinology and Metabolism, 306(10), E1188–E1197. https://doi.org/10.1152/ajpendo.00579.2013
  • Rossetti, M. L., Steiner, J. L., & Gordon, B. S. (2017). Androgen-mediated regulation of skeletal muscle protein balance. Molecular and cellular endocrinology447, 35–44. https://doi.org/10.1016/j.mce.2017.02.031
  • Fester, L., Prange-Kiel, J., Zhou, L., Blittersdorf, B. V., Böhm, J., Jarry, H., Schumacher, M., & Rune, G. M. (2012). Estrogen-regulated synaptogenesis in the hippocampus: sexual dimorphism in vivo but not in vitro. The Journal of Steroid Biochemistry and Molecular Biology, 131(1-2), 24–29. https://doi.org/10.1016/j.jsbmb.2011.11.010
  • Tobiansky, D. J., Wallin-Miller, K. G., Floresco, S. B., Wood, R. I., & Soma, K. K. (2018). Androgen Regulation of the Mesocorticolimbic System and Executive Function. Frontiers in Endocrinology, 9, 279. https://doi.org/10.3389/fendo.2018.00279
  • Wang, L., Wang, N., Zhang, W., Cheng, X., Yan, Z., Shao, G., Wang, X., Wang, R., & Fu, C. (2022). Therapeutic peptides: current applications and future directions. Signal transduction and targeted therapy7(1), 48. https://doi.org/10.1038/s41392-022-00904-4
  • de la Iglesia, H. O., & Schwartz, W. J. (2006). Minireview: timely ovulation: circadian regulation of the female hypothalamo-pituitary-gonadal axis. Endocrinology147(3), 1148–1153. https://doi.org/10.1210/en.2005-1311

SEO tags: kisspeptin, KNDy neurons, GnRH pulses, hypothalamus, metabolic rate, insulin sensitivity, visceral fat, osteoporosis, bone remodeling, estrogen, testosterone, neurotransmitters, anxiety, depression, anhedonia, hippocampal plasticity, integrative chiropractic care, functional medicine, El Paso injury clinic, Medical Director Dr. Maria Guadalupe Cardenas, Dr. Alex Jimenez, peptide therapy, circadian rhythm, sleep optimization, stress reduction, endocrine disruptors, resistance training, weight-bearing exercise, DEXA, body composition, HRV, personal injury rehabilitation, concussion care, internal medicine and chiropractic collaboration

El Paso Dysplastic Nevus Excision & Integrative Care

El Paso Dysplastic Nevus Excision & Integrative Care

Abstract: In this educational post, I guide you through a clear, step-by-step clinical approach to excising a dysplastic nevus with moderate atypia using modern, evidence-based methods. You will see how a properly executed anesthetic field block creates a pain-free experience, why dermatologic surgery for moderate atypia uses narrow margins, and how meticulous tissue handling supports definitive histologic assessment. I also share how our multidisciplinary team at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso, Texas integrates chiropractic care, internal medicine oversight, functional medicine, and rehabilitation. Under the medical direction of Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI #1164426749; Texas MD License #J2933), and in collaboration with me, Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, we blend precision procedural care with whole-person strategies grounded in current research. This post highlights how integrative chiropractic care fits into surgical dermatology and personal injury care to optimize healing, reduce pain, and support long-term outcomes.

El Paso Dysplastic Nevus Excision & Integrative Care

Introduction: Perspective on Modern, Multidisciplinary Skin Lesion Care

I am Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST. In our El Paso clinic, we often see patients who need carefully planned excisions following a diagnostic shave biopsy. Today, I’ll walk you through a real case: a 62-year-old gentleman returning approximately one month after a shave biopsy revealed a dysplastic nevus with moderate atypia. Our goals: remove the residual lesion with clinically appropriate narrow margins, enable a pain-free experience using a precise anesthetic field block, and ensure the tissue specimen is ideal for pathology.

What makes this care unique is our integrative model. As the Medical Director and Collaborative Physician, Dr. Maria Guadalupe Cardenas, MD (Internal Medicine), provides medical oversight and coordinates care pathways common to multidisciplinary injury and integrative clinics. In parallel, our chiropractic services, functional medicine strategies, and rehabilitation protocols create a cohesive system designed to keep the patient safe, comfortable, and moving toward recovery based on the best available evidence.

Building the Plan: Why Dysplastic Nevus with Moderate Atypia Requires Focused Margins

  • Key concept: Dysplastic nevi with moderate atypia are atypical moles with architectural and cytologic changes that warrant complete excision to reduce the risk of residual atypical tissue.
  • Evidence rationale: For moderate atypia, many dermatologic guidelines support excision with narrow margins (often around 2 mm beyond the visible or scar boundary) to ensure complete removal while preserving healthy tissue. Histopathologic evaluation confirms clearance.

In this case, the original lesion measured approximately 5 x 6 millimeters. I planned margins of roughly 2 millimeters around the current scar, translating to about 5 millimeters around the original lesion perimeter. Using a template helps me create a symmetric, fusiform design aligned with relaxed skin tension lines, minimizing postoperative tension and optimizing cosmetic results. Templates reduce human error in margin symmetry, and a well-planned ellipse supports primary closure with minimal dog-ears.

Design and Anesthesia: A Pain-Free Field Block by Interrupting Cutaneous Nerve Signaling

My goal with anesthesia is simple: make the experience pain-free and efficient. I start by prepping with alcohol, then reinforce the concept of a field block—a circumferential anesthetic “fence” that interrupts nerve signals entering the skin around our excision site.

Technique overview:

  • I select an ideal entry point near the planned excision boundaries.
  • I advance the needle, then inject while withdrawing, turning within the dermis/subcutaneous plane to create a continuous ring of anesthesia.
  • I repeat on the opposite side and, as needed, add lateral entry points to ensure complete coverage, always aiming for minimal needle insertions that produce maximal numbing.

Why it works physiologically:

  • The field block targets the terminal branches of sensory nerves within the dermis and subcutaneous tissue. By bathing these fibers with 1 percent lidocaine with epinephrine, we block voltage-gated sodium channels, preventing depolarization and halting nociceptive transmission.
  • Epinephrine causes local vasoconstriction, reducing bleeding and prolonging lidocaine’s dwell time near nerves. This prolongs anesthesia, helps maintain a bloodless field, and enhances visualization during precise excision.
  • Injecting in subcutaneous tissue to “saturate” beneath the lesion creates a foundational blockade. When we perform intradermal injections after subcutaneous saturation, patients typically report little or no sensation because the deeper nociceptive input has already been interrupted.

Adjunct comfort measures:

  • I use a cold “free spray” over the injection point. Rapid cooling stimulates A-delta fibers, which preferentially transmit cold sensations, creating a gating effect that reduces pain perception as the needle enters. This immediate numbing means they rarely feel the injection.
  • I steer the needle by slight bending to guide the tip across the dermal plane, carefully visualizing the trajectory under the skin. Injecting while withdrawing forms a visible intradermal wheal line that confirms even distribution.

Patient response:

  • Using these methods, our patient reported no pain throughout the anesthetic process. This is exactly the outcome we strive for—an effective, pain-free field block before excision.

Precision Excision: Narrow Margins and Tissue Integrity

With anesthesia confirmed and a clean field, the next step is the excision. Narrow margins are not arbitrary; they balance oncologic safety with tissue preservation, especially in cosmetically sensitive areas.

Core principles:

  • Margin control: For moderate atypia, 2-mm margins are commonly used; they are sufficient for complete removal while minimizing unnecessary tissue loss.
  • Fusiform design: An ellipse aligned with skin tension lines enables linear closure under reduced tension, decreasing the risk of hypertrophic scarring and optimizing cosmesis.
  • Specimen integrity: Gentle handling and correct orientation markings help pathologists assess margins and architecture accurately, confirming clearance.

Physiology of healing:

  • Minimal tension reduces micro-ischemia at wound edges, aiding angiogenesis and fibroblast activity necessary for collagen deposition.
  • Vasoconstriction from epinephrine tempers intraoperative bleeding, stabilizing the clot and early extracellular matrix formation.

Integrative Chiropractic Care in Dermatologic Surgical Recovery

While excision of a skin lesion may seem isolated from musculoskeletal care, an integrative approach adds value for recovery, comfort, and function—especially in older adults or those with comorbidities.

How chiropractic care fits:

  • Posture and movement optimization: After excision, patients often guard movement due to fear of pulling sutures. Chiropractic and rehabilitative strategies help maintain normal biomechanics and prevent compensatory strain.
  • Neuromuscular re-education: Gentle manual therapy and targeted exercises support proprioception and movement confidence, reducing myofascial tension near or distant from the surgical site.
  • Pain modulation: Chiropractic interventions can engage descending inhibitory pathways, reducing central sensitization that sometimes amplifies minor post-procedural discomfort.
  • Circulatory support: Mobility, diaphragmatic breathing, and safe motion progressions improve local perfusion, supporting oxygen delivery and waste clearance in healing tissues.

In practice, I assess global movement patterns and provide tailored strategies to keep patients functional without stressing the incision. For example, we may adjust daily ergonomic habits, teach safe range-of-motion techniques, and implement light isometrics that maintain muscle tone without disturbing the wound.

Multidisciplinary Oversight: Internal Medicine Leadership with Dr. Maria Guadalupe Cardenas, MD

Our clinic operates within a multidisciplinary framework common in integrative and injury care settings. Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI #1164426749; Texas MD License #J2933) serves as our Medical Director and Collaborative Physician. With over 40 years of experience as an internist, Dr. Cardenas supervises medical protocols, ensures safety for patients with complex health histories, and aligns the plan with best practices.

Medical oversight matters because:

  • Risk stratification: Internal medicine evaluates cardiovascular status, diabetes control, anticoagulation, and immunomodulating conditions that might impact bleeding, infection risk, or wound healing.
  • Medication management: Guidance on peri-procedural adjustments for antiplatelets/anticoagulants or immunosuppressants balances safety and procedural efficacy.
  • Systems-based care: Internal medicine connects dermatologic procedures with broader health concerns—sleep, nutrition, metabolic status—each influencing recovery timeline and scar quality.

Collaborative roles:

  • Dr. Cardenas provides medical direction, reviews histories, and creates safe peri-procedural pathways.
  • I deliver the procedure, chiropractic integration, functional medicine insights, and rehabilitative planning.
  • Together, we coordinate personal injury processes, documentation, and patient education.

Functional Medicine Integration: Optimizing Healing Physiology

Functional medicine supports the body’s innate healing mechanisms through targeted lifestyle and nutritional strategies tailored to the patient’s biology.

Focus areas:

  • Inflammation modulation: Adequate omega-3 intake, polyphenols (curcumin, quercetin), and antioxidant-rich foods can support controlled inflammation necessary for healing while preventing prolonged inflammatory states that delay recovery.
  • Glycemic control: Stable blood sugar supports fibroblast function, collagen cross-linking, and reduces infection risk; critical in older adults and those with metabolic syndrome.
  • Micronutrient sufficiency: Vitamin C (collagen synthesis), zinc (DNA replication and immune function), and vitamin A (epithelial integrity) are essential. We personalize supplementation cautiously, consistent with medical oversight.

Reasoning:

  • The acute wound healing phases—hemostasis, inflammation, proliferation, remodeling—depend on energy availability, micronutrient cofactors, and balanced immune signaling. Diet and lifestyle calibrate these processes.
  • Sleep quality and stress modulation (e.g., paced breathing) influence HPA axis activity and cytokine profiles that can either facilitate or impair tissue repair.

Rehabilitation Strategy: Safe Motion, Scar Care, and Long-Term Outcomes

Rehabilitation begins as soon as the procedure ends.

Key steps:

  • Early wound protection: Educate on dressing care, signs of infection, and avoiding tension across the incision.
  • Progressive mobility: Introduce gentle, non-straining movements to prevent stiffness and maintain circulation.
  • Scar optimization: Once the wound has closed, consider silicone sheeting, gentle massage, and sun protection to improve scar quality.
  • Ergonomics: Adjust lifting strategies, workstation setup, and daily routines to prevent undue strain near the surgical site.

Physiologic reasoning:

  • Controlled motion stimulates mechanotransduction pathways in fibroblasts, guiding orderly collagen alignment and increasing tensile strength.
  • Silicone occlusion modulates hydration and reduces excessive collagen deposition, decreasing hypertrophic scar risk.

Personal Injury Care and Documentation

In injury care settings, precision documentation complements clinical excellence:

  • Clear procedural notes with lesion size, margin plan, anesthesia specifics, and patient responses.
  • Photo documentation for pre- and post-excision views (when appropriate).
  • Communication with referring providers and insurers regarding necessity, medical oversight, and outcomes.

Clinical Observations from My Practice

At Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic), I have observed:

  • Patients experience significantly better comfort with a well-executed field block using 1% lidocaine with epinephrine and adjunct cold spray.
  • Narrow, well-planned margins for moderate atypia yield high clearance rates while preserving cosmesis.
  • Integrative chiropractic and functional medicine improve confidence in movement, reduce compensatory pain patterns, and support faster return to normal activities.

Step-by-Step Narrative: From Planning to Excision

  • Pre-Procedure:
    • Confirm pathology: dysplastic nevus with moderate atypia.
    • Explain margins and expectations to the patient.
    • Prepare sterile field with antiseptic; use alcohol for initial prep and repeat.
  • Field Block:
    • Choose entry point; advance needle; inject while withdrawing to create a continuous anesthetic ring.
    • Turn within the tissue plane to cover both sides without fully removing the needle.
    • Add lateral points if needed; saturate subcutaneous tissue under the lesion.
    • Verify numbness; apply cold spray before further injections.
  • Intradermal Distribution:
    • Thread the needle across the dermis; visualize tip; inject on withdrawal to form a visible wheal line indicating spread.
    • Assess patient comfort continuously; recalibrate if sensation persists.
  • Excision:
    • Mark ellipse with template; align with skin tension lines.
    • Excise along just outside the marked borders to respect margins.
    • Handle tissue gently; orient specimen; achieve hemostasis; close in layers if indicated.
  • Post-Procedure:
    • Educate on dressing changes, signs of infection, and motion precautions.
    • Schedule follow-up for pathology results and suture removal.
    • Provide integrative guidance on movement, nutrition, sleep, and stress.

Why Each Technique Matters

  • Template-guided marking: Ensures symmetry, facilitates linear closure, and reduces dog-ears.
  • Field block with epinephrine: Prolongs anesthesia, reduces bleeding, and improves operative field visibility.
  • Injecting on withdrawal: Distributes anesthetic evenly and reduces intratissue pressure spikes that can be uncomfortable.
  • Cold spray: Activates sensory gating to reduce needle pain.
  • Narrow margins: Balance complete excision of atypia with tissue preservation, aligning with evidence and cosmetic considerations.
  • Integrative follow-through: Addresses systemic determinants of healing and functional recovery beyond the incision line.

Safety Considerations

  • Avoid epinephrine in end-arterial regions if risk factors exist; assess peripheral vascular disease.
  • Screen for lidocaine allergies and arrhythmic history.
  • Coordinate with internal medicine on anticoagulation decisions and infection-risk mitigation.

Our Team-Based Care in El Paso, Texas

At Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic), our care model weaves together:

  • Chiropractic care (Dr. Jimenez): Movement analysis, manual therapy, neuromuscular re-education, ergonomic optimization.
  • Medical oversight (Dr. Cardenas, MD): Risk stratification, medication management, systems-based medical direction.
  • Functional medicine: Nutrition, sleep, stress, and personalized supplementation.
  • Rehabilitation: Progressive mobility, scar care, and return-to-function planning.
  • Personal injury services: Comprehensive documentation, coordination with legal and insurance entities where applicable.

Conclusion: Modern, Evidence-Based, Integrative Care for Skin Surgery

Excision of a dysplastic nevus with moderate atypia is more than a precise cut; it is a coordinated effort grounded in physiology, patient comfort, and multidisciplinary safety. By pairing a pain-free field block with careful margin planning and whole-person support, we improve outcomes and the patient experience. Under the medical direction of Dr. Maria Guadalupe Cardenas, MD, and through our integrative chiropractic, functional medicine, and rehabilitative care, patients receive comprehensive, evidence-based support from diagnosis to recovery.


References

Percutaneous Tenotomy for Chronic Tendinopathy

Percutaneous Tenotomy for Chronic Tendinopathy: An Integrative Approach

Abstract

Hello, I’m Dr. Alex Jimenez. Welcome to our educational corner, where we delve into the latest advancements in musculoskeletal health. My extensive background, holding titles like DC, APRN, FNP-BC, and multiple functional medicine certifications, allows me to bridge various disciplines to offer comprehensive, evidence-based care.

In this post, we will explore percutaneous tenotomy, a groundbreaking, minimally invasive procedure for treating chronic tendinopathies such as tennis elbow, plantar fasciitis, and Achilles tendinopathy. We will detail the two leading techniques, Tenex (ultrasonic emulsification) and TenJet (hydroresection), explain their physiological mechanisms, and show how they remove diseased tendon tissue while preserving healthy structures. This discussion is grounded in the latest evidence-based research from leading experts in the field.

Furthermore, I will explain how our unique multidisciplinary practice in El Paso, Texas, integrates these advanced procedures. At Injury Medical Clinic, I work alongside our Medical Director, Dr. Maria Guadalupe Cardenas, MD. With over 40 years of experience as a Board-Certified Internist, Dr. Cardenas provides essential medical oversight, ensuring a safe, effective, collaborative environment. Together, we combine functional medicine, rehabilitative science, and integrative chiropractic care to create a holistic treatment journey that resolves pain, restores optimal function, and prevents recurrence.

Join me as we explore the science behind percutaneous tenotomy and discover how this innovative treatment, combined with a patient-centered, integrative framework, is transforming outcomes for those with chronic tendon pain.

Percutaneous Tenotomy for Chronic Tendinopathy

Understanding the Challenge of Chronic Tendinopathy

As a clinician with decades of experience, I’ve seen countless patients struggle with tendinopathy, a condition often mislabeled as “tendinitis”. The key difference is that tendinitis implies active inflammation, whereas tendinopathy describes a degenerative state of the tendon. In tendinopathy, the tendon’s collagen fibers become disorganized, weakened, and filled with abnormal, painful tissue and sometimes microcalcifications. This is not an inflammatory problem but a structural failure of the tissue.

Conditions like lateral epicondylosis (tennis elbow), patellar tendinopathy (jumper’s knee), Achilles tendinopathy, and plantar fasciitis can be notoriously difficult to treat. Traditional conservative measures like rest, ice, and physical therapy are often effective for acute injuries but may fall short once the condition becomes chronic. In these cases, the degenerative tissue itself prevents healing, creating a cycle of pain and dysfunction. This is where modern, targeted interventions become essential.

Introducing Percutaneous Tenotomy: A Minimally Invasive Revolution

One of the most exciting advancements in musculoskeletal medicine is percutaneous tenotomy, an FDA-approved, ultrasound-guided procedure designed to debride, or remove, diseased tendon tissue. The term “percutaneous” simply means “through the skin,” highlighting its minimally invasive nature. This procedure represents a significant leap forward, offering a more definitive solution than conservative care but far less invasive than traditional open surgery.

The beauty of percutaneous tenotomy lies in its precision. Using real-time ultrasound imaging, we can guide a specialized instrument directly to the damaged tissue. This lets us selectively remove the degenerative, pain-generating portions of the tendon while leaving the surrounding healthy tissue intact. This precision is critical for promoting a robust healing response.

Two primary technologies dominate this field: Tenex and TenJet. Both are now accessible to appropriately trained primary care and specialty providers, allowing these procedures to be performed safely and effectively in the office.

The Tenex Health TX System: Ultrasonic Debridement

At our clinic, we utilize the Tenex Health TX system. This technology is a marvel of bioengineering, leveraging the principles of phacoemulsification—a technique famously used in modern cataract surgery.

  • How It Works: The Tenex system uses a handheld device connected to a console. The key component is an 18-gauge, double-lumen needle. When activated by a foot pedal, the needle tip vibrates at an ultrasonic frequency (around 20,000 Hz). This ultrasonic energy precisely emulsifies, or liquefies, the targeted degenerative tendon tissue.
  • The Double-Lumen Design: The Tenex probe’s ingenuity lies in its dual functionality. While the vibrating tip breaks down the pathologic tissue, a second, parallel lumen within the same needle simultaneously irrigates the area with saline and suctions the emulsified debris away. This “cut and remove” action is performed in a single, efficient step.
  • The Procedure: The procedure is performed under sterile conditions. After administering a local anesthetic, I use an ultrasound probe (covered in a sterile sheath) to visualize the damaged tendon. I insert the Tenex needle through the skin and guide it in real time to the area of tendinopathy. I then activate the device and methodically move the needle tip back and forth through the diseased tissue. The entire debridement process, or “cutting time,” is remarkably short, typically lasting between 30 and 90 seconds. The patient hears a humming sound but feels no pain due to the local anesthetic.

The TenJet System: A High-Velocity Saline Jet

The primary alternative to Tenex is the TenJet system. While the goal is the same—to remove diseased tendon tissue—the mechanism is different.

  • How It Works: TenJet uses a technology called hydroresection. Instead of ultrasonic energy, it employs a highly pressurized, high-velocity jet of sterile saline that shoots out from the tip of its specialized needle. This powerful fluid stream acts like a water knife, cutting and excising soft, degenerative tissue.
  • Simultaneous Aspiration: Like Tenex, the TenJet wand has a built-in suction feature that immediately removes resected tissue and excess saline, keeping the operative field clear and preventing pressure buildup.
  • Comparison: Both Tenex and TenJet are excellent tools. The choice between them often comes down to physician preference, training, and the specific characteristics of the tendon being treated. Both offer a significant advantage over traditional surgery by minimizing tissue trauma and accelerating recovery.

The Power of Integrative Care: Our Multidisciplinary Model

Performing an advanced procedure like percutaneous tenotomy is only one piece of the puzzle. True, lasting healing requires a comprehensive, integrative approach that addresses the patient as a whole. This is the core philosophy of our practice at Injury Medical Clinic.

My unique qualifications as a Doctor of Chiropractic (DC), an Advanced Practice Registered Nurse (APRN), a Family Nurse Practitioner (FNP-BC), and a certified Functional Medicine practitioner allow me to view health through multiple lenses. This is further strengthened by our collaborative structure with Dr. Maria Guadalupe Cardenas, MD, our esteemed Medical Director.

Dr. Cardenas is a Board-Certified Internist with an NPI of #1164426749 and Texas Medical License #J2933. With over four decades of clinical experience, she provides invaluable medical oversight for our practice. This multidisciplinary setup, where an MD and a DC work in tandem, ensures that our patients receive care that is both holistic and medically sound. We integrate the following services to create a powerful, synergistic treatment plan:

  1. Medical Oversight and Diagnosis (Dr. Cardenas): Dr. Cardenas’s internal medicine expertise is crucial for screening patients, managing comorbidities, and ensuring advanced procedures are medically appropriate. Her role guarantees the highest standards of patient safety.
  2. Functional Medicine Investigation (Dr. Jimenez): Why did the tendon fail in the first place? Functional medicine helps us answer this question. We investigate underlying factors like nutritional deficiencies (e.g., Vitamin C, zinc), systemic inflammation, metabolic dysfunction (like insulin resistance), and hormonal imbalances that can impair tissue repair. Addressing these root causes is essential for preventing recurrence.
  3. Integrative Chiropractic Care (Dr. Jimenez): A tendinopathy in the elbow or foot doesn’t exist in a vacuum. It is often linked to biomechanical dysfunction elsewhere in the body. As a chiropractor, I assess and correct kinetic chain imbalances. For example:
    • Tennis Elbow: This is often related to poor mechanics in the shoulder, scapula, and even the thoracic spine. Chiropractic adjustments and soft tissue mobilization can restore proper joint mobility and muscle firing patterns, reducing strain on the elbow.
    • Plantar Fasciitis: This is frequently linked to ankle immobility, tight calf muscles, or even pelvic misalignments that alter gait mechanics. Chiropractic care can address these upstream biomechanical faults. By correcting the body’s overall structure and movement patterns, we offload the healing tendon and create an environment where it is no longer subjected to repetitive microtrauma.
  4. Targeted Rehabilitation: Following a procedure like Tenex, the body needs the right signals to rebuild the tendon with strong, organized collagen. Our rehabilitation programs are designed to do just that. We progress patients from gentle range-of-motion exercises to eccentric loading exercises, which are scientifically proven to stimulate collagen synthesis and tendon remodeling (Alfredson et al., 1998). This phase is critical for translating the procedure’s structural fix into functional strength and resilience.

A Patient’s Journey at Our Clinic: From Pain to Performance

Let’s walk through a typical patient journey for someone with chronic tennis elbow:

  1. Initial Consultation & Diagnosis: The journey begins with a comprehensive evaluation. This includes a detailed history, physical exam, and diagnostic ultrasound to confirm tendinopathy and pinpoint the exact location of the diseased tissue.
  2. Collaborative Review: Dr. Cardenas and I review the case to confirm the diagnosis and ensure the patient is a good candidate for percutaneous tenotomy. We rule out any medical contraindications.
  3. Root Cause Analysis: We conduct a functional medicine workup, which may include blood tests to check inflammatory markers, nutrient levels, and metabolic health indicators.
  4. The Procedure: We perform the Tenex procedure in our office. The patient walks in and walks out, typically needing only a small adhesive bandage over the entry site.
  5. Post-Procedure Care: The initial phase focuses on rest and pain management, then quickly transitions to the active phase.
  6. Integrative Chiropractic & Rehabilitation: This is where the magic happens. The patient begins a structured program that includes:
    • Chiropractic adjustments to the spine, shoulder, and wrist to optimize biomechanics.
    • Soft tissue therapies like Active Release Technique (ART) or Graston to address scar tissue in surrounding muscles.
    • A progressive rehabilitation plan starting with gentle isometrics and progressing to the crucial eccentric strengthening exercises.
  7. Nutritional & Lifestyle Support: Based on the functional medicine findings, we provide targeted nutritional advice and supplements to support collagen production and reduce systemic inflammation.

By combining the precision of percutaneous tenotomy with the holistic framework of integrative chiropractic and functional medicine, we don’t just eliminate pain; we rebuild a more resilient, functional person. This is the future of musculoskeletal care—a future we are proud to offer our patients in El Paso today.


References

Alfredson, H., Pietilä, T., Jonsson, P., & Lorentzon, R. (1998). Heavy-load eccentric calf muscle training for the treatment of chronic Achilles tendinosis. The American Journal of Sports Medicine, 26(3), 360–366. https://doi.org/10.1177/03635465980260030301

Seng, K., & Lee, K. (2020). Percutaneous ultrasonic tenotomy for tendinopathies. Journal of Functional Morphology and Kinesiology, 5(3), 54. https://doi.org/10.3390/jfmk5030054


Integrative Medicine: What to Know About HRT & Menopause


Find out the benefits of HRT conbined with integrative medicine and how it can transform your menopause experience.

Abstract

Menopause represents a profound biological shift, extending far beyond a simple decline in hormones. While Hormone Replacement Therapy (HRT) is a cornerstone of treatment, it often falls short of resolving persistent symptoms like hot flashes, fatigue, brain fog, weight gain, and mood instability. This is because menopause is not merely a hormonal issue; it is a complex metabolic event rooted in three core biological problems: persistent inflammation (elevated C-reactive protein and oxidative stress), mitochondrial dysfunction (impaired cellular energy production), and localized insulin resistance. These factors prevent HRT from working effectively and contribute to the challenging symptoms many experience. In this educational post, I’ll explore these underlying biological drivers from my perspective as Dr. Alex Jimenez. We will delve into groundbreaking research highlighting the catastrophic decline of NAD+ during this transition and its impact on mitochondrial health. I will outline a comprehensive, evidence-based strategy that goes beyond standard HRT. This integrative approach combines targeted hormonal support with essential nutritional interventions, including key minerals and vitamins like magnesium, potassium, vitamin D3/K2, boron, zinc, taurine, and methylated B vitamins. Furthermore, I will explain how our unique clinical model at Injury Medical Clinic PA in El Paso, Texas, integrates my expertise in chiropractic and functional medicine with the invaluable medical oversight of Dr. Maria Guadalupe Cardenas, MD, our board-certified Medical Director. Together, we provide a multidisciplinary framework to address the neuro-musculoskeletal, hormonal, and metabolic facets of menopausal health, helping you reclaim your vitality and well-being.

Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST
Injury Medical Clinic PA
Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine)
Medical Director & Collaborative Physician
NPI #1164426749, Texas MD License #J2933

As a clinician with dual credentials in chiropractic care (DC) and as a Family Nurse Practitioner (APRN, FNP-BC), and with advanced certifications in functional medicine (CFMP, IFMCP), I have dedicated my career to understanding the intricate web of human physiology. My practice, Injury Medical Clinic PA, is built on an integrative model that merges multiple disciplines to achieve comprehensive patient outcomes. A cornerstone of this model is my collaboration with Dr. Maria Guadalupe Cardenas, MD. With over four decades of experience as a board-certified internist, Dr. Cardenas serves as our Medical Director, providing essential medical oversight and clinical wisdom that enriches our patient care protocols. This multidisciplinary partnership allows us to create treatment plans that are holistic and grounded in the highest standards of medical and evidence-based practice.
In my years of clinical observation, particularly through the lens of functional medicine, I have seen countless women navigate the challenging transition of perimenopause and menopause. Many arrive at my clinic feeling frustrated and unheard. They have often been told their symptoms are “just part of aging” or are purely hormonal, yet standard Hormone Replacement Therapy (HRT) has failed to provide complete relief. They still struggle with debilitating fatigue, persistent hot flashes, unexplained weight gain, and a rollercoaster of emotions. The transcript I am about to elaborate on touches upon the very core of this issue—a critical misunderstanding of the menopausal process. It is not just about hormones; it is about biology. Specifically, it is about cellular energy, inflammation, and metabolic health.
In this detailed post, I will expand on these concepts and translate the latest scientific research into a practical, easy-to-understand journey. We will explore why simply “running HRT” is like putting high-performance fuel into an engine that is clogged and misfiring. The fuel is essential, but it cannot fix the underlying mechanical problems. We will uncover the three main biological dysfunctions that sabotage hormonal balance and learn how to address them with a targeted, integrative approach that combines precise hormonal support, chiropractic care for neuro-musculoskeletal integrity, and functional nutrition. My goal is to empower you with the knowledge to move beyond just surviving menopause and truly start thriving.

The Great Misconception: Why HRT Alone Is Not Enough

For decades, the prevailing narrative surrounding menopause has been one of simple hormonal deficiency. The logic seems straightforward: as the ovaries stop producing estrogen and progesterone, replacing these hormones should restore balance and ease symptoms. While Hormone Replacement Therapy (HRT) can be a crucial and life-changing intervention for many, it is not a silver bullet. My clinical experience, supported by a growing body of evidence-based research, reveals a more complex reality. Many women I see in my practice are already on HRT yet continue to feel, in their own words, “like crap.” They are diligent with their prescriptions, but hot flashes persist, fatigue runs bone-deep, and brain fog clouds their daily lives.
This paradox exists because standard HRT primarily addresses the hormonal deficiency, not the underlying biological dysfunctions unfolding at the same time. Menopause is not just a hormonal event; it is a profound metabolic shift that creates a challenging internal environment. Giving hormones to a body struggling with inflammation, mitochondrial decay, and insulin resistance is like planting a beautiful garden in toxic, nutrient-depleted soil. The seeds (hormones) are there, but they cannot sprout and flourish.
To truly understand and effectively manage menopause, we must look beyond the hormones and address three fundamental biological problems:
Uncontrolled Inflammation and Oxidative Stress: HRT does not inherently lower systemic inflammation markers like C-reactive protein (CRP) or quell the storm of oxidative stress.
Mitochondrial Dysfunction and Localized Insulin Resistance: HRT does not rebuild our cellular powerhouses—the mitochondria—or correct the specific insulin resistance that develops in the brain and metabolic tissues.
Accelerated Nutrient Depletion: The tissue repair and metabolic acceleration spurred by HRT can deplete essential minerals and cofactors faster, creating new deficiencies if not properly managed.
Let’s dissect each of these issues to understand why they are the real culprits behind persistent menopausal symptoms and how an integrative approach is necessary to restore true wellness.

Biological Problem #1: The Inflammatory Barrier

One of the most common and frustrating experiences for women on HRT is the persistence of hot flashes. You are faithfully applying your estrogen patch or cream, yet you are still waking up drenched in sweat and experiencing sudden waves of intense heat throughout the day. This isn’t because the estrogen isn’t present; it is because a wall of inflammation is blocking its message.

How Inflammation Sabotages Estrogen’s Vasodilatory Effect

Estrogen plays a critical role in thermoregulation (the body’s ability to maintain a stable core temperature), primarily through its effects on the blood vessels. One key function is promoting the production of nitric oxide (NO), a potent vasodilator. Nitric oxide signals smooth muscle in the arterial walls to relax, allowing blood vessels to widen. This process, known as vasodilation, is essential for dissipating heat and maintaining circulatory health. When estrogen levels are optimal and the body is in a low-inflammatory state, this system works beautifully.
However, the menopausal transition often brings a significant increase in systemic inflammation. Multiple factors drive this, including the natural decline of estrogen (which has anti-inflammatory properties), age-related cellular changes, and lifestyle factors. This pro-inflammatory state is characterized by elevated levels of inflammatory cytokines (like IL-6 and TNF-alpha) and markers such as C-reactive protein (CRP).
Here is the crucial point: inflammation inhibits the nitric oxide pathway. High inflammation and associated oxidative stress (an imbalance between free radicals and antioxidants) damage the delicate inner lining of blood vessels, called the endothelium. This condition, known as endothelial dysfunction, prevents the cells from responding properly to estrogen’s signal. So, even when estrogen hits its receptors on the endothelial cells, the inflamed, dysfunctional machinery cannot produce enough nitric oxide.
The result? The blood vessels remain constricted when they should be dilating. The body’s ability to effectively manage heat is compromised. You take your hormone, but you keep the hot flashes. It is a classic case of cellular miscommunication, where the messenger (estrogen) arrives, but the recipient (the blood vessel) is too “sick” with inflammation to understand and execute the command. This is why just increasing the estrogen dose often fails to resolve the issue and can sometimes lead to other problems, like breast tenderness. The solution isn’t always more hormones; it’s first extinguishing the inflammatory fire.

Integrative Chiropractic and Medical Management of Inflammation

At Injury Medical Clinic PA, our approach to taming inflammation is multifaceted, leveraging the strengths of both functional medicine and chiropractic care under the guidance of Dr. Cardenas’s medical expertise.
Medical and Functional Diagnostics: We begin with comprehensive lab testing that goes beyond standard panels. Dr. Cardenas and I often order markers like hs-CRP (high-sensitivity C-reactive protein), homocysteine, and lipid peroxides to quantify inflammation and oxidative stress. This gives us a baseline and allows us to track progress objectively.
Targeted Anti-Inflammatory Nutrition: We guide patients through dietary modifications designed to reduce the inflammatory load. This typically involves removing pro-inflammatory foods like processed sugars, industrial seed oils (e.g., soybean, corn oil), and refined carbohydrates while emphasizing a diet rich in phytonutrients from colorful vegetables, healthy fats (like omega-3s from fish, avocados, and olive oil), and clean protein.
Chiropractic Care and the Nervous System: Chronic musculoskeletal stress and spinal misalignments can act as a significant source of systemic inflammation. As a chiropractor, I utilize precise spinal adjustments to restore proper joint mechanics and reduce nerve irritation. This is not just about alleviating back or neck pain. By optimizing nervous system function, particularly the autonomic nervous system, we can help shift the body from a chronic “fight-or-flight” (sympathetic) state to a “rest-and-digest” (parasympathetic) state. The parasympathetic nervous system plays a key role in downregulating inflammation through pathways like the cholinergic anti-inflammatory pathway. Correcting spinal dysfunction can therefore be a powerful tool in lowering the body’s overall inflammatory burden, allowing hormones like estrogen to work more effectively.
Supplementation: Based on lab results and clinical presentation, we may recommend powerful anti-inflammatory agents such as high-dose omega-3 fatty acids, curcumin (from turmeric), and resveratrol, which help to quell the inflammatory cascade at a cellular level.
By addressing inflammation first, we create a receptive internal environment. We are not just adding estrogen; we are ensuring the body can hear its message loud and clear. This is the first critical step toward resolving persistent symptoms like hot flashes and improving overall cardiovascular health.

Biological Problem #2: The Energy Crisis—Mitochondrial Collapse and Insulin Resistance

If inflammation is the static interfering with hormonal signals, then mitochondrial dysfunction is the power failure shutting down the entire system. This is arguably the most profound and least-appreciated aspect of the menopausal transition. The pervasive fatigue, brain fog, depression, anxiety, and stubborn weight gain are not just “side effects” of hormonal decline; they are direct consequences of a cellular energy crisis.

Mitochondria: The Powerhouses of Your Cells

To grasp the magnitude of this problem, we need a quick biology refresher. Every one of your trillions of cells contains tiny organelles called mitochondria. Their primary job is to take the fuel from the food you eat—glucose (from carbohydrates) and fatty acids (from fats)—and convert it into adenosine triphosphate (ATP) through a process called cellular respiration.
ATP is the universal energy currency of the body.
Every single biological process requires ATP. Thinking, moving, breathing, pumping your heart, synthesizing hormones and neurotransmitters, regulating your body temperature, repairing tissues—it all runs on ATP. When your mitochondria are robust and efficient, you feel vibrant, sharp, and resilient. When they are dysfunctional, your body’s systems begin to fail.

The Double Whammy in Menopause: Insulin Resistance and NAD+ Decline

During menopause, mitochondria face a perfect storm of challenges that leads to their decline and dysfunction.
1. Localized Insulin Resistance:
You have likely heard of insulin resistance in the context of type 2 diabetes, where muscle and liver cells stop responding to insulin, leading to high blood sugar. However, in menopause, a very specific and insidious form of insulin resistance develops in two critical areas: the hypothalamus (the brain’s master regulatory center) and metabolic tissues (like muscle).
The Problem of Fuel Overload: This localized insulin resistance means that even if there is plenty of glucose in the bloodstream, the mitochondria inside these key cells cannot effectively pull it in and use it for energy. Imagine a power plant (the mitochondrion) surrounded by heaps of coal (glucose) but with a broken conveyor belt, unable to get the fuel to the furnace. Cells are literally soaked in glucose but starving for energy.
The Shift to Visceral Fat Storage: This metabolic gridlock has devastating consequences. Because the body cannot efficiently burn glucose or access stored fat from adipocytes (fat cells) for energy, its default survival mechanism kicks in: it stores any excess energy as fat. Worse, it preferentially stores it as visceral fat—the dangerous, inflammatory fat that wraps around your internal organs. This is why so many women in menopause experience rapid weight gain, particularly around the midsection, even when they have not changed their diet or exercise habits. It is not a simple caloric problem of “eating too much and moving too little.” It is a metabolic problem of dysfunctional fuel partitioning. Your biology is programmed to store, not burn.
2. Catastrophic NAD+ Decline:
The second, and perhaps more fundamental, hit to mitochondrial function comes from the decline of a critical molecule called Nicotinamide Adenine Dinucleotide (NAD+). A groundbreaking 2021 study published in Nature Cell Biology provided definitive proof of something functional medicine practitioners had long observed: NAD+ levels decline catastrophically, and this decline accelerates during menopause (Covarrubias et al., 2021).
NAD+: The Mitochondrial Power Supply: NAD+ is essential for mitochondrial function. It acts as a key electron shuttle in cellular respiration, physically carrying the energy harvested from glucose and fatty acids to the machinery that produces ATP. Think of NAD+ as the fleet of trucks that transports the coal from the yard to the power plant’s furnace.
The Consequences of NAD+ Depletion: Without sufficient NAD+, the entire energy production line grinds to a halt. Even if glucose could get into the cell, the mitochondria lack the essential cofactor to convert it into ATP. This means the mitochondria lose their power supply. The lights go out at the cellular level.

The Clinical Manifestations of an Energy-Starved Brain and Body

This collapse in ATP production, driven by both insulin resistance and NAD+ depletion, is the root cause of the most debilitating symptoms of menopause:
Pervasive Fatigue: This isn’t just feeling tired; it’s profound cellular exhaustion. Your cells lack the ATP to function optimally.
Brain Fog and Cognitive Decline: The brain is the most energy-demanding organ in the body, consuming about 20% of your total ATP production. The prefrontal cortex—the region responsible for executive functions like mood regulation, impulse control, emotional stability, and rational thought—is particularly vulnerable. When it is energy-starved, you experience brain fog, memory lapses, and difficulty concentrating.
Depression, Anxiety, and Irritability: The synthesis and regulation of neurotransmitters like serotonin, dopamine, and GABA are highly energy-dependent processes. An energy-starved prefrontal cortex cannot maintain stable levels of these crucial mood-regulating chemicals. They all crash. This is why you can “take antidepressants like Skittles and still feel like trash.” You are treating a downstream symptom (low serotonin) while ignoring the upstream problem: the neurons have no ATP to synthesize serotonin in the first place. You are not “hormonal” or “crazy”—your brain is neurochemically unstable because its cells lack the fundamental energy required for proper function.
Hot Flashes: As we discussed, the hypothalamus controls thermoregulation. When mitochondria in hypothalamic neurons are energy-starved due to NAD+ decline, the entire system becomes unstable, leading to thermoregulatory collapse. This results in the classic hot flashes and night sweats.
Weight Gain and No Libido: The metabolic shift towards fat storage, driven by mitochondrial dysfunction, explains the stubborn weight gain. Libido, a complex interplay of hormones, neurology, and psychology, is also an energy-intensive process that falters when ATP is scarce.
All of these seemingly disconnected symptoms are anchored to one unifying problem: dying, dysfunctional mitochondria. Period. HRT alone does not rebuild mitochondria or restore NAD+ levels. To solve the energy crisis, we need a targeted strategy to reboot our cellular powerhouses.

Rebooting the Mitochondria: An Integrative Strategy

At our clinic, we rebuild mitochondrial health from the ground up, a process that requires a combination of medical, nutritional, and lifestyle interventions.
Restoring Insulin Sensitivity:
Dietary Intervention: The first step is to manage glucose and insulin levels through a low-glycemic diet. This involves reducing or eliminating refined sugars and processed carbohydrates that cause sharp blood sugar spikes. We emphasize a diet rich in fiber, healthy fats, and quality protein to promote stable blood glucose.
Exercise: Both resistance training and high-intensity interval training (HIIT) are incredibly effective at improving insulin sensitivity in muscle tissue, effectively “re-opening” the door for glucose to enter the cells and be used for energy.
Nutraceuticals: Certain supplements like berberine, alpha-lipoic acid, and chromium can help restore insulin sensitivity at the cellular level, acting on pathways similar to some prescription medications.
Boosting NAD+ Levels:
Precursor Supplementation: We can directly support NAD+ production by supplementing with its precursors, such as Nicotinamide Riboside (NR) or Nicotinamide Mononucleotide (NMN). These molecules provide the raw materials the body needs to synthesize more NAD+. This is a cornerstone of addressing the age-related and menopause-accelerated decline documented in research.
Lifestyle Factors: Caloric restriction, fasting, and intense exercise are also potent natural stimulators of NAD+ production through pathways involving proteins called sirtuins.
Supporting Mitochondrial Structure and Function:
Key Cofactors: We ensure patients have adequate levels of nutrients essential for the electron transport chain (the ATP-producing machinery), such as Coenzyme Q10 (CoQ10), L-carnitine, B vitamins, and magnesium.
Reducing Oxidative Damage: We use antioxidants like PQQ (pyrroloquinoline quinone), which has been shown to protect mitochondria from oxidative stress and even stimulate the growth of new mitochondria (mitochondrial biogenesis).
By implementing this comprehensive mitochondrial rescue plan, we address the root cause of the energy crisis. We are not just masking symptoms; we are restoring your cells’ fundamental ability to produce energy. This allows the fog to lift, the mood to stabilize, and vitality to return.

Biological Problem #3: The Unseen Drain on Essential Nutrients

The third, often-overlooked biological problem in menopause management is the accelerated depletion of key nutrients. Hormone Replacement Therapy, by its very nature, is designed to stimulate cellular activity and tissue repair—processes that were slowed by hormonal decline. When you reintroduce estrogen and other hormones, you are essentially “turning the metabolic engine back on” and asking it to run faster. This is a good thing, but it comes at a cost.
Think of it like a construction project. Before the project starts, the demand for raw materials (bricks, lumber, wiring) is low. Once construction begins, the demand skyrockets. If the supply of these materials doesn’t increase to meet the new demand, the project will quickly stall.
Similarly, when HRT speeds up metabolic processes and tissue repair, it dramatically increases the body’s demand for the raw materials required for these functions. These “raw materials” are the essential minerals, vitamins, and amino acids that act as cofactors in countless enzymatic reactions. If these nutrients are not supplied in adequate amounts, you can develop deficiencies that undermine the benefits of HRT and create a new set of symptoms.

The Non-Negotiable Raw Supplies for Hormonal and Metabolic Function

Based on decades of research and my own extensive clinical practice, there is a core group of nutrients that I consider non-negotiable for any woman navigating perimenopause and menopause, especially if she is on HRT. The body requires these raw supplies to function correctly, from metabolizing hormones to producing energy and maintaining bone density.
Magnesium: This is the master mineral. Magnesium is a cofactor in over 300 enzymatic reactions in the body. It is critical for ATP production, nerve function, muscle relaxation, and blood sugar control. It also plays a vital role in the methylation pathway, which is essential for detoxifying estrogens and preventing the buildup of harmful metabolites. Estrogen itself can increase the cellular uptake and utilization of magnesium, leading to a faster depletion. Symptoms of magnesium deficiency—such as anxiety, muscle cramps, insomnia, and heart palpitations—are incredibly common in menopausal women and are often mistaken for hormonal symptoms. If you feel “jittery” on HRT, it is a good chance you are taking too little magnesium (and taurine) to handle the metabolic shift.
Potassium: This electrolyte works in concert with sodium to maintain fluid balance, nerve transmission, and muscle contractions. It is also crucial for maintaining healthy blood pressure. Menopausal hormonal shifts can affect the body’s regulation of fluids and electrolytes, making adequate potassium intake essential.
Vitamin D3 and Vitamin K2: This pair is well known for its role in bone health, which is paramount because estrogen loss accelerates bone density decline. Vitamin D3 facilitates calcium absorption from the gut. Still, Vitamin K2 directs that calcium into the bones and teeth, preventing it from depositing in soft tissues like arteries and kidneys, where it can cause calcification and cardiovascular disease. Their function extends beyond bones; Vitamin D is technically a pro-hormone that influences immune function, mood, and insulin sensitivity.
Boron: This trace mineral is a hidden gem in hormone metabolism. Boron has been shown to increase the half-life and bioavailability of both estrogen and testosterone by slowing their excretion. It also supports bone health and has anti-inflammatory properties. It is a critical, yet often forgotten, nutrient for optimizing HRT.
Zinc: Zinc is essential for immune function, wound healing, and the production of stomach acid for proper digestion. It is also a key cofactor for the enzymes that produce steroid hormones, including progesterone and testosterone. Zinc deficiency can weaken the immune system, impair skin health, and reduce hormone synthesis.
Taurine: This unique amino acid has powerful benefits for menopausal women. Taurine helps to stabilize cell membranes, acts as an antioxidant within mitochondria, and supports cardiovascular health. Crucially, it helps calm the nervous system by supporting GABA function, which can alleviate the anxiety and “jitteriness” that some women experience as their metabolism shifts on HRT. It works synergistically with magnesium to buffer the excitatory effects of a revitalized metabolism.
Methylated B Vitamins: The B-complex vitamins (B6, B12, Folate) are the spark plugs of our metabolism. They are indispensable for energy production in the mitochondria and for a critical biochemical process called methylation. Methylation is required to synthesize neurotransmitters (serotonin, dopamine), detoxify hormones (especially estrogen), and regulate gene expression. Many individuals have genetic variations (like MTHFR) that impair their ability to convert standard B vitamins into their active, methylated forms. For these individuals, and for most women in menopause, supplementing with pre-activated forms like methylfolate, methylcobalamin (B12), and pyridoxal-5-phosphate (P-5-P, the active form of B6) is non-negotiable. If you experience breast tenderness on HRT, it can be a sign of poor estrogen methylation, often correctable with improved B6 and overall methylation support.
These nutrients are not optional add-ons; they are the fundamental building blocks your body needs to run its new, hormonally supported operating system. Ignoring them is a primary reason why many women fail to achieve the full benefits of HRT.

Aligned & Empowered: Chiropractic Conversations on Women’s Health-Video

The Clinical Playbook: A Practical Guide to Implementation

Understanding the “why” is crucial, but the “how” brings results. Based on the principles we have discussed, here is a practical, evidence-based playbook for navigating menopause. We customize this framework for each patient at our clinic, always under the medical supervision of Dr. Cardenas and me.

Rule #1: The Fourteen-Day Rule for Hormonal Adjustments

This is one of the most important and most frequently violated rules in hormone management. Hormones do not work like aspirin. When you introduce a new hormone or adjust a dose, it takes time for that hormone to distribute throughout the body, saturate the tissues, and achieve a steady state. This process takes approximately two weeks (fourteen days).
If you keep tweaking your dose every three days based on how you feel that particular day, you are chasing a moving target and creating wild fluctuations. You are generating more hormonal chaos, which can actually induce more hot flashes and mood swings than you started with.
The Protocol:
Make one adjustment at a time.
Wait a full fourteen days before assessing the effect and considering another change. Patience is paramount.
Track your symptoms objectively. Use a journal to note the frequency and intensity of hot flashes, sleep quality, mood, and energy levels. This provides data, not just feelings.
Stop messing with doses once your primary symptoms, like hot flash frequency, hit zero or reach a manageable, stable baseline. More is not always better. The goal is to find the lowest effective dose that resolves symptoms.

Standard Dosing Protocols and Formulations

While individual needs vary, a common starting point that is both effective and aligns with physiological principles is as follows:
Transdermal Estradiol: Applied once a day. Using estrogen through the skin (as a patch, gel, or cream) is generally preferred because it bypasses the “first-pass metabolism” in the liver. This avoids the increased risk of blood clots and the elevation of inflammatory markers associated with oral estrogen.
Oral Progesterone: Taken at bedtime only. Micronized oral progesterone has a natural sedative effect that can significantly improve sleep quality. It also protects the uterine lining (in women with a uterus) and has calming, anti-anxiety effects in the brain through its metabolite, allopregnanolone.
DHEA (Dehydroepiandrosterone): Taken in the morning. DHEA is a precursor hormone produced by the adrenal glands that can convert to both estrogen and testosterone. It often helps with energy, mood, and libido. However, it can also convert to androgens that cause side effects.
Troubleshooting DHEA: If you get cranky, irritable, or develop oily skin or acne, the dose may be too high for you, or you may be converting it too readily down the androgen pathway. The simple solution is to cut the DHEA dose in half and reassess.

Essential Lab Monitoring: Test, Don’t Guess

Objective data is your best friend. We cannot effectively manage what we do not measure.
Baseline Labs: Get a comprehensive lab panel done today, before you start any new hormonal or nutritional protocol. This should include a full hormone panel (Estradiol, Progesterone, FSH, Free and Total Testosterone, DHEA-S), thyroid panel (TSH, Free T3, Free T4), and the key metabolic and inflammatory markers we discussed (hs-CRP, Fasting Insulin, Fasting Glucose, HbA1c).
Follow-up Labs: Repeat the panel six weeks after you start the playbook. This timing allows hormones to reach a steady state and the initial effects of nutritional changes to become apparent.
Interpreting Estradiol Levels:
If your estradiol level is over 100 pg/mL, you are likely taking too much. This can increase the risk of side effects like breast tenderness and is often unnecessary for symptom control. The goal is relief, not hormone levels like a 20-year-old.
If your estradiol level is under 30 pg/mL and you are still symptomatic, you likely have room to bump up the dose gently.
Troubleshooting Common Side Effects:
Chest/Breast Tenderness: This is a classic sign of estrogen excess or, as mentioned, poor estrogen methylation. First, lower the estrogen dose. If it persists, we then investigate B6/methylation support.
Feeling Jittery or Anxious: This is rarely from the estrogen itself. It is a good chance you are either taking too much DHEA or, more commonly, you have too little magnesium and taurine on board to handle the increased metabolic rate and neuronal firing that comes with hormonal restoration.

The Integrative Chiropractic and Medical Framework at Injury Medical Clinic

This entire playbook is embedded within our unique clinical structure at Injury Medical Clinic PA. Drawing on my chiropractic and functional medicine background, my role is to identify and address the foundational pillars of health: the neuro-musculoskeletal system, metabolic function, and nutritional status.
As a chiropractor, I focus on keeping the nervous system—the body’s master control system—free from interference. Spinal health is not just about pain; it is about facilitating optimal communication between the brain and the body. By restoring proper alignment and motion, we can help downregulate the sympathetic “stress” response and reduce a key source of systemic inflammation, creating a more favorable environment for hormones to work.
This is where our collaboration with Dr. Maria Guadalupe Cardenas becomes so vital. As our Medical Director and a highly experienced internist, she provides the essential medical oversight required for any protocol involving prescription hormones like estradiol and progesterone. Dr. Cardenas reviews lab work, consults on dosing strategies, and manages the prescriptive aspects of care, ensuring everything we do is safe, effective, and adheres to the highest medical standards. Her four decades of internal medicine experience provide an invaluable perspective on complex cases and potential comorbidities.
Together, we bridge conventional medicine and functional/chiropractic care. A patient might see me for a chiropractic adjustment to address nerve irritation contributing to her systemic stress load, receive a detailed nutritional plan based on functional medicine principles to rebuild her mitochondria, and have Dr. Cardenas manage and fine-tune her HRT prescription. We also incorporate rehabilitation, personal injury care, and other services as needed, creating a truly holistic and patient-centered experience.
This multidisciplinary setup allows us to treat the whole person. We don’t just chase symptoms or look at a single hormone level in isolation. We are rebuilding the biological foundation of health, brick by brick, so that you can not only get through menopause but emerge on the other side with more energy, clarity, and vitality than you have felt in years. The journey requires a deep understanding of physiology, a commitment to evidence-based protocols, and, most importantly, patience. But the result—reclaiming your life—is worth the effort.

References

Covarrubias, A. J., Kale, A., Perrone, R., López-Domínguez, J. A., Pisco, A. O., Kasler, H. G., Schmidt, M. S., He, Y., Goya, R. G., & Verdin, E. (2021). Senescent cells promote tissue NAD+ decline during aging via the activation of CD38+ macrophages. Nature Cell Biology, 23(11), 1265–1279. [https://doi.org/10.1038/s41556-021-00781-6](https://doi.org/10.1038/s41556-021-00781-6)

SEO Tags: menopause, perimenopause, HRT, hormone replacement therapy, hot flashes, mitochondrial dysfunction, NAD+, insulin resistance, functional medicine, integrative chiropractic care, Dr. Alex Jimenez, Dr. Maria Guadalupe Cardenas, El Paso, TX, inflammation, CRP, magnesium, vitamin D3, methylated B vitamins, DHEA, progesterone, estradiol, brain fog, menopause weight gain, menopause fatigue, functional neurology

Unlocking Frozen Shoulder: Hydrodistension and Integrative Care

Unlocking Frozen Shoulder: Hydrodistension and Integrative Care

Abstract

This educational post explores the advanced technique of hydrodistension (or hydroplasty) for treating adhesive capsulitis, commonly known as frozen shoulder. As a practitioner rooted in integrative and functional medicine, I continually seek the most effective, evidence-based solutions for my patients. Here, I’ll guide you through a detailed look at the hydrodistension procedure, drawing on insights from leading sports medicine experts. We will examine the anatomical basis, the procedural steps, and the physiological mechanisms that make this technique a powerful tool for restoring mobility and relieving pain. I will also explain how this intervention fits within our multidisciplinary practice at Injury Medical Clinic, where my work as a Doctor of Chiropractic and Family Nurse Practitioner is complemented by the medical oversight of our Medical Director, Dr. Maria Guadalupe Cardenas, MD. Our goal is to provide a comprehensive treatment journey that combines advanced medical procedures with chiropractic care, rehabilitation, and functional medicine to achieve lasting patient outcomes.

Unlocking Frozen Shoulder: Hydrodistension and Integrative Care

At Injury Medical Clinic, our philosophy is built on collaboration and integration. My name is Dr. Alex Jimenez, and I bring a multifaceted perspective to patient care, holding qualifications as a Doctor of Chiropractic (DC), an Advanced Practice Registered Nurse (APRN), a Board-Certified Family Nurse Practitioner (FNP-BC), and certifications in Functional Medicine (CFMP, IFMCP), among others. This diverse background allows me to view health and injury through a uniquely broad lens.

A cornerstone of our practice is our multidisciplinary team approach. I work closely with Dr. Maria Guadalupe Cardenas, MD, our esteemed Medical Director and an internist with over 40 years of experience. Her role is vital, providing essential medical direction and oversight that ensures our patients receive care that is not only effective but also safe and comprehensive. This partnership between a chiropractor/nurse practitioner and an internist lets us blend the best of the medical and chiropractic worlds, offering services ranging from personal injury rehabilitation and functional medicine to advanced interventional procedures. Today, I want to share insights into one such procedure that exemplifies this integrated model: hydrodistension for frozen shoulder.

Understanding Adhesive Capsulitis (Frozen Shoulder)

Before diving into the procedure, let’s understand the condition it treats. Adhesive capsulitis, or frozen shoulder, is a debilitating condition characterized by severe pain and a progressive loss of shoulder motion. The underlying pathology involves the glenohumeral joint capsule—the strong, fibrous sac that envelops the shoulder joint. In a healthy shoulder, this capsule is flexible and allows for a wide range of motion. In adhesive capsulitis, the capsule becomes inflamed, thickens, and contracts, effectively “shrinking” around the joint. This process leads to the formation of adhesions, which are bands of scar tissue that bind the capsule to the humeral head (the ball of the shoulder joint), severely restricting movement.

Patients typically experience three phases:

  1. Freezing Stage: A gradual onset of deep, aching pain, often worse at night. As pain intensifies, range of motion begins to decrease. This stage can last from weeks to months.
  2. Frozen Stage: Pain may start to subside, but stiffness becomes the primary complaint. The shoulder’s range of motion is significantly limited, making daily activities like dressing or reaching overhead extremely difficult. This phase can last for several months to a year.
  3. Thawing Stage: Shoulder mobility slowly improves as the condition resolves. This can be a very long process, sometimes taking one to two years to regain full or near-full function.

The goal of any effective treatment is to shorten these phases, alleviate pain, and restore function as quickly and completely as possible.

Hydrodistension: An Advanced Technique for Restoring Mobility

Hydrodistension, also known as hydroplasty, is a minimally invasive procedure designed specifically for adhesive capsulitis. The fundamental principle is to physically stretch and break the adhesions within the joint capsule by injecting a large volume of fluid. This creates more space within the joint, allowing for an immediate improvement in range of motion.

I recently had the opportunity to review the work of a primary care sports medicine physician. Their meticulous, ultrasound-guided approach is an excellent model for understanding how to perform this procedure safely and effectively. Let’s break down his process, which serves as a benchmark in modern, evidence-based practice.

To visualize the target area, we can look at an ultrasound image of the posterior (back) shoulder.

In the image, you can clearly see the layers of tissue:

  • The deltoid muscle on the surface.
  • The infraspinatus muscle (one of the rotator cuff muscles) just below it.
  • The posterior capsule, the key target, which appears as a bright, fibrous line.
  • The humeral head, the “ball” of the shoulder joint.
  • The glenoid, the “socket” of the shoulder joint.

The goal is to accurately place a needle into the glenohumeral joint space—the small area between the capsule and the humeral head—to deliver the fluid.

The Three-Step Hydrodistension Procedure

The doctor’s method is a well-orchestrated, three-step process designed for maximum patient comfort and procedural success. It involves precise, ultrasound-guided injections to ensure accuracy and safety at every stage.

Step 1: Suprascapular Nerve Block

The first and arguably most compassionate step is to manage the patient’s pain during and after the procedure. This is achieved with a suprascapular nerve block.

  • The Target: The suprascapular nerve, which provides approximately 70% of the sensory innervation to the shoulder joint. By numbing this nerve, we can significantly reduce procedure-related pain and provide intermediate relief for hours afterward. The nerve is targeted at the spinoglenoid notch, a small anatomical landmark located just medial to the glenohumeral joint.
  • The Technique: Using an ultrasound, Dr. visualizes the spinoglenoid notch and guides a needle to the area. He then injects a local anesthetic, typically a combination of lidocaine (fast-acting) and ropivacaine (long-acting). This dual-anesthetic approach provides both immediate and extended pain control.
  • Why It’s Done: This nerve block is crucial for patient tolerance. The hydrodistension itself can be uncomfortable as the capsule stretches. By preemptively blocking the primary sensory nerve, the patient remains comfortable, and the physician can perform the procedure without causing undue distress. This aligns with our patient-centered approach at Injury Medical Clinic, where comfort and safety are paramount.

Step 2: Numbing the Joint Capsule

Next, anesthetize the injection site and the joint capsule.

  • The Target: The posterior glenohumeral joint space.
  • The Technique: A smaller, 25-gauge needle is guided under ultrasound into the joint space. A small amount of buffered lidocaine is injected. The “buffering” is done by adding sodium bicarbonate to the lidocaine, which raises its pH to be closer to that of the body’s tissues. This simple modification reduces the stinging sensation of the injection, further enhancing patient comfort.
  • Why It’s Done: This local numbing ensures the larger needle in the final step is painless. It also confirms that the needle tip is correctly positioned within the intra-articular space before the main injection begins.

Step 3: The Hydrodistension Injection

This is the main event, where the therapeutic distension occurs.

  • The Injectate: A carefully formulated mixture totaling 51 mL. It consists of:
    • 10 mL of 1% lidocaine (fast-acting anesthetic)
    • 10 mL of 0.5% ropivacaine (long-acting anesthetic)
    • 30 mL of sterile saline (the primary volume for distension)
    • 1 mL of Kenalog (40 mg) (a corticosteroid to reduce inflammation)
  • The Technique: A larger, 18-gauge needle is guided into the same intra-articular position. This is often a two-person job; The doctor guides the needle while his medical assistant steadily pushes the large volume of fluid from the syringe. As the fluid is injected, the ultrasound screen provides real-time feedback. You can literally watch the posterior capsule lift and stretch away from the humeral head as it fills with fluid.
  • The “Break”: The goal is to continue injecting until the capsule is stretched to its limit and the adhesions break. On ultrasound, this appears as a sudden expansion followed by slight deflation as the fluid finds new space within the joint, or may even extravasate (leak) through a small tear in the now-stretched capsule. This visible “break” is the hallmark of a successful procedure. The patient often feels an immediate sense of release and an increase in their range of motion.

Using a corticosteroid like Kenalog is critical. It strongly suppresses the inflammatory process that drives capsule thickening and contraction. This not only relieves pain but also helps prevent rapid re-formation of adhesions, creating a therapeutic window for the next phase of care: rehabilitation.

The Role of Integrative Chiropractic Care Post-Procedure

The hydrodistension procedure is a powerful “reset” for the shoulder, but it is not a standalone cure. The real, long-term success comes from what happens next. The days and weeks following the procedure are a critical window of opportunity to restore normal joint mechanics and muscle function. This is where our integrative model at Injury Medical Clinic truly shines.

As a Doctor of Chiropractic, I immediately focus on capitalizing on the newly gained mobility. My clinical observations, detailed on platforms like my professional website and LinkedIn, consistently show that a structured, multi-faceted rehabilitation program is essential.

Our post-hydrodistension protocol includes:

  • Gentle Chiropractic Mobilization: After the procedure, I perform specific, gentle mobilization techniques on the glenohumeral joint and surrounding joints, including the scapulothoracic (shoulder blade on the rib cage), acromioclavicular, and sternoclavicular joints. The goal isn’t aggressive manipulation, but to encourage smooth, physiological movement and prevent the joint from stiffening again. We must respect the body’s healing process while re-educating the joint on how to move correctly.
  • Targeted Soft Tissue Therapy: Adhesions don’t just form in the capsule; the surrounding muscles often become tight, guarded, and develop trigger points. We use techniques like myofascial release, instrument-assisted soft tissue mobilization (IASTM), and trigger point therapy to release tension in the rotator cuff, deltoid, and periscapular muscles. This restores muscle pliability and reduces compensatory strain patterns.
  • Prescriptive Rehabilitation Exercises: This is the most crucial component. We guide patients through a phased exercise program that begins with gentle pendulum exercises and passive range-of-motion on the day of the procedure. As tolerance improves, we progress to:
    • Active-assisted range of motion (using the other arm or a pulley to help move the affected shoulder).
    • Active range of motion (moving the shoulder under its own power).
    • Strengthening exercises, starting with isometrics and progressing to resistance bands to rebuild the strength and endurance of the rotator cuff and scapular stabilizers.

Under the medical direction of Dr. Cardenas, we ensure this rehabilitation process is medically appropriate for the patient, monitoring for complications and managing post-procedural inflammation. This collaborative oversight allows us to safely push the boundaries of recovery.

Conclusion: An Integrated Path to Recovery

Treating complex conditions like adhesive capsulitis requires more than a single intervention. It demands a holistic, integrated approach that addresses the problem from multiple angles. The hydrodistension procedure, as expertly demonstrated by physicians, provides a powerful mechanical and pharmacological intervention to break the cycle of stiffness and pain. It creates a pivotal opportunity for recovery.

However, the comprehensive, team-based care that follows truly solidifies the gains and leads to lasting results. At Injury Medical Clinic, our unique structure—combining my expertise in chiropractic and functional medicine with the invaluable medical oversight of Dr. Maria Guadalupe Cardenas—allows us to provide that. We bridge the gap between advanced medical procedures and hands-on rehabilitative care, guiding our patients on a seamless journey from profound limitation to renewed function and a life free from pain.


References

  • Boutin, R. D., Darrow, M. A., & Schenker, M. L. (2014). Ultrasound-guided shoulder interventions. Physical Medicine and Rehabilitation Clinics of North America, 25(2), 247–266. https://doi.org/10.1016/j.pmr.2014.01.002
  • Ryan, V., Brown, H., Minns Lowe, C. J., & Lewis, J. S. (2016). The pathophysiology associated with primary (idiopathic) frozen shoulder: A systematic review. BMC Musculoskeletal Disorders, 17(1), 340. https://doi.org/10.1186/s12891-016-1190-9
  • Tveitå, E. K., & Røe, C. (2009). Ultrasound-guided hydrodistension and physiotherapy for patients with frozen shoulder. Physiotherapy Research International, 14(1), 39–51. https://doi.org/10.1002/pri.422