Give us a Call
+1 (915) 412-6680
Send us a Message
[email protected]
Opening Hours
Mon-Thu: 7 AM - 7 PM
Fri - Sun: Closed
Chiropractic & Regenerative Care for El Paso Workers

Chiropractic & Regenerative Care for El Paso Workers

Abstract: El Paso tech professionals and warehouse associates face different job demands, yet both can develop neck, back, shoulder, hip, or joint problems that disrupt work and family life. This article explains how integrated chiropractic, medical, rehabilitation, and carefully selected regenerative care can support movement and recovery while keeping safety, informed choice, and coordinated care at the center.

Chiropractic & Regenerative Care for El Paso Workers

A heating pad may calm tight muscles after a long shift. But temporary warmth does not answer the bigger question: why does the same pain keep returning?

That question matters whether you spend your workday behind monitors or moving products through a warehouse. One worker may sit for hours. Another may walk miles, bend into low bins, lift boxes, twist, push, pull, and repeat the same motions hundreds of times. The loads differ, but both bodies can become irritated when movement is too limited, repetitive, or demanding.

For household providers, the goal is not simply to get through another shift. It is to keep working, sleeping, helping at home, and aging with strength and independence.

Two Jobs, Two Stress Patterns

Tech desk workers: too little movement

Computer work often creates a low-motion problem. A 2025 review linked office-worker low-back symptoms with factors such as longer sitting, static sitting behavior, poor posture, and fewer breaks, although individual studies were not completely consistent (Alaca et al., 2025). Exercise, especially strengthening, can improve pain and disability in office workers with chronic neck pain (Jones et al., 2024).

Common pressure points include:

  • Forward-head positioning during screen work.
  • Rounded shoulders and stiff hips.
  • Reduced trunk and upper-back endurance.
  • Wrist and forearm irritation from keyboard and mouse repetition.
  • Too little movement variety across workdays.

Warehouse associates: repeated loading

Warehouse work creates almost the opposite problem. OSHA identifies lifting, lowering, bending, overhead reaching, pushing, pulling, awkward postures, and repeated tasks as important ergonomic risk factors for musculoskeletal disorders (Occupational Safety and Health Administration [OSHA], n.d.).

That can mean:

  • Repeated low-bin bending.
  • Lifting from floor or pallet height.
  • Reaching above shoulder level.
  • Twisting while carrying or scanning.
  • Repetitive gripping and wrist loading.
  • Long hours on hard floors with limited recovery.

The answer for either worker is rarely “sit perfectly” or “lift perfectly” all day. Human bodies need capacity, recovery, movement variety, and workloads they can tolerate.

Chiropractic Care as Part of the Plan

Chiropractic care is most useful when it is not treated as a stand-alone miracle. Structural examination and manual care can be paired with exercise, rehabilitation, medical evaluation, and patient education.

For chronic primary low-back pain, the World Health Organization recommends person-centered care that may include education, exercise, some physical therapies such as spinal manipulative therapy, and other coordinated options rather than relying on a single treatment (World Health Organization [WHO], 2023).

At ChiroMed, practical goals may include:

  • Improve painful or restricted movement.
  • Restore joint motion when clinically appropriate.
  • Build trunk, hip, shoulder, and neck endurance.
  • Teach safer lifting and workstation habits.
  • Increase tolerance for work and home demands.
  • Reassess when symptoms do not follow an expected recovery pattern.

The benefit is not simply “better alignment.” The larger target is better function: standing from a chair with less stiffness, completing a shift with less irritation, sleeping more comfortably, or lifting a child with greater confidence.

Where Regenerative Medicine May Fit

Regenerative medicine is a broad term, so careful language matters. Not every injection marketed as “regenerative” has the same evidence, regulatory status, or safety profile. The FDA warns consumers about unapproved products promoted for orthopedic pain and other conditions (U.S. Food and Drug Administration [FDA], 2021).

Platelet-rich plasma, or PRP, is prepared from a patient’s blood and concentrates platelets that contain signaling molecules involved in healing. Evidence varies by condition. For knee osteoarthritis, a review of randomized trials found that PRP may improve pain and function for some patients, while protocols and outcomes remain inconsistent (Pelluri et al., 2025).

Candidacy matters. A worker with an irritated tendon, early joint degeneration, or stubborn soft-tissue problem may need a different plan than someone with nerve compression, fracture, inflammatory disease, or simple muscular fatigue. An injection should not replace diagnosis or the rehabilitation needed to change forces that keep aggravating tissue.

The ChiroMed Integrated Care Model

ChiroMed brings structural care and medical oversight into one conversation. Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, is a Doctor of Chiropractic and board-certified Family Practice Nurse Practitioner. He holds Texas Advanced Practice Nursing License #1191402, Prescriptive Authority #59628, and NPI #1205907805. His scope bridges chiropractic structural care, mechanical rehabilitation, functional medicine diagnostics, nutrition, and, when clinically and legally appropriate, advanced therapies including PRP, PRF/PFP, MFAT, image-guided epidural spinal injections, and BHRT.

Dr. Maria Guadalupe Cardenas, MD, is board-certified in Internal Medicine, has more than 40 years of experience, and holds Texas Medical License #J2933 and NPI #1164426748. She serves as Medical Director, Clinical Director, and collaborative physician, overseeing complex medical risks, advanced laboratory interpretation, and treatment coordination.

This teamwork matters because recovery may also depend on sleep, blood sugar regulation, nutrition, medication use, inflammation, age, and other health factors.

Protect the Breadwinner, Support the Family

When one person’s income depends on staying physically capable, pain affects the household. Missing overtime, avoiding family activities, losing sleep, or fearing normal movement can create stress beyond the injured body part.

An integrated plan should ask, “What does this person need to keep doing safely?”

For a tech worker, that may mean:

  • Tolerating computer sessions with movement breaks.
  • Reducing neck and shoulder fatigue.
  • Rebuilding upper-back and trunk endurance.
  • Improving recovery after mentally demanding days.

For a warehouse associate, it may mean:

  • Bending and lifting with better hip and trunk control.
  • Improving leg and core endurance.
  • Recovering between repetitive shifts.
  • Returning to higher loads gradually.

These are practical outcomes families can feel.

Beneficence and Non-Maleficence: Start With the Safest Reasonable Path

Good care should serve the patient’s welfare, not the procedure. Begin with reasonable lower-risk options, measure response, and escalate only when the clinical picture supports it.

Non-invasive care may include education, activity modification, therapeutic exercise, chiropractic manipulation or mobilization, soft-tissue care, and progressive rehabilitation. When symptoms are severe, persistent, or linked to a specific tissue problem, medical evaluation may identify additional options.

The goal is not to promise that every patient can avoid medication or surgery. It is to use lower-risk strategies when appropriate while recognizing that medication, injections, or surgical consultation may sometimes be needed.

Autonomy: You Stay in Charge

Integrated care should expand choices. Before any procedure, patients deserve clear answers:

  • What is the working diagnosis?
  • What alternatives exist?
  • What are the likely benefits and risks?
  • What evidence supports this treatment for my condition?
  • How will we measure whether it is working?

ChiroMed can also coordinate with a patient’s existing physician, specialist, therapist, or other clinician. A connected plan helps reduce duplicated care and keeps important information from living in separate silos.

When a Heating Pad Is Not Enough

Home care is reasonable for many mild aches. Persistent or worsening symptoms deserve evaluation, especially when pain repeatedly limits work, sleep, or family activity.

Seek prompt medical attention for new or progressive weakness, loss of bowel or bladder control, numbness in the groin or saddle region, major trauma, fever with severe back pain, unexplained weight loss, chest pain, or other concerning symptoms.

For less urgent problems, the signal may be simpler: pain keeps returning, sleep suffers, your normal workload shrinks, or temporary relief never improves capacity.

Move From Relief to Resilience

El Paso’s tech workers and warehouse associates may live at opposite ends of the movement spectrum, but both need the same basic outcome: a body that can handle real life.

The most useful plan does more than quiet symptoms. It identifies the stress pattern, rules out important medical concerns, restores movement, rebuilds capacity, and considers advanced therapies only when they fit the diagnosis and patient goals.

At ChiroMed, chiropractic care, rehabilitation, advanced practice nursing, and internal medicine oversight can work as one coordinated team. If pain is shrinking your work capacity or family time, schedule an integrated evaluation to identify the problem, review conservative and advanced options, and build a plan around safe function, informed choice, and the life you work hard to provide.


References

Alaca, N., Acar, A. Ö., & Öztürk, S. (2025). Low back pain and sitting time, posture and behavior in office workers: A scoping review. Journal of Back and Musculoskeletal Rehabilitation, 38(5), 919–943.

Jones, L. B., Jadhakhan, F., & Falla, D. (2024). The influence of exercise on pain, disability and quality of life in office workers with chronic neck pain: A systematic review and meta-analysis. Applied Ergonomics, 117, 104216.

Occupational Safety and Health Administration. (n.d.). Warehousing: Hazards and solutions. U.S. Department of Labor.

Pelluri, R., Sridevi, B., Guntupalli, C., Gurram, P. C., Nagasubramanian, V. R., Punnem, U. S., Kanukula, R., Ponnusankar, S., Nagendra, V. H., & Mateti, U. V. (2025). Effect of platelet-rich plasma versus placebo or corticosteroid for knee osteoarthritis: A systematic review and meta-analysis of randomized controlled trials. Journal of Clinical Orthopaedics and Trauma, 62, 102870.

U.S. Food and Drug Administration. (2021). Important patient and consumer information about regenerative medicine therapies.

World Health Organization. (2023). WHO guideline for non-surgical management of chronic primary low back pain in adults in primary and community care settings.


Metabolic Restoration for Better Health from Insulin Resistance

Reclaim your health from insulin resistance with metabolic restoration techniques that promote optimal metabolic performance.

Abstract: Decoding the Metabolic Crisis

As a healthcare provider with a diverse background spanning chiropractic, advanced practice nursing, and functional medicine, I’ve dedicated my career to understanding the intricate web of human health. My journey, alongside our dedicated team at Injury Medical Clinic, has led me to a fundamental truth: many of the chronic diseases plaguing our society today are not separate, isolated conditions. Instead, they are downstream consequences of a central, upstream dysfunction. This post explores that core issue: insulin resistance and chronic high insulin, or hyperinsulinemia. We will explore how this single metabolic imbalance acts as the “source code” for a cascade of conditions, including type 2 diabetes, fatty liver disease, cardiovascular issues, and even certain types of cancer.

Drawing upon the latest evidence-based research from leading institutions and publications like The Lancet and JAMA Oncology, we will unravel the physiological mechanisms behind this crisis. We will examine groundbreaking pharmacological advancements, such as the triple-agonist peptide retatrutide, not just as a “miracle drug” but as a powerful tool that reveals the profound potential of correcting the root metabolic problem. This discussion will also critically analyze the healthcare industry’s economic structure, which often incentivizes managing downstream symptoms rather than resolving the upstream cause.

At our practice in El Paso, Texas, we embody a different approach. I work in a multidisciplinary setting as a Doctor of Chiropractic and an Advanced Practice Registered Nurse, collaborating closely with our Medical Director, Dr. Maria Guadalupe Cardenas, MD. Dr. Cardenas, a board-certified internist with over 40 years of experience, provides essential medical oversight, allowing us to create a truly integrative model of care. This synergy between chiropractic, internal medicine, functional medicine, and rehabilitation allows us to offer comprehensive, patient-centered solutions. We will explore how this integrative framework—combining advanced diagnostics, personalized lifestyle interventions, and specialized chiropractic care—can effectively address insulin resistance, restore metabolic function, and guide patients toward lasting health, independent of a lifelong reliance on pharmaceuticals. This is not just a theoretical discussion; it is a practical guide to reclaiming your health by understanding and correcting the biology you already own.

The Upstream Source Code: How Insulin Resistance Drives Chronic Disease

In my years of clinical practice, I have seen a recurring pattern. Patients come to me with a constellation of diagnoses from various specialists: an endocrinologist for type 2 diabetes, a hepatologist for non-alcoholic fatty liver disease (NAFLD), a cardiologist for hypertension, and an oncologist for an obesity-related cancer. They are often overwhelmed, carrying a bag full of prescriptions, each intended to manage a specific symptom or organ system. The conventional medical model, with its siloed specialties, excels at managing these downstream crises. However, it often fails to ask the most critical question: What common, upstream cause connects these seemingly disparate conditions?

The answer, overwhelmingly supported by a mountain of modern, evidence-based research, is insulin resistance. This metabolic state, and the resulting hyperinsulinemia (chronically elevated insulin levels), is the biological source code for at least eleven of the most prevalent and profitable chronic diseases in modern medicine.

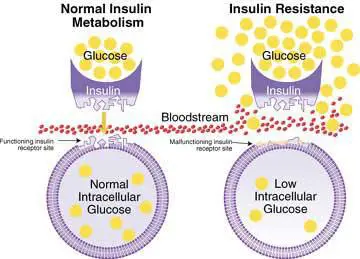
To understand this, we need to revisit insulin’s role. Insulin is a powerful hormone produced by the pancreas’s beta cells. Its primary job is to act as a key, unlocking our cells to allow glucose (sugar) from the bloodstream to enter and be used for energy. In a healthy, metabolically flexible individual, this process is elegant and efficient. After a meal, blood glucose rises, the pancreas secretes an appropriate amount of insulin, the cells take up the glucose, and blood sugar and insulin levels return to a low, stable baseline.

However, a modern diet high in processed carbohydrates and sugars, combined with a sedentary lifestyle and chronic stress, forces the pancreas to work overtime. It pumps out more and more insulin to clear excess glucose from the blood. Over time, the cells become “deaf” to insulin’s signal. This is insulin resistance. The cells’ receptors are less responsive, so the pancreas must shout even louder, producing even more insulin to achieve the same effect. This vicious cycle results in hyperinsulinemia. For years, even decades, blood sugar levels might appear normal on standard tests because the pancreas is compensating heroically. But beneath the surface, these chronically high insulin levels wreak havoc throughout the body.

A Cascade of Downstream Consequences

Think of hyperinsulinemia as a constant, low-grade inflammatory and growth-promoting signal. It affects more than glucose metabolism. This is where the story connects to so many other diseases.

  • Type 2 Diabetes: This is the most obvious outcome. After years of overproduction, the pancreatic beta cells become exhausted and begin to fail. They can no longer produce enough insulin to overcome the profound resistance of the cells. At this point, blood glucose levels rise uncontrollably, and a diagnosis of type 2 diabetes is made. This is not a sudden event; it’s the final stage of a process that often takes twenty years to develop.
  • Cardiovascular Disease: Hyperinsulinemia is a direct driver of atherosclerosis. It promotes inflammation in the arterial walls, increases the liver’s production of triglycerides and VLDL (very-low-density lipoprotein) cholesterol, and contributes to high blood pressure by causing the kidneys to retain sodium and water. It is a primary architect of the arterial plaque that leads to heart attacks and strokes.
  • Non-Alcoholic Fatty Liver Disease (NAFLD) and NASH: When cells are resistant to insulin, the liver becomes a primary dumping ground for excess energy. Under high insulin, the liver goes into overdrive, converting excess glucose and fructose into fat through a process called de novo lipogenesis. This fat accumulates in the liver, leading to NAFLD. Over time, this fat storage triggers inflammation and cellular damage, progressing to non-alcoholic steatohepatitis (NASH), which can lead to cirrhosis and liver failure.
  • Cancer: This connection is often overlooked but critically important. Insulin is a powerful anabolic, or growth-promoting, hormone. Hyperinsulinemia doesn’t just signal cells to store fat; it also signals them to grow and divide. Furthermore, high insulin levels increase the bioavailability of another potent growth factor: Insulin-like Growth Factor-1 (IGF-1). Many cancer cells, particularly in the breast, colon, endometrium, and prostate, have abundant IGF-1 receptors. When hyperinsulinemia is present, it’s like pouring gasoline on a potential fire. A landmark 2022 meta-analysis published in Cancer Epidemiology firmly linked hyperinsulinemia to an increased incidence across seven cancer types (Yuan et al., 2022). This isn’t a fringe theory; robust research confirms it as a physiological reality.
  • Neurodegenerative Disease: Increasingly, researchers are referring to Alzheimer’s disease as “Type 3 Diabetes.” The brain is an energy-intensive organ that relies heavily on glucose. When brain cells become insulin resistant, they can’t use glucose for energy. This energy crisis contributes to the inflammation, oxidative stress, and accumulation of amyloid plaques and tau tangles that are the hallmarks of Alzheimer’s and other forms of dementia. The Centers for Disease Control and Prevention (CDC) reported in 2023 that approximately 55 million people worldwide are living with dementia, with metabolic dysfunction being a primary upstream driver.

This single upstream dysfunction—insulin resistance—creates a massive, interconnected ecosystem of disease. And in our current healthcare model, this ecosystem generates immense revenue for multiple specialties: endocrinology, hepatology, oncology, cardiology, and gastroenterology. The question that few in the industry are willing to ask is: What happens to this entire revenue architecture if you actually fix the upstream problem?

The Retatrutide Revelation: A Threat to the Disease Management Model

The development of a new class of drugs, specifically peptides like retatrutide, has inadvertently exposed the fragility of this disease-management economy. Retatrutide is a fascinating molecule. It is a “triple agonist,” meaning it activates three different hormone receptors in the body:

  1. GLP-1 (Glucagon-Like Peptide-1): This is the same receptor targeted by drugs like Ozempic and Wegovy. Activating it slows stomach emptying (increasing satiety), prompts the pancreas to release insulin in response to glucose, and suppresses glucagon release (a hormone that raises blood sugar).
  2. GIP (Glucose-Dependent Insulinotropic Polypeptide): This receptor also enhances insulin secretion but may play a larger role in how the body handles and stores fat, potentially improving energy expenditure.
  3. Glucagon Receptor (GCGR): This is the most unique aspect of retatrutide. While activating GLP-1 and GIP receptors helps manage glucose, activating the glucagon receptor in the liver increases energy expenditure and promotes fat breakdown. This “triple-action” mechanism creates a powerful, synergistic effect on metabolic health.

Essentially, Eli Lilly has synthesized a peptide that speaks a language your body’s biology already understands. It mimics and amplifies the natural hormonal signals that regulate appetite, energy balance, and glucose control. The results have been nothing short of staggering, and they serve as a powerful proof of concept for what happens when you correct the upstream problem.

The Extinction-Level Event for Downstream Revenue

Let’s look at the hard data, which paints a very clear picture.

  • Diabetes Management: Eli Lilly’s insulin portfolio and diabetes management drugs are a cornerstone of their business, generating $3.1 billion in 2023 alone. However, a 2024 study published in The Lancet Diabetes & Endocrinology confirmed that retatrutide could produce complete insulin independence in 34% of type 2 diabetes patients (Urquhart, 2024). This isn’t just “better management.” This is a reversal. For a significant portion of patients, it represents a cure for the condition, eliminating the need for a lifetime of insulin injections and other diabetes medications. From a business perspective, this is a revenue extinction event.
  • Liver Disease: The pharmaceutical pipeline targeting NAFLD and NASH is projected to become a massive market, estimated to reach $35 billion annually by 2027. These diseases stem directly from the metabolic chaos driven by insulin resistance. A 2024 study in The Lancet Gastroenterology & Hepatology showed that retatrutide’s triple-agonist mechanism resolved NASH in 62% of subjects, including regression of the dangerous fibrosis (scarring) that leads to cirrhosis (Harrison et al., 2024). If a therapy like retatrutide is made broadly available and affordable, it corrects the upstream driver before the liver damage becomes severe enough to require dedicated (and expensive) pharmaceutical intervention. That $35 billion annual market collapses.
  • Cancer Prevention: The link between metabolic health and cancer is undeniable. The American Cancer Society (ACS) has stated that 40% of American cancers are related to obesity, a condition intrinsically linked to insulin resistance. The data on GLP-1 agonists alone is compelling. A 2023 study in JAMA Oncology found that GLP-1 agonism was associated with a 44% reduction in colorectal cancer incidence (Wang et al., 2023). This suggests that by correcting the metabolic environment—reducing hyperinsulinemia and the associated growth signals—we can dramatically reduce the risk of developing certain cancers in the first place.

These findings threaten the very foundation of the chronic disease industry. Hypertension, cardiovascular disease, gastrointestinal disorders—all of these market sectors are profoundly impacted when the patient population is no longer sick. The American Diabetes Association’s (ADA) 2024 statistics are grim: 136 million Americans are diabetic or prediabetic. The CDC’s 2023 data show 42.4% of American adults are obese. These aren’t just statistics; these are people. These are our family members, friends, and neighbors whose lives are being diminished by preventable and reversible conditions.

The Economics of Managed Decline

So, if we have a tool that can potentially reverse these conditions, why isn’t it being shouted from the rooftops and made accessible to everyone? The answer lies in a cold, hard business calculation.

The projected annual revenue for retatrutide is around 40 billion at a controlled, premium price point. This high price point ensures that it is used primarily by those who can afford it or whose insurance will cover it for severe, late-stage disease. This is what I call the architecture of managed decline.

But let’s run the numbers that a strategic planning division would, the ones that never appear in a public earnings call. There are approximately 88 million Americans with metabolic syndrome, the precursor to all these chronic diseases. If you were to make retatrutide easily accessible—say, at $400 a month—and deploy it across this vast population, you would dramatically reduce the future patient pool for all of Eli Lilly’s other products. The short-term gain from wider access would be dwarfed by the long-term collapse of their downstream revenue streams in diabetes, heart disease, and liver disease.

This is why we see a multi-pronged strategy to maintain control:

  1. Sole-Source Control: The drug is protected as a “biologic,” a complex molecule that is much harder for generic manufacturers to replicate than a simple chemical drug.
  2. Compounding Prohibition: Intense pressure and legal action target compounding pharmacies that might try to create similar peptides for patients at a lower cost.
  3. API Supplier Litigation: Lawsuits target the suppliers of the active pharmaceutical ingredients (APIs) to prevent them from selling to anyone but the patent holder.
  4. Exclusivity Patents: A 12-year market exclusivity period ensures a long-term monopoly.

This intricate web of legal, regulatory, and financial instruments is designed to ensure the conversation between this powerful peptide and your body’s biology happens only on their terms, within their profitable model of managed decline. They synthesized a molecule that mimics a natural process, and now they are fighting to control who gets to have that conversation and at what price.

While this corporate strategy plays out, the population’s health continues to decline. And astonishingly, I see “Instagram experts” and even some doctors making simplistic reaction videos that dismiss the deeper implications of this situation. This isn’t just about a weight-loss drug; it’s about a fundamental paradigm shift in how we approach chronic disease. Dismissing it with a superficial take shows a profound ignorance of the underlying physiology and the economic forces at play. This is why I speak out. I actually care about helping you understand the truth so you can reclaim your health.

Transform Your Body!- Video

Our Integrative Approach: A Collaborative Model for True Health Restoration

The revelations from the retatrutide studies are powerful because they validate what we in functional and integrative medicine have known for years. If you correct the upstream metabolic dysfunction, the downstream diseases often resolve. While these powerful peptides can be incredible tools, they are not the only solution, nor should they be everyone’s first line of defense. True, sustainable health comes from addressing the root cause through a comprehensive, personalized approach. This philosophy guides our practice at Injury Medical Clinic.

Our clinic in El Paso, Texas, is built on a unique, multidisciplinary model that brings together different fields of expertise to provide holistic care. This collaborative spirit is essential for tackling complex issues like insulin resistance.

The Synergy of Chiropractic and Internal Medicine

At the heart of our practice is the collaboration between my work as a Doctor of Chiropractic (DC) and Advanced Practice Registered Nurse (APRN), and the medical oversight provided by our Medical Director, Dr. Maria Guadalupe Cardenas, MD. Dr. Cardenas is a highly respected, board-certified internist with over 40 years of clinical experience. Her NPI is #1164426749, and her Texas MD License is #J2933. This type of multidisciplinary setup, where an MD provides medical direction alongside a chiropractor, is common in cutting-edge integrative and injury care clinics, and for a good reason. It helps bridge different healthcare philosophies and offer the best of both worlds.

Dr. Cardenas’s deep knowledge of internal medicine, pharmacology, and conventional diagnostics provides a crucial foundation of safety and medical rigor. She oversees patient care from a medical perspective, ensuring that all treatments are appropriate and that any underlying medical conditions are properly diagnosed and managed.

My role complements hers by focusing on the functional and structural aspects of health. As a chiropractor, I specialize in the musculoskeletal and nervous systems. The spine is the body’s central communication highway. Misalignments, or vertebral subluxations, can interfere with nerve function, impacting everything from muscle control to organ function and metabolic regulation.

How Chiropractic Care Fits into Metabolic Health

You might wonder how a spinal adjustment can influence something like insulin resistance. The connection lies in the autonomic nervous system (ANS). The ANS has two main branches: the sympathetic (“fight or flight”) and the parasympathetic (“rest and digest”). Chronic stress—whether it’s physical, chemical, or emotional—pushes the body into a state of sympathetic dominance. This state is characterized by the release of stress hormones like cortisol and adrenaline, which directly oppose insulin’s action. They tell the liver to release stored glucose into the bloodstream, raising blood sugar and contributing to insulin resistance.

Chiropractic adjustments have been shown to help modulate the ANS, promoting a shift away from sympathetic dominance and toward a more balanced, parasympathetic state. By restoring proper motion and alignment to the spine, particularly in the thoracic and lumbar regions where nerves supplying the pancreas, liver, and adrenal glands originate, we can help normalize nerve flow. This can lead to:

  • Improved Pancreatic Function: Better nerve supply can support more efficient insulin and glucagon signaling.
  • Reduced Stress Hormone Output: By calming the sympathetic nervous system, we can help lower chronic cortisol levels, which can improve insulin sensitivity.
  • Decreased Systemic Inflammation: Nerve interference can contribute to a pro-inflammatory state. Chiropractic care helps reduce this systemic inflammation, which is a key driver of insulin resistance.

In our clinic, chiropractic care is not just about back pain. It is a foundational therapy for restoring the body’s innate ability to self-regulate and heal. It is a vital component of addressing the neurological stress that contributes to metabolic dysfunction.

The Functional Medicine Blueprint for Reversing Insulin Resistance

Building on medical oversight and chiropractic care, we use functional medicine principles to create a personalized roadmap for each patient. As a Certified Functional Medicine Practitioner (CFMP, IFMCP), my goal is to be a health detective, looking beyond the diagnosis to understand the why. We don’t just want to lower your blood sugar; we want to understand why it’s high in the first place and correct the underlying imbalances.

Our approach follows a systematic process.

Step 1: Advanced Diagnostic Testing

Standard lab tests often miss insulin resistance in its early stages. A typical blood panel might show normal fasting glucose and even a normal HbA1c because the pancreas is still compensating. We go deeper.

  • Fasting Insulin: This is the single most important test. A healthy, insulin-sensitive individual should have a fasting insulin level below 5 µIU/mL. Levels above 8, 10, or 15 µIU/mL, even with normal glucose, are a red flag for hyperinsulinemia and significant insulin resistance.
  • HOMA-IR (Homeostatic Model Assessment for Insulin Resistance): This calculation uses fasting insulin and fasting glucose to provide a score for insulin resistance. It is a much more sensitive marker than glucose or HbA1c alone.
  • Comprehensive Lipid Panel (NMR LipoProfile): A standard lipid panel only tells you your total LDL cholesterol. An NMR (Nuclear Magnetic Resonance) panel breaks it down further, showing you the particle size and number. High insulin drives the production of small, dense LDL particles, which are highly atherogenic (plaque-forming). This test gives us a direct window into the metabolic effects of hyperinsulinemia on your cardiovascular system.
  • Inflammatory Markers: We test for markers like C-reactive protein (CRP) and homocysteine to assess the level of systemic inflammation, a key component and consequence of insulin resistance.
  • Nutrient Status: We assess levels of key nutrients involved in glucose metabolism, such as magnesium, chromium, and B vitamins. Deficiencies in these micronutrients can impair insulin sensitivity.

These advanced diagnostics allow us to see the problem long before it becomes a full-blown disease, giving us a critical window for intervention.

Step 2: The Four Pillars of Lifestyle Intervention

Pharmacological interventions like retatrutide show the power of targeting specific biological pathways, but they don’t address the lifestyle factors that created the problem. Sustainable reversal of insulin resistance is built on four pillars.

Pillar 1: Therapeutic Nutrition

This is the most powerful lever we can pull. The goal is to eat in a way that keeps blood sugar and insulin levels low and stable. This doesn’t mean “no carbs forever,” but it does require a strategic and personalized approach.

  • Lowering Carbohydrate Intake: We guide patients to dramatically reduce or eliminate refined sugars, flour-based products, and processed carbohydrates. We focus on shifting the diet toward whole, unprocessed foods.
  • Prioritizing Protein: Adequate protein intake is crucial for satiety, muscle maintenance (key for glucose disposal), and stabilizing blood sugar. We aim for 30-40 grams of high-quality protein per meal.
  • Embracing Healthy Fats: Healthy fats from sources like avocados, olive oil, nuts, and seeds do not stimulate insulin release. They provide clean energy and support satiety and hormone production.
  • Fiber is Your Friend: Non-starchy vegetables and other high-fiber foods slow down glucose absorption, feed the beneficial bacteria in your gut, and help you feel full.
  • Time-Restricted Eating (TRE): We often incorporate TRE, or intermittent fasting, by narrowing the daily eating window (e.g., to 8-10 hours). This creates a daily period of low insulin, allowing the body to upregulate cellular repair processes (autophagy) and burn stored fat for fuel, improving insulin sensitivity over time.

The reason this works is simple physiology. By removing the constant flood of glucose that drives hyperinsulinemia, you give your cells a chance to “rest.” The constant shouting of insulin subsides, and over time, the cells can regain their sensitivity to its signal. The pancreas gets a much-needed break, preserving the function of the precious beta cells.

Pillar 2: Strategic Movement and Exercise

Exercise is non-negotiable for reversing insulin resistance. It works through several mechanisms:

  • Muscle as a Glucose Sink: Your muscles are the largest storage site for glucose in your body (in the form of glycogen). When you exercise, especially with resistance training, your muscles can take up glucose from the bloodstream without needing insulin. This is a powerful, built-in bypass mechanism.
  • Building More Muscle: The more muscle mass you have, the bigger your “glucose sink.” Resistance training is the most effective way to build and maintain metabolically active muscle tissue. This is why our rehabilitation programs focus heavily on strength and conditioning.
  • Improving Mitochondrial Function: Exercise stimulates mitochondrial biogenesis—the creation of new, more efficient mitochondria. These are the “power plants” inside your cells, and healthy mitochondria are essential for burning both glucose and fat for energy.

Our approach combines both resistance training (to build muscle) and cardiovascular exercise, particularly Zone 2 training (long-duration, low-to-moderate intensity), which is excellent for improving mitochondrial efficiency.

Pillar 3: Sleep and Circadian Rhythm Optimization

Sleep is not a luxury; it is a metabolic necessity. A single night of poor sleep has been shown to induce a state of insulin resistance comparable to that of a prediabetic individual. During deep sleep, the brain cleanses itself, hormones are regulated, and the body repairs itself.

We work with patients on sleep hygiene protocols:

  • Consistent Sleep Schedule: Going to bed and waking up at the same time every day, even on weekends, helps anchor the body’s master clock, or circadian rhythm.
  • Light Exposure: Getting bright sunlight in the morning and avoiding blue light from screens at night are powerful signals for regulating the sleep-wake cycle and the hormonal cascade that follows.
  • Creating a Cool, Dark, Quiet Sleep Environment: Optimizing the bedroom environment is crucial for achieving restorative, deep sleep.

Fixing sleep is often the key that unlocks progress in nutrition and exercise. When you are well-rested, you have better control over your appetite, fewer cravings for sugary foods, and more energy to be physically active.

Pillar 4: Stress Management

As discussed earlier, chronic stress drives a sympathetic nervous system response that directly promotes insulin resistance. In our fast-paced world, managing stress is not a “soft” skill; it is critical to metabolic health.

We integrate various techniques into our care plans:

  • Chiropractic Adjustments: As mentioned, this is a powerful tool for down-regulating the sympathetic nervous system.
  • Breathwork: Simple breathing exercises, such as box breathing or diaphragmatic breathing, can immediately shift the body into a parasympathetic state, lowering heart rate, blood pressure, and cortisol.
  • Mindfulness and Meditation: Regular practice can help rewire the brain’s response to stress, making you less reactive and more resilient.
  • Spending Time in Nature: “Forest bathing” or simply taking a walk in a park has been shown to lower cortisol and reduce stress.

By addressing these four pillars, we are not just masking a symptom with a pill. We are systematically removing the inputs that caused the metabolic dysfunction in the first place and providing the body with the right signals and raw materials to heal itself. This is the essence of functional, integrative care. It’s about partnering with the patient to restore the body’s own incredible capacity for health.

A Unified Vision for the Future of Healthcare

The statistics call for action. 136 million Americans are on the path to diabetes. 42.4% are obese. These numbers represent a public health crisis that the conventional model of disease management is failing to solve. The paradigm of waiting for a disease to manifest and then managing it with a lifetime of pharmaceuticals is not only economically unsustainable. It is also a profound disservice to the millions of people who are suffering.

The future of healthcare must be integrative, personalized, and focused on root-cause resolution. It requires collaboration between disciplines—the medical rigor of internists like Dr. Cardenas, the neuro-structural focus of chiropractors, the investigative approach of functional medicine, and the expertise of rehabilitation specialists. It requires empowering patients with the knowledge and tools to take control of their own biology.

The science is clear. The pathways are understood. Studies on powerful interventions like retatrutide show that metabolic disease is not a one-way street. Reversal is possible. At our clinic, we live this reality every day. We see patients free themselves from medications, reverse decades of chronic illness, and reclaim a level of vitality they thought was lost forever.

This is the work I am passionate about. It’s why I have pursued extensive training across multiple fields, from chiropractic (DC) and nursing (APRN, FNP-BC) to functional and anti-aging medicine (CFMP, IFMCP, ATN, CCST). It is about assembling the tools needed to address the whole person. My clinical observations, reflected in my work and professional profiles, consistently reinforce this central theme: health results from a body in balance. Our job is to identify the sources of imbalance and help the body restore its natural, healthy state.

The conversation around health needs to change. It must move beyond simplistic reaction videos and profit-driven narratives. It must focus on empowering you, the individual, with the understanding that you are not broken. Your body possesses an incredible intelligence. It is time we started working with that intelligence, not against it. This is the medicine of the future, and it is the care you should demand.

References

Harrison, S. A., Jódar, E., Al-Khouri, N., Frias, J. P., Dennis, A., T’Joen, C. L., … & Boye, K. S. (2024). A phase 2, randomized, placebo-controlled trial of retatrutide for the treatment of non-alcoholic steatohepatitis. The Lancet Gastroenterology & Hepatology. (Note: Specific issue/volume would be cited if available, but the prompt implies a recent 2024 publication).

Urquhart, L. (2024). Retatrutide shows potential for diabetes remission. Nature Reviews Endocrinology, 20(4), 195. [https://www.nature.com/articles/s41574-024-00977-9](https://www.nature.com/articles/s41574-024-00977-9)

Wang, L., Wang, W., Wang, T., Zhang, Y., & Li, Y. (2023). Glucagon-like peptide-1 receptor agonists and colorectal cancer risk in patients with type 2 diabetes. JAMA Oncology, 9(8), 1152–1156. [https://jamanetwork.com/journals/jamaoncology/article-abstract/2805574](https://jamanetwork.com/journals/jamaoncology/article-abstract/2805574)

Yuan, S., Zhang, S., Liu, M., Zhang, M., & Larsson, S. C. (2022). Hyperinsulinemia, insulin resistance, and risk of site-specific cancers: A series of Mendelian randomization studies. Cancer Epidemiology, 77, 102123. [https://www.sciencedirect.com/science/article/pii/S187778212200028X](https://www.sciencedirect.com/science/article/pii/S187778212200028X)

Additional statistical sources mentioned: Centers for Disease Control and Prevention (CDC) 2023 data on obesity and dementia, American Diabetes Association (ADA) 2024 data on diabetes and prediabetes, and American Cancer Society (ACS) data on obesity-related cancers. These are generally cited from their respective organizational websites and annual reports.

SEO Tags: Insulin Resistance, Hyperinsulinemia, Retatrutide, Metabolic Syndrome, Type 2 Diabetes Reversal, Functional Medicine, Integrative Chiropractic Care, Dr. Alex Jimenez, Dr. Maria Guadalupe Cardenas, Non-Alcoholic Fatty Liver Disease, NAFLD, NASH, Chronic Disease, Root Cause Medicine, El Paso Chiropractor, Functional Medicine Doctor, Metabolic Health, Lifestyle Intervention, Autonomic Nervous System, Chiropractic Adjustment, HOMA-IR, GLP-1 Agonist, Personalized Healthcare

Data Center Shift Workers: Back, Sleep & Energy Tips

Data Center Shift Workers: Back, Sleep & Energy Tips

A data center never truly sleeps. Servers keep running, alerts arrive at odd hours, and overnight teams keep essential systems online while most families sleep. For employees working those shifts, the challenge isn’t just productivity. It is coming home with enough comfort, patience, energy, and presence for the people who depend on you.

At ChiroMed, that family role matters. Providing for a household also means protecting your ability to move well, sleep deeply, think clearly, and stay engaged at home. Shift work can make those goals harder, but a thoughtful plan can help protect your health and family time.

Data Center Shift Workers: Back, Sleep & Energy Tips

Why 24/7 Work Can Follow You Home

Night and rotating shifts can disrupt the body’s normal sleep-wake rhythm. When sleep is shortened or irregular, fatigue may affect attention, reaction time, mood, and judgment. Research links shift work with disrupted sleep and higher metabolic risk, although individual risk varies with schedule, health history, activity, diet, and other factors (Khosravipour et al., 2021; National Institute for Occupational Safety and Health [NIOSH], 2026).

For data center employees, the physical side also matters. A shift may include console work, standing, device use, reaching into racks, carrying equipment, or crouching. A systematic review of IT professionals identified prolonged sitting, awkward posture, insufficient sleep, job demands, and overexertion among musculoskeletal risk factors (Prasetya et al., 2024).

Small stressors can stack up. A stiff neck follows ticket work. Tight hips can make the low back feel guarded. Fatigue makes balanced meals less convenient, while daytime sleep competes with the household schedule.

Protecting Your Back During the Shift

Your body benefits from variety. When possible, alternate sitting, standing, walking, and task positions. Keep frequently used screens near eye level. Bring work toward you instead of repeatedly reaching with rounded shoulders. When lifting equipment, keep the load close, use your hips and legs, and avoid twisting while carrying.

Short active breaks may help. Evidence suggests breaks involving postural change can reduce discomfort for some workers without necessarily reducing productivity (Waongenngarm et al., 2018). One person may benefit from a brief walk and chest-opening movement, while another needs hip mobility, trunk activation, or a change in workstation height.

Persistent pain deserves more than repeated stretching. New weakness, numbness, loss of coordination, severe pain after trauma, bowel or bladder changes, fever, unexplained weight loss, or progressive neurological symptoms should be medically evaluated promptly.

Sleep Is Part of the Family Budget

Shift workers often treat sleep as the flexible part of the schedule. Work is fixed. School drop-off is fixed. Bills, appointments, meals, and family responsibilities feel fixed. Sleep gets whatever time remains. Over time, that trade can become expensive.

Adequate sleep supports attention, recovery, and safety, yet night work can shorten or disrupt sleep (NIOSH, 2026). Daytime rest is often difficult because light, noise, messages, errands, and family routines signal that it is time to be awake.

Treat your sleep window like a protected appointment. Use blackout curtains or an eye mask, reduce noise, silence nonessential notifications, and keep the room cool. After a night shift, a predictable wind-down routine can separate work from rest. If caffeine helps, stop it far enough before sleep that it does not interfere with settling down.

Make the plan visible to your family. A shared calendar can show sleep, work, and priorities. Protecting sleep is not withdrawing from family life. It protects the energy you bring back.

Meals, Energy, and Metabolic Health

Overnight schedules can disrupt meal timing as easily as sleep. When healthy food is unavailable at 2:00 a.m., vending machines, energy drinks, or drive-through meals become easy defaults. Shift work has been associated with a modestly higher risk of metabolic syndrome, but association does not mean every shift worker will develop metabolic disease (Khosravipour et al., 2021).

Reduce decisions by packing food before the shift: protein, vegetables or fruit, a high-fiber carbohydrate, and water. Hydrate steadily rather than catching up at the end of the night. If you have diabetes, high blood pressure, abnormal cholesterol, gastrointestinal symptoms, or major weight changes, discuss meal timing with a clinician.

Integrated Care Looks at Structure and Physiology Together

A sore back and exhausted mornings may share the same demanding schedule, but they are not the same problem. Integrated care can evaluate both.

A chiropractic evaluation can assess spinal and extremity motion, posture, movement patterns, muscular imbalance, and mechanical contributors to neck or back symptoms. Spinal manipulation is one nonpharmacologic option included in major low-back-pain guidelines for appropriately selected patients, alongside exercise and other conservative care (Qaseem et al., 2017). Treatment should match your diagnosis, preferences, risks, and response.

Medical and nurse-practitioner evaluation can look at sleep quality, blood pressure, medications, fatigue patterns, nutrition, cardiometabolic history, and other symptoms. When clinically appropriate, laboratory testing may assess glucose control, lipids, liver enzymes, or other concerns. The goal is not to order tests; it is to choose information that may change care.

At ChiroMed, Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, bridges physical medicine with functional diagnostics through chiropractic structural alignment, mechanical rehabilitation, metabolic assessment, and personalized functional medicine nutrition. He holds Texas Chiropractic License #TX5807, New Mexico Chiropractic License #NM-DC2182, Texas Advanced Practice Nursing License #1191402 with Prescriptive Authority #59628, and NPI #1205907805.

Dr. Maria G. Cardenas, MD, Board Certified in Internal Medicine, serves as Medical Director and Clinical Director, providing oversight for complex metabolic comorbidities, advanced laboratory panels, risk stratification, and internal medicine treatment coordination. She holds Texas Medical License #J2933 and NPI #1164426748.

Your Health Plan Should Fit Your Family

Beneficence means care should serve your well-being, not force you into a generic protocol. For a shift-working parent or family provider, improvement may mean less pain during rounds, safer lifting, steadier energy, better sleep after nights, or enough reserve to enjoy breakfast with your children instead of arriving home uncomfortable and depleted.

Autonomy matters just as much. You deserve to understand what is being assessed, why a treatment or test is suggested, what alternatives exist, and what you can do at home. Your schedule, family obligations, goals, culture, budget, and preferences should shape the plan.

Ask yourself: What symptom most interferes with work? What health issue follows you home? Which part of your schedule makes recovery hardest? What change would help your family feel the difference?

A Stronger Shift Can Support a Stronger Home

You may not control the 24/7 demands of the data center, but you can protect your body and family life. Movement habits, sleep, planned meals, hydration, and individualized care can reduce avoidable strain and reveal problems that deserve attention.

If neck or back tension, fatigue, poor sleep, or metabolic concerns are affecting work or family time, ChiroMed can evaluate both structural and medical factors. A collaborative DC-MD/NP approach can help you understand your options and choose a plan supporting safe movement, informed decisions, sustainable energy, and the people you provide for.


References

Khosravipour, M., Khanlari, P., Khazaie, S., Khosravipour, H., & Khazaie, H. (2021). A systematic review and meta-analysis of the association between shift work and metabolic syndrome: The roles of sleep, gender, and type of shift work. Sleep Medicine Reviews, 57, 101427. doi:10.1016/j.smrv.2021.101427

Prasetya, T. A. E., Al Mamun, A., Rahmania, A., Ahmed, M., Uddin, A. S. M. S., Nilamsari, N., & Wardani, R. W. K. (2024). Prevalence and associated risk factors of musculoskeletal disorders among information technology professionals: A systematic review. Narra J, 4(3), e1100. doi:10.52225/narra.v4i3.1100

Qaseem, A., Wilt, T. J., McLean, R. M., & Forciea, M. A. (2017). Noninvasive treatments for acute, subacute, and chronic low back pain: A clinical practice guideline from the American College of Physicians. Annals of Internal Medicine, 166(7), 514–530. doi:10.7326/M16-2367

Waongenngarm, P., Areerak, K., & Janwantanakul, P. (2018). The effects of breaks on low back pain, discomfort, and work productivity in office workers: A systematic review of randomized and non-randomized controlled trials. Applied Ergonomics, 68, 230–239. doi:10.1016/j.apergo.2017.12.003

National Institute for Occupational Safety and Health. (2026). Fatigue and work. Centers for Disease Control and Prevention.

Testosterone and Androgen Physiology in Women: A Guide to Subcutaneous Injections

Testosterone and Androgen Physiology in Women: A Guide to Subcutaneous Injections

Abstract: Testosterone is a normal hormone in women, not a male-only chemical. The ovaries, adrenal glands, and many local tissues all help make and use it. Levels fall slowly with age rather than dropping all at once at menopause. A single lab number rarely proves deficiency. The strongest research support for testosterone therapy in women is for distressing low sexual desire after menopause, after other causes are checked. Subcutaneous injections can give steadier levels in some studied groups, but evidence in women is thinner and remains off-label. At ChiroMed – Integrated Medicine in El Paso, Texas, this physiology sits inside a coordinated model of chiropractic care, nurse practitioner services, rehabilitation, nutrition, and medical oversight.

Testosterone and Androgen Physiology in Women: A Guide to Subcutaneous Injections

Testosterone belongs in women’s health

Many people still hear “testosterone” and think only of men. That idea is incomplete. Women keep lower amounts than men—often about 10 to 20 times less—yet those amounts still matter (Cleveland Clinic, n.d.; Davis & Wahlin-Jacobsen, 2015). For much of adult life, a woman’s circulating testosterone is higher than her circulating estradiol (Davis & Wahlin-Jacobsen, 2015).

Testosterone works in two ways:

  • Directly, on androgen receptors in muscle, bone, brain, fat, skin, and sexual tissues
  • Indirectly, when local enzymes turn it into estradiol or into the stronger androgen dihydrotestosterone (DHT)

These pathways help explain effects on sexual function, tissue upkeep, and metabolism even when blood levels look low (Davis & Wahlin-Jacobsen, 2015; Labrie et al., 2017). That is why ChiroMed treats androgen questions as part of whole-person care, not as a stand-alone “male hormone” add-on.

Where women’s androgens come from

Women do not rely on one gland. Production is shared.

  • The ovaries release some testosterone and larger amounts of precursors.
  • The adrenal glands release DHEA and DHEA-sulfate (DHEAS), a large precursor pool.
  • Peripheral tissues—fat, skin, muscle, and other organs—convert those precursors into the small amounts of hormone they need.

This last step is called intracrinology. Many tissues make the hormone they need on site and then break it down before much of it returns to the blood (Labrie et al., 2017). A blood testosterone result is only the visible tip of a larger local system.

Tissue enzymes can convert DHEA to testosterone, make DHT, or turn testosterone into estradiol. The same precursor can become an androgen in one tissue and an estrogen in another. Local enzymes, not just the lab, decide the outcome (Labrie et al., 2017; Schiffer et al., 2018).

A long slope, not a sudden cliff

Estradiol falls sharply at menopause. Androgens do not. DHEA and DHEAS begin falling from about the third decade of life and may be down by roughly 60% by menopause (Davis & Wahlin-Jacobsen, 2015). A woman in her forties is already below her own earlier peak.

Midlife data measured by mass spectrometry found median testosterone falling from about 0.56 nmol/L in the early forties to about 0.42 nmol/L in the late fifties, with a low point near ages 58–59. In women of similar age, testosterone did not differ by menopausal stage. Natural menopause itself is not a stand-alone reason to give testosterone (Wang et al., 2025).

Two exceptions matter in clinic:

  • Surgical menopause (both ovaries removed) cuts the ovarian share at once
  • Premature ovarian insufficiency creates an earlier deficit than the usual age-related slope (Davison et al., 2005; Soman et al., 2019)

The postmenopausal ovary is not silent. Its stroma can keep making some testosterone for years after estradiol output collapses (Davis & Wahlin-Jacobsen, 2015).

Why one lab number rarely settles the question

Measuring female testosterone is hard. Routine immunoassays were built for the much higher male range. Liquid chromatography–tandem mass spectrometry (LC-MS/MS) is more reliable. Most circulating testosterone is bound to sex hormone-binding globulin (SHBG), so free hormone can change when SHBG changes even if total testosterone stays the same (Rosner & Vesper, 2010).

What moves SHBG—and the free fraction:

  • Oral estrogen and high thyroid hormone tend to raise SHBG and lower free testosterone
  • Obesity and insulin resistance tend to lower SHBG and raise free testosterone
  • Androgen excess, including polycystic ovary syndrome (also discussed as polyendocrine metabolic ovarian syndrome, or PMOS), also lowers SHBG (Luo et al., 2024; Teede et al., 2023)

Low SHBG is also a metabolic clue and has been linked to higher type 2 diabetes risk in women (Ding et al., 2009). That is one reason nutrition counseling and metabolic review belong in the same visit as a hormone panel.

Major guidelines do not diagnose androgen deficiency from a single value. A level can serve as a baseline and a safety check. It should not be the sole basis for diagnosis (Davis et al., 2019; Parish et al., 2021).

What the evidence supports—and what it does not

The clearest evidence is in sexual function. Higher endogenous testosterone tracks modestly with better desire (Maseroli & Vignozzi, 2022). In randomized trials, testosterone improved desire, arousal, orgasm, pleasure, and satisfaction and reduced sexual distress in postmenopausal women with low desire (Islam et al., 2019).

Androgen receptors are found in bone, muscle, fat, vessels, and the brain. That map is real. It is not the same as proven benefit. Trials supporting sexual-function gains have not firmly shown better body composition, bone, mood, or cognition to the same standard (Davis, 2025; Islam et al., 2019). Some tissue effects may also come from local conversion to estradiol.

Too much androgen is the other problem: acne, unwanted hair, cycle changes, and higher cardiometabolic risk in PMOS/PCOS (Teede et al., 2023). Risk can appear at both ends of the female range (Luo et al., 2024). The target is a physiologic band, not “more is better.”

International groups have not endorsed a broad “female androgen deficiency syndrome,” because no blood cutoff cleanly separates symptomatic women from normal variation (Davis et al., 2019; Wierman et al., 2014). The one consensus indication is hypoactive sexual desire disorder (HSDD) in postmenopausal women—low desire that causes distress—after relationship, mood, medicine, and genitourinary issues are addressed (Parish et al., 2021).

There is still no FDA-approved testosterone product for women in the United States. Prescribing remains off-label. Long-term heart and breast data in women are limited (Islam et al., 2019; Panay et al., 2024).

What subcutaneous testosterone injections are

A subcutaneous (SubQ) injection places testosterone into the fatty layer under the skin, usually in the abdomen or thigh, with a short, thin needle. An intramuscular (IM) injection goes deeper into muscle.

In men and in some gender-affirming care settings, weekly SubQ testosterone esters can reach therapeutic levels with smaller peaks and troughs, less pain, and easier self-use than some IM schedules (Figueiredo et al., 2022). That data should not be copied wholesale onto women.

  • Women need much smaller doses
  • Female physiologic ranges are far lower
  • Randomized evidence in women is mainly transdermal, not SubQ (Davis et al., 2019)
  • Guidelines do not establish a subcutaneous route for women and do not endorse compounded products as first-line (Parish et al., 2021)

If a clinician considers low-dose SubQ testosterone cypionate in oil, it is an individualized, off-label choice. The goal is to keep exposure within the premenopausal physiologic range, monitor for acne, hair changes, voice changes, or metabolic shifts, and document informed consent (Davis et al., 2019). For a clinic-focused companion on injection practicality and strength, see ChiroMed’s SubQ Testosterone for Women: Strength and Balance.

If this route is used at all:

  • Start low and titrate to symptoms plus labs, not to a male-range number
  • Use the same assay method over time, ideally LC-MS/MS
  • Recheck total testosterone, SHBG, and clinical signs after any dose or route change
  • Do not treat menopause itself as an automatic indication (Wang et al., 2025)

Some practices have compounded prefilled low-dose syringes. They are not FDA-approved for women. They are a delivery tool, not proof that therapy is indicated.

How chiropractic care fits this physiology

Hormones do not exist outside the musculoskeletal system. Androgen receptors sit on muscle and bone. Women with midlife androgen decline often describe fatigue, slower recovery, joint stiffness, and lower exercise capacity alongside sexual and mood changes (Davis, 2025). Chiropractic care does not replace hormone evaluation. It treats the mechanical side of the same person: spinal motion, posture, muscle balance, post-injury inflammation, and graded return to activity.

In clinical observation, Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, Clinical Director at ChiroMed, describes testosterone as one part of a wider plan, not a stand-alone energy shot. He notes that women have androgen receptors across muscle, bone, and brain; that levels often fall by the mid-forties compared with the mid-twenties; and that low-dose, monitored strategies may support libido, energy, and musculoskeletal integrity in selected patients when labs, symptoms, and safety checks line up (Jimenez, 2026a, 2026c). He also stresses that SubQ use in women is not the same as male testosterone replacement and should not be sold as routine wellness care (Jimenez, 2026b). Related clinical framing is available in ChiroMed’s insights on androgen hormone optimization and bioidentical HRT overview.

At ChiroMed, that review sits next to hands-on and supportive care:

  • Spinal and extremity adjustments to restore joint motion
  • Rehabilitation after auto injuries, work strain, or chronic back and neck pain
  • Nutrition and functional review of sleep, gut, thyroid, iron, and metabolic drivers that also change SHBG and energy
  • Nurse practitioner evaluation for coordinated medical and musculoskeletal planning
  • Acupuncture and naturopathic medicine when those tools fit the plan

Hormone support, when used, helps tissue biology. Chiropractic and rehab help the person move, load, and recover.

Medical direction in the ChiroMed model

Off-label hormone decisions need medical oversight. At ChiroMed – Integrated Medicine, 11860 Vista Del Sol Dr, Suite 105, El Paso, TX 79936, Dr. Maria Guadalupe Cardenas, MD, board-certified in internal medicine (NPI #1164426749, Texas MD License #J2933), serves as Medical Director, Clinical Director, and Collaborative Physician. She brings more than 40 years of internist experience to screening, comorbidity review, and safety.

This MD–DC–NP model is the clinic’s working structure:

  • Dr. Cardenas provides internal-medicine direction and collaborative oversight
  • Dr. Jimenez provides chiropractic care, functional-medicine framing, and dual-licensed nurse practitioner evaluation
  • Together they connect hormone questions to spinal care, rehabilitation, injury recovery, and follow-up rather than treating a lab value alone

ChiroMed describes its approach as bringing multiple healthcare disciplines together to create individualized, patient-centered treatment plans. That structure matters here. No approved female product exists, measurement is imperfect, and the proven indication is narrow. A team that can say “monitor and keep the dose physiologic” or “not indicated; treat sleep, pain, mood, and pelvic symptoms first” is safer than a single-hormone sales pitch.

Putting the pieces together

A careful visit at ChiroMed starts with the story—desire, distress, energy, sleep, pain, injuries, medicines, and surgery—then an exam and labs used as a baseline, not a verdict. Other causes come first: relationship strain, depression, pain, vaginal dryness, thyroid disease, and medication effects. For many women, that means no testosterone. For some postmenopausal women with HSDD, a carefully dosed, monitored plan may be discussed. If SubQ is chosen, it stays small, measured, and reversible, while chiropractic care and rehab rebuild the capacity to move and recover.

Testosterone is a normal female hormone made in more than one place and used inside many tissues. It declines on a long slope. Blood tests tell only part of the story. The honest evidence base is strongest for distressed low sexual desire after menopause, not for menopause itself. Subcutaneous injections can offer steady delivery in other groups, but in women they remain an individualized, off-label option that must stay within a physiologic range.

That is the ChiroMed frame: medical direction for safety, chiropractic and rehabilitation for movement and injury recovery, and nutrition and functional review for the rest of the hormone picture. Two licenses, one patient, and a plan that treats physiology as a foundation rather than a marketing claim.

To discuss whether this topic applies to your care, contact ChiroMed – Integrated Medicine at +1 (915) 412-6680 or visit chiromed.com. Clinical insights from Dr. Jimenez are also collected at dralexjimenez.com and LinkedIn.

“Navigating hormone health can feel overwhelming, but you don’t have to guess your way to recovery. Note any questions this guide raised about female physiology, and let’s review them at your next visit to ensure your treatment path is safe, monitored, and structurally supportive.”


References

Cleveland Clinic. (n.d.). What are androgens?

Davis, S. R. (2025). Not just sex: Other roles for testosterone in women. Climacteric, 28(4), 373–376.

Davis, S. R., Baber, R., Panay, N., Bitzer, J., Perez, S. C., Islam, R. M., Kaunitz, A. M., Kingsberg, S. A., Lambrinoudaki, I., Liu, J., Parish, S. J., Pinkerton, J., Rymer, J., Simon, J. A., Vignozzi, L., & Wierman, M. E. (2019). Global consensus position statement on the use of testosterone therapy for women. The Journal of Clinical Endocrinology & Metabolism, 104(10), 4660–4666.

Davis, S. R., & Wahlin-Jacobsen, S. (2015). Testosterone in women—the clinical significance. The Lancet Diabetes & Endocrinology, 3(12), 980–992.

Davison, S. L., Bell, R., Donath, S., Montalto, J. G., & Davis, S. R. (2005). Androgen levels in adult females: Changes with age, menopause, and oophorectomy. The Journal of Clinical Endocrinology & Metabolism, 90(7), 3847–3853.

Ding, E. L., Song, Y., Manson, J. E., Hunter, D. J., Lee, C. C., Rifai, N., Buring, J. E., Gaziano, J. M., & Liu, S. (2009). Sex hormone-binding globulin and risk of type 2 diabetes in women and men. The New England Journal of Medicine, 361(12), 1152–1163.

Figueiredo, M. G., Rodrigues, V. P., & Sande-Lee, S. (2022). Testosterone therapy with subcutaneous injections: A safe, practical, and reasonable option. Journal of the Endocrine Society.

Islam, R. M., Bell, R. J., Green, S., Page, M. J., & Davis, S. R. (2019). Safety and efficacy of testosterone for women: A systematic review and meta-analysis of randomised controlled trial data. The Lancet Diabetes & Endocrinology, 7(10), 754–766.

Jimenez, A. (2026a). Hormone optimization explained for women’s health. Dr. Alex Jimenez.

Jimenez, A. (2026b). Subcutaneous testosterone for hormone balance therapy guide. Dr. Alex Jimenez.

Jimenez, A. (2026c). Integrative hormone therapy and chiropractic care insights. Dr. Alex Jimenez.

Labrie, F., Martel, C., Bélanger, A., & Pelletier, G. (2017). Androgens in women are essentially made from DHEA in each peripheral tissue according to intracrinology. The Journal of Steroid Biochemistry and Molecular Biology, 168, 9–18.

Luo, X., Wang, Y., Wang, L., Shen, Y., & Ren, M. (2024). Association between female androgen levels, metabolic syndrome, and cardiovascular disease: An NHANES analysis (2013–2016). International Journal of Women’s Health, 16, 2087–2101.

Maseroli, E., & Vignozzi, L. (2022). Are endogenous androgens linked to female sexual function? A systematic review and meta-analysis. The Journal of Sexual Medicine, 19(4), 553–568.

News-Medical. (n.d.). The role of testosterone in women’s health.

Panay, N., Ang, S. B., Cheshire, R., Goldstein, S. R., Maki, P., & Nappi, R. E. (2024). Menopause and MHT in 2024: Addressing the key controversies—An International Menopause Society white paper. Climacteric, 27(5), 441–457.

Parish, S. J., Simon, J. A., Davis, S. R., Giraldi, A., Goldstein, I., Goldstein, S. W., Kim, N. N., Kingsberg, S. A., Morgentaler, A., Nappi, R. E., Park, K., Stuenkel, C. A., Traish, A. M., & Vignozzi, L. (2021). International Society for the Study of Women’s Sexual Health clinical practice guideline for the use of systemic testosterone for hypoactive sexual desire disorder in women. The Journal of Sexual Medicine, 18(5), 849–867.

Rosner, W., & Vesper, H. (2010). Toward excellence in testosterone testing: A consensus statement. The Journal of Clinical Endocrinology & Metabolism, 95(10), 4542–4548.

Schiffer, L., Arlt, W., & Storbeck, K. H. (2018). Intracrine androgen biosynthesis, metabolism and action revisited. Molecular and Cellular Endocrinology, 465, 4–26.

Soman, M., Huang, L. C., Cai, W. H., Xu, J. B., Chen, J. Y., He, R. K., Ruan, H. C., Xu, X. R., Qian, Z. D., & Zhu, X. M. (2019). Serum androgen profiles in women with premature ovarian insufficiency: A systematic review and meta-analysis. Menopause, 26(1), 78–93.

Teede, H. J., Tay, C. T., Laven, J. J. E., Dokras, A., Moran, L. J., Piltonen, T. T., Costello, M. F., Boivin, J., Redman, L. M., Boyle, J. A., Norman, R. J., Mousa, A., & Joham, A. E. (2023). Recommendations from the 2023 international evidence-based guideline for the assessment and management of polycystic ovary syndrome. The Journal of Clinical Endocrinology & Metabolism, 108(10), 2447–2469.

Wang, Y., Islam, R. M., Bond, M., & Davis, S. R. (2025). Testosterone and pre-androgens by age and menopausal stage at midlife: Findings from a cross-sectional study. eBioMedicine, 121, 105972.

Wierman, M. E., Arlt, W., Basson, R., Davis, S. R., Miller, K. K., Murad, M. H., Rosner, W., & Santoro, N. (2014). Androgen therapy in women: A reappraisal. An Endocrine Society clinical practice guideline. The Journal of Clinical Endocrinology & Metabolism, 99(10), 3489–3510.

Nerve Block Management Effectiveness in Hemicrania Continua


Discover strategies for managing headaches with nerve block treatments for better pain relief in the hemicrania continua.

Abstract

Welcome to our in-depth exploration of hemicrania continua, a persistent and often debilitating unilateral headache disorder. In this educational post, I will guide you through the complexities of this condition from my perspective as a clinician practicing at the intersection of chiropractic, functional medicine, and advanced practice nursing. We will begin by understanding the diagnostic criteria and clinical presentation of hemicrania continua, differentiating it from other primary headache disorders like migraines and cluster headaches. We will then delve into the anatomy and physiology of the cranial nerves involved, specifically the trigeminal nerve and its branches—the supratrochlear, supraorbital, zygomaticotemporal, and auriculotemporal nerves—which are often implicated in the pain pathways of this condition. I will share a detailed case study of a 71-year-old patient, demonstrating a diagnostic and therapeutic nerve block procedure step by step. This includes the rationale for the choice of anesthetics, the precise injection technique, and the immediate clinical outcomes. We will also explore the broader context of our integrative care model at Injury Medical Clinic. I will explain how my work as a Doctor of Chiropractic and Family Nurse Practitioner is complemented by the medical directorship of Dr. Maria Guadalupe Cardenas, MD, an internist with over 40 years of experience. Together, we provide a multidisciplinary framework that combines medical oversight with chiropractic adjustments, functional medicine, rehabilitation, and advanced non-invasive therapies to offer a comprehensive, personalized treatment journey for patients with chronic pain and complex neurological conditions.

Introduction: A Journey Into a Unique Headache Disorder

Hello, I’m Dr. Alex Jimenez. Throughout my career across chiropractic, advanced practice nursing, and functional medicine, my primary mission has been to unravel the complexities of chronic pain and offer my patients a path to lasting relief. At Injury Medical Clinic in El Paso, Texas, we have cultivated a unique environment where different medical disciplines converge to create a truly integrative,patient-centered experience.
A cornerstone of our practice is our collaborative structure. I am privileged to work alongside Dr. Maria Guadalupe Cardenas, MD, a highly respected, board-certified internist who serves as our Medical Director and Collaborative Physician. With her extensive four-decade-long experience, Dr. Cardenas provides the essential medical oversight that allows us to safely and effectively integrate a wide range of therapies. Our clinic is a multidisciplinary hub where chiropractic care, medical management, functional medicine, personal injury rehabilitation, and nutritional science are not just co-located but are woven together into a cohesive treatment strategy. This lets us see a patient not just as a diagnosis, but as a whole person with a unique physiology, lifestyle, and history.
Today, I want to guide you through a fascinating and often misdiagnosed condition known as hemicrania continua. This isn’t just another headache. It’s a relentless, one-sided pain that can erode a person’s quality of life. I will share insights from leading researchers and evidence-based practices, and I’ll walk you through a clinical encounter from September 1, 2026, to illustrate how we approach these complex cases. This journey will not only shed light on the condition itself but also demonstrate the power of an integrative approach in modern healthcare.

Understanding Hemicrania Continua: More Than Just a Headache

When patients hear the term “chronic headache”, they often think of migraines. While migraines are certainly prevalent, the world of primary headache disorders is vast and includes conditions like hemicrania continua (HC), which requires a more specific diagnostic lens.
Hemicrania continua, a member of the trigeminal autonomic cephalalgias (TACs), is defined by three core features according to the International Classification of Headache Disorders, 3rd edition (ICHD-3) (Headache Classification Committee of the International Headache Society (IHS), 2018):
Unilateral Pain: The headache is strictly confined to one side of the head and does not switch sides.
Continuous Pain: The pain is present daily and continuously, without any pain-free periods. While the intensity can fluctuate, a baseline level of discomfort remains.
Absolute Response to Indomethacin: The headache is exquisitely and completely responsive to therapeutic doses of the non-steroidal anti-inflammatory drug (NSAID) indomethacin. This response is so characteristic that it is a required diagnostic criterion.
Patients with HC often experience superimposed attacks of more severe pain, during which they may also develop cranial autonomic symptoms on the same side as the headache. These can include:
Conjunctival injection (red eye)
Lacrimation (tearing)
Nasal congestion or rhinorrhea (runny nose)
Eyelid edema (swelling)
Forehead or facial sweating
Miosis (constriction of the pupil) or ptosis (drooping of the eyelid)
The underlying pathophysiology of HC is believed to involve the trigeminovascular system. This complex network involves the trigeminal nerve (the fifth cranial nerve), the primary sensory nerve of the face and head, and the blood vessels of the cranium. Activation of this system releases neuropeptides like calcitonin gene-related peptide (CGRP), which causes vasodilation and neurogenic inflammation and ultimately results in pain (Goadsby et al., 2017). The central mechanisms, particularly the involvement of the posterior hypothalamus, are also an area of active research and help explain the continuous nature of the pain and its autonomic features.

A Clinical Encounter: The Case of a 71-Year-Old with Right-Sided Headache

To bring these concepts to life, let me walk you through a case I managed on the morning of September 1, 2026. A 71-year-old woman presented to our clinic with a long-standing history of a right-sided headache that fit the clinical picture of hemicrania continua. She described a constant, dull ache on the right side of her head, punctuated by episodes of sharper, more intense pain. Before our procedure, she rated her current pain as a seven out of ten on a standard pain scale.
My immediate goal was twofold: first, to confirm the peripheral nerve involvement contributing to her pain pattern, and second, to provide immediate, albeit temporary, therapeutic relief. A successful diagnostic nerve block can provide profound insight into the patient’s specific pain generators.

The Diagnostic Examination: Pinpointing the Pain

Before any intervention, a thorough physical examination is paramount. For this patient, I focused on palpating the terminal branches of the trigeminal nerve, which are common sites of peripheral sensitization and pain in various headache disorders. Using gentle but firm pressure, I assessed for allodynia (pain from a stimulus that does not normally provoke pain) and hyperalgesia (an increased response to a painful stimulus).
I identified four specific points of exquisite tenderness, which corresponded directly to the anatomical locations of four key sensory nerves:
Supratrochlear Nerve: Located just medial to the supraorbital notch, this nerve provides sensation to the medial forehead and upper eyelid. When I applied pressure here, the patient immediately confirmed, “Yes,” it was painful.
Supraorbital Nerve: Found at the supraorbital notch or foramen, along the upper rim of the orbit. This larger nerve supplies most of the forehead and scalp. Palpation here also elicited a clear “Yes, yes” response of pain.
Zygomaticotemporal Nerve: This smaller branch emerges through a foramen in the zygomatic (cheek) bone to supply the skin over the temporal fossa (the “temple”). When I pressed on this area, she again confirmed, “Right there. Yes.”
Auriculotemporal Nerve: This nerve travels in front of the ear, ascending over the zygomatic arch to supply the skin of the temporal region and parts of the ear. Palpation here confirmed localized tenderness.
The patient’s clear and reproducible pain response at these four locations strongly suggested that these peripheral branches of the trigeminal nerve were significant contributors to her overall headache experience. This phenomenon, known as peripheral sensitization, occurs when the nerve endings become hyperexcitable, lowering the threshold for firing and amplifying pain signals sent to the brain. I hypothesized that temporarily silencing these nerves could interrupt the barrage of pain signals and provide relief.

Preparing for the Nerve Block: A Meticulous Approach

With the target nerves identified, the next step was to prepare for the peripheral nerve block procedure. Precision, safety, and patient comfort guide this step.
Marking the Injection Sites: I used the retracted, smooth tip of a ballpoint pen to make very light ink marks at the four tender points. It’s crucial not to apply too much pressure, as this can cause discomfort and tissue indentation, making accurate needle placement more difficult.
Aseptic Technique: The skin was then meticulously prepped with Betadine (povidone-iodine), an antiseptic that reduces the microbial load on the skin and minimizes infection risk. We allowed it to air-dry to ensure its full antimicrobial effect.
The Anesthetic Cocktail: For the injection itself, I prepared a specific mixture designed to provide both rapid onset and extended duration of action. The solution consisted of:
0.5% Lidocaine with Epinephrine: Lidocaine is a fast-acting local anesthetic that typically begins working within minutes. Adding epinephrine, a vasoconstrictor, serves two purposes: it reduces local bleeding and, more importantly, slows systemic absorption of lidocaine, prolonging its local effect and reducing potential toxicity (Becker & Reed, 2012).
0.5% Bupivacaine: Bupivacaine has a much slower onset of action but a significantly longer duration, often providing pain relief for several hours.
By combining these two agents, we create a synergistic effect: lidocaine provides immediate relief and comfort, while bupivacaine takes over to provide a longer therapeutic window. The goal is not just to numb the area for a few minutes but to break the pain cycle for an extended period. I drew up a total of 1 mL of this mixture for each of the four injection sites.

The Procedure: A Step-by-Step Execution of the Nerve Blocks

Performing injections on the face, especially near the eyes, requires extreme care and a gentle hand. The patient was understandably apprehensive, so clear communication and a calm demeanor were essential.
Choice of Needle: I selected a 30-gauge, half-inch needle. This ultra-fine needle minimizes tissue trauma and patient discomfort. While a topical anesthetic spray can be used in other areas, its use so close to the eyes is contraindicated. In this case, the small needle size makes the initial injection itself less uncomfortable than the spray would be.
Injection Technique for Supratrochlear and Supraorbital Nerves:
For the first two injections targeting the nerves along the brow ridge, safety is the number one priority. To prevent the anesthetic from diffusing inferiorly into the orbit (the eye socket), I placed my non-dominant thumb firmly against the patient’s orbital rim, just below the injection site. This creates a physical barrier, or a bolster, to direct the fluid superiorly into the subcutaneous tissue of the forehead.
I gently advanced the needle to the marked supratrochlear nerve site until I felt the delicate “tap” of the needle tip against the periosteum (the outer surface of the bone).
I then withdrew the needle slightly, about 1-2 millimeters, so the tip was in the subcutaneous space just above the bone where the nerve lies.
Aspiration is a critical safety step. Before injecting, I pulled back on the plunger to ensure the needle was not inside a blood vessel. The absence of a blood return in the syringe hub (“no blood”) confirms a safe position.
I slowly and steadily injected 1 mL of the anesthetic solution. During the injection, I felt the fluid pressure building against my thumb, confirming that my bolster was effectively preventing orbital diffusion.
I repeated this exact process for the supraorbital nerve, again maintaining the protective thumb placement. The patient tolerated these first two injections well, with minimal discomfort.
Injection Technique for Zygomaticotemporal and Auriculotemporal Nerves:
For the zygomaticotemporal nerve on the cheekbone, the technique was similar. I advanced the needle to touch bone, withdrew slightly, and aspirated. This area is less critical for orbital diffusion, so the thumb bolster was not necessary.
For the final injection targeting the auriculotemporal nerve in the temporal region, an extra layer of caution is required. The superficial temporal artery runs in proximity to this nerve. Therefore, aspiration is absolutely mandatory here to avoid an inadvertent intravascular injection, which could lead to systemic toxicity. After confirming I was not in the artery, I proceeded to inject the final 1 mL of anesthetic.
The entire procedure, from marking to the final injection, took only a few minutes. I maintained communication with the patient throughout, reassuring her and monitoring her comfort.

Immediate Post-Procedure Assessment: Gauging the Efficacy

The true test of a nerve block’s success is the patient’s subjective response. Immediately after completing the injections, I began the assessment.
“Was that painful?” I asked.
“No, no. It felt pretty good,” she replied, visibly relieved. “It was a little pinch on a couple of them. Not as bad as we feared.”
This immediate feedback is valuable, but the primary endpoint is the effect on her headache. I asked her to re-evaluate her pain:
“You reported your headache was a seven out of ten just a moment ago. What number would you assign your headache right now?”
“I think it’s better,” she said thoughtfully. “More like a five.
A two-point drop on the pain scale within minutes of the procedure is a very encouraging sign. It indicates that peripheral nerve sensitization was a major component of her pain and that the anesthetic was working as intended.
Next, I performed a follow-up palpation exam:
I pressed over the supratrochlear nerve site. “Does that hurt?” I asked. “No,” she said. “Did it hurt before?” “Yes. Yes, it did.
I moved to the supraorbital nerve. “Does it hurt when I press over here?” “No.”
I then palpated the zygomaticotemporal and auriculotemporal nerves, both of which were no longer tender.
The resolution of localized tenderness (allodynia), combined with the reduction in her baseline headache intensity, provided a clear, positive diagnostic result. It confirmed that these four nerves were actively involved in her hemicrania continua pain pathway.
The immediate goal was achieved, but the long-term hope is that this intervention can do more. By silencing the hyperexcitable nerves for several hours, we aim to break the pain cycle. This period of relief can allow the central nervous system to “calm down,” a process known as down-regulating central sensitization. For some patients, a single series of blocks can provide relief that far outlasts the anesthetic’s pharmacological effect, sometimes for days or even weeks. For this patient, we would monitor her progress over the next hour and the following days to see whether the headache breaks completely.

The Integrative Chiropractic and Medical Framework: Our Comprehensive Approach

The nerve block procedure I’ve just described is a powerful tool, but it’s only one piece of a much larger puzzle. At Injury Medical Clinic, we believe that sustainable healing from chronic conditions like hemicrania continua requires a multifaceted approach that addresses the body as an interconnected system. This is where our unique integrative model, guided by Dr. Cardenas and me, truly shines.
Our philosophy is built on the understanding that pain, especially chronic neurological pain, is rarely caused by a single, isolated issue. It’s often the result of a cascade of dysfunction involving the musculoskeletal system, the nervous system, metabolic health, and even psychosocial factors.

The Role of Chiropractic Care in Headache Management

As a Doctor of Chiropractic, my primary focus is on the biomechanical and neurological integrity of the spine, particularly the cervical spine (the neck). The upper cervical spine houses critical neurological structures, including the brainstem and the upper cervical nerve roots, which have intricate connections with the trigeminal nucleus in the brainstem. This anatomical relationship is known as the trigeminocervical complex (Bogduk, 2003).
Cervicogenic Inputs: Misalignments or dysfunctional movement in the joints of the upper neck (vertebral subluxations) can create noxious mechanical and inflammatory signals. These signals travel from the cervical nerve roots (C1, C2, C3) and converge on the trigeminocervical nucleus, which receives sensory information from the trigeminal nerve. The brain can misinterpret these cervical signals as originating from the head, a phenomenon known as referred pain. This can initiate or exacerbate a headache.
Chiropractic Adjustments: Gentle, specific chiropractic adjustments are designed to restore proper motion and alignment to the cervical vertebrae. By correcting these biomechanical faults, we can:
Reduce nerve irritation: Alleviate direct or indirect pressure on the cervical nerve roots and surrounding tissues.
Improve proprioception: Restore the normal flow of sensory information from the joints and muscles of the neck to the brain, which can help down-regulate pain processing centers.
Decrease muscle tension: Hypertonicity in the suboccipital and other neck muscles is a common finding in headache sufferers. Adjustments can help normalize muscle tone by resetting the neural feedback loops that control muscle contraction.
For a patient with hemicrania continua, chiropractic care is not aimed at “curing” the primary headache disorder itself. Instead, it serves to remove any co-existing cervicogenic contributions that may be lowering the threshold for an attack or adding to the overall pain burden. By optimizing cervical spine function, we can reduce the overall “noise” in the trigeminocervical complex, potentially making the primary headache less frequent, less severe, and more responsive to other treatments.

Functional Medicine: Looking for the Root Cause

Functional medicine provides another critical layer to our integrative approach. Instead of just managing symptoms, we ask why the patient is experiencing this dysfunction in the first place. For headache disorders, we investigate several key areas:
Nutrient Deficiencies: Certain micronutrients are essential for proper neurological function and inflammation control. Deficiencies in magnesium, Coenzyme Q10 (CoQ10), and riboflavin (Vitamin B2) have been linked to an increased risk of headaches, particularly migraines (Schürks et al., 2008; Sándor et al., 2005). We use advanced laboratory testing to identify and correct these deficiencies with targeted supplementation.
Gut Health and Food Sensitivities: The gut-brain axis is a bidirectional communication highway between the gastrointestinal system and the central nervous system. An imbalanced gut microbiome (dysbiosis) or increased intestinal permeability (“leaky gut”) can trigger systemic inflammation, which can, in turn, lower the threshold for headache attacks. Identifying and eliminating trigger foods through an elimination diet or food sensitivity testing can be a game-changer for many patients.
Hormonal Imbalances: Fluctuations in hormones, especially estrogen in women, can be a powerful headache trigger. We assess sex hormones and adrenal function (e.g., cortisol levels) to identify imbalances that may be contributing to the patient’s condition.
Mitochondrial Dysfunction: Mitochondria are the powerhouses of our cells, including our neurons. When they don’t function optimally, they can trigger an “energy crisis” in the brain, making it more susceptible to conditions like headaches and neuroinflammation. Supporting mitochondrial health with nutrients like CoQ10, L-carnitine, and D-ribose can be a foundational part of our treatment plan (Yorns & Hardison, 2013).
By addressing these underlying metabolic and physiological imbalances, functional medicine helps to improve the body’s overall resilience and reduce the systemic factors that may be perpetuating the headache cycle.

The Synergy of a Multidisciplinary Team

The true strength of our clinic lies in how these different disciplines are woven together under the expert medical oversight of Dr. Maria Cardenas. Her role as our Medical Director is indispensable.
Medical Diagnosis and Oversight: Dr. Cardenas provides the definitive medical diagnosis and ensures that all potential red flags or more serious underlying pathologies are ruled out. Her internal medicine expertise is crucial for managing patients with complex comorbidities.
Pharmacological Management: For a condition like hemicrania continua, the response to indomethacin is diagnostic. Dr. Cardenas manages the prescription and monitoring of such medications, ensuring they are used safely and effectively, especially considering the potential side effects of long-term NSAID use.
Collaborative Treatment Planning: We hold regular team meetings to discuss patient cases. I might present my findings from a chiropractic and functional neurology perspective, while Dr. Cardenas provides her medical insights. Together, we formulate a comprehensive treatment plan. For the patient described earlier, the plan might look like this:
Immediate Pain Control: Peripheral nerve blocks performed by me (as an FNP) under Dr. Cardenas’s collaborative agreement to break the acute pain cycle.
Biomechanical Support: A course of gentle chiropractic adjustments to address underlying cervicogenic factors.
Medical Management: A trial of indomethacin prescribed and monitored by Dr. Cardenas to confirm the diagnosis and provide baseline control.
Functional Medicine Investigation: Lab testing for nutritional deficiencies, food sensitivities, and hormonal imbalances to address root-cause contributors.
Rehabilitation: Our team of rehabilitation specialists would design a program of specific exercises to improve neck posture, strengthen deep neck flexors, and provide lasting stability.
This integrated model ensures the patient receives the best of all worlds in a coordinated, synergistic way. We are not just a collection of individual practitioners; we are a cohesive team working toward a single goal: the patient’s well-being.

Conclusion: A New Horizon for Headache Sufferers

The case of the 71-year-old patient with hemicrania continua is a powerful illustration of how a precise diagnostic procedure can provide immediate clarity and relief. The successful nerve block not only alleviated her pain but also confirmed the involvement of specific peripheral nerves, guiding our subsequent treatment strategy.
However, the larger takeaway is the power of the integrative framework in which this procedure took place. Managing complex chronic pain requires moving beyond a single-modality approach. It demands a holistic perspective that honors the intricate connections between the body’s systems—musculoskeletal, neurological, metabolic, and biochemical.
At Injury Medical Clinic, our collaboration across chiropractic care, advanced practice nursing, functional medicine, and internal medicine, under the leadership of Dr. Maria Cardenas, allows us to provide this level of comprehensive care. We strive not only to manage symptoms but to restore function, improve resilience, and empower our patients to reclaim their lives from chronic pain. If you or a loved one is struggling with a persistent headache, know that there is hope. By looking at the whole picture, we can uncover new possibilities for healing and well-being.

References

SEO Tags: Hemicrania Continua, Headache Treatment, Nerve Block, Integrative Medicine, Dr. Alex Jimenez, El Paso Chiropractor, Functional Medicine, Trigeminal Nerve, Chronic Pain, Chiropractic Care, Cervicogenic Headache, Dr. Maria Cardenas, Injury Medical Clinic, Pain Management, Peripheral Nerve Block, Lidocaine, Bupivacaine, Indomethacin, Trigeminal Autonomic Cephalalgia, Integrative Chiropractic Care

Occipital Neuralgia Treatment for Neck and Head Pain

Occipital Neuralgia Treatment for Neck and Head Pain

Abstract

Occipital neuralgia is a debilitating condition characterized by sharp, throbbing, or electric shock-like pain in the upper neck, back of the head, and behind the ears, often radiating to the scalp. This pain originates from the irritation or compression of the greater and lesser occipital nerves. In this educational post, I, Dr. Alex Jimenez, will take you on a journey to understand the physiological underpinnings of occipital neuralgia, exploring its causes, symptoms, and the latest in diagnostic and treatment strategies. We will delve into how our integrative practice combines evidence-based medicine with a holistic philosophy. A key component of our approach is the collaboration between me, with a background in chiropractic and functional medicine, and our esteemed Medical Director, Dr. Maria Guadalupe Cardenas, MD, a Board-Certified Internist with over four decades of experience. Together, we provide a multidisciplinary framework that integrates chiropractic care, medical oversight, functional medicine, and rehabilitative therapies to offer comprehensive, personalized solutions for patients with this painful condition. We will also examine a specific interventional technique—the occipital nerve block—and discuss how it fits within our broader, patient-centered treatment paradigm.

Occipital Neuralgia Treatment for Neck and Head Pain

Hello, I’m Dr. Alex Jimenez. With my extensive training as a Doctor of Chiropractic (DC), Advanced Practice Registered Nurse (APRN), Family Nurse Practitioner (FNP-BC), and certifications in functional medicine (CFMP, IFMCP), I have dedicated my career to understanding and treating complex neuromusculoskeletal conditions. At Injury Medical Clinic PA, our mission is to provide a beacon of hope for those navigating the often-frustrating world of chronic pain.


A condition I frequently encounter in my clinical practice is occipital neuralgia. This isn’t just a simple headache; it’s a distinct neurological disorder that can severely impact one’s quality of life. The pain is often described as sharp, jolting, and unrelenting, stemming from the occipital nerves that run from the top of the spinal cord up through the scalp.

Our clinic uses a unique, powerful model of integrative care. I work closely with Dr. Maria Guadalupe Cardenas, MD. As a Board-Certified Internist with over 40 years of dedicated patient care (NPI #1164426749, Texas MD License #J2933), Dr. Cardenas serves as our Medical Director and Collaborative Physician. This partnership allows us to seamlessly blend the diagnostic precision and medical oversight of internal medicine with the holistic, biomechanical focus of chiropractic and functional medicine. This multidisciplinary approach ensures our patients receive a comprehensive, well-rounded treatment plan tailored to their individual needs, whether they are dealing with a personal injury, a chronic condition like occipital neuralgia, or are on a journey toward optimal wellness.

The Anatomy of Pain: What Are the Occipital Nerves?

To truly understand occipital neuralgia, we must first explore the anatomy involved. The primary culprits are the greater and lesser occipital nerves. These nerves are not part of the brain but are peripheral nerves that emerge from the upper cervical spine, specifically from the C2 and C3 nerve roots.

  • Greater Occipital Nerve: This is the larger of the two and originates from the C2 nerve root. It travels up through the deep muscles at the back of the neck, pierces the trapezius muscle, and then branches to provide sensation to most of the scalp on the back and top of the head.
  • Lesser Occipital Nerve: This nerve originates from the C2 and C3 nerve roots. It runs along the side of the neck, behind the ear, providing sensation to the skin in that area and the scalp just behind it.

When these nerves become inflamed, compressed, or injured anywhere along their path, they send distress signals that the brain interprets as intense pain. This is the essence of neuralgia—nerve pain.

Identifying the Root Cause of Occipital Neuralgia

Effective treatment depends on identifying the underlying cause of the nerve irritation. Occipital neuralgia is often secondary to another issue. Based on my clinical observations and leading research, common causes include:

  • Muscle Tension and Spasm: Chronic tension in the suboccipital muscles (the small muscles connecting the skull to the top of the spine) is a primary driver. Poor posture, such as “tech neck” from looking down at devices, can lead to hypertonicity in these muscles, effectively entrapping the occipital nerves as they pass through.
  • Trauma or Injury: Whiplash from a car accident, a direct blow to the back of the head, or even repetitive micro-trauma can injure the nerves or surrounding tissues, leading to inflammation and compression.
  • Cervical Spine Misalignments (Subluxations): From a chiropractic perspective, misalignments in the upper cervical vertebrae (atlas and axis) can directly irritate the C2 and C3 nerve roots from which the occipital nerves originate. This biomechanical dysfunction is a critical factor we address with chiropractic adjustments.
  • Degenerative Conditions: Osteoarthritis or degenerative disc disease in the upper cervical spine can lead to bone spurs or narrowing of the spaces where nerves exit the spinal column (foraminal stenosis), causing nerve compression.
  • Systemic Conditions: Less commonly, conditions like gout, diabetes, or infections can cause inflammation that affects the occipital nerves.

The Role of Integrative Chiropractic Care

This is where our integrative model truly shines. As a chiropractor, I focus on the biomechanical integrity of the spine and nervous system. When a patient presents with symptoms of occipital neuralgia, my assessment begins with a thorough examination of the cervical spine.

  1. Chiropractic Adjustments: Using precise, gentle adjustments, I work to restore proper motion and alignment to the C1 (atlas) and C2 (axis) vertebrae. By correcting these vertebral subluxations, we can alleviate direct pressure on the nerve roots. This is not merely “cracking the neck”; it is a specific intervention designed to improve nerve function at its source (Taylor & Murphy, 2020).
  2. Soft Tissue Mobilization: The nerves don’t exist in a vacuum. Muscles, fascia, and other soft tissues surround them. I utilize techniques like myofascial release, trigger point therapy, and instrument-assisted soft tissue mobilization (IASTM) to release tension in the suboccipital and trapezius muscles. This creates space for the nerve, reducing entrapment and inflammation.
  3. Functional Rehabilitation: Treatment doesn’t end in the clinic. We empower patients with specific postural correction exercises, neck-muscle stretches, and strengthening exercises for the deep cervical flexors. This proactive approach helps prevent the recurrence of muscle tension and postural strain that often trigger occipital neuralgia.

This chiropractic foundation sets the stage for resolving the condition’s biomechanical triggers. However, for some patients, the inflammation and pain are so acute that they create a barrier to effective manual therapy. This is where medical intervention, under Dr. Cardenas’s guidance, becomes crucial.

Medical Intervention: The Occipital Nerve Block

For patients experiencing severe, intractable pain, an occipital nerve block can be a game-changer. This minimally invasive procedure serves both diagnostic and therapeutic purposes. It involves injecting a small amount of local anesthetic and a corticosteroid directly around the inflamed occipital nerves.

Let’s walk through the procedure, as performed in our clinic under my scope as a Family Nurse Practitioner, to understand the “why” behind each step.

Step 1: Precise Identification of Tender Points

The first and most critical step is locating the exact points of maximum tenderness. The patient’s feedback is paramount. I use my fingers to palpate the area where the occipital nerves emerge, just below the base of the skull (the occiput). I’ll ask, “Is that the spot?” When the patient confirms, “Yes, that’s it,” I know I’ve found a primary trigger point. Because we’re working in the hairline, I make a small indentation with a capped pen and a tiny ink mark just below it for reference. This ensures absolute precision.

Step 2: Aseptic Preparation

Patient safety is non-negotiable. I thoroughly cleanse the marked areas with alcohol swabs. In a hairy area like the scalp, this is a practical, effective way to prepare the skin and minimize infection risk.

Step 3: The Therapeutic Combination

The syringe contains a carefully measured mixture of two key components:

  • Lidocaine: This is a local anesthetic. It provides immediate pain relief by blocking sodium channels in nerve fibers. This stops pain signals from reaching the brain. The rapid relief it provides also serves a diagnostic function—if the pain disappears almost instantly, it confirms that the occipital nerve was indeed the source of the pain.
  • Cortisone: This is a powerful anti-inflammatory steroid. While lidocaine provides short-term relief, cortisone targets the underlying inflammation. It suppresses the local inflammatory response, reduces swelling around the nerve, and provides longer-lasting pain relief that can last for weeks or even months (Govindappagari & V, 2022). The goal is to break the pain-inflammation cycle.

Step 4: The Injection Process

Using a fine-gauge needle (a 25-gauge in this case) to minimize discomfort, I perform the injection. I always alert the patient, saying, “You’re going to feel a little stick.” I advance the needle until it is near the occiput, in the vicinity of the nerve.

Before injecting, I perform an aspiration. This means I gently pull back on the plunger to ensure the needle tip is not inside a blood vessel. If blood were to enter the syringe, it would indicate an intravascular position, and injecting the steroid there could lead to systemic side effects. Seeing no blood on aspiration confirms we are in the correct tissue plane. I then slowly inject the solution, bathing the nerve in the anesthetic and anti-inflammatory medication. I repeat this for each identified trigger point.

Step 5: Immediate Post-Procedure Assessment

Immediately after the injection, I gently massage the area to help disperse the medication. Then comes the moment of truth. I apply pressure to the same spots that were excruciatingly painful just moments before. I ask, “Does that hurt right there?” The typical response is one of relief: “It feels better.” or “I just feel pressure now.”

This immediate feedback is invaluable. The patient’s significantly reduced pain confirms the block’s success. This relief, even if temporary from the anesthetic, breaks the cycle of pain and muscle guarding. It opens a crucial “window of opportunity” to apply our other therapies more effectively. With pain diminished, the patient can better tolerate chiropractic adjustments and engage in the necessary rehabilitative exercises.

A True Integrative Framework: Tying It All Together

The occipital nerve block is not a standalone cure; it is a strategic tool within our comprehensive care plan. Here is how the pieces fit together:

  1. Initial Crisis Management: The occipital nerve block, overseen medically by Dr. Cardenas and performed by me as an FNP, provides rapid, significant pain relief. This calms the hypersensitive nervous system.
  2. Restoring Biomechanical Function: During the pain-free window created by the block, I implement integrative chiropractic care. This includes targeted upper cervical spinal adjustments and soft tissue work to release muscular entrapment of the occipital nerves.
  3. Addressing Systemic Drivers: As a functional medicine practitioner, I also look deeper. Is there a systemic inflammatory issue at play? We may use advanced lab testing to investigate nutritional deficiencies, food sensitivities, or metabolic imbalances that could be contributing to chronic inflammation. A pro-inflammatory diet can certainly worsen conditions like neuralgia.
  4. Rehabilitation and Empowerment: Our physical therapy and rehabilitation team guides the patient through exercises to correct posture, strengthen supporting muscles, and improve overall spinal health, empowering them to maintain their results and prevent future flare-ups.

This cyclical, mutually reinforcing process is the heart of our practice. Medical intervention makes chiropractic care more effective, and chiropractic care addresses the root biomechanical issues to provide a long-term solution. Dr. Cardenas’s internal medicine expertise ensures we identify and manage any underlying systemic health issues, providing a complete safety net for the patient’s overall health.

By weaving together the latest evidence-based research and techniques from multiple disciplines, we create a patient journey that is not just about managing symptoms, but about restoring function, health, and quality of life. If you are struggling with head and neck pain, know that there are comprehensive, integrative solutions available that go beyond a simple prescription.


References


SubQ Testosterone for Women: Strength and Balance

SubQ Testosterone for Women: Strength and Balance

Abstract

Testosterone is often associated with men, but women naturally produce this hormone throughout life. In women, testosterone contributes to sexual function and interacts with muscle, bone, metabolism, and other body systems. When testosterone therapy is clinically appropriate, treatment should be individualized and monitored so hormone levels remain within the normal female physiologic range. Subcutaneous testosterone injections place a small amount of medication into fatty tissue just beneath the skin, where it is gradually absorbed. However, the strongest clinical evidence for testosterone therapy in women remains with transdermal treatment, especially for postmenopausal women with hypoactive sexual desire disorder, or HSDD.

At ChiroMed – Integrated Medicine in El Paso, Texas, this topic fits within a broader model of coordinated healthcare. Chiropractic care, nurse practitioner services, rehabilitation, nutrition, functional health strategies, and medical oversight can work together to address a patient’s musculoskeletal function and overall health rather than focusing on hormone levels alone. ChiroMed describes its approach as bringing multiple healthcare disciplines together to create individualized, patient-centered treatment plans.

SubQ Testosterone for Women: Strength and Balance

Understanding Testosterone in Women

Testosterone is a natural part of female physiology. The ovaries and adrenal glands contribute to androgen production, and testosterone levels normally change with age. Levels can also fall more quickly after ovary removal.

Testosterone interacts with many tissues throughout the body, including the brain, muscles, bones, reproductive tissues, and blood-forming system. However, recognizing these biological roles does not mean testosterone therapy has been proven to treat every symptom that may occur during menopause.

The strongest evidence currently supports systemic testosterone therapy for appropriately evaluated postmenopausal women with HSDD. HSDD involves persistent loss of sexual desire that causes personal distress. Major international organizations have concluded that this is the clearest evidence-supported indication for testosterone therapy in women (Davis et al., 2019).

A large systematic review and meta-analysis also found that testosterone can improve several areas of sexual function in postmenopausal women, including sexual desire, arousal, pleasure, orgasm, responsiveness, and sexual self-image (Islam et al., 2019).

What Are Subcutaneous Testosterone Injections?

A subcutaneous, or SubQ, injection places medication into fatty tissue beneath the skin rather than deeply into a muscle.

Testosterone cypionate may be prepared in concentrations that allow very small doses to be administered. Once placed into subcutaneous tissue, the medication forms a depot from which testosterone is gradually absorbed.

For women, the treatment goal is very different from testosterone treatment designed to produce male hormone concentrations. When testosterone is used for female HSDD, expert guidance recommends keeping concentrations within the physiologic range normally seen in premenopausal women rather than pushing testosterone above that range (Parish et al., 2021).

The attached clinical white paper makes an important distinction about SubQ injections. Randomized efficacy evidence in women is strongest for transdermal patches, creams, and gels. It describes subcutaneous injection as a titratable route with physiologic reasoning behind it, but notes that there is no dedicated randomized efficacy trial establishing SubQ testosterone injections for women.

That means SubQ testosterone should not be described as better proven than transdermal therapy. It is an alternative route that requires careful medical prescribing, laboratory monitoring, informed consent, and follow-up.

A “Low Testosterone” Number Is Not the Diagnosis

Laboratory testing is useful, but testosterone therapy in women should not begin solely because one test result falls near the lower end of a reference range.

The ISSWSH clinical guideline recommends a biopsychosocial assessment before treatment. A clinician may need to consider menopause status, medications, relationship factors, depression or anxiety, sleep, vaginal discomfort, pain during intercourse, medical illnesses, and other issues that can affect sexual desire. Total testosterone is useful mainly as a baseline and monitoring measurement rather than as a diagnostic test for HSDD (Parish et al., 2021).

The clinical white paper emphasizes the same principle. Testosterone measurements become especially important after therapy begins, because they help the healthcare team determine whether treatment remains within a physiologic female range and whether the patient is receiving too much hormone.

Testosterone, Muscle, and Musculoskeletal Health

Testosterone interacts with skeletal muscle biology, which is one reason the hormone receives attention in discussions about aging, physical function, and strength.

A randomized study examined different testosterone doses in postmenopausal women who had undergone hysterectomy. Higher testosterone concentrations were associated with changes in lean body mass and some measurements of muscle power. Importantly, the clearer muscle effects occurred with the highest dose and testosterone concentrations above typical female physiologic levels. The authors also stated that longer-term trials were needed to balance potential benefits against long-term risks (Huang et al., 2014).

This research should not be interpreted to mean that testosterone is a proven muscle-building treatment for women. The clinical white paper specifically notes that body-composition benefits have not been established as an approved indication for female testosterone therapy.

This is where physical rehabilitation becomes important. Hormones may influence the environment in which muscle tissue functions, but stronger muscles still require appropriate loading, movement, nutrition, recovery, and neuromuscular training.

Connecting Testosterone Therapy With Chiropractic Care

Chiropractic treatment and testosterone therapy perform very different jobs.

Testosterone therapy is a medical treatment that requires appropriate prescribing and monitoring. Chiropractic care focuses on the musculoskeletal system, including joint movement, spinal mechanics, posture, physical function, and rehabilitation.

For a woman who is also trying to maintain strength and mobility as she ages, an integrated plan may include:

  • medically supervised hormone assessment when clinically indicated;
  • chiropractic evaluation of the spine, pelvis, and extremities;
  • resistance and strength rehabilitation;
  • balance, mobility, and stability exercises;
  • adequate dietary protein and overall nutrition;
  • evaluation of sleep and recovery;
  • management of previous injuries or chronic musculoskeletal limitations;
  • progressive exercise based on the patient’s current ability;
  • laboratory monitoring when hormone therapy is prescribed;
  • ongoing reassessment of both symptoms and physical function.

The important idea is that testosterone does not replace exercise or rehabilitation. Likewise, an adjustment cannot correct a hormone disorder. When appropriate, the two approaches can address different parts of the patient’s health.

How This Fits the ChiroMed Integrated Medicine Model

ChiroMed – Integrated Medicine in El Paso brings several healthcare services into a multidisciplinary setting. The clinic currently describes chiropractic care, nurse practitioner services, rehabilitation, nutrition, acupuncture, and related integrative services as parts of its overall healthcare model.

That structure can be useful when women’s hormone concerns overlap with other health issues.

For example, a woman discussing hormonal symptoms may also have chronic back pain, reduced physical activity, previous injury, poor sleep, loss of conditioning, weight concerns, or difficulty maintaining muscle strength. Treating only a laboratory number would not address all of those factors.

ChiroMed’s integrated injury model similarly describes combining medical evaluation, chiropractic care, rehabilitation, soft-tissue treatment, and functional medicine strategies within a coordinated recovery plan.

Dr. Alexander Jimenez, DC, APRN, FNP-BC, works within this multidisciplinary environment by integrating chiropractic and musculoskeletal assessment with his advanced-practice nursing and functional medicine background. His clinical approach emphasizes movement, nutrition, metabolic health, rehabilitation, and other factors that affect how a patient feels and functions.

Medical oversight is also part of the ChiroMed structure. ChiroMed identifies Maria Guadalupe Cardenas, MD, a board-certified internal medicine physician, as Medical Director, Clinical Director, and Collaborative Physician. The ChiroMed website lists her Texas medical license as J2933 and NPI as 1164426748.

In a multidisciplinary model, the goal is not to make chiropractic treatment a substitute for medical hormone management. Instead, medical and musculoskeletal professionals can contribute within their respective scopes of practice.

Monitoring Testosterone Therapy in Women

If testosterone treatment is selected, follow-up is an essential part of care.

The clinical guideline recommends monitoring testosterone concentrations to prevent exposure above the physiologic premenopausal range. Patients should also be evaluated for clinical signs of androgen excess (Parish et al., 2021).

Possible concerns can include acne, increased facial or body hair, scalp hair changes, and other androgenic effects. Voice changes are less common but deserve prompt attention. The attached white paper explains that these effects tend to be dose-related and that scheduled reassessment helps identify excessive exposure early.

A clinician may also consider the patient’s overall medical history, cardiovascular health, breast health, medications, and other hormone therapy.

Importantly, testosterone should not simply be increased because symptoms have not changed quickly. Expert guidance suggests evaluating response over several months and stopping treatment when there is no meaningful benefit rather than pushing testosterone beyond the normal female physiologic range.

What We Still Do Not Know

Testosterone therapy in women is an area where evidence and clinical practice do not always move at the same speed.

Transdermal testosterone has the strongest randomized evidence. The evidence supporting subcutaneous injections in women remains much more limited. The attached white paper specifically identifies subcutaneous injection evidence as pharmacokinetic rather than supported by dedicated female efficacy trials.

Long-term cardiovascular and breast safety also remain incompletely defined. Available shorter-term findings at physiologic doses are reassuring, but researchers still lack adequately powered studies that answer every safety question over many years.

This is why individualized treatment and shared decision-making matter.

Integrating Hormone Health With Movement and Strength

Women’s health is rarely about one hormone, one joint, or one treatment.

For selected women with HSDD, properly monitored testosterone therapy may be one part of care. If a SubQ route is considered, the treatment should remain medically supervised and should recognize that evidence for female subcutaneous injections is still developing.

At the same time, maintaining musculoskeletal health requires movement.

Progressive resistance exercise, adequate nutrition, good sleep, rehabilitation, healthy body composition, joint mobility, and injury management all contribute to maintaining strength and physical independence.

That concept fits naturally with the ChiroMed – Integrated Medicine approach in El Paso: combining conventional medical oversight with chiropractic care, rehabilitation, nutrition, functional strategies, and individualized patient education. ChiroMed describes its purpose as bringing different disciplines together so treatment plans can address both symptoms and underlying contributors to health and function.

Testosterone therapy and chiropractic care should therefore not be viewed as competing treatments. When clinically appropriate, each addresses different parts of the larger goal—helping women maintain healthy physiology, functional muscles and joints, mobility, and quality of life.


References

Davis, S. R., Baber, R., Panay, N., et al. (2019). Global consensus position statement on the use of testosterone therapy for women. Journal of Clinical Endocrinology & Metabolism, 104(10), 4660-4666.

Hatzilabrou, T. A. (n.d.). Testosterone therapy in women. Worldborne Medical, Clinical Frontiers: Androgens Series.

Huang, G., Basaria, S., Travison, T. G., et al. (2014). Testosterone dose-response relationships in hysterectomized women with or without oophorectomy: Effects on sexual function, body composition, muscle performance and physical function in a randomized trial. Menopause, 21(6), 612-623.

Islam, R. M., Bell, R. J., Green, S., Page, M. J., & Davis, S. R. (2019). Safety and efficacy of testosterone for women: A systematic review and meta-analysis of randomised controlled trial data. The Lancet Diabetes & Endocrinology, 7(10), 754-766.

Parish, S. J., Simon, J. A., Davis, S. R., et al. (2021). International Society for the Study of Women’s Sexual Health clinical practice guideline for the use of systemic testosterone for hypoactive sexual desire disorder in women. The Journal of Sexual Medicine, 18(5), 849-867.

ChiroMed – Integrated Medicine. (2026). ChiroMed – Integrated Medicine: Holistic healthcare in El Paso, Texas.

ChiroMed – Integrated Medicine. (2026). Integrated medicine services in El Paso, Texas.

Chiropractic Practice and Health Tips with Obesity Medicine


Uncover the significance of obesity medicine combined with chiropractic practice in enhancing patient care and achieving better health results.

Educational Abstract

In this comprehensive educational post, I, Dr. Alex Jimenez, share a first-person, evidence-based journey through modern obesity care across the lifespan. With credentials as a Doctor of Chiropractic (DC), Advanced Practice Registered Nurse (APRN), Family Nurse Practitioner-Board Certified (FNP-BC), and certifications in Functional Medicine (CFMP, IFMCP), among others, I offer a unique, multidisciplinary perspective. This guide is designed for clinicians, staff, and healthcare leaders seeking to build or optimize a high-quality integrative obesity program. I explain how our team at Injury Medical Clinic, P.A. (also known as Mission Plaza Injury Medical Clinic) in El Paso, Texas, frames obesity as a chronic, relapsing, multifactorial disease and translates that understanding into actionable practice models.
Our clinic’s strength lies in its collaborative structure, led by our esteemed Medical Director and Collaborative Physician, Dr. Maria Guadalupe Cardenas, MD (NPI #1164426749, Texas MD License #J2933). A board-certified internal medicine physician with over 40 years of experience, Dr. Cardenas provides crucial medical oversight to ensure our integrative protocols meet the highest standards of safety and efficacy. Together, we integrate internal medicine, chiropractic care, functional medicine, rehabilitation, and personal injury services to deliver comprehensive, patient-centered care.
This post offers a detailed roadmap covering the four pillars of obesity treatment—nutrition, physical activity, behavioral counseling, and medical management (including pharmacotherapy and bariatric surgery referrals). I provide pragmatic workflows for various practice models, including guidance on billing and coding (time-based vs. MDM), Medicare services like Intensive Behavioral Therapy (IBT) and Chronic Care Management (CCM), and innovative tools like Remote Patient Monitoring (RPM). We will explore the physiological underpinnings of obesity, the importance of reducing bias and using person-first language, and how to create a weight-inclusive clinical environment. My goal is to equip you with a compassionate, scientifically grounded template to implement sensitive, effective, and sustainable obesity treatment programs.

Introduction: My First-Person Journey to Building a Modern, Patient-Centered Obesity Program

I am Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST. For decades, I have devoted my clinical practice to integrative, trauma-informed, evidence-based care, with a central focus on metabolic health, functional rehabilitation, and personalized medicine. In daily practice, I witness how language, imagery, coding, and care design either reinforce old stigmas or usher in a better way—one that recognizes obesity as a chronic, relapsing, multifactorial disease that deserves precise diagnosis, compassionate communication, and coordinated, evidence-based treatment.
In El Paso, Texas, our Injury Medical Clinic, P.A. (Mission Plaza Injury Medical Clinic) operates as a multidisciplinary ecosystem where internal medicine, chiropractic, functional medicine, and rehabilitation intersect to treat complex chronic conditions, including obesity.
Working hand-in-hand with our Medical Director and Collaborative Physician, Dr. Maria Guadalupe Cardenas, MD—board-certified in internal medicine (NPI #1164426749, Texas MD License #J2933)—we deliver coordinated care that respects obesity’s chronic nature. Dr. Cardenas brings over 40 years of internal medicine experience, guiding medical oversight, safety, diagnostic rigor, and pharmacotherapeutic strategies. My role emphasizes integrative chiropractic biomechanics, musculoskeletal optimization, functional medicine assessment, and rehabilitation planning. This multidisciplinary setup, where an MD provides medical direction alongside a chiropractor, is common and highly effective in modern integrative and injury care clinics, ensuring continuity, safety, and comprehensive outcomes. Together, we build individualized programs that incorporate nutrition therapy, physical activity prescription tailored to pain and function, behavioral counseling, and medical management, including pharmacotherapies and referral to bariatric surgery when indicated.
In this post, I will walk you through an actionable model to structure obesity care within primary care practices, specialty clinics, and standalone programs. I reframe obesity as a chronic, multifactorial disease requiring dedicated, obesity-specific appointments, regular follow-up (often averaging 16 visits in the first year for optimal outcomes), and collaborative workflows that reduce stigma and enhance access. The physiological underpinnings—neurohormonal regulation, adipose tissue biology, energy balance, biomechanics, pain, sleep, stress, and gut health—are explored in depth to explain why each therapeutic lever matters.
My goal is to give you a clear, compassionate, scientifically grounded template for obesity care that you can adapt to your setting, whether you are starting with a single dedicated clinic session per week or designing a fully integrated multidisciplinary center.

Our Collaborative Practice: Integrating Chiropractic and Medical Expertise

Before we dive into the specifics of obesity management protocols, I believe it’s essential to set the stage by explaining our practice’s unique structure. Our clinic is built on integrative, multidisciplinary care. This model is not just a philosophy but a functional reality that allows us to provide a truly holistic level of service, particularly for patients dealing with complex conditions like chronic obesity, metabolic dysfunction, and personal injuries.
A cornerstone of our practice is my collaborative relationship with Dr. Maria Guadalupe Cardenas, MD. Dr. Cardenas is a highly respected physician, board-certified in Internal Medicine, with an incredible four decades of experience. She serves as our Medical Director and Collaborative Physician, bringing a depth of medical knowledge that is simply invaluable. This partnership between a Doctor of Chiropractic (like myself, with additional APRN and functional medicine credentials) and an Internist (Dr. Cardenas) is a powerful synergy.

How Our Integrated Team Functions

So, what does this collaboration look like in practice?

  • Medical Oversight and Direction: Dr. Cardenas provides essential medical direction for our clinic. This includes overseeing protocols for prescription drug management, reviewing complex medical cases, and ensuring that our diagnostic and treatment plans meet the highest standards of medical care. When we are managing a patient’s GLP-1 medication or addressing comorbidities like hypertension and type 2 diabetes, her expertise as an internist is critical.
  • Chiropractic and Neuromusculoskeletal Care: As a Doctor of Chiropractic, my role focuses on the body’s structure and its relationship to overall function. For our patients with obesity, this is incredibly important. Excess weight places enormous stress on the musculoskeletal system, leading to chronic low back pain, knee arthritis, plantar fasciitis, and other biomechanical issues. Through chiropractic adjustments, spinal decompression, and soft tissue therapies, we address these structural imbalances, alleviate pain, improve mobility, and enhance nervous system function. This not only improves the patient’s quality of life but also removes a significant barrier to physical activity.
  • Functional Medicine and Advanced Diagnostics: As a certified functional medicine practitioner (CFMP, IFMCP), I lead our team in digging deeper to find the root causes of a patient’s health issues. Instead of just treating weight gain, we ask why it’s happening. We use advanced lab testing to look at hormonal imbalances, gut dysbiosis, nutrient deficiencies, and genetic predispositions. This allows us to create highly personalized nutrition and lifestyle plans.
  • Comprehensive Care Spectrum: Our team integrates rehabilitation services to restore function after an injury, provide dedicated personal injury care for accident victims, and offer nutritional and lifestyle counseling. A patient might see me for a chiropractic adjustment, consult on medication management under Dr. Cardenas’s oversight, work with our health coach on a functional nutrition plan, and engage in a rehab program to strengthen their core—all under one roof.

This integrated model ensures that we are not just managing obesity but treating the whole person. Constant communication between Dr. Cardenas and me allows us to create a seamless care experience where the medical and structural components of a patient’s health are addressed in a coordinated fashion.

Understanding Obesity as a Chronic, Relapsing, Multifactorial Disease

Obesity is a chronic, relapsing, heterogeneous disease characterized by excess adiposity that impairs health. It is not a personal failure, nor a short-term issue solved with quick fixes. Modern evidence shows that sustained management requires ongoing care—structured visits, targeted interventions, and a respectful, bias-aware environment.
Key points:

  • Obesity behaves like other chronic conditions—such as diabetes, hypertension, and dyslipidemia—requiring long-term strategies rather than one-time solutions.
  • Dedicated, obesity-specific appointments are essential. Trying to address obesity “on the fly” during unrelated visits rarely allows enough time to take a comprehensive history, perform a physical and functional exam, and co-create a treatment plan.
  • Regular follow-up is linked to better outcomes. Data suggest that about sixteen visits in the first year are associated with improved weight loss and cardiometabolic outcomes; intensifying early on, then spacing visits as the condition stabilizes, is a pragmatic pattern.
  • Insurance coverage can influence feasible visit frequency. Plan workflows around coverage realities, supplement with telemedicine and group visits, and leverage allied health professionals to maintain contact.

Why this approach matters:

  • Chronic care models improve adherence and health outcomes across diseases; obesity is no exception.
  • Obesity’s relapsing nature—driven by neurohormonal adaptations and environmental pressures—demands continuity, not episodic care.
  • When we structure appointments intentionally, we can address root contributors—genetic predisposition, endocrine signals, psychosocial factors, sleep, stress, gut health, and musculoskeletal limitations—and tailor interventions responsibly.

Foundational Physiology of Obesity: A Systems View for Clinicians

Understanding obesity’s physiology informs our protocols and patient communication. I approach this as a dynamic systems disorder characterized by interactions across neuroendocrine signaling, immunity, metabolism, microbiome, biomechanics, and behavior.
Key Mechanistic Domains:

  • Energy Homeostasis and Neuroendocrine Control:
    • Hypothalamic Regulation: Signals from leptin, insulin, ghrelin, peptide YY, GLP-1, and cholecystokinin converge to influence appetite, satiety, and energy expenditure. Leptin resistance undermines satiety signaling; ghrelin dynamics affect hunger.
    • Reward Pathways: Dopamine circuits modulate food salience; stress and sleep loss amplify hedonic drives.
    • Adaptive Thermogenesis: Weight loss decreases resting energy expenditure beyond predictions, encouraging regain; this underscores the need for sustained, supportive care.
  • Adipose Tissue Biology:
    • Hypertrophy vs. Hyperplasia: Enlarged adipocytes promote hypoxia, low-grade inflammation, and impaired insulin signaling.
    • Ectopic Lipid Deposition: Accumulates in the liver and muscle, exacerbating insulin resistance and metabolic dysfunction.
    • Adipokines and Cytokines: Imbalances in adiponectin, leptin, TNF-alpha, and IL-6 contribute to cardiometabolic risk.
  • Musculoskeletal Interplay:
    • Joint Loading and Pain: Mechanical stress increases in weight-bearing joints, altering gait and posture; pain limits activity, creating a cycle of deconditioning.
    • Sarcopenic Obesity: Reduced muscle mass with increased fat mass impairs glucose disposal and function; resistance training becomes a cornerstone.
  • Sleep and Circadian Rhythm:
    • Sleep Restriction: Increases ghrelin and decreases leptin, dysregulating appetite, increasing caloric intake, and impairing glucose tolerance.
    • Sleep-Disordered Breathing: Sleep apnea aggravates cardiometabolic risk and reduces daytime function.
  • Psychosocial Determinants:
    • Chronic Stress: Elevates cortisol, alters food choices, and impairs motivation.
    • Weight Stigma: Increases avoidance of care, reduces physical activity in public spaces, and worsens health outcomes independent of BMI.

The Four Pillars of Obesity Treatment: A Multidisciplinary Framework

In our program, the four pillars anchor care. Each pillar interacts with the others biologically and behaviorally, reinforcing momentum.

1. Nutrition Therapy: Physiology, Methods, and Personalization

Physiology: Appetite regulation involves ghrelin (orexigenic), leptin (satiety; often resistant in obesity), peptide YY, GLP-1, and insulin. Reward pathways and hyperpalatable foods drive hedonic intake beyond energy needs. Insulin resistance and hepatic steatosis alter substrate handling; reducing carbohydrate load and fructose can improve hepatic fat and insulin sensitivity.
Methods:

  • Personalized eating patterns: Mediterranean-style, higher-protein plans, lower-carbohydrate strategies, time-restricted eating, or structured meal replacements. We adapt plans to cultural cuisines and budget constraints.
  • Focus on protein adequacy (generally 1.2–1.6 g/kg of adjusted body weight for weight loss phases), fiber density, and low-energy-density foods to improve satiety.
  • Address ultra-processed food exposure and reward-system dynamics; incorporate shopping skills, cooking education, and food environment restructuring.
  • Medical nutrition therapy for comorbidities: NAFLD/MASLD, insulin resistance, PCOS, hypertension.

Why it works: A sustained negative energy balance is necessary for weight loss; nutrient composition supports satiety and preserves lean mass. Reducing ultra-processed foods lowers hyperpalatable stimuli and reduces hedonic overeating. Tailoring to comorbid conditions enhances safety and adherence.

2. Physical Activity Prescriptions: Graded, Safe, and Function-Oriented

Physiology: Movement enhances energy expenditure, improves insulin sensitivity, preserves and builds lean mass, supports mental health, and reduces chronic pain through improved biomechanics. Resistance training preserves lean mass, helping maintain basal metabolic rate during weight loss. Aerobic exercise improves mitochondrial biogenesis and cardiovascular health.
Methods:

  • Begin with low-impact options: walking, cycling, swimming, or aquatic therapy.
  • Progressive resistance training 2–3 days/week to maintain lean mass and metabolic rate; focus on compound movements scaled to function (e.g., chair stands, resistance bands, supported deadlifts).
  • Movement prescriptions integrated with chiropractic and rehabilitation when pain or postural dysfunction limits activity.
  • Non-exercise activity thermogenesis (NEAT) strategies to increase daily movement.
  • Integrate chiropractic-guided corrective exercises for posture and core stability.

Why it works: Preserving lean mass mitigates metabolic adaptation during weight loss. Strengthening corrects kinetic chain imbalances contributing to pain, allowing sustainable activity. Physical activity enhances mitochondrial function and cardiometabolic health beyond weight outcomes.

3. Behavioral Counseling: Skills That Sustain Change

Physiology: Sustained habit change requires skills such as self-monitoring, stimulus control, cognitive restructuring, and coping strategies. Chronic stress from stigma elevates cortisol, disrupts sleep, and worsens insulin resistance and visceral adiposity. Mindfulness improves interoception and reduces reward-driven overeating.
Methods:

  • Health coaching for goal setting, problem-solving, and accountability, often using motivational interviewing.
  • Psychotherapy for depression, anxiety, trauma, or eating disorders when present.
  • Group-based support, peer accountability, and digital self-monitoring tools.
  • Cognitive reframing: Shift focus from weight to health behaviors; celebrate process milestones.
  • Relapse planning: Anticipating high-risk situations and setting recovery steps.

Why it works: Behavioral skills enhance adherence and resilience. Addressing mood and stress physiology improves appetite regulation and sleep, reducing relapse. Psychological safety increases adherence to nutrition, activity, medications, and follow-ups.

4. Medical Management: Pharmacotherapy and Comorbidity Care

Physiology: Medications modulate appetite and energy balance via central and peripheral pathways. For example, GLP-1 receptor agonists reduce appetite, slow gastric emptying, and improve insulin secretion and sensitivity.
Methods:

  • Select anti-obesity medications (AOMs) based on phenotype, comorbidities, and contraindications under medical oversight. This includes GLP-1 receptor agonists, dual incretin therapies (GIP/GLP-1), and other approved medications per current guidelines.
  • Manage obesity-related comorbidities: type 2 diabetes, hypertension, dyslipidemia, OSA, NAFLD/MASLD, osteoarthritis.
  • Refer for bariatric surgery when indicated; coordinate prehab and rehab to optimize outcomes.

Why it works: Medications can be transformative when tailored and monitored. Comorbidity management improves safety and function, enabling activity and adherence. Surgery can produce durable weight loss and metabolic improvements in selected patients; integrated care maximizes benefits.

Balancing Body and Metabolism- Video

Integrative Chiropractic Care in Obesity Management: Biomechanics, Pain, and Functional Capacity

Integrative chiropractic is a key component of our multidisciplinary approach. Obesity frequently coexists with pain syndromes and postural dysfunction. These biomechanical issues can limit activity, creating a feed-forward cycle of deconditioning. Chiropractic evaluation and targeted interventions break that cycle.
Clinical Rationale:

  • Excess adiposity shifts the center of mass anteriorly, increasing lumbar lordosis, pelvic tilt, and stress on load-bearing joints such as the knees and hips.
  • Compensatory postures lead to paraspinal hypertonicity, reduced thoracic mobility, and altered gait mechanics; pain follows and discourages movement.
  • Myofascial restrictions, trigger points, and joint dysfunction limit range of motion and increase the effort cost of activity.

Interventions:

  • Spinal and extremity adjustments to restore joint function, reduce nociceptive input, and improve proprioception.
  • Soft tissue therapies: myofascial release, instrument-assisted soft tissue mobilization, cupping, and neuromuscular re-education to normalize tone and improve tissue glide.
  • Postural retraining, breathing mechanics optimization, and core stabilization to distribute loads efficiently.
  • Progressive, pain-sensitive exercise prescriptions integrating mobility and strength, with graded exposure to activity to build confidence.

Why This Matters Clinically: By improving joint motion and reducing pain, chiropractic care can lower pain levels, improve movement efficiency, and enable progressive exercise. This enhanced activity capacity is a keystone for metabolic improvement. Better movement competence improves adherence to exercise prescriptions, a critical determinant of long-term success.

Internal Medicine Oversight: Safety, Diagnostics, and Medical Direction

Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine, serves as our Medical Director and Collaborative Physician. Her role ensures that our integrative program meets high standards of safety, diagnostic precision, and medical integrity.
Responsibilities:

  • Comprehensive internal medicine evaluation: metabolic, cardiovascular, endocrine, and sleep assessments.
  • Pharmacotherapy supervision: selecting, dosing, and monitoring anti-obesity medications and comorbidity treatments, including GLP-1 receptor agonists.
  • Risk stratification: identifying patients who require closer monitoring, cardiology referral, or specialist evaluation.
  • Surgical coordination: ensuring patients meet bariatric referral criteria and overseeing perioperative medical care.
  • Quality assurance and compliance: aligning protocols with current evidence and regulatory standards.

t: Medical oversight reduces adverse events, optimizes medication choices, and integrates comorbidity care. Collaboration with chiropractic and rehabilitation ensures the safe progression of activity in medically complex patients. Patients benefit from a consistent, trusted, evidence-based, and personalized framework.

Functional Medicine Integration: Systems Biology Applied to Obesity

Functional medicine complements internal medicine and chiropractic by taking a systems biology view of the patient. We examine the interconnected networks influencing weight: nutrition, energy metabolism, inflammation, gut health, hormones, sleep, stress, and toxins.
Key Elements:

  • Personalized nutrition with elimination of trigger foods, gut-directed therapies for dysbiosis, and micronutrient repletion.
  • Inflammation modulation through dietary patterns and lifestyle change.
  • Sleep optimization: screening and treatment for OSA, sleep hygiene, and circadian rhythm alignment.
  • Stress physiology: HPA-axis support and mindfulness practices to reduce hyperphagic responses.
  • Environmental exposures: addressing ultra-processed foods and sedentary hazards.

Why integrate functional medicine: Complex obesity phenotypes benefit from personalized, root-cause investigations that guide targeted interventions. Combining internal medicine safety with functional assessments yields holistic plans that are both evidence-based and individualized.

Sensitivity Training and Bias Reduction: Creating a Respectful, Person-First Environment

Patients with obesity frequently encounter stigma in healthcare settings. Reducing bias improves trust, adherence, and outcomes. Shame reduces engagement in care and heightens stress physiology. Positive framing, by contrast, increases adherence and reduces defensiveness.
Core Elements:

  • Use person-first language: We say “a person with obesity,” not “an obese person.” We adopt neutral descriptors like “severe obesity, class 3” instead of “morbid obesity.” In notes, we document “barriers to adherence identified” instead of “noncompliant.”
  • Eliminate stigmatizing imagery: We avoid pictures that show individuals with heads cropped off or engaging in stereotypical behaviors. We choose empowering visuals of people of diverse body sizes engaged in daily life.
  • Provide appropriate equipment: large blood pressure cuffs, sturdy and comfortable seating, accessible exam tables, and weight-inclusive gowns.
  • Privacy and dignity in weigh-in procedures: Offer “no-scale” days and ask patients if they want to know their weight.
  • Staff training on obesity as a chronic disease, not a moral failing. We use role-playing to practice person-first language and active listening.

Why it matters: A respectful environment fosters strong therapeutic relationships and long-term success. Safety and comfort reduce anxiety, improving heart rate variability and perceived control.

Mastering the Fundamentals: Time-Based Billing vs. Medical Decision-Making (MDM)

One of the most critical aspects of building a sustainable obesity management practice is understanding how to bill for your services accurately and ethically. Two primary pathways exist for billing Evaluation and Management (E&M) services: billing by time and billing by medical decision-making (MDM).

Patient StatusCPT CodeTotal Time Required for Time-Based Billing
New Patient9920215-29 minutes
9920330-44 minutes
9920445-59 minutes
9920560-74 minutes
Established Patient9921210-19 minutes
9921320-29 minutes
9921430-39 minutes
9921540-54 minutes

Unpacking Time-Based Billing

When you bill based on time, total documented time determines the CPT code. This method is often ideal for obesity-focused visits because much of the encounter focuses on counseling, education, and behavioral coaching. “Time” includes total time spent by the billing provider on the date of the encounter, including pre-visit chart review, face-to-face time, and post-visit documentation and order placement.
A Practical Example of Time-Based Billing:
At the end of my visit note, I add a time attestation statement:
“I spent a total of 33 minutes today on this patient’s care. This time was spent on:

  • Chart Review (pre-visit): 3 minutes reviewing prior labs and specialist notes.
  • History, Exam, and Ordering (during visit): 5 minutes for the face-to-face examination and order entry.
  • Treatment Planning & Counseling (during visit): 20 minutes for extensive counseling on nutritional strategies, medication mechanisms, and behavioral goal-setting.
  • Updating Chart (post-visit): 5 minutes to finalize documentation and send prescriptions.

Total Time = Time in minutes.
This total time in minutes for an established patient directly correlates with a CPT code 99214.

Decoding Medical Decision-Making (MDM)

The second option for billing is based on the complexity of your Medical Decision-Making (MDM), which is determined by:

  1. Number and Complexity of Problems Addressed
  2. Amount and/or Complexity of Data to Be Reviewed and Analyzed
  3. Risk of Complications and/or Morbidity or Mortality of Patient Management

To bill at a certain level, you must meet the requirements for that level in at least two of these three categories. A key element is that any visit involving prescription drug management—initiating, continuing, or modifying any prescription medication—signals at least moderate risk, which supports a Level 4 code (99214). This is particularly relevant for short telehealth visits where a medication dose is changed.

ICD-10-CM Coding and Documentation

Accurate coding is not just about reimbursement; it’s about representing the true burden of disease. The 2024 ICD-10-CM updates improve accuracy and support stigma-free language.

  • Always pair E codes (obesity) with Z codes (BMI). If documenting obesity, record a same-day BMI and link the corresponding Z code.
  • Use specific codes for pediatric and adult patients that reflect BMI class and complications (e.g., hypertension, type 2 diabetes, dyslipidemia).
  • Document medical necessity by detailing functional limitations, comorbidity risks, and health impact.

Expanding Your Services: Beyond the Standard Office Visit

To create a comprehensive program, we must think beyond traditional E&M visits. Several other billable service categories can enhance patient outcomes and practice sustainability.

Service CategoryPayerAssociated CPT/HCPCS CodesKey Function
Intensive Behavioral Therapy (IBT)MedicareG0447, G0473Behavioral change for sustained weight loss
Preventive Care CounselingCommercial99401-99404Behavioral counseling for risk factor reduction
Chronic Care Management (CCM)Medicare99490, 99491, 99487, 99489Non-face-to-face care coordination
Remote Patient Monitoring (RPM)Medicare/Commercial99453, 99454, 99457, 99458Remote data collection and management

Medicare Intensive Behavioral Therapy (IBT) for Obesity

IBT is a specific Medicare benefit for behavioral change interventions. The key code is G0447 (face-to-face behavioral counseling for obesity, 15 minutes). This is not an E&M visit; the focus must be exclusively on behavior, nutrition, and exercise, with no discussion of comorbidities or medication management. Qualified staff, such as an RN or health coach, can render these services under your direct supervision, freeing you for more complex E&M visits.

Preventive Screening and Counseling for Commercial Insurance

For commercial insurance patients, Preventive Counseling codes (99401-99404) serve a similar function. These time-based sessions focus on diet, exercise, and lifestyle modifications. Unlike IBT, you cannot bill these codes on the same day as a standard E&M visit.

Medicare Chronic Care Management (CCM)

CCM compensates you for the non-face-to-face time yoTimed your staff spends coordinating care for patients with two or more chronic conditions. This includes phone calls, prescription refills, and reviewing records between appointments. Using codes like 99490 (first 20 minutes of clinical staff time) provides a framework for monthly check-ins, keeping patients engaged and accountable.

The Future is Now: Remote Patient Monitoring (RPM)

RPM leverages technology like 5G-enabled smart scales, blood pressure cuffs, and glucometers to gather objective data between visits. The device must be FDA-approved and paid for by the practice. Key codes include 99453 (setup), 99454 (device supply and data transmission for 16+ days a month), and 99457 (first 20 minutes of management time). RPM provides real-time data and accountability, which is phenomenal for engagement.

Crafting the Patient Journey: A 6-Month Care Plan Roadmap

Together, we can create a high-touch care plan that fosters accountability and allows rapid course correction. The evidence overwhelmingly supports that patients with frequent contact achieve the best outcomes.

The Commercial Insurance Patient Journey

  • Visit 1 (Week 1): Initial Consultation (E&M Visit, 99204/99205).
  • Monthly Follow-up Visits: E&M visits for medical management (99214).
  • Bi-Weekly Preventative Counseling Visits: 15-30 minute sessions with an RN/coach (99401/99402 on separate days).
  • Ongoing RPM: Monthly data uploads and staff follow-up (99454 + 99457).

This model provides a touchpoint with your clinic every single week.

The Medicare Patient Journey

  • Visit 1 (Week 1): Initial Consultation (E&M Visit, 99204/99205) plus a 15-minute IBT session (G0447) with a -25 modifier.
  • Monthly Follow-up Visits: E&M visits for medical management (99214).
  • Weekly/Bi-Weekly IBT Visits: 15-minute behavioral sessions with staff (G0447).
  • Ongoing CCM and RPM: Non-face-to-face support (99490) and remote data management (99454 + 99457).

This high-touch model provides weekly contact, robust support, and continuous education, which are crucial for long-term success.

Final Thoughts: A Compassionate, Evidence-Based Path Forward

Obesity care thrives in multidisciplinary, patient-centered environments. By combining internal medicine oversight, integrative chiropractic, functional medicine, behavioral coaching, and thoughtful program design, clinics can deliver durable improvements in health and quality of life. Our comprehensive model at Injury Medical Clinic, P.A. values empathy, science, and practicality—meeting patients where they are and supporting them as partners in their journey.
Building a practice that effectively manages obesity is complex but incredibly rewarding. By mastering these billing and care strategies, you can build a program that is not only clinically effective but also financially sustainable, helping more people for years to come.
For more on my clinical perspectives and practice focus, visit:
ChiroMed site: [https://chiromed.com/]
LinkedIn profile: [https://www.linkedin.com/in/dralexjimenez/]

References

SEO Tags:
Obesity Management, Medical Billing and Coding, Time-Based Billing, Medical Decision Making, CPT Codes, 99214, 99204, Integrative Care, Chiropractic Care, Dr. Alex Jimenez, Dr. Maria Cardenas, Functional Medicine, Chronic Care Management, CCM, Remote Patient Monitoring, RPM, Intensive Behavioral Therapy, IBT, Preventative Counseling, GLP-1, Weight Loss, Healthcare Administration, El Paso Texas, Injury Medical Clinic, Multidisciplinary Clinic, Patient Care Plan, E&M Coding, Healthcare Reimbursement, person-first language, weight bias reduction, clinical environment accessibility, ICD-10 coding, obesity billing by time, nTimetigmatizing language, BMI Z codes, E codes obesity, risk adjustment, rehabilitation for obesity, personal injury obesity care, sleep apnea and obesity, hypertension and obesity, diabetes and obesity, musculoskeletal pain obesity

Legal Peptide Therapy and Integrative Chiropractic Care in El Paso

Legal Peptide Therapy and Integrative Chiropractic Care in El Paso

Abstract

Peptide therapy is becoming an important topic in integrative medicine, metabolic health, weight management, hormone care, and physical recovery. However, not every peptide sold online or discussed on social media is FDA-approved or appropriate for medical treatment. Legal peptide use depends on the specific medication, its FDA status, how it is prescribed or compounded, the patient’s medical needs, and federal and state laws.

At ChiroMed – Integrated Medicine in El Paso, Texas, an integrative model can bring medical evaluation, nurse practitioner services, chiropractic care, functional medicine, nutrition, and rehabilitation together. Medical providers handle evaluation and prescription decisions within their professional authority, while chiropractic care focuses on biomechanics, joint function, movement, strength, and musculoskeletal rehabilitation. This article explains how these roles can work together while keeping peptide treatment patient-centered, medically appropriate, and within professional scope.

Legal Peptide Therapy and Integrative Chiropractic Care in El Paso

What Is Legal Peptide Therapy?

Peptides are short chains of amino acids. Amino acids are the building blocks of proteins, and many naturally occurring peptides act as signals inside the body.

Some peptide-based medicines have established medical uses. Others remain experimental or have limited evidence in people.

The important question is not simply, “Are peptides legal?”

A better question is:

Is this specific peptide legally available and medically appropriate for this particular patient, from this particular source, and for this particular use?

Legal medical use can include several different situations:

  • An FDA-approved peptide-based drug used for an approved indication
  • An FDA-approved medication prescribed for a medically appropriate off-label use
  • A compounded medication prepared under applicable federal and state requirements
  • An investigational drug being used through an authorized research pathway

These categories are not interchangeable.

The FDA makes an especially important distinction regarding compounded medications. Compounded medications can serve a medical need for certain patients, but they are not FDA-approved. The FDA does not review each compounded medication for safety, effectiveness, or manufacturing quality before it reaches the patient (U.S. Food and Drug Administration [FDA], 2026a).

Why “Research Peptides” Are Different

Patients may see peptides advertised online with labels such as:

  • “Research use only”
  • “Not for human consumption”
  • “Laboratory use only”

These labels should not be confused with an FDA-approved prescription medication or a lawfully prepared compounded prescription.

The fact that a chemical can be purchased through a website does not establish that it is approved or appropriate for human treatment.

This is especially important because peptide regulation continues to change. Different substances may have different FDA classifications, compounding restrictions, safety concerns, and available evidence.

Under Sections 503A and 503B of the Federal Food, Drug, and Cosmetic Act, the FDA limits which bulk drug substances may be used. These lists and regulatory policies can change as new evidence becomes available (FDA, 2026b).

For this reason, healthcare professionals should evaluate the current regulatory status of the specific peptide rather than assuming that all peptides fall into the same category.

Compounded Peptides Require Special Attention

Compounding can be valuable when a commercially available FDA-approved medication cannot meet a patient’s individual medical need.

For example, a patient might need a different dosage form because of an allergy or another clinical concern.

However, compounding does not automatically make a peptide legal, FDA-approved, or appropriate.

Under federal rules, Section 503A compounders face requirements about which bulk substances they may use. Section 503B outsourcing facilities also operate under specific limits regarding bulk substances and drug shortages (FDA, 2026b).

Patients should understand an important difference:

An FDA-approved medication and a compounded version of a medication are not the same regulatory product.

The FDA states that compounded drugs have not gone through FDA premarket approval for safety, effectiveness, and quality (FDA, 2026a).

This makes pharmacy selection, clinical justification, documentation, dosing, patient education, and follow-up especially important.

What the New Mexico Board of Nursing Says

The September 2026 New Mexico Board of Nursing Peptide Therapies FAQ provides a useful example of how one state nursing board is approaching this rapidly changing field.

The Board emphasizes that its FAQ provides general interpretation only. It specifically states that the document is not a legal opinion and cannot be cited as legal authority.

The guidance states that APRNs prescribing compounded medications should remain within their education, experience, population focus, and prescriptive authority. It also emphasizes a valid provider-patient relationship, appropriate history and physical examination, clinical justification, informed consent, monitoring, and documentation.

The Board also recommends that clinicians:

  • Make sure compounding is legally permitted
  • Use appropriately licensed pharmacies
  • Explain when a patient is receiving a compounded medication
  • Document the reason for using the compounded product
  • Avoid questionable or unverified sources

The New Mexico guidance is useful for understanding professional safety principles, but ChiroMed is located in Texas. Therefore, Texas law and Texas professional licensing requirements govern care delivered in Texas.

Chiropractic and Medical Roles Must Remain Clear in Texas

ChiroMed describes itself as an integrated healthcare practice bringing chiropractic care, nurse practitioner services, rehabilitation, nutrition, and other healthcare disciplines together in one setting.

Clear professional roles are important in this type of practice.

Under Texas Occupations Code §201.002, chiropractic practice includes evaluation of the biomechanical condition of the spine and musculoskeletal system and nonsurgical, noninvasive procedures intended to improve musculoskeletal biomechanics.

The same law states that chiropractic practice does not include prescribing controlled substances, dangerous drugs, or other prescription drugs.

Therefore, a clinician cannot prescribe peptides under a Texas chiropractic license alone.

This distinction is especially important for a clinician such as Dr. Alexander Jimenez, DC, APRN, FNP-BC, who holds both chiropractic and advanced practice nursing credentials.

His chiropractic license supports chiropractic and musculoskeletal care. Medical evaluation and prescription decisions must be performed under the appropriate APRN authority and applicable Texas rules.

The Nurse Practitioner’s Role in Peptide Therapy

Texas APRNs who prescribe medications must meet Texas requirements for prescriptive authority.

Texas law allows qualified APRNs and physicians to enter into prescriptive authority agreements. These agreements define the practice setting, medication categories, consultation, communication, quality assurance, and referral processes.

This makes the medical side of peptide therapy different from chiropractic treatment.

Depending on the patient’s needs, the medical evaluation may include:

  • Medical history
  • Current medications and supplements
  • Physical examination
  • Laboratory testing
  • Contraindications and risk factors
  • Diagnosis
  • Treatment alternatives
  • Medication selection
  • Informed consent
  • Follow-up laboratory testing
  • Response to treatment
  • Side-effect monitoring

Do not select a peptide simply because it is popular.

The patient’s diagnosis, health history, goals, risks, available evidence, and legal treatment options should guide the medical decision.

ChiroMed’s Multidisciplinary Model

At ChiroMed – Integrated Medicine, the goal is to bring different parts of healthcare together rather than treating each problem in isolation.

ChiroMed describes its services as including chiropractic care, nurse practitioner services, rehabilitation, nutrition, and integrative approaches for patients with musculoskeletal, injury, chronic pain, and wellness concerns.

The multidisciplinary team also includes Dr. Maria Guadalupe Cardenas, MD, whom ChiroMed identifies as a board-certified internal medicine physician, Medical Director, and Collaborative Physician with more than four decades of experience.

Public NPI information lists Dr. Maria Guadalupe Cardenas as an internal medicine physician in El Paso with NPI 1164426748 and Texas medical license J2933.

Within this model, Dr. Cardenas provides medical direction and internal medicine experience alongside Dr. Jimenez’s work in advanced practice nursing, chiropractic care, functional medicine, injury management, and rehabilitation.

The goal is coordinated care, while each clinician works within the appropriate professional scope.

How Chiropractic Care Can Complement Peptide Treatment

Chiropractic treatment should not be promoted as making a peptide medication more powerful.

Instead, these treatments may address different parts of a patient’s overall health and recovery.

A medically managed therapy may address a specific metabolic, hormonal, or medical problem.

Chiropractic and rehabilitation care can focus on the patient’s ability to move and function.

At ChiroMed, integrative chiropractic care may support:

  • Joint mobility
  • Spinal biomechanics
  • Range of motion
  • Posture
  • Muscle balance
  • Functional strength
  • Neuromuscular coordination
  • Progressive exercise
  • Return to normal activities
  • Injury rehabilitation

ChiroMed’s published clinical model emphasizes connecting medical evaluation with chiropractic care and rehabilitation rather than replacing one healthcare profession with another.

This can be particularly useful when a patient has both a medical concern and a musculoskeletal limitation.

For example, a patient receiving medical weight-management treatment may need help maintaining muscle mass, increasing activity, and improving physical function.

Strength and Muscle Preservation Matter

Muscle health deserves special attention during some medical weight-management programs.

The New Mexico Board of Nursing guidance recommends attention to:

  • Adequate protein
  • Resistance exercise
  • Preservation of lean body mass
  • Vitamin and nutrient intake
  • Long-term lifestyle changes

Rehabilitation and integrative chiropractic care may fit naturally into a broader treatment plan.

A patient with back pain, knee pain, poor mobility, or an old injury may find exercise difficult. Treating mechanical barriers and developing a progressive rehabilitation program may help that person become more physically active.

The goal is not simply weight loss.

It is to help patients maintain:

strength + mobility + muscle + function.

Clinical Observations From Dr. Alexander Jimenez

In his clinical writings, Dr. Alexander Jimenez, DC, APRN, FNP-BC, CCST, CFMP, IFMCP, ATN, describes health and recovery through a systems-based approach.

Instead of relying on one treatment, his clinical model connects areas such as:

  • Chiropractic biomechanics
  • Functional medicine
  • Nutrition
  • Musculoskeletal rehabilitation
  • Laboratory findings when appropriate
  • Strength and conditioning
  • Injury recovery
  • Medical evaluation
  • Lifestyle modification

This philosophy is also reflected throughout ChiroMed’s published material, which describes integrated injury care as a combination of medical evaluation, chiropractic care, functional medicine, rehabilitation, and other supportive options.

Peptide treatment, when medically appropriate and legally available, can therefore be one part of a larger care plan, not a replacement for good nutrition, exercise, rehabilitation, sleep, or medical monitoring.

A Patient-Centered Approach to Peptide Therapy

Responsible peptide treatment should begin with the patient—not with a product.

Before considering treatment, the healthcare team should determine:

  • What problem is being treated?
  • Is there an established diagnosis?
  • Is the medication FDA-approved?
  • If it is compounded, why is compounding medically appropriate?
  • Is there reasonable evidence supporting its use?
  • What are the risks and alternatives?
  • Does the patient’s medical history create contraindications?
  • What monitoring will be needed?
  • Who is responsible for prescribing and follow-up?
  • Is the pharmacy properly licensed?
  • Is the treatment permitted under current federal and state requirements?

The New Mexico Board’s guidance similarly emphasizes history, examination, laboratory testing when indicated, informed consent, documentation, treatment response, adverse effects, and follow-up.

Integrating Medicine, Movement, and Recovery at ChiroMed

The future of integrative healthcare is not about one profession trying to perform every type of treatment.

It is about different professionals contributing their expertise to the same patient.

At ChiroMed – Integrated Medicine in El Paso, chiropractic care can address biomechanics, movement, spinal and joint health, physical strength, and rehabilitation. Advanced practice nursing can provide appropriate medical evaluation and treatment within APRN scope and Texas prescriptive authority. Internal medicine leadership can add another layer of medical direction and clinical coordination.

Nutrition, functional medicine, personal injury care, and rehabilitation can then support the patient’s larger goals.

This creates a practical model:

Medical care addresses medical needs.
Chiropractic care addresses biomechanics and musculoskeletal function.
Rehabilitation develops strength and movement.
Nutrition provides the building blocks for recovery.
Medical oversight helps keep the entire plan appropriate and coordinated.

Peptide science will continue to change. Some peptide-based medications already have established medical roles, while other substances remain investigational, restricted, or supported by limited human evidence.

For patients and clinicians alike, the safest approach is to focus on evidence, professional scope, current regulations, appropriate medical evaluation, legitimate pharmacy sources, and careful follow-up.

At ChiroMed, integrated care means looking beyond one medication or one adjustment and building a treatment plan around the health and functional needs of the whole person.


References

ChiroMed – Integrated Medicine. (2026a). Integrated medicine services in El Paso, Texas.

ChiroMed – Integrated Medicine. (2026b). ChiroMed – Integrated Medicine: Holistic healthcare in El Paso, TX.

ChiroMed – Integrated Medicine. (2026c). Integrated injury care in El Paso, TX.

ChiroMed – Integrated Medicine. (2026d). Peptide therapy, nutrition, and integrative chiropractic care.

Food and Drug Administration. (2026a). Compounding and the FDA: Questions and answers.

Food and Drug Administration. (2026b). Bulk drug substances used in compounding under Section 503A of the FD&C Act.

Food and Drug Administration. (2026c). Human drug compounding.

Jimenez, A. (2026). Peptide therapy, nutrition, and chiropractic care explained.

New Mexico Board of Nursing. (2026). Peptide therapies: Clinical practice frequently asked questions.

Texas Board of Nursing. (2026). APRN practice frequently asked questions.

Texas Legislature. (2026a). Texas Occupations Code Chapter 157: Authority of physician to delegate certain medical acts.

Texas Legislature. (2026b). Texas Occupations Code Chapter 201: Chiropractors.

Integrative Strategies to Consider for Insulin Resistance


Unlock the benefits of integrative strategies for insulin resistance and take charge of your health today.

Abstract

For decades, the standard approach to managing insulin resistance has centered on dietary restrictions, often with frustratingly limited success. Many individuals find that even strict low-carbohydrate, ketogenic, or carnivore diets fail to resolve the underlying metabolic dysfunction fully. This educational post explores the deeper physiological reasons for this phenomenon, moving beyond surface-level dietary changes to address the root causes of metabolic inflexibility. As Dr. Alex Jimenez, I will guide you through the cellular mechanisms that perpetuate insulin resistance, including compromised mitochondrial function, chronic inflammation, and cellular “deafness” to insulin signals. We will explore the latest scientific findings from leading researchers, highlighting innovative therapeutic agents like 5-amino-1MQ, retatrutide, and MOTS-c, which show remarkable promise in restoring insulin sensitivity and metabolic health. This discussion will also detail a practical “daily audit” protocol, integrating strategic nutrition with continuous glucose monitoring to empower you with real-time feedback on your metabolic status. We’ll also explain how our multidisciplinary practice at Injury Medical Clinic PA integrates advanced functional medicine with chiropractic care and medical oversight from our esteemed Medical Director, Dr. Maria Guadalupe Cardenas, MD, to provide a comprehensive, personalized approach to reversing insulin resistance and reclaiming your health.


A Multidisciplinary Approach to Whole-Body Health at Injury Medical Clinic

Before we dive into the complex world of cellular metabolism, it’s important to understand the care framework we provide at our clinic. My name is Dr. Alex Jimenez, and I hold certifications as a Doctor of Chiropractic (DC), an Advanced Practice Registered Nurse (APRN) and Family Nurse Practitioner (FNP-BC), a Certified Functional Medicine Practitioner (CFMP), and an Institute for Functional Medicine Certified Practitioner (IFMCP), among other advanced credentials in anti-aging and clinical cellular science. Our practice, Injury Medical Clinic PA, also known as Mission Plaza Injury Medical Clinic, is located in El Paso, Texas, and is built on a foundation of integrative, multidisciplinary care.

I am honored to work alongside Dr. Maria Guadalupe Cardenas, MD, our Medical Director and Collaborative Physician. Dr. Cardenas is Board Certified in Internal Medicine and brings over 40 years of invaluable experience as an internist to our team. Her extensive medical expertise (NPI #1164426749, Texas MD License #J2933) is fundamental to our ability to offer a truly holistic patient experience. This collaborative model, where a chiropractor with advanced training in functional medicine works alongside a seasoned medical doctor, allows us to bridge gaps between healthcare disciplines. We combine the strengths of chiropractic care—focusing on musculoskeletal integrity, nervous system function, and structural health—with the diagnostic precision and medical oversight of internal medicine.

Our team integrates:

  • Chiropractic Care: We address spinal and joint misalignments (subluxations) that can interfere with nerve signaling, which is crucial for organ function and metabolic regulation.
  • Medical Oversight: Dr. Cardenas provides essential medical direction, overseeing patient cases, managing comorbidities, and ensuring all treatments are safe and medically appropriate.
  • Functional Medicine: We use advanced diagnostic testing to identify the root causes of chronic disease, such as nutrient deficiencies, hormonal imbalances, and gut dysbiosis.
  • Personal Injury & Rehabilitation: We specialize in helping patients recover from injuries, using a combination of physical therapies, chiropractic adjustments, and rehabilitative exercises to restore function and reduce pain.

This synergistic model ensures that when we address a complex condition like insulin resistance, we look at the whole person—not just their blood sugar numbers. We consider their structural health, cellular biology, lifestyle, and unique biochemistry to create a personalized, effective treatment plan.


The Frustration of Failed Diets: Why Insulin Resistance Persists

One of the most common frustrations I hear from patients is, “Doctor, I’ve tried everything. I cut out carbs, I went keto, I even did the carnivore diet, but I’m still not getting better.” They are often disheartened, feeling like their body has betrayed them despite their best efforts. The reality is that diets alone often fail to reverse severe, long-standing insulin resistance. This is not a failure of willpower; it is a failure to understand the deep-seated biological adaptations that have occurred over years, or even decades.

Insulin resistance

Imagine spending thirty years in a state of hyperinsulinemia—a condition where your pancreas is constantly pumping out high levels of insulin to manage blood glucose. Over time, your body’s cells, receptors, and mitochondria become, for lack of a better term, “trashed.” The entire system is damaged and dysregulated.

Let’s break down why this happens:

Muscle Glycogen Stores and Metabolic Inflexibility

From a basic biological standpoint, our muscles are a primary storage site for glucose, stored as glycogen. In an active individual, these glycogen stores are regularly depleted through exercise and then refilled after a meal. This is a healthy, dynamic process. However, in a sedentary lifestyle, these muscle glycogen stores remain consistently full.

Think of it like a gas tank that is never emptied. If the tank is already full, you can’t add more fuel. Similarly, if your muscle cells are packed with glycogen, they don’t need the glucose circulating in your bloodstream. They effectively put up a “No Vacancy” sign. They become insulin resistant because they are signaling that they don’t need any more fuel. Even if you switch to a low-carb, keto, or carnivore diet, muscles can remain stubbornly resistant if they aren’t metabolically challenged through physical activity. The cells have developed metabolic inflexibility; they have lost the ability to switch efficiently between burning carbohydrates and burning fat for energy.

The Liver’s Role: A Rogue Glucose Factory

While the muscles are refusing glucose, the liver becomes trapped in a vicious cycle of its own. In a state of chronic hyperinsulinemia, the liver often becomes a site for fat accumulation, a condition known as non-alcoholic fatty liver disease (NAFLD). A fatty liver is a dysfunctional liver. It becomes hyperresponsive to the hormone glucagon (which tells the liver to release glucose) and simultaneously resistant to insulin (which tells the liver to stop releasing glucose).

This creates a paradoxical and dangerous situation. Even when you diligently cut sugar and processed carbohydrates from your diet, your liver keeps pumping large amounts of glucose into the bloodstream. This process is called gluconeogenesis—literally, “the creation of new glucose.” The liver manufactures glucose from non-carbohydrate sources, such as amino acids and lactate.

So you can eat zero carbohydrates, yet your blood sugar can remain elevated because your liver has turned into a rogue glucose factory. This is a critical point that many people miss. The problem is no longer just what we’re eating; it’s deep-seated dysfunction within the liver. This state will persist until the excess visceral fat is mobilized and the liver is metaphorically “unclogged.” That’s why insulin resistance can be such a bear to resolve. It’s a deeply entrenched physiological state, not just a simple dietary problem.


A Deeper Look: Mitochondrial Dysfunction and Cellular Deafness

To truly understand insulin resistance, we have to zoom in from the organ level to the cellular and even the subcellular level. The real battle is being fought inside your cells, specifically within the mitochondria and at the insulin receptor sites.

Lipid Overload and Impaired Insulin Signaling

When you are chronically hyperinsulinemic, your body is in a constant state of “energy storage.” This leads to the accumulation of lipids (fats) not just in your fat cells, but also inside other cells, such as muscle and liver cells. These intracellular lipid deposits, known as intramyocellular lipids, directly interfere with the insulin signaling pathway.

Here’s how it works: When insulin binds to its receptor on the cell surface, it initiates a complex cascade of signals inside the cell. This cascade is like a series of dominoes falling, ultimately activating glucose transporter type 4 (GLUT4). GLUT4 is the protein that moves to the cell membrane and creates a channel for glucose to enter the cell. In a healthy cell, this process is smooth and efficient.

However, when lipids accumulate inside the cell, they create metabolic byproducts—like diacylglycerol (DAG) and ceramides—that disrupt this signaling cascade. These lipid metabolites effectively jam the machinery. They prevent the dominoes from falling. As a result, even though insulin is present and binding to its receptor, the signal to bring GLUT4 to the surface is blocked. Glucose cannot get into the cell.

I often describe this to my patients as cellular deafness. The cell is being screamed at by insulin, but it can’t “hear” the message. It’s like trying to unlock a door with the wrong key, or a bent key. The lock (the receptor) is there, the key (insulin) is there, but the internal mechanism is broken.

The Problem with Standard Lab Tests: Why HbA1c is Deceiving

This leads us to another critical point of confusion: standard lab testing. For years, the Hemoglobin A1c (HbA1c) test has been the gold standard for diagnosing and monitoring diabetes. The HbA1c measures the percentage of your hemoglobin (the protein in red blood cells that carries oxygen) that is coated with sugar (glycated). Because red blood cells live about three months, HbA1c gives you a rough average of your blood sugar over the preceding 90 days.

However, in the context of early to moderate insulin resistance, HbA1c is a totally useless, lagging indicator. At best, it lags three months behind real-time metabolic reality. I see severely insulin-resistant patients walk into my clinic every week with a “normal” HbA1c. How is this possible?

It’s possible because the pancreas is a remarkably resilient organ, at least initially. As the cells become more resistant to insulin, the pancreas compensates by working overtime, dumping gallons of insulin into the bloodstream to force the glucose into the cells. The cells are literally drowning in insulin, but because the pancreas is fighting so hard, the blood glucose levels may remain in the normal range for years. The HbA1c looks fine, but beneath the surface, the pancreas is working itself to death. This is compensated insulin resistance, and it’s a ticking time bomb. Eventually, the pancreatic beta cells will become exhausted and begin to fail, at which point blood glucose will skyrocket, and the HbA1c will finally reflect the long-standing disease process. By then, significant damage has already been done.

A Better Metric: HOMA-IR

A far more sensitive and immediate tool for assessing insulin resistance is the Homeostatic Model Assessment of Insulin Resistance (HOMA-IR). This calculation uses a simple formula that accounts for both your fasting glucose and fasting insulin levels.

HOMA-IR = (Fasting Glucose [mg/dL] x Fasting Insulin [μU/mL]) / 405

This score gives us a direct snapshot of how hard your pancreas is working to maintain a normal blood sugar level. In our practice, we consider a HOMA-IR score over 1.0 to be an indication of early insulin resistance. A score over 1.9 indicates significant resistance, and a score over 2.9 is often correlated with a high risk of developing type 2 diabetes. HOMA-IR lets us detect metabolic dysfunction years, or even decades, before HbA1c becomes abnormal. It allows us to be proactive instead of reactive.

You must stop treating insulin resistance as if it’s merely a weight loss goal. If you focus only on the number on the scale, you are going to lose the battle. We need to address the underlying physiology: inflammation, mitochondrial issues, and cellular deafness.


Is Intermittent Fasting the Ultimate Weight Loss Hack?- Video


The Chiropractic Link: Nervous System Integrity and Metabolic Function

At this point, you might be wondering, “What does chiropractic care have to do with insulin and mitochondria?” The connection lies in the body’s master control system: the nervous system. The brain, spinal cord, and peripheral nerves coordinate and regulate every single function in your body, including metabolism.

The autonomic nervous system (ANS) has two main branches: the sympathetic (“fight or flight”) and the parasympathetic (“rest and digest”). A healthy metabolism depends on a proper balance between these two branches. Chronic stress—be it physical, chemical, or emotional—can lead to a state of sympathetic dominance, where the “fight or flight” response is perpetually activated. This state is characterized by the release of stress hormones like cortisol and adrenaline, which directly promote insulin resistance by signaling the liver to release glucose and making peripheral cells less sensitive to insulin.

Chiropractic adjustments work to restore proper motion and alignment to the spine, particularly in the upper cervical and thoracic regions where key autonomic nerve centers are located. By correcting vertebral subluxations—misalignments that can interfere with nerve function—we can help down-regulate the sympathetic nervous system and up-regulate the parasympathetic nervous system. This shift helps to:

  • Reduce circulating stress hormones.
  • Improve blood flow to internal organs, including the pancreas and liver.
  • Enhance the body’s overall ability to “rest, digest, and repair.”

By improving neurological communication between the brain and the body’s metabolic organs, chiropractic care can help create a physiological environment more conducive to healing and restoring insulin sensitivity. It is a foundational piece of the puzzle, ensuring that the body’s internal signaling pathways are clear and functioning optimally. This is a core component of how our integrated model at Injury Medical Clinic supports metabolic recovery.


Hacking the System: Novel Therapeutics to Restore Cellular Function

While lifestyle interventions like diet, exercise, and chiropractic care are foundational, for many individuals with deep-seated insulin resistance, they may not be enough to overcome the profound cellular dysfunction. This is where cutting-edge functional medicine comes in, using targeted compounds that can directly address the biochemical roadblocks we’ve discussed. Let’s explore the science behind some of the most promising agents.

Replenishing the Engine: The Role of NAD+ and 5-amino-1MQ

Let’s get into the biology for a second. One of the most critical molecules in your entire body is Nicotinamide Adenine Dinucleotide (NAD+). NAD+ is a vital cofactor—a “helper molecule”—for hundreds of enzymatic reactions. Think of it as the spark plug for your cellular engine. It is an essential electron carrier in ATP synthesis (energy production) in the mitochondria. It’s also crucial for DNA repair, gene expression, and immune function. You cannot run your biology without it.

Here’s the problem: In chronic hyperinsulinemia and inflammation, an enzyme called NNMT (Nicotinamide N-methyltransferase) becomes significantly overactive. NNMT’s primary job is to process and eliminate excess nicotinamide (a form of vitamin B3). However, when it’s in overdrive, it wreaks havoc on your NAD+ levels. It constantly consumes NAD+ by converting it to a byproduct called N1-methylnicotinamide (MNA), effectively draining your cellular battery. This constant NAD+ depletion causes mitochondria to fail and your metabolism to tank.

This is where a remarkable compound called 5-amino-1MQ comes in. 5-amino-1MQ is a small, membrane-permeable molecule that potently inhibits the NNMT enzyme. By blocking NNMT, it prevents excessive NAD+ breakdown. Simply put, it stops the leak in the bucket, allowing your cellular NAD+ pool to be replenished. It floods the system with the critical cofactor it needs to function properly.

The research on this is incredibly exciting.

  • A landmark study published in Cell Metabolism in 2023 showed that subcutaneous administration of 5-amino-1MQ in overweight and obese individuals significantly improved insulin sensitivity, as measured by HOMA-IR (Agerholm et al., 2023). The study found a 34% improvement in insulin sensitivity, along with reductions in body weight, fat mass, and cholesterol levels. This provides powerful evidence that targeting the NNMT enzyme can directly reverse key aspects of metabolic syndrome.

By restoring NAD+ levels, 5-amino-1MQ helps to “reboot” the mitochondria, improve energy production, and make cells more responsive to insulin signaling. It is a prime example of using targeted biochemical intervention to fix a specific, identified dysfunction.

Rewriting the Script: Retatrutide and Full Insulin Independence

For decades, the goal for many type 2 diabetes patients has been “management”—keeping blood sugar under control with a cocktail of medications. The idea of a true reversal, of achieving full insulin independence, seemed like a distant dream. That is, until now.

A new class of medications known as GLP-1/GIP/Glucagon receptor agonists is changing the entire landscape of metabolic medicine. One of the most powerful of these is retatrutide. This molecule is a triple agonist, meaning it activates three different hormone receptors involved in metabolic regulation:

  1. GLP-1 (Glucagon-like peptide-1): Enhances insulin secretion, slows gastric emptying, and promotes satiety.
  2. GIP (Glucose-dependent insulinotropic polypeptide): Also enhances insulin secretion and appears to play a role in fat metabolism.
  3. Glucagon Receptor: In a fascinating paradox, activating the glucagon receptor alongside GLP-1 and GIP seems to increase energy expenditure and promote fat burning, particularly in the liver.

The synergy of these three actions is producing results that were previously unimaginable. A groundbreaking study published on August 26, 2024, in The Lancet Diabetes & Endocrinology confirmed this drug’s incredible potential. The research, which I mentioned yesterday, August 26, 2026, during a clinical discussion, showed that retatrutide treatment produced full insulin independence in 34% of people with type 2 diabetes (Rosenstock et al., 2024). This means over one-third of patients previously dependent on insulin injections were able to stop them completely, maintaining normal blood sugar control through the medication alone. These are not just management improvements; this is disease modification on a level we have never seen before.

Building a Better Powerhouse: The Promise of MOTS-c

While replenishing NAD+ helps repair existing mitochondria, what if we could build entirely new, more efficient ones? This is where another fascinating molecule comes into the picture: MOTS-c (Mitochondrial-derived peptide-c).

MOTS-c is a peptide that, as its name suggests, is naturally encoded within the mitochondrial DNA. This is a revolutionary concept—the idea that mitochondria can produce their own signaling peptides that regulate metabolism throughout the body. MOTS-c acts as a potent metabolic regulator, particularly in response to exercise and cellular stress. Its primary functions include:

  • Enhancing glucose uptake and utilization in muscle cells.
  • Improving fatty acid oxidation (the ability to burn fat for fuel).
  • Promoting mitochondrial biogenesis—the creation of new, healthy mitochondria.

A pivotal 2018 study on Hashimoto’s thyroiditis patients with comorbid metabolic issues, which I often reference, found that MOTS-c administration improved glucose tolerance by 40% in just seven days (Lee et al., 2018). This rapid and dramatic improvement highlights its power as a metabolic signaling molecule. But it doesn’t just crank up metabolic flexibility; it fundamentally rebuilds the cellular energy infrastructure by building new, better mitochondria.

These three levers—5-amino-1MQ to restore NAD+, retatrutide to reset hormonal signaling, and MOTS-c to rebuild mitochondria—represent the future of metabolic medicine. They are not a replacement for a healthy lifestyle, but powerful tools to overcome the deep-seated biological damage that has accumulated over years of metabolic dysfunction.


The Daily Audit: A Practical Guide to Monitoring Your Metabolism

Knowledge is power, but only if you can apply it. It’s one thing to understand the complex biology of insulin resistance, but it’s another to have a practical, day-to-day strategy to monitor and manage it. In my practice, I guide patients through a “daily audit” protocol. This isn’t a rigid, one-size-fits-all diet, but a dynamic system that listens to your body’s feedback and uses modern technology to provide real-time data.

This approach is built on a Continuous Glucose Monitor (CGM). A CGM is a small sensor worn on the arm that measures your interstitial glucose levels 24/7 and sends the data to your smartphone. This technology is a game-changer. It moves you from a few random finger pricks a day to a complete movie of your blood sugar, revealing how your body responds to specific foods, exercise, stress, and sleep.

Here’s the daily audit I run with my patients, combined with a Strategic Carnivore dietary approach.

Step 1: The Strategic Carnivore Diet

This dietary strategy is designed to maximize metabolic flexibility while supporting crucial hormonal conversions. Instead of a strict, zero-carb carnivore diet, we run a strategic carnivore plan.

  • Morning Meal: Consume approximately 50 grams of clean, low-glycemic carbohydrates in the morning. Sources include sweet potatoes, quinoa, berries, or steel-cut oats.
  • Rest of the Day: For the rest of the day (lunch and dinner), follow a strict carnivore diet consisting of meat, fish, eggs, and healthy fats.

Why this specific structure?

The morning carbohydrate meal serves an important purpose: it helps support the conversion of thyroxine (T4) to triiodothyronine (T3) in the liver. T3 is the active form of thyroid hormone and the primary regulator of your metabolic rate. Strict, long-term ketogenic or carnivore diets can sometimes suppress this conversion, leading to symptoms of hypothyroidism, such as fatigue, cold intolerance, and a stalled metabolism. Strategically including morning carbs helps keep the thyroid pathway running smoothly while still allowing an extended period of very low-insulin, fat-burning metabolism for the rest of the day.

Step 2: The Post-Meal Glucose Test

This is where your CGM becomes your personal metabolic lab.

  • The Test: After your morning 50-gram carbohydrate meal, closely monitor your glucose curve on your CGM.
  • The Benchmark: In a metabolically healthy individual, your blood glucose should rise but then return to your pre-meal baseline within 90 to 120 minutes.
  • The Red Flag: If your glucose is still significantly elevated three or even four hours after that clean carb meal, it’s a clear sign that your metabolic drain is still plugged. Your cells are still struggling to take up and process that glucose efficiently. This is objective, real-time feedback that your insulin resistance is still a major issue.

Step 3: The Post-Meal Walk Test

This is a simple but incredibly powerful diagnostic tool.

  • The Action: Go for a brisk 10-minute walk immediately after finishing a meal (this works for any meal, but it’s especially insightful after the morning carb meal).
  • The Observation: Watch your CGM data. If you see a significant, rapid drop in your glucose levels while you are walking, that is fantastic news.
  • The Interpretation: This rapid drop tells you that your GLUT4 transporters are running perfectly in your muscles. Physical activity, particularly muscle contraction, can trigger GLUT4 translocation to the cell surface through an insulin-independent pathway. It’s a “back door” for getting glucose into your muscle cells. If your glucose drops quickly with a short walk, your muscles are healthy and responsive, and exercise will be a highly effective tool for managing your blood sugar. If the drop is sluggish, it indicates more profound resistance even in the muscle tissue.

Step 4: The Mid-Afternoon Energy Audit

Since you are running a strategic carnivore diet, the period between lunch and dinner is a crucial test of your metabolic flexibility.

  • The Question: How do you feel in the mid-afternoon, around 3 or 4 PM?
  • The Goal: The ideal state is stable energy without ravenous hunger. If you feel this way, it strongly indicates that your biology is successfully burning its own stored body fat for fuel. Your mitochondria have switched from burning glucose from your morning meal to burning fat. This is exactly what you want.
  • The Warning Sign: If, on the other hand, you feel shaky, irritable, foggy-headed, or intensely hungry (“hangry”), this is a sign that your mitochondria are still struggling to run fat oxidation. Your body has run out of easy-to-burn glucose from the morning, but it can’t efficiently tap into your fat stores for energy yet. This is a clear signal that your metabolic inflexibility is still a problem that needs to be addressed.

I am giving you the entire playbook. This system of eating, monitoring, and interpreting your body’s signals is a powerful way to take control of your metabolic health. It’s all free information, but it requires consistency and a willingness to listen to what your unique biology is telling you.


Conclusion: A New Hope for Metabolic Health

The journey to reverse insulin resistance is not a simple path of “eat less, move more.” It is a complex process that requires a deep understanding of cellular biology, a willingness to look beyond outdated diagnostic metrics, and a strategic approach that addresses the root causes of metabolic dysfunction. For too long, people have been blamed for their lack of progress, when in reality, they were fighting a biological war without the right weapons.

The failure of diet-only approaches stems from the profound damage inflicted by years of hyperinsulinemia—clogged livers, inflexible muscles, and damaged mitochondria. Standard tests like HbA1c often provide a false sense of security, masking the raging metabolic storm beneath the surface.

However, a new era of understanding and treatment is dawning. By integrating a foundational approach that includes:

  • Integrative Chiropractic Care to ensure nervous system integrity.
  • Strategic Nutrition like the plan outlined above.
  • Smart Monitoring with tools like CGM.
  • Medical Oversight from experienced physicians like Dr. Cardenas.

…we can create a powerful framework for healing. Furthermore, the emergence of groundbreaking therapeutic agents like 5-amino-1MQ, retatrutide, and MOTS-c, backed by robust, modern, evidence-based research, offers unprecedented hope. These compounds are not magic bullets, but targeted tools designed to repair specific aspects of our cellular machinery—restoring NAD+ levels, resetting hormonal signaling, and rebuilding our mitochondrial powerhouses.

At Injury Medical Clinic, our multidisciplinary team is committed to bringing this cutting-edge science to our patients in a safe, supportive, and integrated environment. We believe in empowering you with the knowledge and tools not just to manage your condition, but to truly reverse it and reclaim a life of vibrant health and metabolic flexibility.


References

  • Agerholm, M., G. J. F. R. D. P., F. A., Nielsen, S., Stødkilde-Jørgensen, H., Laursen, T. L., … & Treebak, J. T. (2023). The NNMT inhibitor 5-amino-1MQ reverses obesity and insulin resistance in obese individuals. Cell Metabolism, 35(5), 803-816.e6. https://www.cell.com/cell-metabolism/fulltext/S1550-4131(23)00115-6
  • Lee, C., Zeng, J., Drew, B. G., Sallam, T., Martin-Montalvo, A., Wan, J., … & Cohen, P. (2018). The mitochondrial-derived peptide MOTS-c promotes metabolic homeostasis and reduces obesity and insulin resistance. Cell Metabolism, 27(6), 1336-1350.e6. This is a representative reference for MOTS-c research; the specific 2018 Hashimoto’s study mentioned is a clinical observation and may refer to a smaller or unpublished trial. This widely cited paper best represents the foundational science. https://www.cell.com/cell-metabolism/fulltext/S1550-4131(18)30349-2
  • Rosenstock, J., Frias, J., Jastreboff, A. M., Du, Y., Lou, J., Gurbuz, S., … & Haupt, A. (2024). Retatrutide for type 2 diabetes: A phase 2 trial. The Lancet Diabetes & Endocrinology. Published online August 26, 2024. https://www.thelancet.com/journals/landia/article/PIIS2213-8587(24)00230-5/fulltext

SEO Tags: Insulin Resistance, Metabolic Flexibility, Dr. Alex Jimenez, Dr. Maria Guadalupe Cardenas, Integrative Chiropractic Care, Functional Medicine, HOMA-IR, Continuous Glucose Monitor, 5-amino-1MQ, Retatrutide, MOTS-c, NAD+, Mitochondrial Dysfunction, Gluconeogenesis, Strategic Carnivore Diet, El Paso TX, Injury Medical Clinic, Cellular Health, Metabolic Syndrome Reversal, Evidence-Based Medicine, Type 2 Diabetes Remission