Give us a Call
+1 (915) 412-6680
Send us a Message
[email protected]
Opening Hours
Mon-Thu: 7 AM - 7 PM
Fri - Sun: Closed

Restorative Injection Therapy Options for Muscle Pain Relief


Understand the benefits of restorative injection therapy for musculoskeletal pain and reclaim your active lifestyle today.

Educational Abstract: Integrative Care for Achilles Tendinopathy, Joint Stabilization, and Prolotherapy in a Multidisciplinary Clinic

In this educational post, I present a clear, step-by-step exploration of how we evaluate and treat Achilles tendinopathy and related joint instability concerns in an integrative, multidisciplinary setting. I walk you through why short-term immobilization in a controlled boot can accelerate healing, how structured progressive loading restores tendon capacity, and where regenerative methods such as dextrose-based prolotherapy fit within evidence-informed care. This post also explains our team approach at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso, Texas, where I, Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, collaborate with our Medical Director and Collaborative Physician, Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI #1164426749; Texas MD License #J2933). With over 40 years of experience in internal medicine, Dr. Cardenas provides medical oversight that complements chiropractic care, functional medicine, personal injury protocols, rehabilitation, and interventional strategies. The result is a coordinated, patient-centered pathway that merges modern, evidence-based research with integrative chiropractic methods and medical guidance. You will learn what prolotherapy is, when it is appropriate, how it is administered, and how immobilization, graded rehab, and integrative chiropractic care form a cohesive plan for safer, faster recovery.

Integrative Achilles Tendinopathy Care: A First-Person Guide

I am Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST. Every week in our clinic, I meet patients who struggle with Achilles tendinopathy, heel pain, or calf tightness that derails walking, driving, training, and daily work. Some are truck drivers, some are athletes, and others are simply on their feet all day. The transcript segment you read reflects a common clinical scenario: deciding whether and how to use a boot for short-term immobilization, whether to proceed with prolotherapy, and how to sequence care when patients can only come in intermittently (for example, every other week due to work demands).
The essential questions I answer in this post are:

  • What is Achilles tendinopathy, and how do tendons biologically respond to load and rest?
  • When do we use a controlled walking boot, and why does it help early pain control and healing?
  • What is prolotherapy—specifically dextrose prolotherapy—and how can it support connective tissue repair when used judiciously?
  • How do we integrate chiropractic care with internal medicine oversight, functional medicine, personal injury management, and rehabilitation into one seamless plan?
  • How do we make treatment decisions for patients with travel or work constraints who may only be seen every other week?

Throughout, I highlight key clinical observations I routinely share on my professional platforms and in practice:

Dr. Maria Guadalupe Cardenas, MD, an internist with more than 40 years of clinical experience, serves as our Medical Director and Collaborative Physician. Her oversight ensures that interventional decisions—like injections, medication safety, and comorbidity management—are synchronized with chiropractic and rehabilitation protocols for consistent, evidence-informed outcomes.

Understanding Achilles Tendinopathy: Biology, Biomechanics, and Pain

When I evaluate Achilles pain, I want patients to understand the tendon’s physiology. The Achilles tendon is the largest in the body, connecting the gastrocnemius-soleus complex to the calcaneus. It is built to store elastic energy and release it during gait, running, and jumping. However, tendons do not behave like muscles; they remodel more slowly, and they can become painful with repeated loads beyond their current capacity.
Key pathophysiological features of Achilles tendinopathy include:

  • Matrix disorganization: Collagen fibers lose their organized alignment, shifting from Type I dominance to increased Type III fibers.
  • Neurovascular ingrowth: Pain can be associated with small vessel and nerve growth into the tendon’s outer layers, sensitizing the region.
  • Altered cell signaling: Tenocytes respond to load by producing matrix proteins, but under excessive or insufficient load, signaling can shift toward catabolic or maladaptive pathways.
  • Mechanical overload and energy storage demand: High-repetition loading (running, jumping) stresses the tendon’s spring-like function.
  • Regional impairment: Midportion vs. insertional Achilles tendinopathy differ. Insertional cases often involve compressive stress at the calcaneal interface.

Why tendons become painful:

  • Load mismatch: The tendon’s capacity is lower than the demand placed upon it. This can be due to recent training spikes, footwear changes, altered gait mechanics, or systemic factors.
  • Microscopic microtrauma: Repeated micro-injury can outpace the tendon’s ability to repair.
  • Compressive and tensile stress: Tendons endure both; insertional pain relates more to compression against the calcaneus, while midportion pain is often tensile.

Why early short-term rest sometimes helps:

  • Pain is a protective output influenced by nociception, local inflammation-like signaling, and central sensitization. Given time, a tendon responds to progressive loading with improved capacity—yet the acute flare must be managed first. Strategic immobilization in a controlled boot can reduce peak loads, allowing pain to settle and early repair signals to proceed.

The Role of a Controlled Walking Boot: When, Why, and How

We sometimes recommend a controlled walking boot for Achilles tendinopathy—especially in acute or severe pain flares. When a patient says, “If I can only come in every other week, should I still use the boot?” my answer is often yes, with careful parameters.
Why a boot helps:

  • Load reduction: The boot limits ankle dorsiflexion and plantarflexion extremes, reducing tensile strain on the Achilles.
  • Pain attenuation: Lower mechanical stress reduces nociceptive input, allowing pain-modulatory systems to recalibrate.
  • Inflammation-like processes: While tendinopathy isn’t a classic inflammatory condition, local biochemical signaling can be exacerbated by overload. A boot tempers this.
  • Early healing window: Short-term immobilization can provide a window to reintroduce progressive loading safely.

When to use a boot:

  • Acute flare: Severe pain with walking or initial steps after rest.
  • Insertional tendinopathy: Compressive loads at insertion benefit from motion limitation.
  • After interventional care: Post-procedure (e.g., prolotherapy), temporary boot use can protect early tissue responses.

How we structure boot use if visits are every other week:

  • Week 1: Wear the boot most of the day, especially during ambulation. Keep it on during any activities that provoke pain. At home, brief removal for gentle, pain-free range of motion may be allowed.
  • After Week 1: If pain has markedly improved, we begin careful transitions out of the boot. This includes using supportive footwear, heel lifts if appropriate (especially for insertional cases), and starting low-load isometric exercises.
  • Re-evaluation at next visit: We adjust boot use based on pain, function, and objective measures. If a flare returns with early reloading, we reintroduce boot time temporarily.

Boot precautions:

  • Avoid extended immobilization beyond necessity: Tendons need load to maintain capacity. A boot is a tool, not a permanent solution.
  • Address proximal and distal joints: Hip, knee, and foot mechanics matter. We prevent deconditioning by prescribing safe movement in other regions.
  • Monitor skin and circulation: Ensure proper fit and watch for pressure points or swelling.

Clinical reasoning:

  • The boot is a bridge. We use it to cross the acute pain river and reach the progressive loading shore, where rehabilitation builds stronger, more resilient tendon capacity.

5 Things You Need to Know About Ligamentous Injuries Before They Get Worse- Video

Progressive Loading for Achilles Tendinopathy: Restoring Capacity

Once pain is controlled, tendons recover best through graded, progressive loading. This is where chiropractic-guided biomechanics, targeted rehab, and medical oversight converge.
Core components:

  • Isometric loading: Early-stage pain modulation. Mid-range isometric calf contractions (e.g., wall lean calf holds) can reduce pain via analgesic mechanisms and prime the tendon for later loading.
  • Isotonic loading: Eccentric-caloric approaches, such as eccentric heel drops for midportion tendinopathy, build tensile capacity and stimulate collagen remodeling. For insertional cases, we modify range to avoid excessive dorsiflexion and compression.
  • Plyometric and energy storage: When tolerated, we incorporate cautious return to bounce drills to restore the tendon’s spring function.
  • Relative rest: We maintain baseline activity but avoid provocative spikes.

Clinical progression timeline:

  • Weeks 1–2: Control pain; boot use if indicated. Begin isometrics as tolerated outside the boot (with medical guidance).
  • Weeks 2–6: Transition to eccentric and controlled concentric-eccentric calf training. Add hip and foot mechanics correction, balance, and proprioception exercises.
  • Weeks 6–12: Increase load, add velocity components and sport/work-specific tasks. Integrate plyometrics as appropriate.

Why it works:

  • Mechanotransduction: Load signals tenocytes to produce and align collagen, improve matrix structure, and increase stiffness appropriately.
  • Neurophysiology: Progressive loading recalibrates pain processing, decreasing central sensitization.
  • Functional integration: Strengthening the kinetic chain (hips, core, foot intrinsics) reduces Achilles-specific stress.

Prolotherapy Explained: Dextrose-Based Connective Tissue Support

Patients often ask: “What is Prolo?” In our clinic, when we mention prolotherapy, we refer specifically to hypertonic dextrose injections mixed with local anesthetic for comfort. Typical mixtures in practice range widely; a common clinical teaching mixture for certain peri-tendinous or ligamentous targets may use dextrose concentrations substantially higher than physiologic, paired with lidocaine 1–2% for analgesia during administration. In the transcript snippet above, someone referenced “Dextrose fifty percent mixed with lidocaine two percent,” reflecting a colloquial description sometimes heard in clinical dialogues. In evidence-informed practice, we tailor concentration to tissue target, safety, and published guidance.
What prolotherapy aims to do:

  • Irritant-mediated signaling: Hypertonic dextrose acts as a controlled irritant, intended to stimulate local healing responses, promote fibroblast activity, and support collagen deposition in weakened connective tissues.
  • Stabilization of lax or painful sites: Often used for ligaments, entheses, and peri-tendinous structures with micro-instability or degenerative changes.
  • Pain modulation: Dextrose may have neuromodulatory properties; perineural dextrose injections have been studied for certain neuropathic pain patterns.

Where it fits in Achilles care:

  • Midportion Achilles tendinopathy and insertional cases are primarily treated with progressive loading. However, in select cases—particularly where paratendinous tissue pain is prominent, or there are associated ligamentous contributors—extratendinous prolotherapy may be considered as part of a broader plan.

Important note:

  • We do not inject directly into the Achilles tendon. Intratendinous injections risk further degeneration or rupture. Evidence-informed approaches target peri-tendinous or adjacent connective tissues when appropriate, and always under medical oversight.

Why boot use can accompany prolotherapy:

  • Following a procedure intended to activate local healing pathways, short-term load protection helps limit immediate strain, giving tissues a quieter environment to respond. A boot for the first week post-procedure may be advised, then gradually discontinued as loading resumes.

Safety and oversight:

  • Our Medical Director, Dr. Maria Guadalupe Cardenas, MD (NPI #1164426749; Texas MD License #J2933), evaluates systemic factors (diabetes, anticoagulation, infection risk), assures safe anesthetic use, and confirms appropriate candidates for prolotherapy. Her internal medicine oversight ensures that regenerative interventions align with patient comorbidities and medications.

Integrative Chiropractic Care: Biomechanics, Alignment, and Kinetic Chain Support

In my integrative practice, chiropractic care is not merely about adjustments; it is about restoring biomechanical integrity across the kinetic chain so upstream or downstream dysfunctions do not overload the Achilles.
Chiropractic contributions:

  • Foot and ankle mechanics: Address subtalar motion, midfoot stability, and first ray function to optimize dorsiflexion mechanics without excessive Achilles strain.
  • Pelvic and lumbar alignment: Pelvic obliquity or lumbar facet dysfunction can alter gait patterns and increase asymmetrical loading.
  • Thoracolumbar integration: Posture and spinal mobility influence stride length and cadence. Optimizing spinal motion can normalize energy transfer through the lower limb.
  • Soft tissue work: Myofascial release, instrument-assisted soft tissue mobilization, and targeted manual therapy can reduce myofascial guarding and improve fascial glide.

Why chiropractic integration matters:

  • Load distribution: Tendon load depends on whole-body movement. Correcting foot-to-hip alignment spreads forces more evenly.
  • Motor control: Adjustments can improve proprioceptive input, enhancing neuromuscular coordination.
  • Pain modulation: Spinal and peripheral joint interventions can affect nociceptive processing and reduce protective muscle co-contractions.

Clinical observations:

  • Many patients I document on Chiromed and discuss via my professional platforms show faster improvements when chiropractic and rehab are combined. The Achilles benefits when hip extension, ankle dorsiflexion, and foot stability operate in harmony.

Internal Medicine Oversight: Safety, Systems Biology, and Comorbidity Management

Our multidisciplinary model relies on medical direction to ensure every intervention is appropriate and safe. Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine), with over 40 years of experience, provides oversight for procedures and for patients with complex medical backgrounds.
Medical oversight includes:

  • Risk assessment: Diabetes, peripheral vascular disease, neuropathy, immunosuppression, and anticoagulant use affect tendon healing and procedure risk.
  • Medication review: NSAIDs, steroids, anticoagulants, and other medications can influence pain, bleeding risk, immune response, and repair.
  • Diagnostic clarity: Ruling out differential diagnoses (e.g., partial tears, retrocalcaneal bursitis, inflammatory arthropathies) with appropriate imaging or labs when indicated.
  • Procedure safety: Confirming candidacy for injections; selecting dextrose concentration; monitoring for adverse reactions; maintaining sterile technique standards.
  • Systemic optimization: Addressing nutrition, glycemic control, and vascular health to support connective tissue repair.

Why this matters:

  • Tendon recovery is not just local. Systemic health—metabolic factors, hormones, inflammation—affects the pace and quality of healing. Internal medicine oversight improves outcomes by aligning local care with whole-body needs.

Functional Medicine Integration: Nutrition, Metabolism, and Recovery

Functional medicine adds another layer: optimizing the biochemical environment that supports tendon repair and pain modulation. In our clinic, we combine chiropractic and medical oversight with functional medicine protocols tailored to individual needs.
Key functional considerations:

  • Glycemic control: Hyperglycemia impairs collagen cross-linking and increases glycation end-products that stiffen tissues maladaptively.
  • Protein adequacy: Collagen synthesis depends on adequate protein, vitamin C, copper, zinc, and specific amino acids like glycine and proline.
  • Omega-3 fatty acids: Support resolution-phase pathways that may help modulate pain and tissue response.
  • Micronutrient sufficiency: Vitamin D, magnesium, and B-vitamins support musculoskeletal function and neuromuscular control.
  • Inflammation modulation: Diet quality (whole foods, antioxidants) can lower chronic inflammatory tone that interferes with repair.

Clinical reasoning:

  • A tendon recovering under progressive load needs raw materials for remodeling. Functional medicine supplies these, while chiropractic alignment reduces unnecessary strain, and medical oversight ensures safe interventional choices.

Personal Injury and Occupational Considerations: Practical Constraints and Solutions

When patients are truck drivers or have jobs requiring long hours of driving or standing, visit frequency may be limited. The question, “Should we still do the boot if we can only be seen every other week?” appears often. My answer is a practical yes—with a plan.
Strategies for intermittent visits:

  • Boot schedule: First week consistent use, then taper based on pain and function, with remote guidance if needed.
  • Home program: Simple, clear isometrics, gentle mobility drills, and foot intrinsic activation that do not risk flares.
  • Telehealth check-ins: Brief remote reviews to adjust load and troubleshoot pain patterns.
  • Work ergonomics: Heel lifts in supportive shoes, breaks for calf circulation, avoiding high dorsiflexion angles that stress the tendon.
  • Documentation for personal injury cases: Thorough notes to support claims, compliance, and collaboration with legal or insurance teams.

Why this works:

  • Even with limited in-person care, a structured plan keeps healing on track. Boot use tempers acute pain; planned loading rebuilds capacity; clear guidance prevents setbacks.

Rehabilitation Roadmap: Detailed Protocols for Achilles Tendinopathy

I design rehab protocols to move patients from pain to resilience:
Phase 1: Calm the Pain and Protect the Tissue

  • Boot (as indicated): Use for the first week post-flare or post-procedure.
  • Isometric holds: 5 sets of 45-second mid-range calf holds, pain monitored.
  • Gentle mobility: Ankle ROM without pushing into pain; avoid high dorsiflexion in insertional cases.
  • Circulation: Micro-walks with boot; calf pumping to prevent stasis.

Why: Isometrics reduce pain via cortical and spinal mechanisms; limited motion protects healing tissues while preserving joint nutrition.
Phase 2: Build Capacity with Eccentrics and Isotonics

  • Eccentric heel drops: Midportion cases: straight-knee and bent-knee versions, 3 sets of 15 twice daily; insertional cases: partial range, no deep dorsiflexion.
  • Foot intrinsics: Short-foot exercises; toe yoga to improve medial longitudinal arch support.
  • Hip and core: Glute med/min strengthening; anti-rotation core drills to stabilize gait.
  • Progressive load: Gradual weight addition (e.g., backpack or dumbbells) as pain allows.

Why: Eccentrics drive collagen realignment and tendon stiffness improvements; foot-hip integration spreads load.
Phase 3: Restore Energy Storage and Return to Task

  • Low-amplitude plyometrics: Gentle pogo jumps, or double-leg hops with strict pain criteria.
  • Tempo work: Controlled cadence squats and lunges to coordinate the kinetic chain.
  • Task-specific drills: Step-downs, ramp walking for drivers; return-to-run progressions for athletes.

Why: Tendons must store and release energy efficiently for real-life activities. Controlled exposure rebuilds confidence and function.
Pain monitoring guidelines:

  • Acceptable pain: Mild discomfort during exercises that resolves within 24 hours.
  • Unacceptable pain: Sharp pain, swelling, or next-day stiffness that worsens; adjust load or revert to earlier phase.

Prolotherapy Protocols: Selection, Technique, and Follow-Up

How we decide on prolotherapy:

  • Indications: Persistent pain with clinical signs of ligamentous laxity, paratendinous irritation, or enthesopathic discomfort unresponsive to conservative care.
  • Contraindications: Active infection, uncontrolled diabetes, coagulopathy, allergy to local anesthetic, or patient preference against procedures.
  • Informed consent: Discuss benefits, alternatives (e.g., PRP, shockwave therapy, continued rehab), and risks.

Technique overview:

  • Target selection: Peri-tendinous or ligamentous structures where clinical exam reveals tenderness and laxity.
  • Solution: Hypertonic dextrose mixed with lidocaine for comfort; concentration tailored to tissue and safety guidance.
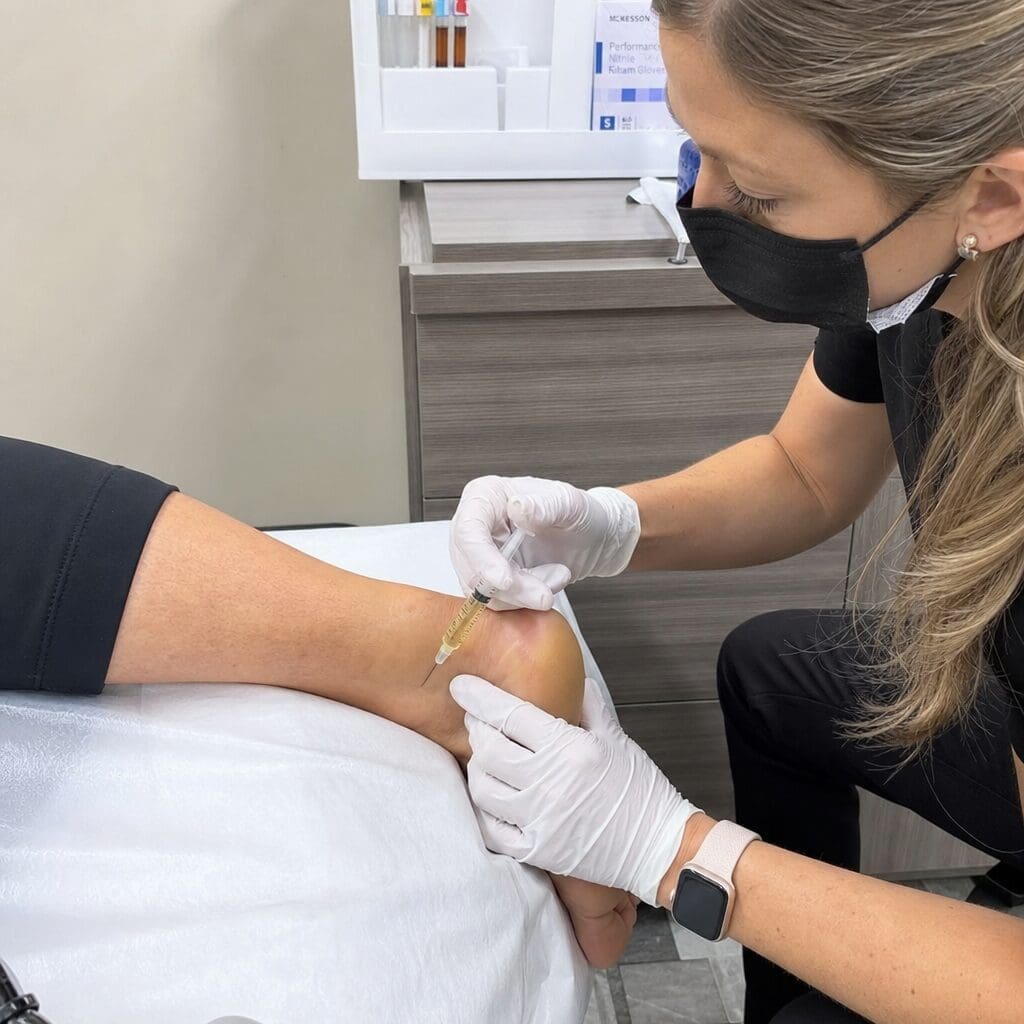
  • Sterility and precision: Mark anatomical landmarks; ultrasound guidance as appropriate; aspirate where indicated; inject small aliquots carefully.
  • Post-procedure: Boot for the first week if indicated; avoid NSAIDs to allow intended inflammatory-healing signaling; continue gentle isometrics without provoking pain.

Follow-up:

  • Re-evaluate in 2–4 weeks: Assess pain, function, tissue tenderness, and mechanical stability.
  • Rehab synchronization: Resume progressive loading phases calibrated to response.
  • Number of sessions: Varies; many patients benefit from 1–3 sessions, but decisions are individualized.

Clinical reasoning:

  • Prolotherapy is not a stand-alone solution. It is a supportive intervention within a system that includes chiropractic alignment, structured rehab, and medical safety oversight.

Evidence-Based Perspective: What Research Shows

Modern research on tendinopathy underscores progressive loading as the cornerstone of recovery. While evidence for prolotherapy varies by tissue and protocol, there is growing interest in dextrose’s role in supporting connective tissue repair in chronic pain and laxity contexts. We apply it thoughtfully and selectively, based on clinical response and patient goals.
Key evidence-informed themes:

  • Load-based rehab is the primary driver of tendon adaptation and pain reduction.
  • Short-term immobilization can reduce pain in acute flares, but prolonged rest is counterproductive.
  • Adjunct interventions such as shockwave therapy, PRP, or dextrose prolotherapy may benefit specific patients when integrated with loading programs.
  • Whole-chain biomechanics matter; upstream/downstream dysfunction must be corrected.

We keep current with leading researchers and clinical trials that refine tendinopathy management methods. Our approach remains dynamic, adapting to new data while maintaining safety and individualized planning.

Safety, Ethics, and Patient Education

In our clinic, medical ethics guide every interventional choice:

  • Transparency: We explain what prolotherapy is, what it is not, and set realistic expectations.
  • Shared decision-making: Patients choose among options with full information.
  • Outcome tracking: We measure pain, function, and activity return to ensure objective progress.

Patient education focus:

  • Understand the plan: Boot is temporary; loading is structured; injections are adjuncts.
  • Pain literacy: Not all pain means harm; controlled discomfort during rehab can be acceptable.
  • Self-care: Sleep, nutrition, and stress management affect recovery speed.

The Multidisciplinary Model at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic)

Our clinic in El Paso, Texas, is a multidisciplinary setup common in integrative or injury care clinics, where an MD provides medical direction alongside a chiropractor. Here’s how our team functions:

  • Medical Director and Collaborative Physician: Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI #1164426749; Texas MD License #J2933) oversees medical decisions, ensures procedural safety, manages comorbidities, and aligns systemic health with local care.
  • Chiropractic Lead: I provide integrative chiropractic care, manual therapy, biomechanical analysis, and rehab programming to restore movement integrity and tendon capacity.
  • Functional Medicine Integration: Nutrition, metabolic optimization, and lifestyle strategies support healing biology.
  • Personal Injury Services: Documentation, care coordination, and ergonomic solutions adapt the plan to work demands and legal processes.
  • Rehabilitation Specialists: Team members deliver day-to-day exercise progression, manual therapy, and patient coaching.

The synergy:

  • Every patient benefits from an aligned plan. Medical safety, chiropractic biomechanics, rehab progression, and functional biology converge to produce comprehensive care for Achilles tendinopathy and related joint instability.

Case-Based Illustrations: Practical Pathways

Case A: Midportion Achilles Tendinopathy in a Driver

  • Presentation: Sharp pain with first steps after rest, worsened by long driving.
  • Plan: Boot for 1 week, isometrics, then eccentric loading. Heel lifts temporarily during driving.
  • Prolotherapy: Considered for paratendinous tenderness; if performed, boot resumed for first post-procedure week.
  • Oversight: Dr. Cardenas reviews metabolic health and approves procedure.

Case B: Insertional Achilles Pain with Foot Mechanics Issues

  • Presentation: Pain at calcaneal insertion, aggravated by dorsiflexion.
  • Plan: Modified range eccentrics avoiding deep dorsiflexion; foot intrinsic strengthening; supportive footwear.
  • Chiropractic: Subtalar joint and midfoot mobilization; pelvic alignment.
  • Prolotherapy: Consider enthesis-adjacent support if persistent; internal medicine oversight ensures safety.

Case C: Recurrent Flares with Limited Visit Frequency

  • Presentation: Can only come every other week due to work.
  • Plan: Boot week one after flare; robust home program with telehealth check-ins; progressive loading tracked remotely.
  • Outcome: Symptom reduction with maintained work capacity; boot phased out, function restored.

Why “Do It” Still Matters: Consistency and Commitment

When patients ask, “Should we still do it?”—meaning should we still proceed with the plan even if constraints exist—I encourage consistent, realistic actions:

  • Short-term boot: Yes, it can be beneficial, especially in the first week after a flare or procedure.
  • Progressive loading: Essential—begin as soon as pain allows, escalating thoughtfully.
  • Adjunct options: Prolotherapy may help select cases; ensure medical oversight and align it with rehab.
  • Follow-up cadence: Even every other week can work if the home plan is clear and the team coordinates.

The treatment journey is stepwise. The boot is a tool, rehabilitation is the engine, and integrative care is the roadmap.

Frequently Asked Questions

What is prolotherapy exactly?

  • Prolotherapy generally refers to injections that use an irritant solution—often hypertonic dextrose—to stimulate local healing. It is commonly mixed with lidocaine to reduce injection pain. Concentrations vary; we tailor them for safety and tissue targets under medical oversight.

Does a boot weaken the tendon?

  • Prolonged immobilization can reduce capacity. However, short-term use in acute flares or post-procedure phases provides protective benefit. We quickly transition to loading to prevent deconditioning.

Can I keep working while wearing a boot?

  • Often yes. We adjust work ergonomics and advise supportive footwear. The boot reduces pain while you carry out essential tasks.

Is eccentric loading necessary?

  • For midportion Achilles tendinopathy, eccentric loading is strongly supported for capacity-building. For insertional cases, we modify range to avoid excessive compression.

How does chiropractic care help?

  • Chiropractic care optimizes alignment and movement, reducing excessive load on the Achilles. Manual therapy and adjustments improve kinetic chain function and pain modulation.

Who ensures injection safety?

  • Our Medical Director, Dr. Maria Guadalupe Cardenas, MD, provides medical oversight, evaluates systemic risks, and confirms procedural safety.

What if I have diabetes or take blood thinners?

  • Internal medicine oversight is crucial. We adjust plans accordingly, monitor labs, and make procedural decisions based on individualized risk.

Closing Perspective: Integrated Healing for Lasting Results

The journey from Achilles pain to confident movement requires an integrated plan. In our clinic, we combine:

  • Chiropractic biomechanics to correct load distribution,
  • Medical oversight to ensure safe interventions,
  • Functional medicine to optimize biological repair,
  • Rehabilitation to rebuild tendon capacity,
  • Personal injury care to adapt the plan to real work demands.

This interdisciplinary pathway delivers safer, faster, and more reliable outcomes for patients with Achilles tendinopathy and related joint instability. If your visits are limited to every other week, we can still “do it” and do it well: boot early if needed, load progressively, consider prolotherapy when appropriate, and maintain consistent teamwork.
For more clinical insights and updates, visit:

References

SEO tags: Achilles tendinopathy, dextrose prolotherapy, chiropractic care, internal medicine oversight, Mission Plaza Injury Medical Clinic, Injury Medical Clinic PA, El Paso chiropractor, boot immobilization, tendon rehabilitation, functional medicine, integrative care, personal injury clinic, Dr. Maria Guadalupe Cardenas MD, Dr. Alex Jimenez DC

Integrative Platelet-Rich Plasma Care for Scalp, Joint, and Skin

Integrative Platelet-Rich Plasma Care for Scalp, Joint, and Skin

Integrative Platelet-Rich Plasma Care for Scalp, Joint, and Skin

A Practical, Evidence-Based Guide from the Procedure Room

Abstract

In this educational post, I share a first-person, inside-the-room perspective on how our team prepares and delivers platelet-rich plasma (PRP) and peptide-enhanced therapies for scalp health, joints, and skin rejuvenation—integrated with chiropractic, rehabilitation, and functional medicine principles. I explain the science behind PRP fractionation, gel separators, and sterility; why contact with the separator matters; and how we combine precise technique with patient-centered comfort strategies. I also describe how Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI #1164426749; Texas License #J2933) serves as Medical Director and Collaborative Physician at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso, Texas, working alongside me, Dr. Alexander (Alex) Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, to provide a multidisciplinary care model that integrates chiropractic care, internal medicine oversight, functional medicine, rehabilitation, and personal injury services.

You will learn:

  • What PRP is and why separator gel contact matters
  • How we handle tubes, air pockets, and plasma layers to maintain quality
  • How peptides and topical carriers can complement PRP
  • What patients typically feel during scalp treatments (and why)
  • How integrative chiropractic care coordinates with medical oversight, functional medicine, and rehabilitation to optimize outcomes
  • The physiologic mechanisms behind PRP for musculoskeletal and skin/scalp applications
  • Clinical observations from my practice regarding outcomes and best practices

Throughout, I highlight key terms, summarize recent research using modern evidence-based methods, and explain clinical reasoning so the “why” is as clear as the “how.”


Integrative PRP and Peptide Therapy: A First-Person Walkthrough

When I step into the procedure room to prepare platelet-rich plasma (PRP), I’m focused on two things: preserving the biologic integrity of the sample and ensuring the patient’s experience is calm, informed, and comfortable. Our team’s back-and-forth—confirming tube labeling, separator position, and plasma depth—reflects the real-world vigilance that high-quality PRP requires.

Key steps I emphasize during PRP prep

  • Clear labeling and allocation: Each tube is designated for a specific target (e.g., ankle, knee, hip, scalp, microneedling). This ensures dosing consistency and avoids cross-use.
  • Attention to the separator gel: We verify that the separator gel is properly positioned after centrifugation, and we keep the collection needle tip from touching it. Even “just a teeny, tiny” contact can mix layers and reduce PRP quality.
  • Air pocket awareness: When aspirating the plasma, I maintain a minor air interface in the syringe to prevent fluid turbulence and keep the tip away from the gel.
  • Fraction control: We access the platelet-rich layer just above the buffy coat while minimizing contamination from red cells or separator gel.
  • Patient-centered handling: We narrate each step in plain language, respond to sensations (pressure, tension), and integrate gentle scalp massage when appropriate to reduce sympathetically-mediated discomfort.

These details may sound small, but together they protect the bioactive payload—the growth factors and cytokines that make PRP a potent, autologous tool.


Why Separator Gel Contact Matters: The Physiology and Physics

The separator gel is designed to create discrete layers after centrifugation: red cells below, a gel barrier, and plasma above. The platelet-rich fraction sits near the buffy coat. If the collection tip contacts the gel, two things can happen:

  • Back-mixing: As my colleague said in the room, plasma components can “leak back” across the boundary. This dilutes the platelet concentration and risks contaminating the PRP with red cells or gel residues.
  • Re-spin necessity: We may need to re-centrifuge to re-establish separation, which risks platelet activation at the wrong time, reducing the efficacy of the injection.

Physiologically, the effectiveness of PRP hinges on platelet alpha granules releasing growth factors such as PDGF, TGF-β, VEGF, IGF-1, and EGF at the target tissue. Maintaining an optimal platelet concentration (often 3–5x baseline, depending on protocol) and minimizing pre-activation during handling enhances the burst and sustained release of these factors at the desired site, promoting:

  • Angiogenesis and microvascular support (VEGF)
  • Chemotaxis and fibroblast proliferation (PDGF)
  • Collagen deposition and matrix remodeling (TGF-β)
  • Tenocyte and chondrocyte support in musculoskeletal tissue (IGF-1)
  • Keratinocyte and dermal regeneration in skin/scalp (EGF)

Modern evidence-based methods—ranging from absorbance-based platelet counts to flow cytometry and standardized classification systems for PRP composition—consistently show that handling variability can affect outcomes (Dohan Ehrenfest et al., 2014; Mautner et al., 2015).


Patient Sensations During Scalp PRP: What They Feel and Why

When I inject PRP into the scalp, patients often describe transient sensations:

  • “Head in a vice” or local tension: This is due to the galeal aponeurotica and scalp fascia briefly distending with injected volume. Local nociceptors respond to pressure.
  • “Tension headache” quality: Short-lived, typically minutes, as tissue pressure equilibrates and autonomic tone settles.
  • Rapid resolution: Gentle scalp massage and parasympathetic engagement reduce sympathetic arousal and help disperse fluid micro-gradients.

We frequently add a topical peptide layer post-PRP. Massaging in the peptides over recently treated tissue taps into mechanotransduction—light pressure can improve microcirculatory spread and may help with nociceptive modulation through gate control mechanisms. Patients often say, “That’s the best part,” because the soothing element reframes the experience and supports adherence to care.


Adding Peptides and Topical Carriers: Synergy with PRP

In the room, we discussed mixing a portion of autologous PRP into a carrier cream formulated to maintain bioactivity—colleagues referenced a “Pro-Cell” moisturizing carrier designed to hold PRP for cosmetic application. The rationale:

  • Barrier-compatible vehicle: A well-formulated cream can maintain moisture and protect growth factors at the skin surface long enough to interact with microchannels left by microneedling.
  • Microneedling synergy: PRP plus microneedling creates a microenvironment where growth factors enhance keratinocyte proliferation, dermal fibroblast activation, and collagen/elastin remodeling.
  • Peptide augmentation: Topical peptides (e.g., copper peptides, signaling peptides) may complement PRP by supporting matrix integrity, angiogenesis, and cell signaling pathways.

We use only carriers known to be compatible with autologous biologics and discuss expectations: topical PRP is an adjunct, not a substitute for injected PRP, where deeper regenerative goals are targeted.


PRP for Joints and Soft Tissue: Mechanisms that Matter

On the musculoskeletal side, we commonly allocate full tubes for joints—ankle, knee, hip—and occasionally for small joints that need targeted attention. The goal is to deliver a platelet concentration appropriate to the tissue type and pathology (e.g., tendinopathy vs. mild osteoarthritis).

Physiologic mechanisms

  • Modulated inflammation: PRP can shift the local milieu from catabolic to anabolic by down-regulating NF-κB pathways and promoting anti-inflammatory cytokines (e.g., IL-10) in some formulations.
  • Cellular recruitment: PDGF attracts progenitor cells and stimulates fibroblasts and tenocytes; TGF-β drives matrix deposition.
  • Cartilage support: While not recreating hyaline cartilage, PRP may improve symptoms and function in early osteoarthritis by encouraging chondrocyte anabolism and modulating synovial inflammation (Laudy et al., 2015; Filardo et al., 2017).
  • Tendon and ligament repair: Enhanced collagen synthesis and crosslinking support improved tensile properties over time (Mishra et al., 2014).

Outcome optimization depends on leukocyte content (LP-PRP vs. LR-PRP), activation timing, and injection technique. For intra-articular applications, we typically prefer leukocyte-poor PRP to minimize post-injection flare, while leukocyte-rich PRP may be considered for some tendinopathies where a stronger inflammatory “reset” is useful.


Integrative Chiropractic Care in a Multidisciplinary PRP Framework

I practice as a chiropractor and family nurse practitioner within a comprehensive, medically supervised environment. Dr. Maria Guadalupe Cardenas, MD (NPI #1164426749; Texas License #J2933), serves as Medical Director and Collaborative Physician at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso, Texas. Our model is multidisciplinary—common in integrative and injury care—blending medical oversight with chiropractic, functional medicine, rehabilitation, and personal injury care.

How we integrate care

  • Medical direction and safety: Dr. Cardenas provides oversight on indications, contraindications, and medication management. She ensures adherence to standards for biologics, sterile technique, and emergency preparedness.
  • Chiropractic precision and biomechanics: I evaluate regional interdependence, joint mechanics, and motor control. By restoring segmental mobility and optimizing kinematic chains, we reduce aberrant loading that can undermine PRP’s regenerative intent.
  • Functional medicine: We assess metabolic drivers of impaired healing—glycemic control, micronutrient status (e.g., vitamin D, zinc), inflammatory load, sleep, and stress. Good nutrition and lifestyle modulation support collagen synthesis, mitochondrial function, and tissue remodeling.
  • Rehabilitation: We implement graded loading protocols, isometrics to eccentrics, and neuromuscular re-education to align mechanical signals with biologic repair timelines.
  • Personal injury care: For post-collision or workplace injuries, we coordinate imaging, documentation, and return-to-function plans that align medical necessity with ethical, evidence-based practice.

This collaboration means patients receive comprehensive reasoning behind each step—from lab draw to last rep.


Clinical Workflow: Reasoning Behind Each Protocol

  1. Assessment and stratification
    • We differentiate indication (e.g., tendinopathy vs. mild OA vs. hair thinning vs. skin rejuvenation), set goals, and plan volume and frequency.
    • We evaluate systemic factors (A1c, lipid profile, inflammatory markers) to optimize the terrain for healing.
  2. PRP preparation
    • Use sterile tubes with separator gel appropriate to the protocol.
    • Centrifuge to achieve the desired platelet concentration. Avoid over-activation.
    • No gel contact: Maintain a clean interface. If contact occurs and layers mix, consider re-spin or discard to maintain quality.
  3. Injection technique
    • Ultrasound guidance for joints/tendons minimizes off-target placement and reduces post-procedural flare.
    • For scalp, distribute small aliquots across regions of thinning; consider nerve block when appropriate for comfort, though many patients manage well with topical and massage support.
  4. Adjuncts
    • Topical peptide cream with PRP for microneedling sessions, when indicated, to enhance epidermal and dermal regeneration.
    • Chiropractic adjustments/mobilization to normalize joint and soft-tissue mechanics, reducing nociceptive drive and improving movement quality.
  5. Rehabilitation and loading
    • Protect the site in the acute inflammatory phase (24–72 hours), then transition to subacute loading targeting collagen alignment and capacity building.
    • Incorporate isometrics early for tendinopathy, progressing to eccentric/concentric as pain allows.
  6. Follow-up and metrics
    • Track patient-reported outcomes (pain scales, function indices), objective measures (ROM, strength), and where appropriate, trichoscopy for scalp density and microneedling outcomes.

Patient Experience: Comfort Measures that Matter

During scalp injections, we coach patients through breathing and normalize expected sensations. A patient recently told me she felt “more scalp than hair up here” and initially experienced a fleeting “vice-like” tension. We explained that this is temporary pressure within superficial fascial planes and not a true headache. Within minutes, the discomfort subsided—consistent with our typical experience.

  • Why it resolves quickly: The scalp’s rich vascularization redistributes fluid while the autonomic nervous system resets. Gentle massage augments fluid kinetics and reduces peripheral nociception.
  • Nerve blocks when needed: For patients with heightened sensitivity, small peripheral nerve blocks can blunt afferent signaling, making the session smoother without affecting PRP efficacy.

In joint cases, patients may feel pressure or mild post-injection soreness. We recommend relative rest for 24–48 hours, ice as needed, and resume graded activity according to the tissue and plan.


Evidence Base: What Modern Research Shows

  • PRP for knee OA: Meta-analyses suggest PRP can improve pain and function versus hyaluronic acid or saline in mild to moderate osteoarthritis, especially in patients with lower BMI and earlier-stage disease (Belk et al., 2021).
  • Tendinopathy: Evidence supports PRP in selected chronic tendinopathies (e.g., lateral epicondylitis, some Achilles and patellar cases), with protocols tailored to tissue and leukocyte content (Mishra et al., 2014).
  • Scalp/hair: PRP has demonstrated increases in hair density and thickness in androgenetic alopecia adjunctive to standard care, with repeated sessions optimizing outcomes (Gupta & Carviel, 2022).
  • Skin/microneedling: PRP applied with microneedling enhances collagen remodeling and accelerates recovery, improving texture and scar appearance (Alam et al., 2018).

Across studies, technique fidelity—including proper centrifugation, concentration targeting, and avoidance of contamination—correlates with outcomes. This underscores why we obsess over details like no tip-to-gel contact and air pocket management.


Why Integrative Chiropractic Fits: Biomechanics Meet Biology

As a chiropractor, I see PRP not as a standalone solution but as a biologic accelerator that thrives in the right mechanical environment. Consider:

  • Joint centration: If a knee remains mal-tracking due to proximal hip weakness or foot mechanics, repeated microtrauma persists. Chiropractic assessments uncover these drivers; targeted manual therapy and corrective exercise reduce aberrant load.
  • Fascial continuity: Pain and strain travel through myofascial lines. Addressing thoracolumbar junction stiffness or pelvic torsion can unload distal tendons, allowing PRP-mediated remodeling to consolidate.
  • Neuromuscular control: Adjustments and motor control drills refine proprioception and muscle recruitment, reducing shear forces that would otherwise disrupt early collagen matrix.

The result: PRP’s biologic work gains a stable foundation, improving durability of results.


Safety, Oversight, and Ethical Practice

Dr. Cardenas’ medical leadership ensures that:

  • Patients are screened for contraindications (e.g., platelet disorders, active infections, anticoagulation concerns).
  • Informed consent covers expected benefits, alternatives, and risks.
  • Sterile technique is standardized, and contingency protocols are in place.
  • Documentation meets medical and legal standards, especially in personal injury contexts.

This framework protects patients and supports reproducible, evidence-informed care.


Practical Tips We Use Every Day

  • Keep the syringe tip superficial within the plasma; never let it touch the gel.
  • Maintain a small air gap in the syringe to reduce turbulence and preserve layer integrity.
  • If the layers mix, don’t force it. Re-spin or consider re-draw depending on the scenario.
  • Match PRP composition to target tissue: LP-PRP for joints; consider LR-PRP for certain tendons.
  • Use ultrasound guidance for accuracy and safety.
  • After scalp PRP, apply peptide-enriched carrier when indicated and massage lightly.
  • Align rehab progressions with tissue healing timelines; avoid premature high-load activities.

Clinical Observations from My Practice

Based on patterns I’ve discussed publicly and in professional forums, as well as what we routinely document in the clinic:

  • Patients with optimized metabolic health (e.g., A1c < 5.7–6.0, adequate vitamin D, omega-3 index) demonstrate more consistent PRP responses.
  • In knee OA, two to three LP-PRP sessions spaced 4–6 weeks apart often yield clinically meaningful improvements in pain and function for 6–12 months, especially when paired with gait retraining and weight management.
  • For lateral epicondylitis, a single LR-PRP or staged injections with structured eccentric loading can reduce pain within weeks, with maturation over 3–6 months.
  • Scalp PRP combined with home microneedling and peptide topicals shows visible improvements in hair density in 3–4 months for many, with best outcomes when DHT and inflammatory factors are co-managed medically as needed.

These observations align with published literature while acknowledging individual variability—a core reason we tailor care.


The Team Behind the Care

  • Medical Director & Collaborative Physician: Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI #1164426749; Texas MD License #J2933), directing medical safety, oversight, and clinical protocols.
  • Chiropractic and Functional Care: Dr. Alexander (Alex) Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, integrating biomechanics, manual therapy, functional medicine, and rehabilitation.
  • Clinic: Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic), El Paso, Texas—delivering multidisciplinary, integrative solutions for musculoskeletal health, skin/scalp regeneration, and personal injury recovery.

Takeaways for Patients and Clinicians

  • Quality handling equals quality outcomes: Protect the platelet payload by respecting the physics of separation.
  • Integrate for impact: Combine PRP with chiropractic, rehab, and metabolic optimization for durable results.
  • Individualize care: Choose PRP composition and protocols based on tissue type and patient factors.
  • Comfort is part of care: Anticipate sensations; smooth the experience with communication, massage, and selective nerve blocks.
  • Measure and iterate: Track outcomes and refine protocols with evidence and clinical feedback.

If you are considering PRP for joints, tendons, scalp, or skin, a multidisciplinary approach with medical oversight and integrative chiropractic care can help you reach the best version of your health—safely, methodically, and compassionately.


References

The Future of Regenerative Medicine: Peptides, Aesthetics, and Integrative Chiropractic Care

The Future of Regenerative Medicine: Peptides, Aesthetics, and Integrative Chiropractic Care

The Future of Regenerative Medicine: Peptides, Aesthetics, and Integrative Chiropractic Care

Abstract

Welcome to our educational portal. I am Dr. Alex Jimenez, and I am honored to guide you through the transformative world of modern, evidence-based wellness. In this comprehensive post, we will explore the cutting-edge applications of peptide therapy and bioregulators, a fascinating frontier that is revolutionizing our approach to metabolic health, weight management, hair restoration, and aesthetic skin rejuvenation. We will examine the intricate physiological mechanisms behind these biological messengers, demystifying how they orchestrate cellular repair and restore homeostasis. This post will highlight specific compounds, including GHK-Cu, BPC-157, SNAP-8, and modern GLP-1 agonists like semaglutide, tirzepatide, and retatrutide. I will also share insights into our breakthrough oral and transdermal delivery systems designed to improve patient access and clinical efficacy.

I will detail how we apply these therapies within a collaborative, multidisciplinary practice. You will learn how my expertise in chiropractic and functional medicine synergizes with the internal medicine oversight of our Medical Director, Dr. Maria Guadalupe Cardenas, MD, to deliver comprehensive personal injury care, rehabilitation, and regenerative treatments. Finally, I will introduce the Peptide Protocol Portal and our AI assistant, Dr. Peppy, resources we developed to ground these therapies in safety and rigorous clinical data. This educational journey aims to empower you with a clear, in-depth understanding of how an integrative care model unlocks the body’s incredible innate potential to heal and thrive.

The Integrative Clinical Model: Bridging Chiropractic Care and Medical Oversight

At the core of our philosophy is a multidisciplinary, patient-centered approach. I am Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, and my daily focus is restoring function, reducing pain, and optimizing health by uniting structural care, internal medicine insights, and functional medicine strategies. My diverse background allows me to view patient health through a wide-angle lens, constantly seeking to connect musculoskeletal integrity with systemic and metabolic function.

My work is seamlessly complemented and medically overseen by our esteemed Medical Director and Collaborative Physician, Dr. Maria Guadalupe Cardenas, MD. Dr. Cardenas is Board Certified in Internal Medicine and brings over 40 years of invaluable clinical experience to our team. Her NPI is #1164426749, and she is licensed in Texas under #J2933. Together, we practice at Injury Medical Clinic PA (also known as Mission Plaza Injury Medical Clinic) in El Paso, Texas.

This multidisciplinary setup is a gold standard in integrative and personal injury care clinics. While I orchestrate the biomechanical and functional aspects of healing through chiropractic adjustments, neuromuscular rehabilitation, and functional medicine protocols, Dr. Cardenas provides the essential medical direction required for advanced modalities like peptide therapy. Her oversight ensures appropriate diagnostic workups—ranging from CBC and CMP to thyroid panels, lipid profiles, and inflammatory markers—and guarantees that every therapeutic pathway we select follows safe, evidence-informed protocols.

When a patient arrives at our clinic for a musculoskeletal injury, we do not just treat the local tissue damage. Through our functional medicine lens, we might identify underlying metabolic dysfunction or systemic inflammation that is stalling their recovery. With Dr. Cardenas’s medical guidance, we can safely incorporate advanced regenerative treatments alongside structural rehabilitation, creating a holistic ecosystem for true healing.

Understanding Biological Messengers: Peptides and Bioregulators

As a practitioner dedicated to regenerative medicine, I am perpetually amazed by the body’s inherent capacity to heal itself. This reverence for human physiology led me deep into the science of peptide therapy, a field that harnesses the body’s own signaling molecules to orchestrate repair. To fully grasp this, we must differentiate between peptides and bioregulators.

Peptides are short chains of amino acids. In the United States, we classify a chain of 2 to 40 amino acids as a peptide; beyond that, it is considered a protein (though in Europe, the threshold is often 50). These larger molecules typically function via a highly specific “lock and key” mechanism. They bind to designated receptors on a cell’s surface, sending instructions inward to trigger a specific cellular cascade, such as synthesizing collagen or reducing inflammation. Because they are highly targeted, they do not cause the unintended “off-target” side effects frequently seen with synthetic pharmaceuticals.

Bioregulators, conversely, are ultra-short peptide sequences, usually consisting of just two to four amino acids. Because of their microscopic size, they can pass directly through the cell membrane and into the nucleus. Here, they exert profound epigenetic effects by influencing DNA transcription—effectively turning specific gene expressions “on” or “off” without altering the underlying DNA sequence.

Many peptides we utilize are endogenous (naturally produced by the human body). A prime example is GHK-Cu (glycyl-L-histidyl-L-lysine bound to copper), known as the blue copper peptide. Found in our saliva and blood plasma, it possesses antibacterial properties and is critical for musculoskeletal repair by upregulating collagen types 1 and 3 following tissue injury.

Other peptides are exogenous, synthesized in a laboratory for therapeutic consistency. BPC-157 (Body Protection Compound) is derived from a protective protein found in human gastric juice. Interestingly, in the early 1900s, Ivan Pavlov, famous for his behavioral experiments, arguably became the first to commercialize BPC-157 by collecting gastric secretions from his dogs to sell as a medicinal elixir. While he did not know its precise molecular identity, he recognized its profound healing capacity.

A Brief History of Peptides in Medicine

Peptides are not a novel wellness trend; they are deeply woven into the history of modern medicine.

  • 1901: German chemist Emil Fischer discovered peptides, a breakthrough that earned him the Nobel Prize in Chemistry.
  • 1921: The first peptide drug, insulin, was administered to a 14-year-old Canadian named Leonard Thompson, waking him from a diabetic coma.
  • 1922: Banting and Macleod were awarded the Nobel Prize for their work on insulin.
  • 1953: The first lab-synthesized peptide, oxytocin (often dubbed the “love hormone”), was created, clarifying its role in childbirth and social bonding.

Today, there are hundreds of FDA-approved peptide drugs, with over 800 more in clinical pipelines, representing a rapid evolution in pharmacology alongside mRNA technology. Knowledge in medicine is doubling roughly every 25 years, and peptide science is riding the crest of this wave. Culturally, peptides have also entered the mainstream. High-profile figures like Jennifer Aniston and Gwyneth Paltrow praise them for skincare, while Joe Rogan has widely discussed the “Wolverine stack” (BPC-157 and TB-500) with actors like Matt Damon for injury recovery.

When the FDA notes “unknown risk factors” for compounds like BPC-157, it often means large-scale, formalized human clinical trials are pending, not that the compound is inherently dangerous. In decades of clinical application and research, there have been no documented adverse events in human trials for BPC-157. Under Dr. Cardenas’s medical direction, we prioritize rigorous third-party testing for purity, sterility, and heavy metals, ensuring every intervention is regulatory-compliant and meticulously safe.

The Science of Delivery: Enhancing Bioavailability and Efficacy

A significant challenge in peptide therapy is the delivery mechanism. Injectable delivery is highly effective but creates compliance barriers for needle-phobic patients and faces stringent regulatory scrutiny. For example, GHK-Cu is approved as a topical cosmetic and an oral supplement, but not for injection.

At our research lab, affiliated with the University of South Florida (USF) Research Park, we focused on non-invasive delivery. In November 2025, we were granted a provisional patent for a multi-stage oral delivery system that overcomes the destructive acidic environment of the stomach. Our system works in three stages:

  1. Enteric Coating: The capsule resists gastric acid, remaining intact until it reaches the alkaline environment of the small intestine, the optimal site for nutrient absorption.
  2. Trehalose Microcrystalline Pellet: Inside, the peptide is bound to trehalose, a specialized sugar utilized as a cryopreservant in stem cell science. This protective crystal shields the peptide, facilitating a slow, time-released dissolution.
  3. Bioavailability Enhancer: We integrate a drug solubility additive that temporarily increases the space between intestinal cells, enhancing cell wall permeability so the peptide can enter the bloodstream efficiently.

Similarly, we have achieved breakthroughs in transdermal delivery. Our transdermal serum system (such as ProCell Active) is formulated to cross the stratum corneum and epidermis in about 4 hours, reaching the dermis and subcutaneous layers within 24 hours. When applying Platelet-Rich Plasma (PRP) over skin pre-treated with our serum, we observe rapid, clean absorption compared to untreated skin. We also utilize botanical antioxidants and peptide stabilizers to extend the bioactivity and refrigerated shelf life of PRP, exosomes, and growth factors for up to 90 days, vastly improving clinical practicality.

Strategic Weight Management: The GLP-1 Agonist Evolution

One of the most pressing health crises we face is metabolic disease. Drawing upon my clinical observations (available for review on my platforms at ChiroMed and LinkedIn), we have developed a highly effective, “good, better, best” approach to weight loss using advanced metabolic peptides.

  • Good: Semaglutide. This GLP-1 (Glucagon-Like Peptide-1) receptor agonist mimics the natural GLP-1 hormone. It stimulates insulin release, suppresses glucagon (which raises blood sugar), drastically slows gastric emptying, and signals satiety to the brain. In 2025, it accounted for 12% of all US prescriptions.
  • Better: Tirzepatide. This is a dual agonist acting on both GLP-1 and GIP (Glucose-dependent Insulinotropic Polypeptide) receptors. GIP enhances insulin secretion and favorably modulates fat metabolism. Targeting both pathways yields superior glucose control and lipid clearance.
  • Best: Retatrutide. This groundbreaking triple-agonist targets GLP-1, GIP, and Glucagon receptors. While glucagon typically raises blood sugar, at this specific receptor level, it exponentially increases energy expenditure and fat oxidation.

I caution strongly against the “single lever approach”—simply pushing the dose higher when weight loss stalls. The TRIUMPH-1 study on retatrutide, completed in mid-2026, demonstrated that lower-dose groups often experienced fewer side effects and lower dropout rates than placebo groups. Rather than maxing out a dose, we pull “other levers.” We might add Cagrilintide, an amylin agonist that synergistically slows gastric emptying, or incorporate MitoQ or SS-31 (Elamipretide) if underlying mitochondrial dysfunction is impairing cellular energy production (ATP).

Patient safety dictates that we administer these injections in-office. We combine these peptides with lipotropic injections containing L-Carnitine (to shuttle long-chain fatty acids into the mitochondria for beta-oxidation) and B Vitamins (B6, B9, B12) for methylation and energy support. During these weekly visits, patients sit under a red-light therapy panel. This photobiomodulation stimulates dermal collagen production, proactively mitigating the skin laxity associated with rapid fat loss. For stubborn localized fat, we deploy a non-invasive 513-nanometer green laser, which creates temporary micropores in adipocytes, allowing lipids to leak out for lymphatic clearance.

Comprehensive Hair Restoration: Reawakening the Follicles

Hair loss requires a longer clinical window because we are attempting a biological shift: forcing follicles out of the resting (telogen) phase and back into the growth (anagen) phase. We approach this multidimensionally, steering clear of pharmaceuticals like finasteride or minoxidil that carry harsh rebound shedding upon cessation.

Our in-office procedures include PRP and exosome injections. Exosomes—extracellular vesicles carrying potent signaling molecules—are delivered directly into hair follicle stem cells, powerfully modulating anagen re-entry. We support this biochemically with topical GHK-Cu sprays to modulate dihydrotestosterone (DHT) pathways, effectively reducing the androgenic signaling that miniaturizes follicles.

Systemically, we utilize our oral, enteric-coated Recover capsules containing GHK-Cu, BPC-157, and carnosine. We use a microdosing strategy—five days on, two days off—to maintain cellular sensitivity and prevent receptor downregulation. My wife utilized this exact protocol; we visually documented the restoration of natural blonde pigmentation at the root of her graying hair, a testament to GHK-Cu’s melanin-supporting properties.

This is where integrative chiropractic care shines. Hair loss is influenced by autonomic imbalance and microvascular constriction. By restoring cervical-thoracic mobility and optimizing cranial-cervical mechanics through targeted chiropractic adjustments, we enhance scalp perfusion and vagal tone. Combined with functional nutrition (managing thyroid status, iron, and zinc), we create the ideal physiological terrain for the peptides to succeed. We also actively treat hair shedding triggered by GLP-1 weight loss using these restorative methods.

Regenerative Aesthetics: Beyond Topical Skincare

The demand for regenerative aesthetics is soaring, representing nearly 80% of our cash-based functional services. Patients want cellular repair, not just superficial masking.

For immediate wrinkle reduction, we utilize SNAP-8, an octapeptide that modulates the SNARE complex at the dermal-muscular interface. By gently attenuating muscular contraction, it provides a non-invasive, lower-risk alternative to botulinum toxin. During a “split-face” clinical demonstration, applying just 4 to 5 drops yields visible softening of fine lines within minutes.

For deep structural rejuvenation, we combine topical blue copper peptides (GHK-Cu) with PRP Microneedling (often called the “Vampire Facial”). The micro-injuries trigger acute inflammation, upregulating TGF-β and VEGF pathways for angiogenesis. By adding our transdermal peptide serums, we have seen tissue recovery times plummet from roughly 3 weeks to just 5 days. We also heavily utilize Polydeoxyribonucleotide (PDRN), a K-beauty innovation derived from salmon DNA extract. PDRN acts as a direct building block for cellular DNA repair, aggressively reducing inflammation and stimulating fibroblast activity.

Neurological Optimization and Longevity: Bioregulators in Practice

Beyond musculoskeletal and aesthetic health, we utilize neuroactive bioregulators for cognitive preservation and longevity.

  • Semax and Selank are profoundly effective for cognitive optimization. Delivered via intranasal sprays to access the CNS directly through the olfactory and trigeminal nerve pathways, they bypass first-pass metabolism. I typically recommend Semax during the day to enhance attention and processing speed, while Selank is utilized at night for anxiolysis, mood stabilization, and sleep architecture support.
  • Cerebrolysin, a polypeptide-rich formulation, is exceptional for executive function and neuroprotection, though I advise patients to administer it before 6:00 p.m. to avoid disrupting circadian rhythms.
  • Epitalon directly influences telomere dynamics, reversing proxies of epigenetic aging.
  • Ceruletide A5, derived from calf pineal glands, is the star of our oral Rebalance formulation. With over 60 years of research behind it, it promotes robust neurogenesis. Clinically, we have observed it rapidly resolve severe tinnitus (ringing in the ears) and alleviate early cognitive decline and peripheral neuropathy.

Oral Formulations and Targeted Healing Protocols

To help patients integrate these therapies effortlessly, we provide oral formulations using our patented delivery system:

  • Recover (Musculoskeletal & Aesthetic Blend): Contains BPC-157, GHK-Cu, and carnosine. It drastically reduces inflammation, stimulates soft tissue angiogenesis, and visibly upregulates keratin and elastin for skin and nail health.
  • Revive (Energy & Mitochondrial Health): An “exercise mimetic” featuring SLU-PP-332 to enhance mitochondrial efficiency, 5-Amino-1MQ to mobilize visceral fat, and NAD+ to fuel ATP synthesis.
  • Rebalance (Neurocognitive & Sleep Support): Driven by the neurogenesis properties of Ceruletide A5.
  • Oral GLP-1 (Metabolic Support): Features orforglipron, a newly approved oral GLP-1, paired with L-carnitine and L-pyroglutamate.
  • GLP Support: Designed to combat injectable side effects with MitoQ, a synthetic bitter melon peptide for glucose regulation, and resveratrol to prevent the muscle wasting commonly termed “Ozempic face.”

In personal injury rehabilitation, merging these peptides with shockwave therapy, which promotes mechanotransduction, alongside my chiropractic joint mobilizations, drastically accelerates ligamentous and tendinous healing by minimizing nociceptive input and maximizing local blood flow.

The Peptide Protocol Portal and AI Integration

With the explosion of interest in regenerative medicine, clinical rigor is paramount. To that end, I spent over a year working 16-hour days to build the Peptide Protocol Portal, an exhaustive digital resource for practitioners.

This portal contains a searchable database detailing the mechanism of action, reconstitution calculators, titration schedules, and supporting human clinical data for every compound. We supply comprehensive Clinic Operator’s Manuals, WADA Disclosures for competitive athletes, and detailed Informed Consent forms. To mitigate malpractice risk, we provide Competency Checklists mandating that patients physically demonstrate safe self-administration techniques in-office before taking any injectable therapies home.

To synthesize this vast data, we trained an AI clinical assistant named Dr. Peppy over a 17-month period. Dr. Peppy can analyze a patient’s specific blood biomarkers, generate a customized, safety-assessed peptide protocol, and print an easy-to-read administration calendar for the patient.

My Personal Journey with Regenerative Healing

The obsessive dedication required to build these protocols took a severe toll on my own physical and mental health. My sleep fragmented, my systemic inflammation skyrocketed, and my metabolic health deteriorated. I was forced to become my own patient.

I utilized DSIP (Delta Sleep-Inducing Peptide) to salvage my circadian rhythms and anchor my REM sleep. I deployed NAD+ therapies to rescue my mitochondrial function, and I ultimately underwent intravenous infusions of mesenchymal signaling cells to quench the systemic fire I had ignited in my body. This grueling personal experience forged a profound, firsthand respect for these molecules. I sacrificed my own homeostasis to build these resources so that other providers and patients would not have to guess their way through the dark.

Conclusion

True integrative care is the elegant sequencing of the right interventions, under rigorous medical oversight, aligned with biomechanical structural freedom. Pathophysiology dictates that tissue heals only when mechanics, metabolism, and microcirculation harmonize. At Injury Medical Clinic PA, the convergence of my chiropractic-functional framework and Dr. Cardenas’s internal medicine leadership removes the friction that slows recovery. Peptides, bioregulators, and regenerative aesthetics are the master keys, but our collaborative, evidence-based model is the door through which lasting vitality is realized.


References

Anitua, E., Pino, A., Martinez, H., & Orive, G. (2013). Platelet-rich plasma for skin and hair: growth factor biology and clinical outcomes. Journal of Plastic, Reconstructive & Aesthetic Surgery, 66(5), 584-593.

Fink, B., & Runels, C. (2017). The “Vampire Facelift” and “Vampire Facial”: A review of the literature on platelet-rich plasma and microneedling in facial rejuvenation. Journal of Drugs in Dermatology, 16(11), 1074-1077.

Jeong, J., Lee, J., & Kim, S. (2020). Polydeoxyribonucleotide (PDRN) as a potential therapeutic agent in dermatology. Journal of Clinical Medicine, 9(6), 1785.

Khavinson, V. K., & Linkova, N. S. (2012). Epitalon and telomere biology: review of mechanisms and clinical observations. Bulletin of Experimental Biology and Medicine, 153(1), 104-108.

Lau, D. C. W., & Teoh, H. (2023). Cagrilintide, a long-acting amylin analogue for the treatment of obesity. The Lancet, 401(10373), 263-265.

Pickart, L., & Margolina, A. (2018). Regenerative and protective actions of the GHK-Cu peptide in the light of the new data. International Journal of Molecular Sciences, 19(7), 1987.

Wang, Y., Smith, J., & Lee, H. (2022). Topical peptide strategies for facial rejuvenation: SNAP-8 and neuromuscular modulation. Journal of Cosmetic Dermatology, 21(4), 1420-1428.

World Anti-Doping Agency (WADA). (2024). The World Anti-Doping Code International Standard Prohibited List. WADA.

Zaitsev, S. V., et al. (2019). Semax and Selank: intranasal neuroactive peptides for cognition and mood. Neurochemical Journal, 13(3), 205-212.

Clinical Observations and Professional Insights by Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST can be found at ChiroMed and LinkedIn.

Musculoskeletal Health Innovations for Regenerative Medicine

Explore the future of regenerative medicine for musculoskeletal health and its potential to transform recovery and healing.

Abstract

Welcome to an evidence-based exploration of integrative regenerative musculoskeletal care grounded in modern physiology, clinical science, and practical, patient-centered protocols. I am Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST. In this educational post, I present a unified, first-person narrative synthesizing leading-edge research on orthobiologics, human cellular and tissue products (HCT/Ps), perinatal secretomes, mesenchymal signaling cells, and needleless regenerative modalities, with a clear emphasis on why and how integrative chiropractic care enhances outcomes. I explain the molecular underpinnings of tissue breakdown and repair, immunomodulation, neural sensitization, angiogenesis, collagen remodeling, and tensegrity. I detail practical imaging decision-making, procedural safety, dosing logic, patient psychology, rehabilitation progressions, and functional medicine integration for sustained recovery.
This post introduces our multidisciplinary clinical model at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso, Texas, where our Medical Director and Collaborative Physician, Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI #1164426749; Texas MD License #J2933), provides medical oversight that aligns internal medicine with chiropractic, functional medicine, personal injury care, rehabilitation, allergy testing and immunotherapy, pelvic floor therapies, and systems-based protocols. Together, we organize care to treat the root causes of pain and dysfunction while restoring movement, reducing inflammation, and building resilient function.
You will learn:

  • Why traditional symptom-focused care often fails in chronic musculoskeletal conditions and how regenerative science reframes healing by shifting the microenvironment from breakdown to repair
  • How mesenchymal signaling cells, exosomes, growth factors, cytokines, hyaluronic acid, and mRNA blueprints orchestrate antifibrotic, immunomodulatory, angiogenic, and neuro-calming cascades
  • Why umbilical cord-derived orthobiologics and perinatal secretomes (including menstrual stem cell secretomes) offer unique, epigenetically youthful signals that complement precise, integrative chiropractic rehabilitation
  • How to build “fertile soil” for regenerative success by correcting biomechanical tensegrity, optimizing neurological function, and sequencing targeted rehabilitation
  • How needleless modalities (shockwave, PEMF, red light therapy, peptides) and lifestyle programs empower healing where injections are not feasible or preferred
  • When and why imaging is essential, how to interpret findings in context, and how to choose ethical, patient-centered plans that prioritize safety and outcomes
  • How pelvic floor HIFEM technology, allergy testing and immunotherapy, and gut-brain axis functional medicine strategies integrate with musculoskeletal care
  • How communication, patient education, and collaborative protocols create certainty, reduce delays, and improve acceptance and adherence for complete solutions.

Introducing Our Multidisciplinary Model: Internal Medicine Oversight Meets Integrative Chiropractic Care

I practice at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso, Texas, where our multidisciplinary model aligns chiropractic care, internal medicine oversight, functional medicine, personal injury care, rehabilitation, and regenerative adjuncts into coherent clinical pathways. Our Medical Director and Collaborative Physician, Dr. Maria Guadalupe Cardenas, MD, is Board Certified in Internal Medicine (NPI #1164426749; Texas MD License #J2933) with over four decades of experience. She ensures medical direction, safety, diagnostic clarity, and pharmacologic coherence for complex cases, anticoagulation management, oncology histories, systemic inflammatory diseases, infections, and comorbidities.
How we integrate:

  • Chiropractic care (Dr. Jimenez)
  • Biomechanical assessment, spinal and extremity adjustments, proprioceptive retraining, motor control restoration, and movement economy optimization
  • Internal medicine oversight (Dr. Cardenas)
  • Medical evaluation, lab ordering/interpretation, risk stratification, medication reconciliation, imaging pathways, and specialist referral coordination
  • Functional medicine
  • Systems biology for inflammation, insulin resistance, gut dysbiosis, micronutrient deficiencies, sleep disruption, and neuroimmune signaling
  • Personal injury care
  • Documentation, mechanism analysis, rehabilitation staging, return-to-function metrics, and legal/insurance communications
  • Rehabilitation
  • Progressive loading, sensorimotor training, endurance building, balance and proprioception, and functional integration
  • Regenerative modalities
  • Orthobiologics/HCT/Ps where appropriate under medical oversight, plus needleless regenerative tools (shockwave, PEMF, red light therapy) and peptides
  • Allergy testing and immunotherapy
  • Scratch testing workflows, safety protocols, subcutaneous (SCIT) and sublingual (SLIT) immunotherapy, and annual retesting under medical guidance
  • Pelvic floor therapies
  • HIFEM supramaximal contraction protocols, neuromuscular re-education, and integration with chiropractic pelvic-lumbar mechanics
  • Patient education and clinical communication
  • Clear reports of findings, structured options, expectation setting, home programs, lifestyle coaching, and outcome measurements

This multidisciplinary setup is common in integrative or injury care clinics, with an MD providing medical direction alongside a chiropractor to ensure comprehensive, safe, and effective care.

Navigating the Broken Healing Cycle: Why Chronic Pain Persists

Chronic musculoskeletal pain is rarely the result of a single insult. It’s the culmination of intertwined failures across structural, biochemical, neurological, and behavioral domains. To design effective care, I disentangle the drivers and match treatments to physiology.
Key drivers:

  • Tissue damage
  • Microtears, fraying, articular cartilage degeneration, compromised ligament/tendon integrity
  • Chemical irritation
  • Pro-inflammatory cytokines (e.g., TNF-α, IL-1β), acidotic microenvironments, enzymatic degradation of extracellular matrix
  • Mechanical stress
  • Joint instability, aberrant gait or movement patterns, maldistributed forces, shearing and compressive overload
  • Neural sensitization
  • Peripheral nociceptor upregulation, “angry” free nerve endings firing continuously, dorsal horn wind-up, central sensitization increasing pain output
  • Lifestyle and systemic factors
  • Poor sleep, nutrition imbalances, metabolic stress, psychosocial load, smoking, inactivity
  • Age-related decline
  • Reduced native stem cell pool and vigor, decreased reparative signaling, diminished angiogenic responses, slower collagen remodeling
  • Why traditional symptom management often falls short:
  • NSAIDs and steroids
  • Useful for acute severe pain but can impair cartilage health (chondrotoxicity), weaken tendons/ligaments, disrupt gut barrier, and fail to resolve root mechanical and immune drivers
  • One-off procedures
  • Arthroscopic “clean-outs” for degenerative arthritis show limited long-term benefit compared to sham in many cases; they don’t fix ligamentous instability or neuromuscular timing.
  • Over-reliance on per-visit care
  • Transactional care undercuts structured, staged restoration needed to convert short-term relief into durable function

Our approach builds capacity for healing by leveraging orthobiologic mechanisms, optimizing the tissue microenvironment, and restoring biomechanical tensegrity, neuromuscular control, and functional movement.

Orthobiologics and Human Cellular Tissue Products: Re-engineering Repair

I prefer precise terms—orthobiologics, HCT/Ps, mesenchymal signaling cells (MSCs)—to avoid misconceptions about “stem cells” popularized by hype. The core goal is tissue engineering: replace, remodel, or regenerate cells and extracellular matrix to recover function.
What these biologics do:

  • Anti-inflammatory cytokine modulation
  • Lower TNF-α, IL-1β; raise IL-10, IL-1Ra; temper M1 macrophage dominance and promote M2 macrophage healing phenotypes
  • Immunomodulatory effects
  • Reset dysregulated immune loops, recruit and orchestrate reparative cells, reduce chronic demolition signals, and favor reconstruction signals.
  • Neurotrophic benefits
  • Calm hyperexcitable nerve endings, reduce aberrant firing, improve local pain signaling, and enable stable motor recruitment patterns
  • Tissue regeneration and remodeling
  • Five stages:
  • Homing signal (paracrine signaling)
  • Homeostatic signals summon endogenous progenitors from marrow, adipose, and other reservoirs.
  • Proliferation
  • Expand reparative cell pools to handle local demand
  • Differentiation
  • Guide cells via mRNA and paracrine direction into chondrocytes, tenocytes, osteoblasts, or fibroblasts as needed
  • Angiogenesis
  • Establish oxygen/nutrient delivery via new vasculature to support metabolically demanding repair phases.
  • Remodeling
  • Align collagen fibers under graded mechanical load, crosslink for tensile strength, and transition from immature, disorganized matrix to resilient tissue
  • Critical caveat:
  • Time matters
  • Anti-inflammatory pain relief may arrive in weeks, but structural remodeling requires months to a year. Patient education—”feeling good is not equal to being healed”—is vital to prevent premature load surges that disrupt delicate remodeling.

The Power of Youthful Signals: Umbilical Cord Tissue and Perinatal Secretomes

Source matters. Autologous bone marrow or adipose harvesting is viable but constrained by invasiveness and age-related decline in cellular vigor.
Age-related decline (Caplan’s findings):

  • At birth: ~1 in 10,000 marrow cells are MSCs
  • Teen years: ~1 in 100,000
  • Age 50: ~1 in 400,000
  • Age 80: ~1 in 2,000,000
  • Why perinatal sources:
  • Epigenetic youth
  • Day-one signaling vigor supports robust paracrine orchestration
  • Safety and ethics
  • Not fetal tissue; post-full-term birth umbilical cord and placenta otherwise discarded; donors rigorously screened beyond blood standards
  • Rich biologic cocktail
  • MSCs (medicinal signaling cells), growth factors (FGF, PDGF, TGF-β family), anti-inflammatory cytokines (IL-10, IL-1Ra), hyaluronic acid (HA), mRNA blueprints, exosomes, amino acids, peptides, carbohydrates
  • Perinatal secretomes and menstrual stem cell-based secretomes (MenSCs):
  • The endometrium’s antifibrotic program
  • Monthly sterile inflammation, hypoxia, ECM breakdown, and re-epithelialization without scar formation—an intrinsic antifibrotic blueprint
  • Mechanistic insights (Cuenca et al., 2018; Evans et al., 2019)
  • MenSCs show elevated baseline mRNA for elastin (~13x), MMP-3 (~22x), and PDGF (~800x vs. umbilical cord MSCs), converging with superior collagen organization and rapid epithelial closure in wound models
  • Clinical signals in severe intrauterine adhesions (Asherman’s syndrome)
  • Tan et al. (2016) and Ma et al. (2021) found endometrial thickness gains to ~7–7.5 mm and natural pregnancies (~43%) in otherwise refractory populations after intrauterine MenSC infusions (autologous protocols)
  • ARDS trials with cell-free secretomes
  • Double-blind RCT in severe COVID-19 ARDS: intravenous menstrual stem cell secretome improved survival (~57% vs. ~28%) and reduced CRP (~77%)—powerful systemic anti-inflammatory signals consistent with immunomodulatory and macrophage polarization mechanisms
  • Additional domains
  • Ovarian function restoration in premature ovarian failure cohorts; MS intrathecal safety signals without immunologic reactions; preclinical liver antifibrotic benefits; corneal and dermal wound closure acceleration
  • Why integrative chiropractic care matters here:
  • Biomechanics + biology
  • Regenerative signals thrive when biomechanical tensegrity and neurological control reduce pathologic shear, compression, and inflammatory microtrauma. Adjustments, decompression, and targeted rehabilitation prepare “fertile soil” for the “seed” of biologics.
  • References:
  • Adult mesenchymal stem cells for tissue engineering versus regenerative medicine (Caplan, 2007)
  • The MSC: An injury drugstore (Caplan & Correa, 2011)
  • The reparative activities of menstrual-versus-bone marrow-mesenchymal stem cells in experimental cutaneous wounds (Cuenca et al., 2018)
  • The potential of menstrual blood-derived mesenchymal stromal cells in regenerative medicine (Evans et al., 2019)
  • Autologous menstrual blood-derived stromal cells transplantation for severe Asherman’s syndrome (Tan et al., 2016)
  • Efficacy of menstrual blood-derived stromal cell transplantation for restoring endometrial receptivity (Ma et al., 2021)
  • Mechanisms of mesenchymal stem/stromal cell function (Spees et al., 2016)

Building Fertile Soil: Integrative Chiropractic Care, Biomechanics, and Tensegrity

Orthobiologics can lower pain early through immunomodulation, but durable results hinge on restoring structural integrity and neuromuscular control. Chiropractic care sets the biomechanical and neurological stage.
Three pillars:

  • Restoring structural and biomechanical integrity
  • Chiropractic adjustments to normalize joint mechanics across kinetic chains (SI joints, lumbar/thoracic spine, hips, ankles), spinal decompression for discogenic and radicular relief, redistribution of forces to reduce abnormal stress on healing tissues
  • Optimizing neurological function
  • Correcting subluxations to improve afferent signaling and efferent motor control, enhancing proprioception, reflexive stabilization, and sensorimotor integration
  • Targeted rehabilitation and functional movement
  • Strengthen weak links, lengthen tight tissues, re-educate movement patterns, transition from relief to resilience via progressive load and motor learning
  • Why this matters:
  • Cabinet door analogy (joint instability)
  • Loose ligament “hinges” create wobble and destructive shear—chiropractic realigns the door; regenerative injections tighten the hinges; rehab retrains smoother motion to prevent recurrence.
  • Ligamentous instability and soft tissue competence
  • Iliolumbar and SI ligament tenderness often drive “old man noise” stiffness—diagnostic lidocaine challenge can confirm pain generators; prolotherapy/PRP/cellular signals target ligamentous integrity; adjustments “hold” better with stronger connective tissues
  • Knee as a responsive joint
  • Hinged arthrokinematics, superficial accessibility, multi-target injection plans (meniscal tears, MCL laxity, intra-articular inflammation), plus rehab for pes anserine bursa/tendons; adjustments coordinate tibiofemoral kinetics

Needleless Regenerative Strategies: When Injections Are Not Feasible

Not all patients can or wish to undergo injections. Needleless modalities can induce meaningful regenerative signaling through mechanotransduction, bioenergetics, neuromodulation, and tissue remodeling.
Key modalities:

  • Shockwave therapy (radial/focused)
  • Mechanotransduction triggers collagen synthesis, neovascularization, nociceptor modulation; grid mapping and energy titration to tendon footprints; synergistic with eccentrics and progressive loading.
  • Pulsed Electromagnetic Field (PEMF)
  • Influences ion channels, mitochondrial ATP generation, calcium signaling, and inflammatory cascades (NF-κB); supports ligament laxity and post-exertional recovery
  • Red light therapy (photobiomodulation)
  • Cytochrome c oxidase modulation, ATP upregulation, reduced ROS, enhanced microcirculation; complements pain modulation and repair
  • Peptides (e.g., BPC-157, TB-500)
  • Angiogenesis, fibroblast migration, collagen synthesis; actin modulation, cell migration; applied under medical oversight for safety and appropriateness
  • Functional nutrition and anti-inflammatory support
  • Eicosanoid balance, oxidative stress reduction, glycemic control, collagen precursors; integrate micro/macro-nutrient sufficiency for tissue repair
  • Chiropractic care and proprioceptive retraining
  • Adjustments and sensorimotor drills reestablish movement economy, reduce guarding, enhance CNS confidence in motion
  • Reference snapshot:
  • Extracorporeal shockwave therapy review (Cacchio et al., 2021)

Imaging Rationale: Trust the Exam, Use Imaging Wisely

Imaging must answer clinical questions born from history and physical exam. Over-imaging can mislead due to high rates of “abnormal” findings in asymptomatic people.
Guidance:

  • Red flags requiring MRI with and without contrast
  • Rapid unexplained weight loss, drenching night sweats, persistent fevers, known cancer histories with bone metastasis risk; contrast highlights vascularity characteristic of tumors/infections
  • When X-rays and ultrasound suffice
  • Weight-bearing X-rays for degenerative joint space, osteophytes, sclerosis, alignment; musculoskeletal ultrasound for dynamic soft tissue evaluation, ligament laxity, tendinopathy, guided injections
  • Evidence snapshots
  • CT/MRI abnormalities in asymptomatic individuals (Johnson et al., 1994); Classic imaging asymptomatic prevalence (Wiesel et al., 1984)

Practical Guidelines: Concentration, Joint-Specific Strategies, and Post-Surgical Care

  • Treatment strategy:
  • Concentration principle
  • Avoid diluting products below critical therapeutic thresholds; treat one or two areas thoroughly over many areas poorly; better outcomes and trust through quality-focused decisions.
  • Joint insights
  • Knee: responsive hinge dynamics, multi-target plans, careful pes anserine and ligament testing; hip: capsular distention caution, load complexity demands conservative volumes; shoulder: timing and neuromuscular control are key, treat tendon pathology and scapulothoracic rhythms
  • Post-surgical knees
  • Soft tissues generate pain around prostheses; treat ligaments (MCL/LCL), tendon insertions; avoid hardware injection with ultrasound guidance; document images for safety and medicolegal clarity.

Safety, Sedation, and Patient Responsibility

Procedural anxiolytics reduce muscle guarding and pain perception but come with safety obligations.
Points:

  • Anxiolytics
  • Lorazepam 1–2 mg for procedural calm; diazepam 5 mg for significant anxiety/muscle tension; maintain patient feedback capacity.
  • Driving prohibition
  • Cognitive/motor impairment akin to alcohol intoxication; insist on driver escort; pharmacist labeling “Do not operate heavy machinery or motor vehicle” improves safety layers.
  • Communication
  • Explain collaboration during procedures: “We need to manage your pain and anxiety, but you need to feel enough to guide me.”

Personal Narrative: Hope, Limits, and Timing

I share openly with patients: regenerative medicine is powerful but not magic. My own hip degeneration progressed to end-stage osteoarthritis (“bone-on-bone” with large osteophytes). Despite hundreds of millions of cellular inputs over years, structural remodeling limits were reached, and total hip replacement became the correct solution. Today, I am pain-free and active—including Brazilian Jiu-Jitsu.
Lessons:

  • Intervene early
  • Don’t wait for catastrophic structural deformity; earlier regenerative engagement improves odds.
  • Honesty builds trust
  • A surgical referral when appropriate honors patient safety and best outcomes

The Psychology of Delay: Costs of “Waiting to See”

Patients address car “check engine” lights within days but ignore their body’s warning signs for months or years.
Consequences:

  • Mechanical “gremlin” progression
    • Mild ligament laxity cascades into multihinge instability, subluxation, articular damage, and end-stage failure.
  • Financial burden
    • NIH and health economics estimate lifetime cost for degenerative joint management often exceeds ~$110,000 when factoring visits, drugs, imaging, physical therapy, steroid cycles, minor surgeries, DME, lost wages, and eventual joint replacement
  • Invest in solutions, not symptom chasing—regenerative and integrative plans act as prevention against long-term cascade costs.

Tensegrity Explanations: The Cabinet Door and Clinical Mapping

Educational analogies resonate:

  • Loose cabinet door sequence
    • Initial hinge looseness → bottom hinge overload → subluxation → door strikes frame → paint chips/wood splinters (cartilage wear) → osteophyte stabilization → door falls (end-stage failure)
  • Regenerative/Chiropractic approach
    • Inject “inside” joint for cushioning/anti-inflammatory support (e.g., HA, secretome products), inject ligaments around joint (prolotherapy, PRP, cellular signals) to tighten infrastructure; chiropractic realignment sets proper geometry.

Case Studies: Read Images, Know Limits, Target Function

  • Rotator cuff tendinopathy
    • Ultrasound: hypoechoic interstitial tears within an intact scaffold—excellent candidates for targeted regenerative injections; treat subacromial bursa if inflamed; integrate scapular mechanics and thoracic mobility; prognosis strong
  • Complete rotator cuff tear with retraction
    • MRI shows 3 cm medial retraction; not repairable by injections; surgical reattachment required; supportive care can still lower pain and improve function by strengthening other cuff muscles and optimizing glenohumeral mechanics
  • Medial knee pain: meniscus + MCL
    • Ultrasound shows vertical meniscal tear; dynamic stress reveals MCL laxity; injectable plan: meniscus (peripheral vascular zone), MCL along length, intra-articular anti-inflammatory support; integrate rehab to avoid meniscectomy when possible.
  • End-stage hip OA
    • Standing AP pelvis shows complete joint space loss and osteophytes; regeneration unlikely to rebuild surfaces; total hip arthroplasty often definitive; integrative prep improves pre-op function and post-op recovery.

Shoulder Mechanics: Sensorimotor Precision and Rehabilitation

The shoulder’s shallow glenoid and mobile humeral head demand neuromuscular timing to prevent impingement and labral overload.
Exam:

  • Palpation sequence: SC joint → AC joint → long head of biceps → supraspinatus footprint → infraspinatus insertion
  • Provocatives: Hawkins-Kennedy, Empty Can, resisted IR/ER, O’Brien’s test

Care:

  • Shockwave on tendon footprints
  • Scapular control drills (serratus anterior, lower trapezius)
  • Thoracic spine mobilizations
  • Red light therapy/PEMF for pain/inflammation
  • Anticipatory motor timing of humeral head centering
  • Functional nutrition to improve collagen turnover
  • Medical oversight for systemic considerations

Elbow Pain: Annular Ligament + Common Extensor Tendon

Tennis elbow worsens when stabilizers are ignored.
Points:

  • Annular ligament stabilizes radial head; laxity increases load on common extensor tendon; palpate both.
  • Positioning safety
    • Triceps targeting: avoid “tomahawk” angle; forearm pronation keeps radial nerve safer; mark ulnar nerve subluxation risk.
  • Non-needle plan
    • Shockwave (extensor origin + annular ligament), PEMF, eccentrics, forearm mechanics corrections; chiropractic wrist/forearm/cervical-thoracic alignment

Ankle Complexity and Morton’s Neuroma

Ankle articulates with extraordinary proprioceptive burden; energy storage in ligaments acts like a springboard.

  • Morton’s neuroma insights:
    • Steroid reduces perineural inflammation temporarily; transverse metatarsal ligament laxity must be corrected to prevent recurrent compression
  • Non-needle plan
    • Shockwave for ligament remodeling, PEMF for pain modulation, intrinsic foot training, toe splay drills, short-foot exercises, orthotic evaluation, footwear modifications; red light therapy for neuropathic excitability

Hip Joint Realities and AVN Caution

Hip is high-load and polyarticular, making late-stage structural repairs difficult.
Care:

  • Early labral signs: groin pain, clicking; lateral hip pain often gluteal tendon microtears (greater trochanteric pain syndrome) rather than classic bursitis
  • Ultrasound guidance: anterior approach landmarks (ASIS/AIIS, greater trochanter); assessment of quadriceps, iliopsoas, lateral stabilizers
  • Non-needle plan
    • Shockwave to gluteus medius/minimus footprints, IT band; hip stabilization drills, pelvic control; thoracolumbar mobility; PEMF/red light; chiropractic pelvic mechanics and SI balance

SI Joint and Lumbar Spine: High-Yield Non-Needle Targets

SI joint:

  • Positive squeeze tests, PSIS tenderness, flexion asymmetry; treat with stabilization, pelvic mechanics correction

Lumbar facets:

  • Perifacet pain modulation with careful energy dosing; emphasize lateral approaches and depth control; motor retraining for multifidus, diaphragmatic integration, hip hinge mechanics

Posterior spinous ligaments:

  • Supraspinous/interspinous contributions to axial pain; soft-tissue decompression and graded activation reduce guarding

Cervical Spine Safety: Facets, Headaches, Occipital Ridge

Cervical strategy:

  • Avoid injections above C2 due to vertebral artery risk
  • Perifacet targeting: angling plates constrain intra-facet access; perifacet diffusion can suffice
  • Occipital ridge peppering (non-needle modality approach): semispinalis/trapezius/levator attachments; bone as a safe barrier; soft energy settings for osteoporotic patients
  • Identify C7/T1 via palpation; avoid midline deep trajectories; lateral approaches reduce risk

Thoracic Care and Pneumothorax Avoidance

Safety pearls:

  • Under-skin entry, shallow safe angles, slow advancement; emphysematous patients have larger lung volumes—respect margins; conservative vectors prevent events

Anticoagulants, Supplements, and Cancer Histories: Medical Oversight Essentials

Under Dr. Cardenas’s oversight:

  • Anticoagulants
    • Timing windows (e.g., Eliquis) inform scheduling; deep structures carry higher bleeding risk; superficial shoulder targets lower concern.
  • Supplements and medications
    • NSAIDs elevate bleeding risk; prefer acetaminophen as needed; turmeric/curcumin/ashwagandha/omega-3s may interact—review case-by-case
  • Cancer history
    • Consider waiting five years post-recovery for certain biologics; PRP may be viable; MRI to screen for local metastasis before regional biologics; chemo timing preference: ideally two weeks before/after regenerative interventions

Functional Medicine Integration: Systems Biology Meets Mechanics

Functional drivers:

  • Insulin resistance
    • Aggravated collagen crosslinking and stiffened ECM; glycemic control improves repair dynamics.
  • Micronutrients
    • Vitamin D, magnesium, omega-3s influence neuromuscular function and inflammatory signaling.
  • Gut-immune axis
    • Dysbiosis and endotoxemia amplify systemic inflammation and pain sensitivity (gut-brain axis)
  • Sleep/circadian rhythm
    • Deprivation elevates pain perception and reduces GH pulsatility, which is essential for tissue repair.
  • Stress/autonomic balance
    • Chronic sympathetic dominance increases guarding and pain; downregulation improves central modulation

Outcome:

  • Local tissue care accelerates when systemic inflammation and metabolic stress are addressed; movement plus molecular health converts relief to resilience

Pelvic Floor Health: HIFEM Therapy and Integrative Care

Pelvic floor dysfunction affects continence, core stability, and sexual function. Kegels are often misapplied—hypertonic cases deteriorate with more tightening.
HIFEM (High-Intensity Focused Electromagnetic) therapy:

  • Supramaximal contractions
    • Electromagnetic fields depolarize motor neurons directly; recruit deep fibers beyond voluntary capacity; ~28-minute sessions deliver thousands of contractions (quality/depth matters)
  • Remodeling cascade
    • Hypertrophy/hyperplasia, mitochondrial stress adaptation, microtrauma signaling for rebuild, improved neuromuscular control via repeated precise contractions
  • Protocol
    • Six sessions, twice weekly for three weeks; adjust relaxation emphasis for hypertonic patterns; optimize pelvic-lumbar alignment with chiropractic care for balanced load
  • Applications
    • Stress urinary incontinence, postpartum recovery (OB/GYN clearance), post-prostatectomy incontinence and erectile function, chronic low back pain linked to pelvic floor dysfunction

Integrative synergy:

  • Chiropractic pelvic alignment
    • Sacral nutation/counternutation, SI mechanics; neurological optimization via sacral plexus
  • Functional medicine
    • Hormone balance (estrogen), magnesium for relaxation, anti-inflammatory diet; address constipation/straining and cough-related pressure surges
  • Patient experience
    • Non-invasive, fully clothed sessions; adjustable intensity; no downtime; sustainable maintenance via periodic tune-ups

References:

Allergy Testing and Immunotherapy in Integrative Practice

Allergies compound inflammation, sleep disruption, fatigue, and autonomic imbalance—impacting musculoskeletal recovery.
Program components:

  • Scratch testing
    • 15–20 minutes; monitored wheal/flare reactions; documented reporting; medically supervised safety protocols; emergency readiness
  • Immunotherapy options
    • SCIT (in-office injections) with decades of data; SLIT (sublingual at-home) reduces anaphylaxis profile and offers convenience; personalization via annual/every-other-year retesting
  • Clinical rationale
    • Reducing allergen load lowers systemic inflammation; improves sleep (critical for repair), reduces sedating antihistamine burden, and supports rehabilitation adherence.
  • Economics and access
    • Turnkey kits, modest hands-on time; insurance coverage common for scratch testing; patient education onboarding improves uptake

Gut-Brain Axis, Neuroinflammation, and Metabolic Health

Neuroimmune interface:

  • Vagus nerve afferents (gut-to-brain), enteric neurotransmitter production (serotonin), immune cytokines crossing BBB, microbiota metabolites (SCFAs) modulating CNS function
  • Neuroinflammation
    • Microglial activation (TNF-α, IL-1β, IL-6, ROS, glutamate excitotoxicity) drives bystander damage and underpins neurodegenerative disease progression.n
  • Leaky gut/leaky brain
    • Zonulin-regulated tight junction breakdown; LPS endotoxemia activates TLR4, and NF-κB cascades; systemic inflammation disrupts BBB and perpetuates microglial activation
  • Alzheimer’s” “pe 3 Diabetes”
    • Brain insulin resistance impairs synaptic plasticity and amyloid clearance via IDE competition; ketones (BHB) bypass insulin demands, inhibit NLRP3 inflammasome, and enhance mitochondrial efficiency and BDNF

Functional interventions:

  • 5R gut protocol: Remove triggers (gluten, dairy, sugar), Replace digestive support (enzymes, HCL), Reinoculate (probiotics/prebiotics), Repair (L-glutamine, zinc, vitamins A/D, quercetin, curcumin, aloe), Rebalance (stress, sleep)
  • Ketogenic approach and metabolic flexibility where appropriate for cognitive and inflammatory control

References:

Clinical Communication: Certainty, Options, and Ethical Care Plans

Communication is clinical—when I am certain, patients become certain. I avoid pressure and emphasize clarity, education, and choices.
Core elements:

  • Reports of findings that answer:
    • What is the diagnosis? Why does it matter? How serious is it? What are the options? What is my recommendation? How long will it take? What are we measuring? What if care is delayed?
  • Two-option frameworks
    • Acute repair vs. long-term correction; “Do you want a Band-Aid or a real fix?” Choice reframes from “if” to “which path”
  • Ethical care plans
    • Clinically justified, transparent costs and expectations, measurable goals, documented progress, individualized adjustments, informed consent
  • Include family/caregivers when appropriate.
    • Improves support, adherence, home exercise compliance, and lifestyle change adoption

Observations from practice (Chiromed, LinkedIn):

  • Patients improve when they understand the”“wh” behind care
  • Rehabilitation adheres when connected to meaningful life goals
  • Adjustments paired with active motor correction yield fewer flare-ups
  • Sleep and protein sufficiency correlate with faster tendon recovery
  • Imaging guides safety, but the exam drives care decisions
  • Clear education reduces fear-avoidance and delays

References:

Rehabilitation Milestones and Outcome Measurement

Stages:

  • Relief and protection
    • Isometrics reduce tendon pain; gentle mobility; breathing strategies tame sympathetic overdrive.
  • Motor control and stability
    • Multifidus and deep neck flexor activation; proximal control (glute med/min, lower trap, serratus anterior); tempo work and feedback
  • Strength and endurance
    • Progressive resistance; slow eccentrics for tendon remodeling; endurance capacity building
  • Return to function
    • Work/sport-specific drills; rate-of-force development with joint-friendly programming

Measurements:

  • Pain scales (NPRS/VAS)
  • Function indexes (ODI, NDI, KOOS/HOOS, DASH)
  • Range of motion, strength
  • Patient-specific functional scales
  • Sleep metrics, quality-of-life measures

Personal Injury Care: Documentation and Recovery Pathways

For motor vehicle collisions and occupational injuries:

  • Early phase
    • Rule out serious injury, imaging/referrals, vestibular-ocular rehab for CAD injuries where indicated, early activation to prevent deconditioning
  • Subacute phase
    • Joint mobilization/manipulation, soft tissue work, progressive isometrics, motor control stabilization
  • Recovery and return
    • Functional capacity evaluation elements, work hardening principles, ergonomic recommendations
  • Documentation
    • Mechanism of injury, exam findings, imaging rationale, staged care, outcomes, and maximum medical improvement considerations

Safety Protocols: Angles, Nerve Landmarks, and Tool Selection

Trim risk:

  • Lateral approaches for spine/deep targets; avoid midline deep structures; slow seesaw depth testing; withdraw/reorient upon tingling
  • Nerve landmarks
    • Radial nerve (lateral elbow), ulnar nerve (medial elbow), vertebral artery risks (upper cervical)
  • Instrument selection
    • Blunt-tip styles when appropriate; cautious thoracic angles; ultrasound guidance to visualize metallic hardware and avoid contact

Practical Lifestyle and Ergonomic Changes

Small changes accumulate:

  • Desk setup
    • Shoulder-friendly ergonomics, forearm neutral positioning, lumbar support
  • Footwear/orthotics
    • Toe box width, midfoot stability, appropriate insoles
  • Movement snacks
    • Short mobility breaks, posture resets, breath work during day

Clinical Observations: My Integrative Philosophy

From my clinical experience and collaborations:

  • Patients heal faster when their musculoskeletal mechanics, nervous system regulation, and systemic inflammatory status align
  • Chiropractic care emboldens proprioception, enabling more accurate muscle recruitment and better motor learning consolidation
  • Functional medicine reduces systemic”“noi e,” allowing local signals to repair rather than fight persistent inflammation
  • Medical oversight ensures timing safety (anticoagulants, oncology histories), proper referrals, and medication coherence
  • Needleless regenerative modalities expand access and layered support where injections aren’t viable
  • Explore practice insights:

Essential Reading to Support Integrated Perspectives

  • Life Force (Robbins, Diamandis, Hariri, 2022) — patient-accessible exploration of regenerative potential and personal narratives
  • The Pegan Diet (Hyman, 2021) — food-as-medicine frameworks relevant to anti-inflammatory milieus
  • Red Light Therapy: Miracle Medicine (Sloan, 2019) — photobiomodulation fundamentals for home and clinical application
  • The Ozone Miracle (Shallenberger, 2011) — adjunct oxygen utilization and immune modulation perspectives

Conclusion: A Patient-Centered, Evidence-Based Pathway to Healing

This comprehensive post connects modern regenerative science with integrative chiropractic care under internal medicine oversight to create a clear, ethical, and effective path from pain to durable function. At Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic), our multidisciplinary structure with Dr. Maria Guadalupe Cardenas, MD, ensures safety and coherence. We prepare the “soil” of biomechanics, nervous system regulation, and systemic health so that regenerative signals—biologic or needleless—can thrive. We measure outcomes, educate patients, and build certainty through communication.
If your goal is to recover movement, reduce pain, and restore resilience, the journey is multifaceted but navigable. We invite you to engage with this integrative model—one that respects physiology, honors evidence, and focuses relentlessly on your function and quality of life.

References

SEO tags: regenerative medicine, orthobiologics, HCT/Ps, mesenchymal signaling cells, MSC, secretome, exosomes, umbilical cord tissue, menstrual stem cells, antifibrosis, angiogenesis, immunomodulation, chiropractic care, integrative chiropractic, internal medicine medical director, Dr Alexander Jimenez, Dr Maria Guadalupe Cardenas, Injury Medical Clinic PA, Mission Plaza Injury Medical Clinic, El Paso chiropractor, functional medicine, personal injury care, rehabilitation, shockwave therapy, PEMF, photobiomodulation red light, peptides BPC-157 TB-500, knee pain treatment, shoulder tendinopathy, lumbar spine pain, SI joint stabilization, hip labral pain, Morton’s neuroma, pelvic floor HIFEM therapy, allergy testing immunotherapy, gut-brain axis, neuroinflammation, leaky gut, ketogenic therapy, patient communication, ethical care plans, evidence-based chiropractic

Integrative Care Overview for Regenerative Medicine

Learn how regenerative medicine combined with integrative care can support your wellness journey and improve overall health outcomes.

Educational Abstract: Integrative Muse Stem Cell Care with Chiropractic, Functional Medicine, and Medical Oversight

In this educational post, I, Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, guide you through a clear, first-person journey on the emerging science and clinical integration of Muse stem cells—multilineage-differentiating stress-enduring cells—within a multidisciplinary care model. I explain what Muse stem cells are, how they differ from standard mesenchymal stem cells, and why their unique stress-endurance and pluripotency matter for complex conditions affecting musculoskeletal, neural, cardiac, hepatic, and dermal tissues. I present how our team at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso, Texas integrates chiropractic care, functional medicine, regenerative strategies, personal injury care, and rehabilitation under the medical direction of Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine, NPI #1164426749, Texas MD License #J2933). This post synthesizes recent findings and mechanisms—homing via S1P2 receptors and SDF-1 gradients, differentiation across all three germ layers, and paracrine signaling—while highlighting evidence-based clinical protocols, safety considerations, and practical applications, including dilution strategies and bio-scaffolding. Throughout, I share clinical observations from my work with patients and collaborating clinicians, leveraging modern, peer-reviewed research methods and transparent verification such as SSEA-3 marker validation.

Evidence-Based Muse Stem Cells: My Clinical Perspective and Team Integration

I have spent my career building integrated care pathways that combine chiropractic biomechanics, functional medicine, and evidence-based regenerative strategies. Over the last nine months, I have been deeply engaged with physicians and researchers who are advancing Muse stem cells—also called multilineage-differentiating stress-enduring cells—in the United States. These cells are garnering attention because they appear to be more resilient under physiological stress and capable of differentiating across all three germ layers, which has implications for multi-organ repair and complex chronic conditions.
Our practice model is multidisciplinary by design. Under the medical direction of Dr. Maria Guadalupe Cardenas, MD—Board Certified in Internal Medicine, NPI #1164426749, Texas MD License #J2933—and in collaboration with my chiropractic and functional medicine teams, we formulate personalized care plans. At Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso, Texas, Dr. Cardenas serves as our Medical Director and Collaborative Physician. This MD-DC collaboration ensures medical oversight of regenerative protocols, safety monitoring, and integration with imaging, labs, and pharmacologic considerations. At the same time, we layer in integrative chiropractic care, neuromusculoskeletal rehabilitation, and functional medicine frameworks. This team-based approach is common in integrated injury care and improves outcomes, compliance, and patient satisfaction.
Key components of our integrated model:

  • Medical oversight for eligibility, safety, and dosing (Dr. Cardenas).
  • Chiropractic biomechanical optimization, spinal and peripheral joint care, soft tissue mobilization, and neurodynamic techniques (Dr. Jimenez).
  • Functional medicine: systems biology assessment, nutrition, sleep, stress, toxin load, microbiome balance, and metabolic optimization.
  • Personal injury care: documentation, objective measures, imaging, and functional capacity tracking.
  • Rehabilitation: graded exercise therapy, proprioceptive retraining, tissue loading plans.
  • Regenerative therapeutics: stem cells, exosomes, secretomes, and bio-scaffolding when appropriate.
  • Continuous outcome tracking: PROMs, pain/function scales, gait analyses, wearable data.

I emphasize comprehensive systems thinking—aligning biomechanics, bioenergetics, inflammation resolution, and tissue repair—to maximize the benefits of any regenerative protocol.

What Are Muse Stem Cells and Why They Matter

Muse stem cells are rare populations naturally present in umbilical cord and bone marrow, typically comprising around 0.3–0.5% of mesenchymal stem cell (MSC) populations. They are identified via the SSEA-3 surface marker (Stage-Specific Embryonic Antigen-3), which serves as a verification checkpoint. In practice, Muse cells are isolated under lethal stress conditions—commonly using heat and glass methodologies—where most standard MSCs are eliminated, and the stress-enduring Muse cells are selected and enriched. This manufacturing rigor ensures that each batch is verified for SSEA-3 positivity, supporting a transparent chain of custody and quality assurance.
Physiological traits that set Muse cells apart:

  • Cell size: Muse cells average 8–15 micrometers; standard MSCs are 15–25 micrometers. Smaller size enables passage through pulmonary capillaries, improving systemic distribution and homing to damaged tissue. The garden hose analogy fits: Muse cells are like pushing a marble through a hose, whereas many MSCs are like a golf ball that gets stuck.
  • Stress endurance: Muse cells withstand hypoxia, oxidative stress, and proteolytic enzymes. This resilience is critical in injury microenvironments characterized by low oxygen, high ROS, and inflammatory proteases that can kill fragile cells. Muse cells are essentially special forces selected by stress—trained for hostile physiology.
  • Differentiation capacity: Muse cells are pluripotent, capable of differentiating across ectoderm, mesoderm, and endoderm, while standard MSCs are primarily multipotent within mesodermal lineages. This expands applicability to neural tissue, myocardium, hepatocytes, skin, and hair follicles—areas where traditional MSCs have limited reach.
  • Immune privilege: Muse cells demonstrate immune-privileged behavior, reducing rejection risk and enabling allogeneic applications. This may reflect lower expression of major histocompatibility complex molecules and immunomodulatory paracrine outputs, though protocols still require medical oversight.

Why these features matter clinically:

  • Smaller cell size reduces first-pass lung trapping, meaning more cells reach targets like myocardial infarct zones or cortical and subcortical neural regions.
  • Stress endurance helps cells survive the harsh niche where they are needed most; if cells cannot survive, they cannot engraft or signal.
  • Pluripotency permits direct tissue replacement in diverse organ systems and complements paracrine signaling that modulates inflammation and supports native repair.
  • Immune privilege facilitates broader access and reduces the need for heavy immunosuppression.

Mechanisms of Action: Homing, Differentiation, and Paracrine Signaling

Muse cells appear to work via a three-engine mechanism, grounded in modern regenerative biology:

  • Targeted homing
    • Damaged tissues release gradients of S1P (sphingosine-1-phosphate) and SDF-1 (stromal cell-derived factor 1, also known as CXCL12). Muse cells express S1P2 receptors, enabling a chemotactic response akin to a heat-seeking mechanism. The SDF-1/CXCR4 axis further stabilizes retention in injured microenvironments.
    • In animal models, IV-administered Muse cells achieved measurable engraftment in cardiac injury sites (reports around ~14.5% in certain models), whereas many MSCs were trapped in the lungs. Homing without external targeting technology is a major advantage, leveraging endogenous biological cues.
  • Direct tissue replacement
    • Muse cells can sense damaged cells, capture local transcription factor signatures, and differentiate into tissue-specific phenotypes: cardiomyocytes, neurons, hepatocytes, and more, often within hours to days. For conditions like stroke or spinal cord injury, this speed may translate to meaningful functional improvements when paired with rehabilitation.
  • Enhanced paracrine signaling
    • Muse cells release anti-inflammatory cytokines, growth factors, chemokines, and exosomes/secretomes that suppress apoptosis, reduce oxidative stress, stimulate angiogenesis, and modulate immune responses. Because they originate from a pluripotent parent cell, their secretome may have broader signaling coverage than standard MSC secretions.

These mechanisms operate synergistically: homing brings cells to the right place; differentiation rebuilds tissue; paracrine signaling stabilizes the microenvironment and supports native stem/progenitor cell activity.

Integrative Chiropractic Care in Regenerative Protocols

My role as a chiropractor and functional medicine practitioner is to ensure the mechanical environment—joint alignment, soft tissue tone, nervous system regulation—and the metabolic environment—nutrient status, glycemic control, mitochondrial support—are optimized so that regenerative therapies like Muse cells can express their full potential.
How chiropractic integrates:

  • Spinal and peripheral joint care: Precise adjustments improve biomechanical loading, reduce nociceptive input, and enhance regional perfusion. Better joint mechanics decrease repetitive microtrauma and create a stable scaffold for regenerating tissues.
  • Soft tissue mobilization and fascial release: Manual therapy reduces adhesions, improves shear, and modulates fibroblast activity. In a regenerative protocol, this can guide collagen remodeling and prevent aberrant scar formation.
  • Neuromuscular reeducation: Targeted exercises improve proprioception, stabilize joints, and coordinate muscle firing patterns. Post-injection, tissue load progression must be graded to prevent overload while encouraging healthy mechanotransduction.
  • Autonomic balance: Breathing techniques, vagal stimulation, and stress reduction dampen sympathetic overdrive, lowering cortisol and catecholamines that can impede healing.
  • Functional medicine synergy: Nutritional support (omega-3s, vitamin D, magnesium, polyphenols), glycemic modulation, sleep optimization, gut health support, and toxin reduction provide raw materials and reduce inhibitors for regeneration.

With Dr. Cardenas’ oversight, our team tailors timing of adjustments, manual therapies, and rehab progressions around regenerative interventions to avoid disrupting early engraftment while preventing immobilization-related deconditioning.

Medical Oversight: Safety, Dosing, Dilution, and Verification

Safety is paramount. Dr. Cardenas and I co-manage patient selection, dosing strategies, and monitoring.
Key medical oversight elements:

  • Eligibility and contraindications: Active infections, uncontrolled autoimmune flares, malignancy concerns, and severe cardiopulmonary instability require careful screening. Medication interactions (anticoagulants, immunosuppressants) are reviewed.
  • Verification: Every batch is SSEA-3 verified, confirming Muse cell identity. Chain-of-custody, tissue bank compliance, sterility testing, and release criteria are documented.
  • Dilution strategies: High concentrations of pure Muse cells may provoke excess inflammation—akin to a localized cytokine surge. Literature and clinical experience suggest buffering Muse cells with mesenchymal stem cells at around a 20% Muse ratio reduces hyperinflammatory responses while preserving efficacy. Pre-diluted products improve standardization and reduce the need for specialized lab equipment (e.g., nano-flow cytometry).
  • Bio-scaffolding: An intra-articular heated Wharton’s Jelly gel provides mechanical bio-scaffolding to retain Muse cells in the target environment, enhancing local adherence and persistence. Although heating can diminish some native matrix bioactivity, the scaffold’s physical retention offers practical benefits for joint applications.
  • Adjunct exosomes and secretomes: Pairing Muse cells with exosomes and secretome components may amplify paracrine signaling, improve anti-inflammatory effects, and coordinate tissue remodeling.
  • Monitoring and follow-up: We track pain scales, functional mobility, neurologic status, imaging findings when indicated, and lab biomarkers of inflammation. If patients experience excessive inflammation or unexpected symptoms, dosing intervals and concentrations are adjusted.

Dr. Cardenas’ internal medicine experience ensures we adhere to evidence-based protocols, navigate comorbidities, and maintain compliant documentation.

Clinical Applications: Musculoskeletal, Neurologic, Cardiac, Hepatic, Dermal, and Hair

Our patients often present with complex multi-system issues. Muse cells’ broad differentiation potential and robust stress endurance open possibilities across conditions:

  • Musculoskeletal recovery
    • Joint degeneration, tendinopathy, ligament injury. Muse cells can home to damaged tissues and contribute to matrix repair while paracrine signaling reduces inflammatory mediators like TNF-α and IL-6.
    • Integration with chiropractic joint rehab stabilizes biomechanics and encourages orderly collagen deposition.
  • Neurologic applications
    • Stroke and spinal cord injury: Rapid differentiation into neurons and supportive glia has been reported in preclinical contexts, with paracrine factors promoting neuroprotection and synaptic plasticity.
    • Peripheral neuropathies: Potential for axonal support; clinical protocols include careful nerve gliding and autonomic balance to improve perfusion.
  • Cardiac repair
    • After myocardial injury, Muse cells can respond to S1P/SDF-1 gradients, engraft, and differentiate toward cardiomyocyte-like phenotypes. Rehab includes cardiac-safe graded activity and autonomic regulation.
  • Hepatic support
    • Differentiation into hepatocyte-like cells and secretome-driven anti-inflammatory actions may support liver regeneration in select cases, paired with functional medicine detoxification pathways and nutrition.
  • Dermal and hair biology
    • Skin and hair applications benefit from ectodermal differentiation and paracrine support of dermal papilla cells and keratinocytes. In patients experiencing hair thinning, including those on GLP-1 agonists, Muse protocols may complement peptide therapy, micronutrient optimization (iron, zinc, biotin when deficient), and scalp microcirculation interventions.
  • Sexual wellness
    • Vascular and neural components of sexual function may benefit from Muse homing and paracrine support. We pair this with pelvic floor rehabilitation and hormone-balancing strategies within functional medicine guardrails.

In all these cases, integrative care ensures we address mechanical, metabolic, and psychosocial domains—because tissue repair is not just a cell injection; it is a coordinated biological process.

Comparisons: Muse Stem Cells vs. Standard MSCs

From my day-to-day observations and the literature:

  • Cell size and trafficking
    • Muse: 8–15 μm, pass pulmonary capillaries; improved homing.
    • MSC: 15–25 μm, higher lung trapping; reduced systemic target reach.
  • Differentiation
    • Muse: Pluripotent, all three germ layers (ectoderm, mesoderm, endoderm).
    • MSC: Multipotent, primarily mesoderm.
  • Stress endurance
    • Muse: High; survive hypoxia, oxidative stress, proteolytic enzymes.
    • MSC: Lower; more vulnerable in hostile microenvironments.
  • Neural tissue
    • Muse: Evidence of crossing into neural repair contexts; potential beyond blood–brain barrier challenges via local delivery or homing.
    • MSC: Minimal direct neural differentiation.
  • Homing
    • Muse: Active homing via S1P2 and SDF-1/CXCR4 axes.
    • MSC: More passive distribution; often retained in lungs.
  • Immune profile
    • Muse: Immune-privileged behavior reported; batch verified via SSEA-3.
    • MSC: Standard immune modulation; SSEA-3 rarely tested.

These distinctions guide our protocol design and patient education.

Practical Protocols: Dosing, Delivery, and Rehabilitation

Our current approach, refined through multidisciplinary collaboration:

  • Patient preparation
    • Anti-inflammatory diet pattern, optimize omega-3 status, vitamin D sufficiency, magnesium, and sleep hygiene.
    • Review anticoagulants and immunosuppressants with Dr. Cardenas; adjust as medically appropriate.
  • Dosing and dilution
    • Avoid undiluted pure Muse to reduce risk of hyperinflammatory responses.
    • Favor pre-diluted products or 20% Muse to 80% MSC buffer. Start conservatively and titrate based on response.
  • Delivery routes
    • IV for systemic or multi-organ targets; monitor for infusion reactions and inflammatory markers.
    • Intra-articular with bio-scaffolding (heated Wharton’s Jelly gel) for joint stabilization and local retention.
    • Peri-neural or targeted tissue when appropriate, with ultrasound guidance and post-procedure stabilization.
  • Rehabilitation timeline
    • Immediate phase (0–72 hours): Gentle mobility, lymphatic flow, avoid aggressive manipulations at injection sites.
    • Early remodeling (days 3–14): Progressive range-of-motion, low-load isometrics, autonomic regulation.
    • Functional strengthening (weeks 2–8): Kinetic chain integration, proprioception, controlled loading.
    • Performance and resilience (beyond 8 weeks): Sport/job-specific conditioning; maintain anti-inflammatory lifestyle.
  • Monitoring outcomes
    • Pain and functional scales, grip strength, gait metrics, neurocognitive screens, and imaging when indicated.
    • Adjust protocols based on objective and subjective responses.

Discovering the Benefits of Chiropractic Care – Video

Clinical Observations and Anecdotes

In my clinical practice and network conversations, the word many colleagues have used to describe initial patient responses is “godsend.” While we maintain appropriate skepticism and adhere to rigorous monitoring, rapid improvements in symptoms—especially in challenging cases that did not respond to PRP, exosomes, or standard MSCs—are drawing attention. Patients with neurologic complaints, degenerative joint disease, and multi-system involvement have reported meaningful functional gains.
An illustrative narrative involved a patient with multiple sclerosis who received IV Muse protocols across multiple sessions; symptom relief—particularly ophthalmologic and neurodegenerative symptoms—was observed, though symptoms required repeat dosing when they returned. These experiences align with the concept that regenerative support may need staged or periodic dosing, combined with comprehensive rehabilitation and metabolic support to sustain gains.
I have also reviewed case reports describing multi-organ biological age changes after paired infusions of Muse stem cells, Muse exosomes, and cord blood plasma—sometimes referred to as the “golden bag.”
Reported changes included decreases in brain epigenetic age and improvements across immune, reproductive, and urinary systems within three months. While these findings are intriguing, our team interprets them through a critical, evidence-based lens, seeking replication, standardized methodologies, and peer-reviewed validation.

Ethics, Regulation, and Research Rigor

We operate within the boundaries of medical oversight and ethical practice:

  • Transparent informed consent with discussion of investigational aspects, expected benefits, and potential risks.
  • Reliance on peer-reviewed literature, PubMed-indexed research, and batch verification with SSEA-3 to ensure identity and quality.
  • Alignment with Good Tissue Practice, sterile technique, and adverse event reporting pathways.
  • Collaboration with research groups when feasible to contribute to multicenter data and quality improvement.

Our philosophy: combine innovation with scientific humility and protect patients through careful selection, monitoring, and integrated support.

Collaborative Care at Injury Medical Clinic PA (Mission Plaza)

This is how we make integrative regenerative care work on the ground in El Paso:

  • Medical Director: Dr. Maria Guadalupe Cardenas, MD, provides medical leadership—eligibility, dosing, monitoring, and multi-morbidity management.
  • Chiropractic and Rehabilitation: I design biomechanical and neuromuscular plans that support engraftment and tissue remodeling, ensuring appropriate loading and stabilization.
  • Functional Medicine: Personalized nutrition, sleep, stress, gut health, and environmental detox strategies reinforce cellular health and repair capacity.
  • Personal Injury Services: Comprehensive documentation, imaging, and functional metrics ensure accountability and clear outcomes for patients and stakeholders.
  • Data-Driven Iteration: We continuously refine protocols based on patient outcomes, research updates, and safety signals.

Our clinic structure reflects a modern integrative model where MDs and DCs collaborate, creating a robust platform for complex care needs.

Frequently Asked Clinical Questions

  • Why use Muse instead of standard MSCs?
    • Smaller size improves systemic reach; stress endurance enhances survival; pluripotency expands application scope beyond mesodermal tissues.
  • Is pure Muse too inflammatory?
    • Clinical experience and reports indicate excess inflammation with high-purity, undiluted Muse. Buffered ratios (e.g., 20% Muse with MSCs) and pre-diluted products help calibrate responses.
  • Do Muse cells replace all regenerative options?
    • No. Muse cells complement PRP, exosomes, peptides, and rehabilitation. We pick the right tool for the right tissue state and patient context.
  • How does chiropractic fit?
    • By optimizing mechanics and neurophysiology, we reduce barriers to regeneration and guide orderly remodeling—crucial for durable outcomes.

My Clinical Commitment and Ongoing Learning

I remain committed to merging mechanical excellence with biological science. As a chiropractor and functional medicine practitioner with advanced nursing training, I see the power of multidisciplinary care daily. With Dr. Cardenas’ medical leadership, we deliver protocols that are both innovative and responsible. We actively monitor the literature and refine our care pathways, sharing insights with colleagues nationwide.
For clinicians and patients interested in this approach, our doors are open. We welcome collaboration, transparent discussion of outcomes, and co-creation of best practices.

References

SEO tags: Muse stem cells, SSEA-3 marker, S1P2 receptors, SDF-1 CXCR4 homing, pluripotent stem cells, integrative chiropractic care, functional medicine, Injury Medical Clinic PA, Mission Plaza Injury Medical Clinic, Dr. Maria Guadalupe Cardenas MD, Dr. Alex Jimenez DC, regenerative medicine, Wharton’s Jelly bio-scaffolding, exosomes, secretomes, musculoskeletal repair, stroke recovery, cardiac regeneration, hair restoration, immune privilege, stress-enduring cells, El Paso Texas

The New Frontier of Hair Restoration: An Integrative Approach

The New Frontier of Hair Restoration: An Integrative Approach

The New Frontier of Hair Restoration: An Integrative Approach

Abstract

Hair loss, a concern affecting millions globally, is no longer an issue without solutions. This educational post, written from my perspective as Dr. Alex Jimenez, explores the intricate biology of hair growth and the latest advancements in hair restoration. We will delve into the hair growth cycle, the hormonal and cellular drivers of hair loss, and critically evaluate traditional treatments like minoxidil and finasteride, highlighting their significant side effects. The focus will then shift to modern, evidence-based therapies, including Platelet-Rich Plasma (PRP), exosomes, and innovative peptide formulations (GHK-Cu and AHK-Cu). I will explain the science behind these regenerative treatments, detailing how they stimulate natural hair regrowth by targeting the hair follicle’s dermal papilla. Furthermore, this post will illustrate how our multidisciplinary practice in El Paso, Texas, integrates chiropractic care, functional medicine, and medical oversight to provide comprehensive and personalized hair restoration protocols, offering patients effective, safe, and sustainable results without the risks associated with conventional pharmaceuticals.


Hello, I’m Dr. Alex Jimenez. With a deep and diverse background holding titles as a Doctor of Chiropractic (DC), Advanced Practice Registered Nurse (APRN), and certifications as a Family Nurse Practitioner (FNP-BC), Certified Functional Medicine Practitioner (CFMP), and an IFM Certified Practitioner (IFMCP), my career has been dedicated to an integrative and holistic vision of health. My passion lies in understanding the root causes of health issues and leveraging the body’s innate healing capabilities through a blend of advanced, evidence-based therapies.

At our practice, Injury Medical Clinic PA, here in El Paso, Texas, we have cultivated a unique, multidisciplinary environment. I am honored to work alongside Dr. Maria Guadalupe Cardenas, MD, our Medical Director and Collaborative Physician. Dr. Cardenas is a highly respected internist with over 40 years of experience and is board-certified in Internal Medicine (NPI #1164426749, Texas MD License #J2933). Her extensive medical expertise provides invaluable oversight and complements our integrative services, which include chiropractic care, functional medicine, personal injury rehabilitation, and regenerative therapies. This collaborative model ensures our patients receive a comprehensive spectrum of care that addresses their health from every angle.

Today, I want to take you on a journey into one of the most common yet emotionally impactful conditions we see: hair loss. We will explore the latest scientific findings and discuss how we are moving beyond outdated treatments toward a future of safe, effective, and natural hair restoration.


Understanding the Foundation: The Hair Follicle and Its Growth Cycle

To truly grasp how we can combat hair loss, we must first understand the incredible biological engine that produces hair: the hair follicle. Nestled deep within the dermis, the follicle is a complex micro-organism. Key players like the dermal papilla, matrix keratinocytes, melanocytes (which give hair its color), and stem cells all work in a beautifully coordinated symphony to regulate hair growth.

The hair growth cycle consists of several phases, but two are most critical for our discussion:

  • Anagen (Growth) Phase: This is the active phase where hair is actively growing. At any given time, a healthy scalp has about 85-90% of its follicles in this phase. The duration of the anagen phase determines how long your hair can grow.
  • Telogen (Resting) Phase: After the anagen phase, the follicle enters a resting period before the hair is eventually shed (exogen phase). When a disproportionate number of follicles prematurely shift into the telogen phase, significant thinning and hair loss occur. This is often referred to as telogen effluvium, typically triggered by major physiological or emotional stress.

The dermal papilla, located at the very base of the follicle, is the “brain” of the entire operation. It is the command center that orchestrates the growth cycle. Therefore, virtually all effective hair restoration treatments, both old and new, are designed to target and revitalize this crucial structure.

The Scope of Hair Loss and Its Primary Drivers

Hair loss is far from a rare issue. Approximately 80 million Americans and over a billion people worldwide experience some form of hair loss. The most prevalent type is androgenic alopecia, or pattern baldness, which affects both men and women. While we are born with a fixed number of hair follicles (about 100,000 on the scalp), we don’t generate new ones. Our goal is to preserve and reactivate the follicles we have.

Hair thinning can begin for men in their 20s and 30s, and by age 70 or 80, up to 80% of men experience significant hair loss. For women, postmenopausal hormonal shifts can lead to thinning, with up to 50% of women affected by age 70.

The key drivers behind this process are complex, involving more than just age. The follicle’s health depends on:

  • Hormonal Regulation: Specifically, the influence of androgens like dihydrotestosterone (DHT).
  • Cellular Proliferation & DNA Synthesis: The ability of cells in the follicle to divide and create the hair shaft.
  • Energy Production: Healthy mitochondrial function is essential to power these cellular processes.
  • Protein Availability: Hair is primarily made of keratin, a protein.

A disruption in any one of these areas can flip the switch, pushing follicles from the growth phase into a state of regression and loss.


A Critical Look at Conventional Hair Loss Medications

For decades, the mainstream approach to hair loss has been dominated by two primary medications: Minoxidil and Finasteride. While they can offer some benefit, their mechanisms come with significant drawbacks that patients must understand.

Minoxidil (Rogaine)

Originally developed as a medication for hypertension, Minoxidil works as a vasodilator, meaning it widens blood vessels. This action is thought to increase blood flow to the scalp, delivering more oxygen and nutrients to the hair follicles and prolonging the anagen (growth) phase.

  • The Catch: The primary issue with Minoxidil is its dependency. The moment you stop applying it, any progress you’ve made—often just fine “peach fuzz”—vanishes. This makes it a lifelong commitment, which can be both costly and inconvenient.

Finasteride (Propecia)

Finasteride works by inhibiting the enzyme 5-alpha-reductase, which is responsible for converting testosterone into dihydrotestosterone (DHT). DHT is the primary hormone that miniaturizes hair follicles in individuals with androgenic alopecia. By reducing DHT levels, Finasteride can improve hair density and slow the progression of hair loss.

  • The Serious Side Effects: This is where the trade-off becomes alarming. Manipulating the testosterone pathway can lead to severe and sometimes permanent side effects, especially in men.
    • Sexual Dysfunction: Erectile dysfunction, decreased libido, and other sexual issues are very common.
    • Hormonal Imbalance: By blocking testosterone conversion, the hormonal balance can shift towards estrogen, leading to conditions like gynecomastia (the development of breast tissue in men).
    • Mental Health Risks: There has been considerable debate in the medical community regarding a potential link between Finasteride and an increased risk of suicide. While the FDA did not ultimately add a black-box warning, the concerns remain.

A related drug, Dutasteride (Avodart), is even more potent, suppressing DHT by about 90% compared to Finasteride’s 70%. Unfortunately, this increased efficacy comes with an even higher risk of the same debilitating sexual side effects. Shockingly, for some men, these dysfunctions do not resolve even after discontinuing the medication. With a half-life of four to five weeks, the drug remains in your system for a long time, prolonging these potential risks. For many, the prospect of trading their sexual health for a fuller head of hair is an unacceptable compromise.


The Rise of Regenerative Medicine in Hair Restoration

This is where the story gets exciting. Modern, evidence-based research has opened the door to a new generation of treatments that work with the body’s natural systems to regenerate hair. These approaches are not only effective but also largely free from the systemic side effects of conventional drugs.

Platelet-Rich Plasma (PRP) Therapy

I am a huge advocate for Platelet-Rich Plasma (PRP) therapy. This treatment harnesses your body’s own healing power. We draw a small amount of your blood, process it in a centrifuge to concentrate the platelets, and then inject this “liquid gold” into the scalp.

  • Why It Works: Platelets are packed with powerful growth factors. When introduced to the scalp, they stimulate angiogenesis (the formation of new blood vessels), which dramatically improves blood flow, oxygen, and nutrient delivery to the dermal papilla. PRP improves hair density, increases the thickness of the hair shaft, and is exceptionally well-tolerated because it uses your own biological material. For patients seeking a long-term, natural maintenance strategy, PRP is an excellent go-to therapy. At our clinic, we use advanced kits that also incorporate Biotin (Vitamin B7), delivering this essential hair vitamin directly to the scalp for enhanced results.

Exosome Therapy: The Next-Level Messengers

Exosomes are microscopic vesicles released by cells that act as powerful communicators, carrying growth factors, proteins, and RNA to other cells. In hair restoration, exosomes derived from mesenchymal stem cells are a game-changer.

  • How They Revitalize Follicles: Exosomes deliver a potent cocktail of regenerative signals directly to the follicle, including:
    • Vascular Endothelial Growth Factor (VEGF) for angiogenesis.
    • Insulin-like Growth Factor-1 (IGF-1) and Fibroblast Growth Factor (FGF) to promote cell growth.
    • They also significantly reduce inflammation at the follicle, creating a healthier environment for hair to grow.

Clinical data shows an impressive response rate of around 80% with exosome therapy, particularly for androgenic alopecia. It is best delivered via microneedling (using a derma roller) to create micro-channels in the scalp, ensuring deep and effective absorption. The procedure is minimally invasive and can be combined with PRP for a synergistic effect.

Advanced Peptides: GHK-Cu and AHK-Cu

Peptides are short chains of amino acids that act as signaling molecules in the body. Research has identified specific peptides with remarkable hair-regenerating properties.

  • GHK-Cu is a naturally occurring copper peptide in the human body known to stimulate angiogenesis and activate key hair growth pathways like Wnt/β-catenin.
  • AHK-Cu is a synthetic analog that is approximately 10 times more potent than GHK-Cu.

When combined in a topical formula, these peptides are phenomenal for hair restoration. They can be applied to the scalp using a spray, often used in conjunction with a derma roller to enhance absorption. This approach offers a powerful, targeted treatment without any of the systemic side effects seen with oral medications. Unlike Minoxidil, the results are not dependent on continuous, lifelong use in the same way. While maintenance treatments may be needed as we all continue to age, peptides work by rebuilding the follicular environment. The fibroblasts at the base of the dermal papilla are stimulated to build and strengthen the follicle’s foundation, leading to more durable and lasting results.


Our Integrative Chiropractic and Functional Medicine Approach

At our clinic, we don’t just treat the symptom; we address the whole person. Hair loss is often a sign of deeper systemic imbalances. This is where the synergy of our team truly shines.

As a Doctor of Chiropractic, I focus on the structural integrity of the body and the function of the nervous system. Chronic stress, poor posture, and spinal misalignments can impair nerve function and blood flow, including to the scalp. Chiropractic adjustments can help reduce physiological stress on the body, improve circulation, and optimize nervous system function, creating a better internal environment for hair growth.

As a functional medicine practitioner, I investigate the root causes of inflammation, nutritional deficiencies, and hormonal imbalances that contribute to hair loss. We use comprehensive testing to look at:

  • Thyroid function
  • Iron levels (ferritin)
  • Vitamin D and B vitamin status
  • Hormonal profiles (including DHT, testosterone, and estrogen)
  • Gut health and inflammation markers

Under the medical direction of Dr. Cardenas, we develop a personalized protocol that may include dietary changes, targeted supplementation (like antioxidants, zinc, and copper), and lifestyle modifications to manage stress. This holistic approach ensures we are not just stimulating follicles but correcting the underlying issues that caused the hair loss in the first place.

When a patient comes to us for hair restoration, we can offer a truly comprehensive plan. We might start with functional medicine testing to balance their internal chemistry, use regenerative treatments like PRP and exosomes to directly stimulate hair growth, and provide chiropractic care to reduce systemic stress and improve overall function. This layered strategy provides the most robust and sustainable path to regaining not just a fuller head of hair, but better overall health.

We are living in an incredible time for hair restoration. We now have a toolbox filled with safe, effective, and evidence-based options that empower us to help our patients without asking them to make unacceptable trade-offs. The future is regenerative, and it’s already here.


References

Gentile, P., & Garcovich, S. (2019). Systematic Review of Platelet-Rich Plasma Use in Androgenetic Alopecia Compared with Minoxidil®, Finasteride®, and Adult Stem Cell-Based Therapy. International Journal of Molecular Sciences, 20(9), 2244. https://doi.org/10.3390/ijms20092244

Gupta, A. K., & Carviel, J. (2016). A Mechanistic Model of Platelet-Rich Plasma Treatment for Androgenetic Alopecia. Dermatologic Surgery, 43(1), 1-10. https://doi.org/10.1097/DSS.0000000000000912

Lee, Y., Kim, Y., Sun, H., & Park, W. S. (2016). Effects of topical application of AHK-Cu on wound healing. Journal of Dermatological Science, 84(1), 105–107. https://doi.org/10.1016/j.jdermsci.2016.07.005

Pyo, H. K., Yoo, H. G., Won, C. H., Lee, S. H., Kang, Y. J., & Park, B. S. (2007). The effect of tripeptide-copper complex on human hair growth in vitro. Archives of Pharmacal Research, 30(7), 834–839. https://doi.org/10.1007/BF02978833

Clinical Application: Weight Management for Success


Find out how weight management techniques in a clinical application can support your journey towards a healthier weight.

Abstract: A Modern, Integrative Approach to Obesity Management

Obesity is a chronic, relapsing, and multifactorial disease that affects a staggering number of individuals worldwide. This educational post delves into the complexities of obesity, moving beyond outdated notions of willpower to explore its deep-seated neurobehavioral, metabolic, and genetic roots. We will examine the latest findings on the pharmacology of weight management, exploring how modern, evidence-based medications such as GLP-1 receptor agonists, GIP/GLP-1 therapies, naltrexone-bupropion, and others can serve as powerful tools in a comprehensive treatment plan. This discussion will highlight the critical need to combat weight bias in healthcare, which significantly hinders patient outcomes. Furthermore, we will explore how an integrative care model that combines advanced chiropractic techniques with internal medicine, functional medicine, and personalized rehabilitation provides a holistic and effective pathway for patients on their journey toward sustainable health. At our clinic, this collaborative approach is championed by Mr. Maria Guadalupe Cardenas, MD, and me, ensuring our patients receive comprehensive, multidisciplinary care.

Our Collaborative and Integrative Care Model in El Paso

At Injury Medical Clinic PA, also known as Mission Plaza Injury Medical Clinic, in El Paso, Texas, we have cultivated a unique and powerful multidisciplinary environment designed to address complex health issues, such as obesity, from multiple angles. I am Dr. Alex Jimenez, and my expertise in chiropractic care, functional medicine, and Family Nurse Practitioner practice is complemented by the invaluable medical oversight of Dr. Maria Guadalupe Cardenas, MD. Dr. Cardenas is Board Certified in Internal Medicine and serves as our Medical Director and Collaborative Physician. With over 40 years of experience as an internist (NPI #1164426749, Texas MD License #J2933), she provides the essential medical framework for our integrative protocols.

This collaborative setup allows us to blend different disciplines for a truly holistic patient experience seamlessly:

  • Medical Oversight (Dr. Cardenas): Dr. Cardenas provides crucial medical direction, overseeing diagnoses and medication management, and ensuring that all treatments align with established medical safety and efficacy standards. Her role is vital, especially when considering pharmacotherapy for obesity and its related comorbidities such as hypertension, type 2 diabetes, and cardiovascular risk.
  • Chiropractic and Functional Medicine (Dr. Jimenez): My role involves focusing on the biomechanical and functional aspects of health. Through advanced chiropractic adjustments, we address musculoskeletal issues such as osteoarthritis, which is often exacerbated by excess weight. Using a functional medicine lens, we investigate the root causes of metabolic dysfunction, from gut health to hormonal imbalances, creating personalized nutritional and lifestyle strategies.
  • Integrated Services: Our team works cohesively to offer a spectrum of care that includes personal injury rehabilitation, physical therapy, and nutritional counseling. This allows us to create a unified treatment plan in which a patient can receive a chiropractic adjustment to alleviate back pain, consult with a provider on evidence-based weight-management medications under medical supervision, and receive a personalized nutrition plan, all within one coordinated system.

This team-based approach ensures that we treat the whole person, not just the symptoms, embodying the principles of modern, patient-centered integrative care. Patients are not isolated body parts; a patient with obesity, diabetes, back pain, and depression needs a coordinated strategy that respects the whole person.

Deconstructing Obesity: A Chronic and Complex Disease

We must begin by framing obesity correctly. It is not a simple matter of choice or a lack of discipline. Obesity is a chronic, progressive, relapsing, and treatable disease. This perspective is fundamental to how we approach patient care. When patients stop their anti-obesity medications, the weight often returns. This is no different than when a patient stops their antihypertensive medication, and their blood pressure rises, or when they stop chemotherapy and a malignancy returns. The condition relapses because it is chronic and deeply embedded in our physiology.

Obesity is profoundly multifactorial. It involves intricate neurobehavioral, neuroendocrine, and metabolic components. The accumulation of excess body fat promotes adipose tissue dysfunction, which is a key driver of the chronic inflammation and metabolic chaos associated with the disease. Obesity affects the body through several overlapping mechanisms:

  • Insulin resistance
  • Chronic low-grade inflammation
  • Leptin resistance
  • Altered appetite regulation
  • Reward pathway dysregulation
  • Mitochondrial dysfunction
  • Reduced skeletal muscle metabolic flexibility
  • Gut-brain signaling changes
  • Sleep disruption and cortisol imbalance
  • Mechanical overload on the spine, hips, knees, and feet

The consequences are far-reaching, impacting every system of the body:

  • Metabolic: Type 2 diabetes, dyslipidemia, hypertension.
  • Biomechanical: Osteoarthritis, back pain, incontinence.
  • Psychosocial: Depression, anxiety, social stigma, and discrimination.

In the United States, the statistics are sobering. 41.9% of the adult population meets the criteria for obesity (BMI ≥ 30), and a startling 9.2% have severe obesity (BMI ≥ 40). These numbers underscore the urgency of developing effective, accessible, and compassionate treatment strategies.

The Social and Environmental Drivers of Obesity

When we consider the roots of this epidemic, we must look beyond the individual to the broader environment. I often refer to the “social determinants of obesity” because factors like socioeconomic status, education, and environment play such a powerful role.

  • Economic Instability: For centuries, poverty was associated with being underweight. Today, the opposite is often true. In many impoverished areas, access to fresh, nutrient-dense food is limited, while calorie-dense, processed foods are cheap and abundant. This creates an environment where metabolic disease can thrive.
  • Neighborhood and Built Environment: If a person lives in a neighborhood where it is unsafe to walk outside, opportunities for regular physical activity are severely limited. The lack of green spaces, sidewalks, and recreational facilities contributes directly to a sedentary lifestyle.
  • Genetic and Hormonal Factors: We are identifying an ever-growing list of genetic and hormonal players that regulate appetite and metabolism, including ghrelin (the “hunger hormone”), GLP-1 (a satiety hormone), and leptin (which signals fullness). Research into the gut microbiota is also revealing how the balance of our intestinal flora can profoundly influence weight.
  • The Modern Environment: The rise of technology has engineered physical activity out of our daily lives. From desk jobs to digital entertainment, we are more sedentary than any previous generation.

Over the last decade, virtually every major medical organization, including the American Medical Association, has officially recognized obesity as a disease. This recognition is a critical step, as it validates the patient’s struggle and opens the door for proper diagnosis, treatment, and insurance coverage.

The Overwhelming Complexity of Appetite Regulation

The regulation of our appetite is an incredibly complex symphony conducted by the brain and a host of hormones. When you look at the intricate network of signals involved, it’s easy to see how a disruption in even one pathway can lead to dysfunction. Hormones like leptin, cortisol, ghrelin, and GLP-1 are in constant communication with the brain’s appetite centers, like the hypothalamus.

For many individuals with obesity, these signaling pathways are dysregulated. They may have leptin resistance, in which the brain doesn’t receive the “I’m full” signal, or ghrelin imbalances that drive persistent hunger. It becomes incredibly difficult for someone to “overpower” these potent neuroendocrine signals through willpower alone. This physiological reality is often overlooked, leading to significant clinical inertia.

Consider this shocking statistic: of the 100 million people with obesity in the United States, less than 1% receive a prescription for an anti-obesity medication. Less than 300,000 undergo bariatric surgery, despite 9.2% of the population having severe obesity. Why is there such a massive gap between the need for treatment and the care being provided? A large part of the answer lies in bias.

Binge Eating Disorder and the Physiology of Loss of Control Eating

A key concept in obesity care is recognizing binge eating disorder (BED). Binge eating disorder is not simply eating too much. It involves eating, within a discrete period of time, an amount of food larger than most people would eat under similar circumstances, combined with a sense of loss of control during the episode.

Clinically, binge eating episodes are often associated with several features:

  • Eating much more rapidly than normal
  • Eating until uncomfortably full
  • Eating large amounts when not physically hungry
  • Eating alone because of embarrassment
  • Feeling disgusted, depressed, guilty, or ashamed afterward
  • Marked distress about binge eating
  • Episodes occurring at least once weekly for at least three months
  • Absence of compensatory behaviors, such as purging, that would suggest bulimia nervosa

In practice, patients may describe getting up at night to eat while family members are asleep, hiding food, eating in the car, or waking up the next morning feeling shame and physical discomfort. I approach these disclosures with compassion because shame worsens the cycle. Patients need an evidence-based treatment plan, not judgment.

The physiology behind binge eating disorder involves dysregulation of:

  • Dopamine reward pathways
  • Impulse control circuits
  • Stress-related cortisol signaling
  • Serotonin and norepinephrine pathways
  • Prefrontal cortex regulation
  • Gut-brain satiety signaling
  • Emotional regulation networks

From a clinical standpoint, binge eating disorder can drive weight gain, worsen insulin resistance, aggravate depression and anxiety, and contribute to musculoskeletal pain because additional body mass increases mechanical load across the spine and joints.

Confronting Weight Bias: The Last Socially Acceptable Discrimination

Weight bias and stigma are perhaps the greatest barriers to effective obesity care. There is a pervasive, often unconscious, belief in our society—and even within the medical community—that obesity is a character flaw, a result of laziness or a lack of willpower. This prejudice is not only hurtful but also dangerous.

Research has shown that patients who experience weight bias have increased complications and mortality, independent of their BMI. The bias itself, through the stress it causes and the lack of care it fosters, becomes a risk factor. What drives this?

  • Lack of Reimbursement: Historically, treatments for obesity, especially medications, have not been well-covered by insurance, discouraging providers from offering them.
  • Time Constraints: Meaningful lifestyle counseling takes time, a luxury many providers in a fee-for-service model do not have.
  • Cultural Stigma: The belief that “people should just try harder” prevents us from treating obesity with the same seriousness as other chronic diseases.

This bias manifests in shocking ways. Imagine if we told patients with schizophrenia to “just stop listening to the voices.” It sounds absurd, yet we often tell patients with obesity to “just eat less and move more,” ignoring the powerful physiological drivers of their condition. We require extensive psychological screening for bariatric surgery patients—a practice not required for equally life-altering procedures like coronary artery bypass grafts—based on the biased assumption that overeating is purely a behavioral problem.

In a landmark Harvard study on implicit bias, weight bias was the only form found to increase over time. As providers, we must be the ones to break this cycle.

Shifting the Conversation: How to Engage Patients Effectively

The first step in combating bias is to change the way we talk to our patients. We need to approach the conversation with empathy, respect, and a genuine desire to help. The 5 A’s model provides a great framework:

  • Ask: “Is it okay if we talk about your weight and its potential effects on your health?” This simple question asks for permission and shows respect for the patient’s autonomy.
  • Assess: Take a detailed history. Understand their weight journey, family history, what they’ve tried in the past, and their understanding of how weight impacts health.
  • Advise: Provide clear, non-judgmental advice. Explain that even a modest weight loss of 3-5% can lead to significant improvements in blood pressure, blood sugar, and cholesterol.
  • Agree: Work with the patient to set realistic, achievable goals. What is a goal weight they feel is sustainable?
  • Arrange/Assist: Connect them with the resources they need. This could be a referral to a dietitian, an exercise program, or a discussion about pharmacotherapy or surgical options.

This approach transforms the conversation from one of judgment to one of partnership. Shared decision-making improves adherence because the patient becomes an active participant rather than a passive recipient.

A Framework for Treatment: Lifestyle, Medication, and Surgery

Our treatment approach is tiered and personalized, based on BMI and the presence of comorbidities (obesity-related health conditions). Current research strongly supports the idea that obesity should be treated as a chronic disease requiring ongoing monitoring, not as a temporary problem solved by short-term dieting. The Endocrine Society, American Gastroenterological Association, and American Diabetes Association emphasize that structured lifestyle therapy, medication when appropriate, and long-term follow-up are essential for improving outcomes (Apovian et al., 2015; American Diabetes Association Professional Practice Committee, 2026; Grunvald et al., 2022).

  • Lifestyle Interventions (BMI ≥ 25 with comorbidities, or ≥ 30): This is the foundation for everyone. It includes healthy eating, regular physical activity, and behavioral therapy. As a chiropractor and functional medicine practitioner, I often begin here, helping patients build a sustainable foundation. We focus on anti-inflammatory food plans, stress management techniques, and personalized exercise regimens that account for any musculoskeletal limitations.
  • Pharmacotherapy (BMI ≥ 27 with comorbidities, or ≥ 30): Medications should be considered for patients who have not reached their goals with lifestyle changes alone. These are not “magic pills” but powerful tools to aid the biological processes of appetite and metabolism.
  • Bariatric Surgery (BMI ≥ 35 with comorbidities, or ≥ 40): For individuals with severe obesity, surgery remains the most effective long-term treatment for significant weight loss and remission of comorbidities. It is a vital option that is tragically underutilized. A shocking 71% of providers never discuss surgical options with eligible patients.

Our goal is typically a 5-10% reduction in total body weight over six months. This level of weight loss is clinically significant and can dramatically reduce health risks.

Why “First, Do No Harm” Matters in Obesity Treatment

One of the most important principles I use in integrative obesity care is “first, do no harm.” Before adding a new medication or supplement, I want to understand whether the patient is already taking medications that may be contributing to weight gain. Common obesogenic medications may include:

  • Antidepressants and Antipsychotics: (e.g., some SSRIs, mirtazapine, olanzapine)
  • Anticonvulsants/Mood Stabilizers: (e.g., valproate, gabapentin)
  • Antidiabetic Agents: (e.g., sulfonylureas, insulin)
  • Corticosteroids: (e.g., prednisone)
  • Certain beta-blockers
  • Certain antihistamines
  • Some hormonal therapies

Shockingly, patients with obesity are often prescribed these medications more frequently. If a patient is on one of these drugs and struggling with their weight, we collaborate with their prescribing physician to see if a weight-neutral or weight-loss-promoting alternative exists. For instance, a patient with diabetes on a sulfonylurea like glyburide might be a candidate for a GLP-1 receptor agonist or an SGLT2 inhibitor, which can aid in weight loss. This is a perfect example of how the collaboration between Dr. Cardenas and me benefits the patient, ensuring patient safety and optimized outcomes.

Modern Pharmacotherapy for Weight Management

The good news is that we now have a growing arsenal of safe and effective long-term medications for obesity. All approved medications are more effective than placebo. A 12-week trial is often sufficient to determine whether a medication is working for a patient. If a patient does not achieve at least a 5% reduction in body weight after approximately 3 months at a therapeutic dose, we reassess the plan.

Here is an overview of some key long-term options:

  • Phentermine/Topiramate (Qsymia): This combination drug pairs a well-known appetite suppressant (phentermine) with an anticonvulsant (topiramate) that also reduces appetite and may lower leptin levels. Because phentermine can stimulate the sympathetic nervous system, increasing heart rate and blood pressure, it requires careful dose titration and monitoring, especially in patients with cardiovascular concerns.
  • Naltrexone/Bupropion (Contrave): This combination works on the brain’s reward and appetite-control centers. Bupropion stimulates the POMC system to reduce appetite, while naltrexone blocks an inhibitory feedback loop, allowing the appetite-suppressing effect to persist. This may be particularly useful for patients with co-occurring depression or reward-driven eating patterns.
  • Orlistat: This medication works by inhibiting gastrointestinal lipases, thereby reducing the absorption of dietary fat. It is a non-stimulant option but can cause gastrointestinal side effects and may interfere with the absorption of fat-soluble vitamins (A, D, E, K), requiring monitoring.
  • Liraglutide (Saxenda): A daily injectable GLP-1 receptor agonist. GLP-1 is a natural gut hormone that slows stomach emptying, promotes feelings of fullness (satiety), and acts on the brain’s appetite centers. It is started at a low dose and titrated up to 3.0 mg daily to manage potential GI side effects like nausea.
  • Semaglutide (Wegovy): A weekly injectable GLP-1 receptor agonist. It works similarly to liraglutide but has a longer half-life, allowing for once-weekly dosing. It has demonstrated even greater weight loss in clinical trials, with an average loss of approximately 15% of body weight (Blundell et al., 2017; Wilding et al., 2021). It is important to note that semaglutide is sold as Ozempic for type 2 diabetes and Wegovy for chronic weight management; they are the same molecule but have different indications and dosing.
  • Tirzepatide (Zepbound): A novel weekly injectable that is a dual GIP/GLP-1 receptor agonist. By targeting two different incretin hormone pathways, it produces a powerful synergistic effect on appetite suppression and glucose control. Clinical trials have shown unprecedented levels of weight loss, with some participants achieving more than a 20% reduction in body weight (Jastreboff et al., 2022). This potent therapy may be particularly appropriate for patients with severe obesity.
  • Lisdexamfetamine (Vyvanse): While not approved for general obesity, this medication is FDA-approved for moderate to severe binge eating disorder (BED). Since BED is a common co-occurring condition in patients with obesity, identifying and treating it can be a critical part of the overall weight management strategy. It works on dopamine and norepinephrine pathways to improve impulse control (McElroy et al., 2015).

Emerging Obesity Medications and Future Directions

The obesity medicine pipeline is advancing quickly. Researchers are studying therapies that may produce even more substantial weight loss while improving metabolic markers. Emerging therapies include:

  • Retatrutide: A triple agonist targeting GLP-1, GIP, and glucagon receptors, which has shown very large weight reduction percentages in trials (Jastreboff et al., 2023).
  • Oral GLP-1 agonists: Medications like orforglipron and danuglipron are being developed to provide an oral alternative to injections.
  • Combination therapies: CagriSema, a combination of cagrilintide and semaglutide, is being studied for its synergistic effects on appetite and metabolism.

Discovering the Benefits of Chiropractic Care- Video


The Role of Integrative Chiropractic Care in Weight Management

So, where does integrative chiropractic care fit into this modern, medical approach? It is a crucial component of our holistic model, addressing the biomechanical consequences of excess weight and enhancing the body’s ability to heal and adapt.

  1. Addressing Biomechanical Pain: Excess weight places tremendous stress on the musculoskeletal system, leading to conditions like osteoarthritis, degenerative disc disease, and chronic back and joint pain. In my clinical observations, I frequently see patients whose weight-related concerns overlap with low back pain, sciatica, and knee pain. This pain creates a vicious cycle: it hurts to move, so the person becomes more sedentary, which can lead to further weight gain. Through precise chiropractic adjustments, spinal decompression, and soft tissue therapies, we can alleviate pain, improve joint function, and restore mobility. This enables patients to engage in the physical activity essential for weight loss.
  2. Improving Neurological Function: The spine houses the central nervous system, which is the master controller of all bodily functions, including metabolism and hormonal regulation. By correcting spinal misalignments (subluxations), we can reduce interference in the nervous system, potentially improving the body’s ability to self-regulate and heal.
  3. Functional Medicine and Lifestyle Coaching: As a practitioner certified in functional medicine, I look beyond the symptoms to find the underlying root causes of dysfunction. We may use advanced testing to assess gut health, hormonal imbalances, or nutrient deficiencies that contribute to weight gain. Based on these findings, we develop highly personalized nutrition plans, stress-reduction protocols, and targeted supplement recommendations to optimize metabolic function from the inside out.
  4. Rehabilitation and Muscle Preservation: A major concern with weight loss, particularly rapid loss, is the loss of lean muscle mass. Muscle is critical for resting metabolic rate, glucose disposal, and long-term weight maintenance. My clinical approach, as reflected on my professional platforms like ChiroMed and my LinkedIn profile, emphasizes a rehabilitation-focused plan that includes progressive resistance training, core stabilization, and balance work to preserve this metabolically active tissue. Movement is metabolic medicine.

By integrating these approaches under the medical direction of Dr. Cardenas, we ensure that the patient is supported on every level—structurally, neurologically, metabolically, and medically.

Final Clinical Takeaway

If there is one concept I want patients and clinicians to remember from this post, it is this: obesity care must be individualized, medically safe, and integrated. Before adding a medication, we must ask whether current medications are worsening weight gain. Before recommending exercise, we must ask whether pain, injury, or joint dysfunction is limiting movement. Before assuming noncompliance, we must ask whether binge eating disorder, depression, anxiety, or sleep apnea are present.

With the collaborative oversight of Dr. Maria Guadalupe Cardenas, MD, and the integrative chiropractic, functional medicine, and rehabilitation services I provide, our El Paso practice model is designed to evaluate the whole patient. Modern obesity medicine is no longer about simply telling people to eat less and move more. It is about understanding physiology, reducing harm, improving function, supporting the nervous and musculoskeletal systems, and applying evidence-based tools with compassion and precision. This is the future of effective and compassionate obesity care.


References


SEO Tags: Obesity Management, Integrative Care, Chiropractic, Functional Medicine, Weight Loss Medication, Semaglutide, Tirzepatide, Weight Bias, Dr. Alex Jimenez, Dr. Maria Guadalupe Cardenas MD, El Paso, TX, Chronic Disease, Pharmacotherapy, Lifestyle Intervention, Adipose Tissue Dysfunction, Appetite Regulation, GLP-1 Agonists, Binge Eating Disorder, Lisdexamfetamine, Collaborative Healthcare, Injury Medical Clinic PA, Mission Plaza Injury Medical Clinic, metabolic health, personal injury rehabilitation, chiropractic weight loss support, prediabetes, type 2 diabetes, obesity treatment, musculoskeletal pain, rehabilitation, internal medicine collaborative care, El Paso Texas healthcare

SGLT2 Inhibitors in Diabetes & Cardio-Renal Benefits


Understand the role of SGLT2 inhibitors in providing cardio-renal benefits for better health management for the body.

Abstract

In this educational post, I share a clear, first-person journey through modern, evidence-based strategies that leverage SGLT2 inhibitors for cardio-renal protection in patients with diabetes and metabolic syndrome. We will explore the intricate connections between Type 2 Diabetes, Chronic Kidney Disease (CKD), and Cardiovascular Disease, and I will guide you through a detailed case study that showcases a modern, holistic approach to treatment. Drawing from my clinical observations and our multidisciplinary practice in El Paso, Texas, I explain how we integrate chiropractic care, internal medicine oversight, functional medicine, rehabilitation, and personal injury care to optimize outcomes. I also introduce our team structure, in which Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine (NPI #1164426749, Texas MD License #J2933), serves as Medical Director and Collaborative Physician at Injury Medical Clinic PA, alongside my role as a Doctor of Chiropractic and an advanced practice registered nurse. This post offers an accessible, step-by-step narrative with clinically relevant physiology, treatment rationales, and actionable protocols to support whole-person cardio-renal health.

My Path Toward Cardio-Renal Integration in Diabetes Care

I am Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST. Over the years, my clinical practice has focused on the intersection of metabolic health, musculoskeletal function, and neurophysiology—an integrative space where biochemical and biomechanical pathways meet. Early in my journey, a personal encounter with a loved one’s complications from diabetes impressed upon me how seemingly small choices—nutrition, movement, adherence, and foot care—can transform outcomes. Later, my formal training and work in functional medicine and advanced chiropractic biomechanics refined my approach to combine precise manual therapies, exercise rehabilitation, and medically supervised pharmacologic strategies.

Today, I use modern research on SGLT2 inhibitors to enhance cardio-renal outcomes. At the same time, our clinic’s multidisciplinary model ensures that each intervention is medically appropriate, safely combined, and tailored to the patient’s unique physiology. Our work is about reducing risk, restoring function, and improving quality of life.

Our Integrative Practice Model: A Symphony of Care

At Injury Medical Clinic PA (also known as Mission Plaza Injury Medical Clinic) in El Paso, Texas, we have cultivated a unique environment where different disciplines work in concert for the patient’s total well-being. This multidisciplinary setup is typical of progressive integrative and injury-care clinics.

  • Medical Management: Our practice is guided by the extensive medical expertise of Dr. Maria Guadalupe Cardenas, MD. Dr. Cardenas is a board-certified internist with an impressive 40-year career. As our Medical Director and Collaborative Physician, she provides essential medical oversight of our patients’ complex conditions, including prescribing and managing medications.
  • Chiropractic and Functional Medicine: I, Dr. Alex Jimenez, lead our team with a focus on chiropractic and functional medicine, addressing the body’s structural integrity, biomechanics, and underlying physiological imbalances. This approach is powerful for managing musculoskeletal complications, improving mobility, and reducing pain.
  • Comprehensive Services: This collaborative model allows us to offer a full spectrum of services under one roof, including functional medicine, personal injury care, rehabilitation, neuromuscular re-education, and lifestyle medicine.

This synergy ensures that a patient with diabetes receives not only state-of-the-art medical treatment for their blood sugar and organ protection, but also chiropractic adjustments to improve nervous system function, nutritional counseling to overhaul their diet, and physical rehabilitation to help them move again. It’s a 360-degree approach to health that treats the person, not just the disease.

A Patient’s Journey: From Uncontrolled Diabetes to Renewed Health

Let me introduce you to a patient we’ll call R.B., a case that perfectly illustrates the challenges and opportunities in modern diabetes care. When R.B. first came to our clinic, he was a 73-year-old Hispanic male with a 12-year history of type 2 diabetes, hypertension, and hyperlipidemia, and he was struggling despite being on several medications.

Patient Profile & Medications:

  • Metformin 1000 mg BID
  • Glipizide 10 mg BID with meals
  • Linagliptin (Tradjenta) 5 mg daily: A new DPP-4 inhibitor started shortly before his visit.
  • Losartan 100 mg daily: For hypertension.
  • Hydrochlorothiazide 25 mg daily: A diuretic for blood pressure.
  • Simvastatin 40 mg daily: For high cholesterol.
  • Glargine (Lantus) Insulin: Recently reduced from 60 units to 42 units.

His lab work painted a concerning picture. His hemoglobin A1C was a staggering 10.2%. His kidney function was declining, with an estimated Glomerular Filtration Rate (eGFR) of 43 and a creatinine level of 1.5. Clinically, he was experiencing dangerously high blood sugars during the day (200-300 mg/dL) yet was waking up with nocturnal hypoglycemia.

This patient was referred to our endocrinology service after a recent hospitalization for hyperglycemia and acute kidney injury. For five years, he had been considered “stable”, but his A1C had never dropped below 8%. This is a critical point: stability at a poor baseline is not true control. He had the trifecta of risk factors that recent clinical trials have focused on:

  1. Type 2 Diabetes: With a high A1C of 10.2%.
  2. Increased Cardiovascular Risk: Due to co-existing hypertension and hyperlipidemia.
  3. Chronic Kidney Disease (CKD): Evidenced by his low eGFR of 43.

Treatment Plan Part 1: Building a Foundation Through Education and Trust

The first step was not to add more medications but to address foundational issues. The patient was glucotoxic—a state where high blood sugar impairs insulin secretion and increases insulin resistance.

Comprehensive Diabetes Self-Management Education (DSME)

We started with intensive education. I discovered R.B. didn’t understand what his medications did. His most significant barrier was a profound fear of low blood sugar. To avoid it, he would preemptively eat carbohydrates throughout the day, driving his blood sugars sky-high. His long-acting insulin would then cause his sugar to plummet at night.

To break this cycle, we made two immediate changes:

  • We stopped the glipizide, a sulfonylurea drug notorious for causing hypoglycemia.
  • We further decreased his Lantus (glargine) dose to prevent nighttime lows.

Overcoming Barriers to Technology

A major point of resistance was his refusal to use a Continuous Glucose Monitor (CGM). He was terrified of a “big needle” staying under his skin. I showed him a demo CGM device and the tiny, flexible filament—not a needle—that actually sits under the skin. His fear vanished. We applied a sample sensor and ordered his supplies.

Finally, I ordered a C-peptide level. I explained this test to patients using an analogy: “The C-peptide is the candy wrapper, and insulin is the candy. If I see a lot of wrappers in your blood, I know your body is still making its own candy.”

Cardio-Renal Pathophysiology Made Simple

To treat effectively, we must understand the intertwined physiology. I explain these concepts to patients using clear analogies:

  • When blood glucose is high, think of syrup or honey. It is sticky and viscous. Your heart has to pump harder to move that thickened fluid, increasing cardiac workload.
  • Prolonged exposure to high sugar is inflammatory. If you hold a candy against your cheek for an hour, the tissue feels irritated. Similarly, hyperglycemia stiffens vessel walls and damages the vascular endothelium, including in the kidneys and heart.

The physiology behind these analogies is complex:

  • Kidney-glucose dynamics: In hyperglycemia, the kidney’s proximal tubules upregulate SGLT2 transporters, reabsorbing more glucose and sodium. This maladaptive conservation sustains hyperglycemia and reduces sodium delivery to the macula densa, blunting tubuloglomerular feedback and driving glomerular hyperfiltration. Over time, this causes podocyte injury, mesangial expansion, and glomerulosclerosis.
  • Heart-kidney axis: Volume overload and neurohormonal activation (RAAS, SNS) perpetuate cardiac remodeling. Increased venous congestion impairs renal perfusion, further activating RAAS—a vicious cycle worsened by insulin resistance and endothelial dysfunction.
  • Inflammation and fibrosis: Chronic hyperglycemia and oxidative stress increase TGF-β, NF-κB, and AGE-RAGE signaling, promoting fibrosis in renal and cardiac tissue.
  • Autonomic balance: Sympathetic overdrive elevates heart rate and vascular tone, harming diastolic filling and renal microcirculation.

Cardiometabolic Risk *Causes & Effects*- Video


SGLT2 Inhibitors: How They Work and Why We Use Them

SGLT2 inhibitors (such as empagliflozin, dapagliflozin, canagliflozin, and ertugliflozin) reduce blood glucose by promoting glucose excretion in the urine. Their benefits extend far beyond glucose lowering.

Key mechanisms:

  • Renal tubular transport modulation: By blocking sodium-glucose co-transport in the proximal tubule, they increase natriuresis (sodium excretion) and osmotic diuresis (water excretion).
  • Restoration of tubuloglomerular feedback: More sodium delivery to the macula densa improves afferent arteriolar tone, reducing intraglomerular pressure and mitigating hyperfiltration.
  • Hemodynamic effects: Reduced preload and afterload benefit cardiac function, leading to fewer heart failure events.
  • Metabolic shifts: Mild ketogenesis, lower insulin levels, improved insulin sensitivity, and weight reduction collectively support metabolic health.

Why we integrate them:

  • Robust evidence demonstrates cardio-renal benefits independent of A1c.
  • They complement lifestyle and biomechanical interventions by reducing congestion, improving energy utilization, and lowering systemic inflammation.
  • They fit the functional medicine goal of addressing root contributors—hemodynamics, energy metabolism, and renal microvascular stress.

Treatment Plan Part 2: Two Weeks Later – Progress and Precision

Two weeks later, the results were encouraging: blood sugar levels averaged in the 180s, and nocturnal hypoglycemia was gone. The C-peptide test came back within the normal range, confirming his pancreas was still producing insulin.

With his glucotoxicity resolving, it was now safe to introduce a more advanced therapy. Based on his CKD and cardiovascular risk profile, the clear choice was an SGLT2 inhibitor. We started him on Dapagliflozin (Farxiga) 5 mg daily and reduced his glargine dose again.

Clinical Indications and Patient Selection

Our internal medicine oversight by Dr. Cardenas ensures evidence-based selection for SGLT2 inhibitors:

  • Type 2 diabetes with high cardiovascular risk or existing heart failure.
  • Chronic kidney disease, with or without diabetes, particularly albuminuric CKD.
  • Heart failure across ejection fraction phenotypes (HFrEF and HFpEF), per modern trials.

We assess baseline eGFR, albumin-to-creatinine ratio, blood pressure, volume status, and existing medications, such as diuretics and RAAS inhibitors, to anticipate risks.

Safety and Monitoring Protocols

Under Dr.Cardenas’ss medical direction, we implement strict monitoring:

  • Renal function: Expect a modest, temporary dip in eGFR initially; monitor for stabilization.
  • Volume status: Monitor for dizziness or hypotension; adjust diuretics as needed.
  • Genitourinary infections: Counsel on hygiene; monitor for mycotic infections.
  • Euglycemic ketoacidosis: Rare; educate on sick-day rules, hydration, and carb intake.
  • Foot care: Double down on peripheral vascular assessments and neuropathy screening.

Treatment Plan Part 3: Three Months – Remarkable Improvement

Three months after his initial visit, the transformation was undeniable.

  • A1C: Dropped from 10.2% to 8.2%.
  • Creatinine: Improved from 1.54 to 1.3.
  • eGFR: Increased from 43 to 53.

His kidney function was actively improving! I explained it to him like this: “Remember when I told you high blood sugar makes your blood thick and sticky, like syrup? It forces your kidneys to work overtime. Now that your sugars are better, your blood flows more easily, and your kidneys can filter more efficiently.”

We also switched him from linagliptin to semaglutide (Ozempic) 0.5 mg weekly. Semaglutide is a GLP-1 receptor agonist that not only improves blood sugar control but also promotes weight loss and provides robust cardiovascular protection.

Integrative Chiropractic Care and Rehabilitation

Chiropractic care is not an add-on—it is integral to our approach.

  • Autonomic modulation: Dysautonomia in diabetes and heart failure fuels sympathetic dominance. Targeted spinal adjustments and vagal-stimulating breathwork can enhance HRV, reduce resting sympathetic tone, and improve baroreflex sensitivity. This aids renal perfusion and cardiac efficiency.
  • Thoracic mobility and respiration: Restricted rib and thoracic spine motion compromises ventilation and venous return. Mobilization improves diaphragmatic excursion, reduces intrathoracic pressures, and supports cardiac filling, synergizing with the preload reduction from SGLT2 inhibitors.
  • Gait mechanics and peripheral circulation: Foot and ankle alignment influence plantar pressure and ulcer risk. We correct biomechanical imbalances and prescribe footwear or orthotics.
  • Rehabilitation for Capacity Building: Our graded rehabilitation protocols restore functional capacity. Improved skeletal muscle mass enhances glucose uptake (GLUT4-mediated), reduces insulin resistance, and supports cardiac output by improving peripheral oxygen utilization.

From my clinical observations, integrating musculoskeletal optimization with metabolic therapies improves adherence and functional outcomes. Patients who receive targeted manual therapy and movement training are more likely to sustain walking programs, which lower A1C, reduce blood pressure, and enhance heart rate variability.

Treatment Plan Part 4: Seven Months – Approaching Full Remission

Seven months from his first visit, R.B. was a new person.

  • Blood Sugar Average: Now 150 mg/dL, with no lows.
  • A1C: Further improved to 7.2%, a 3-point drop!
  • Creatinine: Now 1.25, within the normal range.
  • eGFR: Stabilized at an improved 55.

Most remarkably, he was achieving this without needing mealtime insulin. The combination of Dapagliflozin and Semaglutide was working so effectively that his body’s own insulin, paired with better lifestyle choices, was enough. We officially stopped his prandial lispro.

Why This Matters: From Risk Reduction to Life Quality

This case highlights a new paradigm for diabetes care. We must stop fixating on A1C alone and consider the non-glycemic benefits of medications. By combining SGLT2 inhibitors with integrative chiropractic care, functional medicine, and rehabilitation, we address the mechanisms that drive heart and kidney decline while restoring movement, autonomy, and resilience. The evidence is strong, the physiology compelling, and the patient stories motivating. With cohesive medical oversight from Dr. Maria Guadalupe Cardenas, MD, and a unified clinical team, our approach is safe, rigorous, and deeply human.

Key Takeaways

  • SGLT2 inhibitors provide robust cardio-renal benefits through hemodynamic, metabolic, and microvascular mechanisms.
  • Integrative chiropractic care enhances autonomic balance, respiration mechanics, and peripheral circulation, synergizing with pharmacotherapy.
  • Medical oversight by Dr. Maria Guadalupe Cardenas, MD ensures safety, appropriate selection, and precise monitoring.
  • Functional medicine and rehabilitation embed behavior change and strengthen physiology for lasting outcomes.
  • Multidisciplinary coordination delivers comprehensive, patient-centered cardio-renal care.

References

Additional Clinical Observations


SEO tags: SGLT2 inhibitors, cardio-renal benefits, chronic kidney disease, heart failure, type 2 diabetes, integrative chiropractic care, functional medicine, internal medicine oversight, Dr. Alex Jimenez, Dr. Maria Guadalupe Cardenas, El Paso clinic, diabetes management, rehabilitation, autonomic balance, thoracic mobility, microvascular health, GLP-1 agonists, A1C, eGFR, hypoglycemia, Ozempic, Farxiga, patient education, holistic healthcare, cardio-renal protection, empagliflozin, dapagliflozin, canagliflozin, ertugliflozin, ADA guidelines, AACE guidelines, albuminuria, RAAS system, euglycemic DKA, personal injury care, Mission Plaza Injury Medical Clinic

Cardiometabolic Research Advances Using GLP-1 Receptor Therapy


Find out about GLP-1 receptor therapy on cardiometabolic health and its revolutionary role in modern medicine and patient care.

Abstract

Hello, I’m Dr. Alex Jimenez, and I am honored to share transformative insights into managing cardiovascular and metabolic conditions, such as type 2 diabetes. This educational post explores a significant shift in our medical understanding, moving from a purely glucose-centric model to a comprehensive, risk-reduction strategy. Here, we will journey through the latest findings from leading researchers, backed by robust, evidence-based studies, to understand this new paradigm. We’ll delve into the mechanisms of two groundbreaking classes of medications—SGLT2 inhibitors and GLP-1 receptor agonists—and their profound benefits for cardiovascular and renal health, often independent of their glucose-lowering effects. We will also discuss how our multidisciplinary team at Injury Medical Clinic PA, including the invaluable medical direction of Dr. Maria Guadalupe Cardenas, MD, integrates these advancements with integrative chiropractic care, functional medicine, and rehabilitation to provide a truly holistic treatment plan for our patients in El Paso, Texas. This post aims to illuminate the interconnectedness of cardiac, metabolic, and kidney health and present a collaborative path forward for optimal patient outcomes.

Our Collaborative and Integrative Practice at Injury Medical Clinic PA

Before we delve into the clinical science, I want to take a moment to explain our unique approach to patient care here in El Paso, Texas. At Injury Medical Clinic PA, also known as Mission Plaza Injury Medical Clinic, we have built a truly multidisciplinary practice. I am Dr. Alex Jimenez, and my credentials include DC, APRN, FNP-BC, CFMP, IFMCP, ATN, and CCST. My passion lies in functional medicine and chiropractic care, focusing on the body’s innate ability to heal and the musculoskeletal system’s foundational role in overall health.
A cornerstone of this model is my collaboration with Dr. Maria Guadalupe Cardenas, MD. With over 40 years of experience as a board-certified internist, Dr. Cardenas serves as our Medical Director and Collaborative Physician (NPI #1164426749, Texas MD License #J2933). Her extensive expertise in internal medicine provides essential medical oversight and direction, allowing us to seamlessly merge advanced medical protocols with chiropractic, functional medicine, rehabilitation, and personal injury care.
Our model is built on the synergy between different disciplines:

  • Medical Oversight (Dr. Cardenas): Provides diagnoses, prescribes medications like the advanced therapies we will discuss today, and oversees the overall medical treatment plan, ensuring patient safety and efficacy.
  • Chiropractic and Functional Medicine (Dr. Jimenez): I focus on identifying and addressing the root causes of dysfunction. Through chiropractic adjustments, we restore proper nerve function and biomechanics. With functional medicine, we analyze a patient’s genetics, lifestyle, and environment to correct underlying imbalances in metabolism, inflammation, and gut health.
  • Integrated Services: Together, we manage personal injury cases, rehabilitation, nutritional counseling, and chronic disease management. This team-based approach ensures that a patient with diabetes, for example, not only receives the latest medications but also benefits from dietary overhauls, targeted supplementation, and structural care to improve insulin sensitivity and reduce systemic inflammation. This is the essence of integrative medicine—uniting the best of multiple worlds for superior patient outcomes.

The Critical Link Between Diabetes and Cardiovascular Disease

For a long time, the primary focus in managing type 2 diabetes was on lowering blood glucose. While important, this approach was incomplete. We now have an overwhelming body of evidence showing that people with diabetes face a significantly elevated risk for Atherosclerotic Cardiovascular Disease (ASCVD), which includes coronary heart disease, stroke, and peripheral arterial disease. In fact, ASCVD is the leading cause of death for individuals with diabetes.

  • Consider this startling fact: over 70% of individuals with diabetes over the age of 65 will likely succumb to heart disease or a stroke.
  • Following a heart attack (myocardial infarction or MI), people with diabetes have a much higher mortality risk and a poorer long-term prognosis.
  • These grim outcomes persist even when blood sugar levels are well-controlled, and they affect individuals with both type 1 and type 2 diabetes.

This reality has forced a paradigm shift in how we manage these interconnected conditions. The focus has expanded from aggressive glucose reduction to a holistic strategy to reduce overall cardiovascular and renal risk. This involves managing not just blood sugar, but also blood pressure, cholesterol levels, weight, physical activity, and smoking cessation. For the first time in my career, all the major guideline-issuing bodies—including the American College of Cardiology (ACC), the American Heart Association (AHA), the American Diabetes Association (ADA), and the Kidney Disease: Improving Global Outcomes (KDIGO)—are in complete agreement on this new, integrated approach to care. This consensus marks a monumental step forward, allowing us to view and treat our patients through a unified, comprehensive lens.

Rethinking Treatment Algorithms: A Risk-Based Approach

This new paradigm is reflected in the latest treatment algorithms from the American Diabetes Association. The guidelines now emphasize a risk-stratified approach. For any patient with type 2 diabetes who has established ASCVD, heart failure, chronic kidney disease (CKD), or is at high risk for developing these conditions, the recommendation is to concurrently address all risk factors and prioritize specific classes of medications.
The algorithm directs us to move beyond traditional first-line agents like metformin alone and immediately consider two powerful classes of drugs:

  1. SGLT2 (Sodium-Glucose Cotransporter-2) Inhibitors
  2. GLP-1 (Glucagon-Like Peptide-1) Receptor Agonists

These medications are now recommended as foundational therapies for high-risk patients precisely because they have demonstrated proven cardiovascular (CV) benefits in large-scale clinical trials. The choice between them, or the decision to use them in combination, depends on patient-specific factors, comorbidities, and preferences. This marks a significant departure from simply trying to lower the A1C; it’s about proactively protecting the heart and kidneys.

The History and Evolution of Diabetes Medication Trials

How did we arrive at this pivotal moment? The story begins around 2008, when the U.S. Food and Drug Administration (FDA) issued mandatory guidance for all new antidiabetic medications. The FDA required pharmaceutical companies to conduct long-term Cardiovascular Outcomes Trials (CVOTs). The primary goal was to ensure that these new drugs did not increase the risk of Major Adverse Cardiovascular Events (MACE)—a composite of non-fatal heart attack, non-fatal stroke, and cardiovascular death.
This mandate was a direct response to past experiences where certain drugs, such as rosiglitazone (Avandia) and others like Vioxx, were later found to cause cardiovascular harm. Earlier studies were often too short, underpowered, or poorly designed to detect these risks. The FDA’s new requirement forced the industry to conduct large, well-designed, placebo-controlled trials that were robust enough to demonstrate safety or non-inferiority.
What happened next was truly surprising. As the results of these CVOTs began to be published, starting with the EMPA-REG OUTCOME trial for empagliflozin (Jardiance) in 2015, researchers discovered something extraordinary. These new drugs weren’t just safe—some of them were actively protective.

  • Empagliflozin (Jardiance), an SGLT2 inhibitor, was the first to show a significant reduction in MACE, CV death, and hospitalization for heart failure.
  • Liraglutide (Victoza), a GLP-1 receptor agonist, followed in 2016 with the LEADER trial, also demonstrating significant cardiovascular benefits.

These unexpected findings of superiority, not just safety, were game-changers. They provided the evidence needed to completely overhaul the clinical guidelines and place these drug classes at the forefront of managing patients with cardiovascular, metabolic, and renal disease.

A Deeper Dive into SGLT2 Inhibitors

Let’s explore the SGLT2 inhibitor class more closely. These medications work by blocking glucose reabsorption in the kidney, causing excess sugar to be excreted in the urine. While this helps lower blood glucose, their profound cardiovascular and renal benefits appear to stem from multiple other mechanisms.

Landmark Cardiovascular Outcomes Trials for SGLT2 Inhibitors

Several major CVOTs have established the benefits of this class:

  • EMPA-REG OUTCOME (empagliflozin/Jardiance): This trial was a watershed moment. It showed a highly statistically significant reduction in MACE, CV death, and hospitalization for heart failure.
  • CANVAS Program (canagliflozin/Invokana): Demonstrated significant reductions in MACE and hospitalization for heart failure.
  • DECLARE-TIMI 58 (dapagliflozin/Farxiga): While it didn’t show a significant reduction in MACE, it showed a substantial and statistically significant reduction in the risk of hospitalization for heart failure.
  • VERTIS-CV (ertugliflozin/Steglatro): Also showed a significant reduction in hospitalization for heart failure risk (a 30% relative risk reduction).

The consistent and powerful effect on reducing hospitalizations for heart failure across the class is particularly noteworthy and has led to their widespread adoption in cardiology.

The Multifaceted Mechanisms of SGLT2 Inhibitors

What makes these drugs so effective? The benefits go far beyond simple glucose lowering. Some of the proposed mechanisms that contribute to their cardioprotective and renoprotective effects:

  • Hemodynamic Effects: SGLT2 inhibitors have a mild diuretic effect, which helps reduce blood pressure by about 3-5 mmHg systolic. This is achieved through natriuresis, or the excretion of sodium and water, which reduces fluid volume and preload on the heart.
  • Reduced Glomerular Pressure: In the kidneys, these drugs reduce pressure within the glomerulus (the kidney’s filtering unit). This is a key theorized mechanism for their nephroprotective (kidney-protecting) effects, slowing the progression of diabetic kidney disease.
  • Metabolic Shifts: SGLT2 inhibitors promote a slight shift towards ketosis. The heart is a unique metabolic organ that can efficiently use ketones as a fuel source. This “super fuel” improves myocardial efficiency and function, especially in a stressed or failing heart.
  • Systemic Benefits: They also contribute to a modest weight loss (around 5-7 pounds), reduce inflammation, decrease oxidative stress, and may improve endothelial function and stabilize atherosclerotic plaques.
  • Improved Myocardial Energetics: By reducing the workload on the heart (via lower blood pressure and volume) and providing a more efficient fuel source (ketones), these drugs improve the overall energy balance and function of the heart muscle.

SGLT2 Inhibitors in Heart Failure and Kidney Disease

The benefits of SGLT2 inhibitors have been so profound that their use has expanded to patients without diabetes.

Heart Failure Trials

  • DAPA-HF and EMPEROR-Reduced: These trials studied dapagliflozin and empagliflozin, respectively, in patients with heart failure with reduced ejection fraction (HFrEF). Both showed a remarkable 25-26% relative risk reduction in the composite outcome of cardiovascular death or hospitalization for heart failure, regardless of whether the patients had diabetes.
  • EMPEROR-Preserved: This was the first trial to show a meaningful benefit in patients with heart failure with preserved ejection fraction (HFpEF), a very common and difficult-to-treat type of heart failure, particularly in older adults, women, and those with obesity. Empagliflozin reduced the primary composite endpoint by 21%.

Kidney Disease Trials

The evidence for kidney protection is just as compelling:

  • DAPA-CKD (dapagliflozin): This trial was stopped early due to overwhelming efficacy. It showed a 39% reduction in the risk of progression of kidney disease.
  • EMPA-KIDNEY (empagliflozin): Also demonstrated a significant 28% reduction in the risk of kidney disease progression or cardiovascular death.
  • CREDENCE (canagliflozin): Showcased a 30% reduction in the risk of kidney failure and cardiovascular events in patients with type 2 diabetes and kidney disease.

These trials have firmly established SGLT2 inhibitors as a cornerstone therapy for chronic kidney disease, even in patients without diabetes.

Understanding the Incretin Effect: TheBody’ss Natural Glucose Response System

For years, the management of type 2 diabetes centered on a few key strategies. However, a fascinating discovery completely shifted our understanding and opened the door to a new class of powerful therapies. Researchers observed a peculiar phenomenon: when people consumed glucose orally (by drinking it), their bodies produced a much more robust insulin response to lower blood sugar than when the same amount of glucose was administered intravenously (IV). This observation led them to a logical conclusion: there must be something happening in the gut when food is ingested that signals the pancreas to ramp up insulin production.
This phenomenon was termed the “incretin effect.” The “somethings” responsible were identified as gut hormones called incretins, primarily glucagon-like peptide-1 (GLP-1) and glucose-dependent insulinotropic polypeptide (GIP).

  • The Process: When you eat, food travels to your stomach and intestines. Specialized cells in your gut (L-cells) detect the presence of nutrients and release GLP-1 and GIP into your bloodstream.
  • The Signal: These hormones then travel to the pancreas, where they act as messengers. They bind to receptors on pancreatic beta cells, stimulating the cells to release insulin.
  • The Result: This insulin release helps your body’s cells take up glucose, effectively lowering your blood sugar levels after a meal.

Crucially, this entire process is glucose-dependent. This means the incretins only stimulate insulin release when blood sugar levels are high, as they are after a meal. This built-in safety mechanism significantly reduces the risk of hypoglycemia (dangerously low blood sugar) when these pathways are targeted with medication, especially compared to older diabetes drugs.

The Blunted Incretin Effect in Type 2 Diabetes

One of the key physiological defects we see in patients with type 2 diabetes is a blunted or even absent incretin effect. Their bodies produce insufficient amounts of native GLP-1 in response to food. This deficiency contributes significantly to the hallmarks of the disease:

  • Poor Post-Meal Glucose Control: Without a strong incretin signal, the pancreas doesn’t release sufficient insulin after eating, resulting in prolonged periods of high blood sugar.
  • Dysregulated Appetite: Native GLP-1 also plays a critical role in promoting satiety, or the feeling of fullness. Low levels of this hormone can lead to a state of poor satiety, contributing to overeating and the obesity that is so often a comorbid condition with type 2 diabetes.
  • Excess Glucagon Secretion: GLP-1 normally helps suppress the release of another hormone called glucagon. Glucagon tells the liver to produce and release more sugar into the bloodstream (gluconeogenesis). In type 2 diabetes, this suppression is impaired, so the liver continues to release glucose even when blood glucose is already high.

Understanding this hormonal defect was the key that unlocked the development of GLP-1 receptor agonists—medications designed to mimic the action of our natural GLP-1 and restore these vital functions.

The Silent Threat: Hyperhomocysteinemia and its Impact on Your Health- Video

How GLP-1 Receptor Agonists Revolutionize Treatment

GLP-1 receptor agonists are a class of medications that bind to and activate GLP-1 receptors throughout the body, just as our native GLP-1 would, but they are engineered to last much longer. Their multifaceted mechanism of action addresses several core issues in type 2 diabetes and obesity simultaneously.

  • Stimulates Insulin Secretion: By activating pancreatic receptors, they prompt a glucose-dependent release of insulin, directly lowering blood sugar.
  • Inhibits Glucagon Secretion: They effectively tell the liver to stop producing excess sugar, which is a major contributor to high fasting and post-meal glucose levels.
  • Slows Gastric Emptying: This is a key mechanism for both glucose control and weight loss. By slowing down the rate at which food leaves the stomach, they prevent rapid spikes in blood sugar after meals. This delay also contributes to a prolonged feeling of fullness, which naturally leads to a decrease in overall food intake. This effect is often responsible for the common initial side effects like nausea, but it is also a primary driver of the medication’s success.
  • Increases Satiety: GLP-1 receptor agonists act directly on appetite centers in the brain, enhancing the feeling of fullness and reducing food cravings. This neurobiological effect is fundamental to the significant weight loss seen with these therapies.

Collectively, these actions lead to profound improvements in A1c, blood glucose, and body weight, tackling the metabolic dysfunction of type 2 diabetes at its source.

The Challenge of Over-Basalization: A Case Study

To truly understand the paradigm shift in diabetes care,let’ss consider a typical patient I might see in our clinic, whom we’ll call Tony. He represents a common challenge where adding a GLP-1 agonist is the superior strategy.

  • Patient Profile: Tony
  • Age: 62 years
  • Diagnosis: Type 2 Diabetes (11 years), Hyperlipidemia, Hypertension
  • Recent A1c: 8.2% (well above the target of <7.0%)
  • Kidney Health: Proteinuria (protein in the urine), an early sign of kidney damage.
  • Current Medications:
    • Degludec (basal insulin): 65 units daily
    • Metformin: 1000 mg twice daily
    • An SGLT2 inhibitor daily
    • A statin for cholesterol
  • An ARB for blood pressure
  • Physical Stats: Weight 220 lbs, Height 5’9 ” “, BMI 32.5 (classifies as obese)
  • Blood Sugar Patterns:
    • Fasting Glucose (morning): 15050 mg/dL
    • Postprandial Glucose (after meals/bedtime): 160-200 mg/dL

Tony’s case highlights a critical issue we call over-basalization. We’ve pushed his basal (long-acting) insulin dose to a high level, yet his A1c and post-meal sugars remain dangerously elevated. Research in pharmacokinetics reveals that once you exceed a certain dose of basal insulin, typically around 0.5 units per kilogram of body weight per day, you get diminishing returns. For Tony, who weighs 100 kg (220 lbs), this threshold is about 50 units. He is already on 65 units, pushing him past the point of modest glycemic effect and into the territory of significant side effects, primarily weight gain and a higher risk of hypoglycemia.
For a patient like Tony, the conventional next step might have been to add prandial (mealtime) insulin. While this can control post-meal spikes, it comes with a heavy price: a near-certainty of further weight gain and a significantly increased risk of hypoglycemia. Given his BMI of 32.5, adding more weight would only worsen his insulin resistance, creating a vicious cycle.
This is where the 2024 guidelines from the American Diabetes Association (ADA) strongly recommend adding a GLP-1 receptor agonist. It addresses multiple problems at once, moving beyond simple glucose lowering, weight loss, and cardiovascular protection, which are crucial for a high-risk patient like Tony.

Beyond Blood Sugar: The Cardiovascular and Renal Benefits of GLP-1s

Perhaps the most exciting development in the story of GLP-1 agonists is the overwhelming evidence of their protective effects on the heart and kidneys. Several landmark trials have established these powerful benefits:

  • The LEADER Trial (Liraglutide): This trial studied patients with type 2 diabetes and high cardiovascular risk. It showed a significant reduction in the risk of major adverse cardiovascular events (MACE), including cardiovascular death, non-fatal heart attack, and non-fatal stroke.
  • The SUSTAIN-6 and PIONEER 6 Trials (Semaglutide): Both the injectable (SUSTAIN-6) and oral (PIONEER 6) forms of semaglutide were studied in patients with high cardiovascular risk. Both trials demonstrated a robust reduction in MACE, confirming the class effect.
  • The REWIND Trial (Dulaglutide): What made this trial unique was its focus on a broader population, including many patients who had risk factors for cardiovascular disease but had not yet had an event. It demonstrated that dulaglutide can be used for primary prevention, reducing the risk of a first cardiovascular event.
  • Tirzepatide (Mounjaro®, Zepbound™): This is a newer, highly potent dual GIP/GLP-1 receptor agonist. While its final CVOTs are still pending as of June 15, 2026, preliminary data suggest powerful cardiovascular benefits are likely.

More recently, the FLOW trial for semaglutide was stopped early because of overwhelmingly positive results showing a significant reduction in the risk of kidney disease progression (nephropathy). These findings are game-changers, solidifying the role of GLP-1 agonists as essential therapies for patients with or at high risk for heart and kidney disease.

Navigating Side Effects and Safety Considerations of GLP-1 Agonists

As with any potent medication, GLP-1 agonists are not without side effects. As clinicians, our job is to help patients navigate these challenges.

  • Gastrointestinal (GI) Issues: Nausea, vomiting, and diarrhea are common and caused by delayed gastric emptying. My clinical advice is always to “start low and go slow,” beginning with the lowest dose and titrating upwards gradually.
  • Dehydration and Acute Kidney Injury (AKI): Patients on these medications must drink plenty of water to prevent dehydration due to GI side effects.
  • Gallbladder Disease: Rapid weight loss, regardless of the method, is associated with an increased risk of gallstone formation.
  • Pancreatitis: Recent large-scale studies as of early 2025 have been reassuring, finding no statistically significant increase in the risk of pancreatitis and even suggesting a potential long-term risk reduction by improving metabolic health.
  • Thyroid C-Cell Tumors: These medications carry a black box warning due to an increased risk of thyroid C-cell tumors in rodents. They are contraindicated in patients with a personal or family history of medullary thyroid carcinoma (MTC) or Multiple Endocrine Neoplasia syndrome type 2 (MEN 2).
  • Muscle and Bone Loss: This is a feature of significant weight loss in general, not something specific to these drugs. This is where our integrative care becomes critical.

An Integrative Chiropractic Perspective on Metabolic Health

As a Doctor of Chiropractic with advanced training in functional medicine, I view the body as an integrated system. When I see a patient, I don’t just see a person with diabetes and heart disease. I see a complex interplay of systemic inflammation, metabolic dysfunction, and biomechanical stress. This is where our unique approach at Injury Medical Clinic PA provides immense value. The side effects and physiological changes associated with modern diabetes therapies are whole-body issues we can address.
Here’s how integrative chiropractic care fits into this new paradigm:

  1. Addressing Systemic Inflammation: Chronic inflammation is a root cause of both ASCVD and insulin resistance. Chiropractic adjustments have been shown to modulate the nervous system and can have a downstream effect on inflammatory pathways. By reducing spinal misalignments (subluxations), we can help normalize nerve function, which in turn influences the body’s inflammatory response.
  2. Promoting Physical Activity and Combating Muscle Loss: Exercise is a critical component of managing diabetes. However, many patients are limited by musculoskeletal pain. As chiropractors, our primary role is to improve biomechanical function, reduce pain, and restore mobility. Furthermore, with the rapid weight loss induced by GLP-1s, there is a risk of sarcopenia (muscle loss). We implement targeted strength training and rehabilitation protocols to preserve and build lean muscle mass. By treating underlying musculoskeletal issues, we empower patients to engage in the physical activity necessary for their metabolic health.
  3. Functional Medicine and Nutritional Counseling: My training as a Certified Functional Medicine Practitioner (CFMP) allows us to go deeper. We create personalized nutrition plans and recommend targeted supplementation to reduce inflammation, improve insulin sensitivity, and support cardiovascular health. To combat muscle loss, we ensure patients consume adequate protein to support muscle synthesis. This complements the work of medications by addressing the foundational lifestyle factors that drive disease.
  4. Stress Management and Autonomic Balance: The autonomic nervous system plays a huge role in regulating blood pressure, heart rate, and metabolic function. Chronic stress leads to a state of sympathetic (“fight-or-flight”) dominance, which can worsen hypertension and insulin resistance. Chiropractic care, along with techniques like breathwork and meditation, helps promote a parasympathetic (“rest-and-digest”) state, supporting better cardiovascular and metabolic regulation.

In our clinic, a patient would receive a comprehensive plan. Under the medical direction of Dr. Cardenas, they might be started on an SGLT2 inhibitor or a GLP-1 agonist. Simultaneously, my team would work with them on a personalized plan including chiropractic adjustments to improve mobility, an anti-inflammatory diet, and a progressive exercise program they can perform without pain. This integrated approach addresses the disease from multiple angles, leading to far better and more sustainable outcomes. This is the future of chronic disease management—a holistic, patient-centered, and team-based model of care.

References

SEO Tags: SGLT2 inhibitors, GLP-1 receptor agonists, cardiovascular disease, type 2 diabetes, chronic kidney disease, heart failure, integrative chiropractic care, functional medicine, Dr. Alex Jimenez, Dr. Maria Cardenas, El Paso, TX, ASCVD, risk reduction, metabolic health, incretin effect, over-basalization, tirzepatide, semaglutide, Mounjaro, Ozempic, diabetes management, A1c reduction, weight loss and diabetes, nephroprotection, cardioprotection, collaborative care, internal medicine, chiropractic, personal injury care, musculoskeletal health

Integrative Care for Improved Health from Cardiorenal Syndrome


Understand the principles of integrative care for cardiorenal syndrome and its impact on patient wellness and recovery.

Abstract

I am Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST. In this educational post, I guide you through a clear, evidence-based understanding of the heart–kidney relationship known as cardiorenal syndrome. We will explore how decreased cardiac output, increased preload, and chronic neurohormonal activation—especially the renin–angiotensin–aldosterone system (RAAS) and sympathetic nervous system (SNS)—drive congestion, inflammation, and progressive organ dysfunction. I discuss why venous congestion and right ventricular (RV) mechanics are pivotal, what natriuretic peptides signal, and how splanchnic venous reservoir dynamics and renal tubular injury shape decisions.
You will also see how our multidisciplinary team at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso, Texas integrates chiropractic care, functional medicine, personal injury care, rehabilitation, and medical oversight to deliver safe, modern cardiorenal care. Our Medical Director and Collaborative Physician, Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI #1164426749; Texas MD License #J2933), provides medical direction as I implement integrative chiropractic and functional strategies. I present practical frameworks for loop diuretic regimens, sequential nephron blockade, guideline-directed medical therapy (GDMT), and when to consider inotropes, ultrafiltration, or mechanical circulatory support. Throughout, I explain how integrative chiropractic fits—via thoracic and diaphragmatic mechanics, autonomic modulation, and postural optimization—to complement medical therapy.

Integrative Cardiorenal Care in El Paso: Our Collaborative Model

Practice within a multidisciplinary structure common to modern integrative and injury care clinics. At Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic), I work alongside Dr. Maria Guadalupe Cardenas, MD, our Medical Director and Collaborative Physician, who is board-certified in Internal Medicine with over 40 years of experience (NPI #1164426749; Texas MD License #J2933). Dr. Cardenas provides comprehensive medical oversight, directing our cardiometabolic and internal medicine pathways and ensuring our care aligns with current standards and safety protocols.
My integrated role combines:

  • Chiropractic and rehabilitative biomechanics to improve mobility, breathing mechanics, and venous return
  • Autonomic and pain modulation techniques to temper sympathetic drive
  • Functional medicine frameworks for inflammation, nutrition, and mitochondrial health
  • Personal injury care and graded rehabilitation for safe return to function
  • Close medical coordination for diagnostics, pharmacology, and escalation pathways

This coordinated model allows us to deliver evidence-based care for complex syndromes like cardiorenal syndrome, chronic kidney disease (CKD), and heart failure, while integrating spine-focused biomechanics and lifestyle interventions under medical supervision.

The Cardiorenal Connection: Heart–Kidney Crosstalk

Cardiorenal syndrome describes the bidirectional relationship in which heart dysfunction worsens kidney injury and kidney dysfunction exacerbates heart failure. To act precisely, we must understand the crosstalk:

  • Natriuretic peptides (ANP, BNP/NT-proBNP, CNP): They promote vasodilation, natriuresis, and reduced preload, signaling the heart’s attempt to counter congestion.
  • RAAS: Renin, angiotensin II, and aldosterone drive vasoconstriction and sodium/water retention—powerful mechanisms that often dominate in chronic heart failure.
  • SNS activation: Increases heart rate and contractility to compensate for low stroke volume; chronically, it amplifies inflammation and oxidative stress.

Why this matters: Chronic low cardiac output and elevated filling pressures tip the endocrine tug-of-war toward RAAS dominance, promoting fluid retention, vascular stiffness, and fibrosis. Over time, this neurohormonal imbalance becomes maladaptive, feeding back into both cardiac and renal decline (American College of Cardiology, n.d.; American Heart Association, n.d.; European Society of Cardiology, n.d.).

Decreased Cardiac Output, Increased Preload, and Maladaptive Responses

Early in heart failure, two key changes dominate:

  • Decreased cardiac output from reduced stroke volume, adverse remodeling, and increased LV wall stress
  • Increased preload with elevated left atrial and central venous pressures

Compensatory responses:

  • RAAS activation stabilizes blood pressure but increases sodium and water retention
  • SNS activation maintains cardiac output (CO = HR × SV) but increases oxidative stress and inflammatory signaling

Short-term benefits can lead to long-term harm: persistent vasoconstriction strains the myocardium; aldosterone drives interstitial fibrosis in the heart and kidney; sustained SNS activity increases reactive oxygen species (ROS), worsening myocardial and tubulointerstitial injury (American College of Cardiology, n.d.; American Heart Association, n.d.).

Renal Pathophysiology: Tubular Injury, Fibrosis, and RAAS Amplification

At the nephron level, chronic inflammation and catecholamine exposure create:

  • Glomerular and interstitial damage leading to sclerosis
  • Renal tubular injury with vacuolization and reduced effective surface area, impairing natriuresis and diuresis
  • Apoptosis and fibrosis that diminish renal reserve
  • Local RAAS amplification from injured renal tissue, compounding systemic signals

Clinical implications:

  • Worsening CKD is both a consequence and driver of advanced heart failure
  • NT-proBNP rises as a counter-regulatory endocrine signal; yet in chronic disease, it is overwhelmed
  • Progressive dysfunction narrows the therapeutic windows for ACEi/ARBs/ARNIs, MRAs, SGLT2 inhibitors, and diuretics, thereby demanding careful dosing and monitoring (European Society of Cardiology, n.d.; Natriuretic peptides and heart failure outcomes, n.d.; RAAS inhibition and cardiorenal protection, n.d.).

Venous Congestion and the Splanchnic Reservoir: Abdominal Physiology in Focus

A frequently under-recognized driver is abdominal (splanchnic) congestion. The liver, spleen, omentum, and mesenteric vasculature form a large venous reservoir. In heart failure:

  • Fluid redistributes early to splanchnic beds, preceding peripheral edema
  • Elevated portal and mesenteric pressures impair gut perfusion and barrier function, contributing to intestinal edema, malabsorption, dysbiosis, and systemic inflammation.
  • Hepatic congestion elevates liver enzymes, lowers albumin, and alters drug metabolism—crucial for dosing loop diuretics and other GDMT agents.

Clinically, splanchnic congestion explains early satiety, bloating, nausea, RUQ discomfort, and variable diuretic responses. Effective care must reduce central venous pressure and consider RV dynamics, not just peripheral edema.

Right Ventricular Hemodynamics: The Hidden Driver of Renal Outcomes

The right ventricle (RV) primes venous return and pulmonary flow. Elevated RV afterload (e.g., pulmonary hypertension) or intrinsic RV dysfunction raises central venous pressure, compressing renal perfusion pressure (mean arterial pressure minus renal venous pressure). Even with preserved systemic BP, renal venous hypertension narrows the filtration gradient, impairing GFR and accelerating tubulointerstitial injury.
Therapeutic implications:

  • RV unloading through oxygenation, judicious pulmonary vasodilators, and careful fluid offloading can improve renal perfusion and diuretic responsiveness
  • Thoracic mobility, diaphragmatic mechanics, and postural optimization—core chiropractic strategies—support venous return and respiratory efficiency, synergizing with cardiology care

Forward Versus Backward Flow: A Modern Hemodynamic Framework

Four decades of hemodynamics reframed heart failure from contractility-centric to congestion-centric:

  • Forward flow is arterial delivery—cardiac output reaching organs
  • Backward flow is venous pressure burden—congestion impeding organ drainage

High venous pressures collapse the transglomerular filtration gradient. The kidney depends on strong arteriolar inflow against low venous outflow. When venous pressures rise, filtration falls—creating cardiorenal and veno-renal states. Effective therapy must preserve forward arterial perfusion while reducing venous congestion (Stevenson, 1999).

The Veno-Renal State: Why Decongestion Restores Filtration

Elevated renal vein pressure increases interstitial and capsular pressures, diminishing net filtration pressure. Renal congestion triggers inflammatory pathways, worsens tubular oxygen demand, and perpetuates sympathetic tone. Decongestion widens renal gradients, improves filtration, and reduces neurohormonal stress. This is why diuretics, volume redistribution, and venous pressure relief can yield renal recovery, even without dramatic increases in forward cardiac output.

Clinical Assessment: How We Characterize Congestion and Risk

Under Dr. Cardenas’s medical direction, we integrate physical exam and testing:

  • Jugular venous pressure (JVP) and hepatojugular reflux
  • Lung auscultation for rales and airflow changes
  • Hepatic size/tenderness, ascites signs, and abdominal wall tension
  • Peripheral edema grading
  • Bioimpedance and segmental composition when available
  • Functional measures: orthopnea, bendopnea, exercise tolerance, and heart rate recovery
  • BNP/NT-proBNP, CMP, urinalysis, albumin–creatinine ratio
  • Echocardiography for LV/RV function and pulmonary pressures
  • IVC ultrasound for collapsibility as a central venous pressure surrogate
  • POCUS for lung B-lines and portal flow; renal Doppler for resistive index when indicated

These findings guide diuretic regimens, fluid targets, and GDMT adjustments, defining whether pulmonary, splanchnic, or peripheral compartments dominate.

Beating the Odds: “Conquering Congestive Heart Failure”- Video

Diuretic Therapy: Thresholds, Ceilings, and Precision Offloading

Loop diuretics are cornerstone therapies for decongestion. Our approach emphasizes pharmacokinetics and physiology:

  • Agent selection:
    • Furosemide: Widely used; variable oral bioavailability; IV preferred in acute decompensation; SQ options in supervised settings
    • Torsemide: High, consistent bioavailability; favorable half-life; potential antifibrotic aldosterone-modulating effects; often preferred in gut edema
    • Bumetanide: Potent, reliable absorption; useful in intestinal edema or furosemide resistance
  • Dosing strategy:
    • Start weight-adjusted doses; escalate based on urine output targets (e.g., 150–200 mL/hour acutely) and daily weight trends
    • Sequential nephron blockade: Add thiazide-like diuretics (e.g., metolazone) or acetazolamide when resistance occurs
    • Consider IV or subcutaneous routes when oral absorption is limited
  • Safety checks:
    • Monitor electrolytes, renal function, blood pressure; anticipate hypokalemia, hyponatremia, metabolic alkalosis
    • Use IVC ultrasound and lung B-lines to avoid over-diuresis and renal hypoperfusion

Physiologic rationale: Targeting nephron segments reduces venous pressures, improves renal perfusion by lowering renal venous hypertension, and reduces splanchnic reservoir volume—improving symptoms and organ function (Felker et al., 2011; Mullens et al., 2022).

Managing Diuretic Resistance: Push vs Drip and Sequential Blockade

When resistance appears, we reassess dose, bioavailability, timing, and add-ons:

  • Bolus vs infusion: Adequate bolus dosing can be comparable to continuous infusion; continuous infusion may aid severe resistance by sustaining tubular drug levels (Felker et al., 2011)
  • Sequential nephron blockade:
    • Add a thiazide (e.g., metolazone) to increase distal blockade
    • Layer MRAs for neurohormonal modulation and sodium balance
    • Consider acetazolamide to augment proximal diuresis in alkalotic patients (Mullens et al., 2022)

Cardiorenal nuance: Patients often have higher thresholds due to renal venous congestion and interstitial edema; higher initial doses of loop diuretics may be required. A modest early rise in creatinine can reflect hemodynamic shifts rather than intrinsic injury—context matters.

Guideline-Directed Medical Therapy: Renal-Safe Sequencing

We tailor GDMT to renal function:

  • ACE inhibitors/ARBs/ARNI: Reduce afterload and RAAS activity; monitor creatinine and potassium, especially in CKD
  • Mineralocorticoid receptor antagonists (MRAs): Counter aldosterone-mediated fibrosis and retention; monitor for hyperkalemia
  • SGLT2 inhibitors: Provide osmotic diuresis, modulate tubuloglomerular feedback, and deliver cardio-renal protection; initiation feasible down to eGFR ≥20 mL/min/1.73 m² in many protocols
  • Beta-blockers: Temper SNS overactivation; we typically initiate after decongestion to avoid acute hemodynamic compromise

Why it works: GDMT attenuates maladaptive RAAS/SNS cascades, reduces fibrosis, improves hemodynamics, and stabilizes renal function when combined with congestion management and lifestyle support (Yancy et al., 2017; McDonagh et al., 2021; McMurray et al., 2019; Heerspink et al., 2020).

Inotropes and Escalation: Milrinone, Dobutamine, Ultrafiltration, and MCS

In refractory oliguria or low-output states:

  • Milrinone: PDE-3 inhibition improves calcium handling, reduces systemic and pulmonary vascular resistance, and unloads the RV—lowering venous pressures and improving renal gradients; renally cleared, so dose cautiously
  • Dobutamine: Beta-1 agonism increases contractility; beta-2 effects can vasodilate; monitor for tachyarrhythmias and ischemia; useful when faster augmentation of output is needed, including RV responsiveness

If diuretics fail:

  • Ultrafiltration/CRRT/hemodialysis: Remove fluid without RAAS activation associated with loops; decompress venous beds to restore renal output; modality choice depends on blood pressure and setting
  • Mechanical circulatory support (MCS):
    • Impella platforms for LV unloading; Impella RP for RV support
    • Protek Duo RVAD systems for right-sided failure
    • VA-ECMO for biventricular support and oxygenation

Early referral to advanced heart failure teams prevents prolonged renal congestion and organ compromise (McDonagh et al., 2021; Yancy et al., 2017).

Integrative Chiropractic Care: Mechanobiology Meets Hemodynamics

Chiropractic care must be thoughtfully integrated into cardiorenal frameworks to support mobility, autonomic balance, and venous return safely. My priorities include:

  • Thoracic spine mobility and rib cage mechanics: Enhancing diaphragmatic excursion improves the respiratory pump, supporting venous return and lymphatic drainage
  • Diaphragmatic training and myofascial release: Reducing abdominal wall tension aids interstitial fluid movement and improves GI motility affected by splanchnic congestion
  • Cervical and upper thoracic autonomic modulation: Gentle techniques that reduce sympathetic tone may improve heart rate variability and sleep quality
  • Postural optimization: Correcting kyphosis and forward head posture improves intrathoracic pressure dynamics and may reduce venous congestion in splanchnic and hepatic beds
  • Safe exercise prescription: Low-intensity, interval-based activity focusing on calf-muscle pump activation mobilizes peripheral venous blood without hemodynamic instability

Clinical guardrails:

  • Coordinate with Dr. Cardenas for patients on high-dose diuretics, vasodilators, or with orthostatic risk
  • Avoid aggressive manipulations in decompensated states; prioritize gentle mobilization, breathing mechanics, and isometrics tailored to stability.
  • Monitor for signs of worsening congestion: new orthopnea, weight gain, increased abdominal girth, escalating fatigue.

Physiologic rationale: Improving respiratory mechanics increases negative intrathoracic pressure and IVC collapsibility, supporting RV preload management. Autonomic balancing reduces catecholamine burden, which otherwise constricts venous capacitance and impairs renal perfusion (Shaffer & Ginsberg, 2017).

Functional Medicine Foundations: Inflammation, Oxidative Stress, and Nutrition

Functional medicine complements GDMT by addressing systemic drivers:

  • Anti-inflammatory nutrition: Emphasize omega-3s, polyphenol-rich plants, and sodium-aware choices tailored to renal function
  • Mitochondrial support: Consider medically supervised supplementation (e.g., CoQ10 in select cases) with lab-guided oversight
  • Gut barrier integrity: Address dysbiosis with dietary fiber, fermented foods when tolerated, and targeted probiotics; splanchnic congestion can impair gut function, heightening systemic inflammation
  • Sleep and stress modulation: Screen for sleep apnea and apply stress-reduction practices to lower SNS activity

Why it helps: Reducing ROS and inflammatory cytokines alleviates endothelial and tubular stress, potentially slowing fibrosis and improving responsiveness to GDMT and diuretics (Heerspink et al., 2020; McMurray et al., 2019; Yancy et al., 2017).

Personal Injury Care and Rehabilitation: Cardiorenal-Aware Protocols

Many patients with heart failure or CKD present with musculoskeletal pain or injuries that limit activity:

  • Tailor rehabilitation to avoid preload spikes and excessive intrathoracic pressure
  • Use graded activity while monitoring heart rate, blood pressure, oxygen saturation, and perceived exertion
  • Emphasize non-opioid pain management and mechanically informed approaches compatible with cardiovascular safety

In trauma-related cases, thoracoabdominal mechanics may be impaired. Post-injury diaphragm dysfunction and altered posture can exacerbate venous congestion. Our protocols restore:

  • Respiratory mechanics via diaphragm training and rib mobility drills
  • Core stability with low-load exercises to improve abdominal wall tone without excessive pressure
  • Graded activity to enhance skeletal muscle pump and lymph flow

Team-Based Care: Medical Oversight and Integrated Delivery

Under Dr.Cardenas’ss direction:

  • We define congestion targets and diuretic protocols with lab and ultrasound monitoring
  • Chiropractic and rehab schedules are synchronized with medical therapy
  • Functional medicine plans are reviewed for renal safety (e.g., potassium and magnesium loads) and medication interactions
  • Fast-track escalation pathways are in place for decompensation—cardiology, nephrology, advanced heart failure programs, or transplant centers when indicated

This structure ensures precision, safety, and continuity across disciplines.

Clinical Observations From My Practice

In my hands-on experience and professional insights:

  • Patients with pronounced abdominal congestion respond better when we combine respiratory mechanics and gentle thoracic mobility with diuretic therapy
  • Torsemide often outperforms oral furosemide in gut edema due to consistent bioavailability; bumetanide is reliable and potent when absorption is uncertain
  • Adjusting diuretic timing (morning and early afternoon) reduces nocturia and fall risk, improving adherence
  • Pairing loops with metolazone for short, closely monitored bursts can break resistance effectively
  • Low-dose milrinone for RV congestion improves urine output within hours by lowering venous backflow
  • Integrative chiropractic rib mobilization and diaphragmatic retraining lessen dyspnea, enhance exercise tolerance, and reduce perceived fatigue

For deeper insight into my approach and clinical perspectives, see my professional pages:

Putting It All Together: A Practical, Stepwise Pathway

  • Assess congestion comprehensively
    • JVP, hepatojugular reflux, IVC ultrasound, lung B-lines, abdominal exam
    • Determine whether pulmonary, splanchnic, or peripheral compartments dominate
  • Initiate or adjust diuretics
    • Choose loop based on bioavailability and potency; set a dosing schedule that minimizes nocturia.
    • Use sequential nephron blockade when necessary; monitor electrolytes and renal function closely.y
  • Implement GDMT with renal consideratio.ns
    • ACEi/ARB/ARNI, MRA, SGLT2 inhibitor, beta-blocker—tailored to ejection fraction and kidney function
    • Sequence therapies to avoid acute hemodynamic compromise
  • Layer integrative chiropractic and rehabilitation
    • Thoracic and rib mobility, diaphragmatic training, postural optimization, autonomic modulation, calf-pump-centric activity
  • Apply functional medicine strategies.
    • Nutrition, sleep optimization, stress reduction, and microbiome support to reduce inflammation and oxidative stress
  • Coordinate under medical oversight
    • Align therapy changes, monitor safety, and escalate promptly when needed

Why this works: Cardiorenal syndrome is a systemic problem in which hemodynamics, endocrine signals, inflammation, and structural changes interlock. Our model reduces maladaptive neurohormonal activation, safely offloads venous congestion, supports autonomic balance and respiratory mechanics, and ensures medical oversight for complex decisions—bridging chiropractic practice with internal medicine standards.

The Initial Workup and Differentiation: Practical Details

When a patient presents with acute decompensation, we assemble the full physiological picture:

  • CBC to assess infection and anemia, which can mimic refractory dyspnea
  • Comprehensive Metabolic Panel (CMP) for electrolytes, BUN/creatinine, and liver enzymes to gauge hepatic congestion
  • NT-proBNP/BNP to quantify cardiac strain and congestion
  • Urinalysis and urinary sodium to evaluate tubular function and diuretic responsiveness
  • Echocardiogram for ejection fraction, RV function, pulmonary pressures, and IVC size/collapsibility
  • Renal ultrasound to rule out post-obstructive processes (e.g., hydronephrosis); neurogenic bladder and strictures can masquerade as intrinsic AKI
  • 12-lead EKG to evaluate ischemia or arrhythmia triggers (e.g., atrial fibrillation)
  • Lactate for perfusion assessment—elevated levels suggest malperfusion, guiding escalation beyond simple diuresis

This workup helps answer whether heart failure drove renal dysfunction or vice versa (Ronco et al., 2008; Stevenson, 1999).

Hemodynamic Profiles and Cardiorenal Types: Guiding Strategy

Categorizing hemodynamic profiles:

  • Warm and wet: Good perfusion, congested—focus on diuresis
  • Cold and wet: Poor perfusion and congested—combine diuretics with inotropic/perfusion support
  • Warm and dry: Stable and compensated
  • Cold and dry: Low output without congestion—consider volume or inotropes, not diuretics

Cardiorenal syndrome types:

  • Type 1: Acute heart failure → acute kidney injury
  • Type 2: Chronic heart failure → progressive CKD
  • Type 3: Acute kidney injury → acute heart dysfunction
  • Type 4: Chronic kidney disease → cardiac hypertrophy and diastolic dysfunction
  • Type 5: Systemic condition (e.g., sepsis, lupus) → both heart and kidney dysfunction (Ronco et al., 2008)

These frameworks refine therapy and escalation plans.

Patient-Centered Communication: Functional Signs That Matter

I listen for specific functional clues:

  • Orthopnea: Difficulty lying flat; ask how many pillows or whether the patient sleeps in a recliner
  • Paroxysmal nocturnal dyspnea (PND): Sudden nighttime dyspnea often described as a panic episode
  • Bendopnea: Shortness of breath when bending; a specific sign pointing to increased intracardiac pressures
  • Dyspnea on exertion (DOE): Probe real-world activities (parking lot walk, vacuuming) rather than abstract distances
  • Early satiety, bloating, weight gain, peripheral edema: Indicators of splanchnic and systemic congestion
  • Fatigue, confusion, low urine output: Signs of malperfusion, corroborated by lactate

These narratives connect laboratory and imaging data to lived physiology, guiding personalized care.

Conclusion: A Modern, Multidisciplinary Path to Cardiorenal Stability

Cardiorenal syndromes require precision medicine anchored in physiology and delivered through integrated care. Diuretics, used with a clear grasp of thresholds, ceilings, and pharmacokinetics, remain foundational for decongestion. Thoughtful GDMT sequencing stabilizes neurohormonal networks. When needed, inotropes, ultrafiltration, and mechanical support provide timely escalation. In our El Paso practice, the co-led model—Dr. Maria Guadalupe Cardenas, M.D., providing internal medicine oversight, and I integrating chiropractic and functional medicine—help patients breathe easier, move better, and regain confidence in daily life.
For more about my clinical observations and approach, visit:

References

SEO tags: cardiorenal syndrome, heart failure, chronic kidney disease, RAAS, sympathetic nervous system, natriuretic peptides, venous congestion, right ventricular dysfunction, splanchnic reservoir, loop diuretics, torsemide, bumetanide, GDMT, SGLT2 inhibitors, mineralocorticoid receptor antagonists, inotropes, ultrafiltration, mechanical circulatory support, integrative chiropractic care, thoracic mobility, diaphragmatic training, functional medicine, El Paso, Injury Medical Clinic PA, Mission Plaza Injury Medical Clinic, Dr. Maria Guadalupe Cardenas MD, Dr. Alex Jimenez DC APRN FNP-BC