Stress Headaches After a Car Accident: Why Families Should Recognize the Symptoms
Abstract
A parent may walk away from a car accident, return to work, resume school pickups, cook dinner, help with homework, and appear to be getting back to normal. Yet by evening, a dull pressure begins building around the forehead, temples, or back of the head. The neck feels tight. The shoulders ache. Concentration becomes harder. These symptoms are often described as “stress headaches,” but after a motor vehicle accident, the complete clinical picture matters. A tension-type headache, migraine, whiplash-related headache, and concussion-related headache can overlap. Proper evaluation helps identify warning signs, determine whether the neck or nervous system may be involved, and guide individualized treatment. Options may include appropriate medication, relaxation and stress-management strategies, rehabilitation, exercise, musculoskeletal care, acupuncture, and other treatments chosen based on the patient’s examination and diagnosis.

When the Accident Is Over but the Headaches Are Just Beginning
Imagine a parent who was rear-ended while driving home.
The first few days are busy. Phone calls, vehicle repairs, work responsibilities, school schedules, meals, and family obligations fill the days. The parent may have some neck stiffness but believes the problem will gradually disappear.
During the day, things seem manageable.
Then, almost every evening, a pressure-like headache develops.
It may feel as though a band is tightening around the forehead. The muscles at the base of the skull feel tired. The shoulders are tense. After hours of work, driving, screen time, and caring for children, the headache becomes difficult to ignore.
It is tempting to say, “I’m just stressed.”
Stress may indeed be contributing. But a new headache after a collision deserves more careful consideration because headaches following trauma can have several possible explanations.
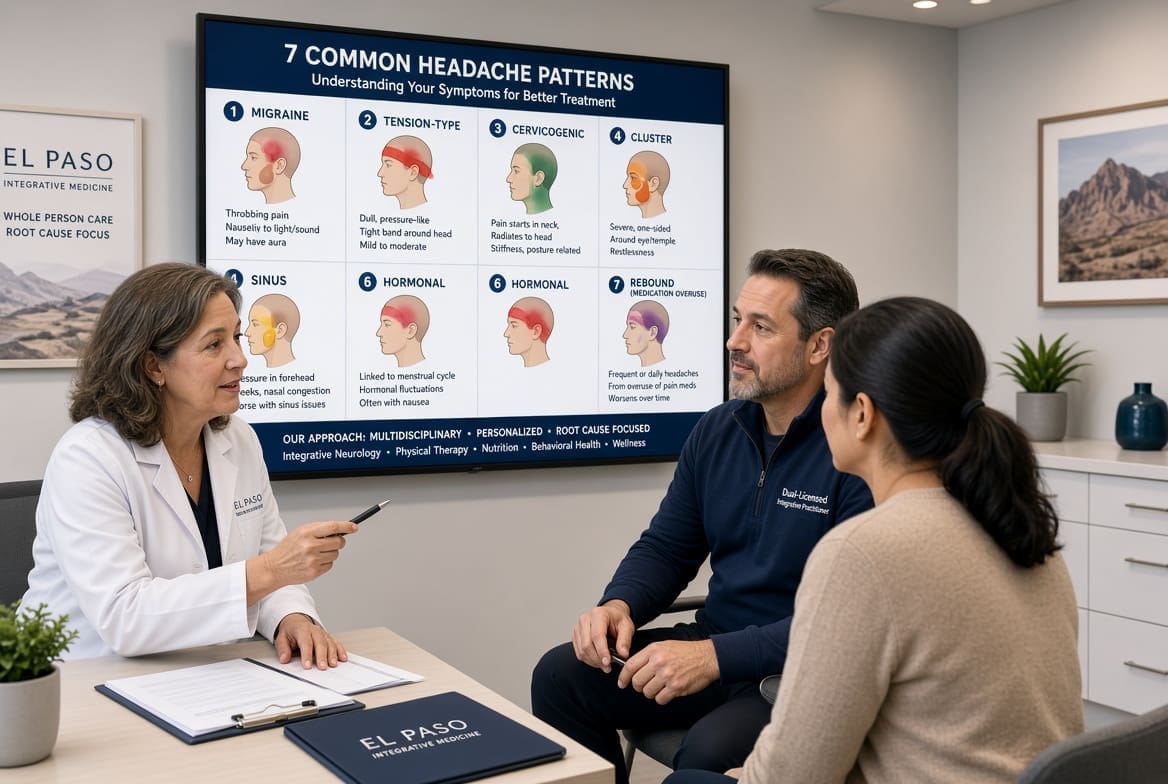
The International Classification of Headache Disorders recognizes headaches attributed to head injury and headaches attributed to whiplash as secondary headache disorders. Importantly, a post-traumatic headache can resemble a tension-type headache or migraine. In other words, how the headache feels does not, by itself, determine why it developed (Headache Classification Committee of the International Headache Society [IHS], 2018).
For additional background, families can review Post-Traumatic Headaches After Accidents: Causes Explained. Post-Traumatic Headaches After Accidents: Causes Explained
What Is a Tension-Type Headache?
Tension-type headaches are among the most common headache disorders.
The classic pattern is a mild-to-moderate headache with a pressing or tightening sensation rather than a strong pulsating sensation. They often affect both sides of the head and generally do not worsen dramatically with walking, climbing stairs, or other ordinary daily activities.
Under established diagnostic criteria, tension-type headaches commonly have characteristics such as:
- Pressure, tightness, or a “band-like” feeling
- Pain on both sides of the head
- Mild-to-moderate intensity
- Tenderness around the scalp, neck, or shoulders
- Episodes lasting from about 30 minutes to several days
- Little or no nausea
- No vomiting
- Less prominent light and sound sensitivity than typically occurs with migraine
Frequent episodic tension-type headaches occur on 1 to 14 days per month for more than three months. Chronic tension-type headaches occur at least 15 days per month for more than three months (IHS, 2018).
However, immediately labeling every pressure-like headache after an automobile accident a “tension headache” can miss an important distinction.
A Headache Can Look Like a Tension-Type Headache but Still Be Post-Traumatic
Suppose our parent never experienced regular headaches before the collision.
After the rear-end impact, neck stiffness develops. Within several days, evening headaches begin. They feel bilateral and pressure-like — almost exactly like tension-type headaches.
The headache phenotype, or outward pattern, may resemble tension-type headache. But because it developed following trauma, clinicians must consider whether it represents a headache attributed to whiplash or another post-traumatic condition.
ICHD-3 defines whiplash as sudden acceleration-deceleration movement of the head involving the neck. A headache developing within seven days of qualifying whiplash can meet criteria for acute headache attributed to whiplash when other diagnostic requirements are satisfied (IHS, 2018).
That distinction is important for families because the correct question is not simply:
“Is this a stress headache?”
A better question is:
“Why did this particular headache begin after this particular accident?”
Stress Headache vs. Migraine
Migraine usually creates a different symptom pattern.
A migraine frequently involves moderate-to-severe pain that may be pulsating or throbbing. It is commonly worse with ordinary physical activity. Some people experience pain predominantly on one side, although migraine can occur on both sides.
Nausea, vomiting, strong light sensitivity, and sound sensitivity are also more characteristic of migraine.
The ICHD-3 describes migraine without aura as attacks usually lasting 4 to 72 hours and commonly involving features such as pulsating pain, moderate-to-severe intensity, worsening with routine activity, nausea, or sensitivity to both light and sound (IHS, 2018).
That does not mean every throbbing post-accident headache is automatically migraine. Trauma-related headaches can also develop a migraine-like pattern.
The clinical history still matters.
What About a Concussion-Related Headache?
Concussion creates another important possibility.
A concussion is a mild traumatic brain injury. Headache is common, but clinicians look beyond it.
Possible concussion symptoms can include:
- Dizziness or balance problems
- Nausea or vomiting
- Blurred or abnormal vision
- Sensitivity to light or noise
- Feeling mentally “foggy”
- Difficulty concentrating
- Memory problems
- Fatigue
- Irritability or emotional changes
- Sleeping more or less than usual
- Trouble falling asleep
Some symptoms develop immediately, while others may become apparent hours or days later. The CDC emphasizes that concussion symptoms can affect physical function, thinking, emotions, and sleep (Centers for Disease Control and Prevention [CDC], 2025).
This is why families should not diagnose a post-accident headache based only on where the pain is located.
Why Physical Stress Can Build During the Day
Return to our parent.
By morning, the headache may be barely noticeable. But then comes commuting, computer work, looking down at a phone, carrying groceries, helping children, cooking, and cleaning.
Meanwhile, the neck and shoulder muscles may still be recovering from the collision.
Whiplash can expose the cervical region to rapid acceleration and deceleration. Afterward, some patients develop neck stiffness, guarding, reduced movement, tenderness, or altered muscular endurance.
The longer the neck must support everyday activities while recovering, the more noticeable the discomfort may become.
Research has identified cervical musculoskeletal impairments in some people with tension-type headache, although the certainty of individual findings varies and clinicians should avoid assuming that every headache originates from the neck (Liang et al., 2025).
That is one reason a proper examination matters.
Emotional Stress Matters Too
Physical strain is only part of the story.
An automobile collision can suddenly introduce:
- Transportation problems
- Financial uncertainty
- Insurance paperwork
- Missed work
- Disrupted childcare
- Poor sleep
- Fear about driving
- Worry about physical symptoms
- Concern about whether recovery will take weeks or months
Those stresses can interact with pain.
Current headache research supports a biopsychosocial perspective in which musculoskeletal, neurologic, behavioral, psychological, sleep, and lifestyle factors may interact rather than operating independently. Psychological factors including anxiety, depression, and fear of pain have been associated with greater headache burden in people with migraine and tension-type headache.
This does not mean the headache is imaginary or “just emotional.”
It means the nervous system, muscles, sleep patterns, emotional state, and physical injury can influence one another.
Why Medical Evaluation Matters
A new or changing headache after an automobile accident should be evaluated according to the circumstances.
A clinician may ask about:
- How the collision happened
- Whether the head struck anything
- Loss of consciousness
- Memory gaps
- Dizziness
- Nausea or vomiting
- Vision changes
- Neck pain
- Shoulder pain
- Numbness or weakness
- Headache location
- Headache quality
- When the headache began
- Previous migraine or headache history
- Medications
- Sleep changes
- Emotional symptoms
The physical examination may include neurologic screening, balance or coordination testing when appropriate, cervical range of motion, muscular examination, strength, sensation, reflexes, and other tests based on the patient’s presentation.
Imaging is not automatically necessary for every headache. Base the decision on the mechanism of injury, examination findings, red flags, and clinical judgment.
For related patient education, see Delayed Symptoms After a Crash: Key Facts to Understand. Delayed Symptoms After a Crash: Key Facts to Understand
Headache Warning Signs Families Should Not Ignore
Some post-accident symptoms require urgent medical evaluation.
Seek emergency care for concerning symptoms such as a headache that progressively worsens and does not go away, repeated vomiting, seizures, unusual confusion or behavior, slurred speech, new weakness or numbness, loss of coordination, increasing inability to stay awake, one pupil becoming larger than the other, or double vision.
These can represent warning signs of a more serious brain injury and should not be managed simply as muscle tension or stress (CDC, 2025).
Treatment Depends on the Diagnosis
No single treatment fits every post-car-accident headache.
The treatment plan should match the diagnosis and the patient’s overall health.
Medication and Prescribed Treatment
For appropriately diagnosed tension-type headache, commonly used acute medications can include acetaminophen or certain nonsteroidal anti-inflammatory medications when medically appropriate.
The 2023 VA/DoD guideline also discusses preventive medication for chronic tension-type headache and stresses the importance of avoiding patterns of excessive analgesic use that may contribute to medication-overuse headache (Sico et al., 2024).
Medication selection should account for medical history, other medications, gastrointestinal risks, kidney disease, cardiovascular considerations, pregnancy, and other individual factors.
Relaxation and Stress Management
For the parent whose symptoms appear after a long day, reducing nervous-system and muscular loading may become part of care.
Strategies may include:
- Regular sleep scheduling
- Relaxation exercises
- Controlled breathing
- Appropriate physical activity
- Scheduled breaks from prolonged computer work
- Stress-management training
- Psychological support when needed
These approaches do not suggest the headache is “all stress.” Instead, they address factors that may amplify pain and muscle tension.
Rehabilitation and Exercise
Physical therapy, rehabilitation, and appropriately prescribed exercise can also be part of tension-type headache management.
The VA/DoD clinical practice guideline includes physical therapy and aerobic exercise among management options for tension-type headache (Sico et al., 2024).
A 2025 systematic review and meta-analysis also found that neck-shoulder strengthening, muscle-relaxation approaches, and some physiotherapy strategies improved selected headache outcomes in chronic tension-type headache, although treatment still needs to be individualized (Onan et al., 2025).
Appropriate Musculoskeletal and Chiropractic Care
When examination identifies cervical joint restriction, muscle guarding, postural problems, or other mechanical findings, carefully selected musculoskeletal care may complement active rehabilitation.
Depending on the patient’s condition, this might involve:
- Gentle manual techniques
- Soft-tissue treatment
- Mobility exercises
- Postural retraining
- Cervical stabilization
- Shoulder and upper-back strengthening
- Progressive functional rehabilitation
Chiropractic treatment should not replace medical or neurologic evaluation when concussion, fracture, vascular problems, or another serious condition is suspected.
The goal is to choose the appropriate treatment for the appropriate patient rather than assuming every post-accident headache requires the same intervention.
Acupuncture and Electroacupuncture as Adjunctive Options
Acupuncture may also be considered as part of a broader treatment strategy for selected headache patients.
A 2025 systematic review reported improvements in some chronic tension-type headache outcomes with electroacupuncture, neck-shoulder exercise, and muscle-relaxation approaches. Interpret the evidence in the context of differences among treatment protocols and studies (Onan et al., 2025).
Patients interested in this option can read Reducing Headaches With Acupuncture: All You Need to Know. Reducing Headaches With Acupuncture: All You Need to Know
Acupuncture and electroacupuncture are best viewed as potential complementary treatments rather than substitutes for evaluating possible concussion or other serious causes of post-traumatic headache.
What Makes Dr. Jimenez’s Injury Medical Chiropractic and Functional Medicine Clinic Different?
Dr. Jimenez’s Injury Medical Chiropractic and Functional Medicine Clinic in El Paso uses a multidisciplinary model that coordinates musculoskeletal, medical, and rehabilitative care, so patients don’t have to navigate each area independently.
Dr. Alex Jimenez, DC, APRN, FNP-BC, combines chiropractic training with advanced-practice nursing and focuses on soft-tissue injury, musculoskeletal assessment, rehabilitation, and integrated medical care.
The practice also includes Dr. Maria Guadalupe Cardenas, MD, a board-certified internal medicine physician with more than 40 years of clinical experience who serves as Medical Director and Collaborative Physician. Clinic materials describe the practice as one of the few El Paso-area models that brings medical direction, nurse-practitioner soft-tissue injury expertise, chiropractic care, rehabilitation, and complementary therapies together in a coordinated clinical setting.
This arrangement can be particularly valuable after an accident because headache symptoms do not always fit neatly into one category. The patient may need cervical examination, concussion screening, medication review, rehabilitation, lifestyle counseling, or referral for additional evaluation.
The goal is not simply to suppress a headache. It is to understand the patient’s presentation and choose care that supports safe recovery.
More information about the clinic’s integrated model is available on the About Dr. Alexander Jimenez and His Clinic page. About Dr. Alexander Jimenez and His Clinic
Helping a Parent Get Through the Evening Again
Return to the parent at the beginning of our story.
The key observation wasn’t simply that the headaches occurred at night.
It was the pattern:
The headaches began after an accident. The neck was tight. Symptoms increased after a full day of physical and emotional demands. No similar headache pattern existed before the collision.
That information gives clinicians a starting point.
Sometimes the diagnosis may be tension-type headache. In other patients, the more accurate explanation may be headache attributed to whiplash, migraine triggered or aggravated after trauma, concussion-related headache, cervicogenic headache, or more than one overlapping condition.
Recognizing those differences gives patients something valuable: better information and greater control over their healthcare decisions.
For families, the message is straightforward.
Do not panic over every headache after an accident — but do not dismiss a recurring new headache as “just stress,” either.
Pay attention to the pattern. Watch for neurologic warning signs. Describe the symptoms carefully. Obtain appropriate medical evaluation.
Once serious conditions have been ruled out and the headache pattern has been identified, conservative and multidisciplinary options such as medication when indicated, stress management, sleep support, rehabilitation, exercise, musculoskeletal care, acupuncture, and electroacupuncture can be considered according to the patient’s individual needs.
References
Centers for Disease Control and Prevention. (2025). Symptoms of mild TBI and concussion. Symptoms of Mild TBI and Concussion
Headache Classification Committee of the International Headache Society. (2018). The International Classification of Headache Disorders, 3rd edition. Cephalalgia, 38(1), 1–211. International Classification of Headache Disorders, 3rd edition
Onan, D., Arıkan, H., Ekizoğlu, E., Taşdelen, B., Özge, A., & Martelletti, P. (2025). The efficacy of physiotherapy approaches in chronic tension-type headache: A systematic review and meta-analysis. Journal of Oral & Facial Pain and Headache, 39(1), 34–48. The efficacy of physiotherapy approaches in chronic tension-type headache
Repiso-Guardeño, A., Moreno-Morales, N., Armenta-Pendón, M. A., Rodríguez-Martínez, M. C., Pino-Lozano, R., & Armenta-Peinado, J. A. (2023). Physical therapy in tension-type headache: A systematic review of randomized controlled trials. International Journal of Environmental Research and Public Health, 20(5), 4466. Physical Therapy in Tension-Type Headache
Sico, J. J., Antonovich, N. M., Ballard-Hernandez, J., Buelt, A. C., Grinberg, A. S., Macedo, F. J., Pace, I. W., Reston, J., Sall, J., Sandbrink, F., Skop, K. M., Stark, T. R., Vogsland, R., Wayman, L., & Ford, A. V. (2024). 2023 U.S. Department of Veterans Affairs and U.S. Department of Defense clinical practice guideline for the management of headache. Annals of Internal Medicine. VA/DoD Clinical Practice Guideline for the Management of Headache
Medical disclaimer: This article is for educational purposes and does not replace an examination, diagnosis, or individualized medical advice from a qualified healthcare professional. New, worsening, or neurologically concerning headaches following trauma require appropriate medical evaluation.