Category: Advanced Practice Registered Nurses (APRN)
ChiroMedBlogAdvanced Practice Registered Nurses (APRN)
Discover the role of Advanced Practice Registered Nurses (APRN): highly skilled healthcare professionals providing specialized care and improving patient outcomes.
This educational post explores the advanced technique of hydrodistension (or hydroplasty) for treating adhesive capsulitis, commonly known as frozen shoulder. As a practitioner rooted in integrative and functional medicine, I continually seek the most effective, evidence-based solutions for my patients. Here, I’ll guide you through a detailed look at the hydrodistension procedure, drawing on insights from leading sports medicine experts. We will examine the anatomical basis, the procedural steps, and the physiological mechanisms that make this technique a powerful tool for restoring mobility and relieving pain. I will also explain how this intervention fits within our multidisciplinary practice at Injury Medical Clinic, where my work as a Doctor of Chiropractic and Family Nurse Practitioner is complemented by the medical oversight of our Medical Director, Dr. Maria Guadalupe Cardenas, MD. Our goal is to provide a comprehensive treatment journey that combines advanced medical procedures with chiropractic care, rehabilitation, and functional medicine to achieve lasting patient outcomes.
At Injury Medical Clinic, our philosophy is built on collaboration and integration. My name is Dr. Alex Jimenez, and I bring a multifaceted perspective to patient care, holding qualifications as a Doctor of Chiropractic (DC), an Advanced Practice Registered Nurse (APRN), a Board-Certified Family Nurse Practitioner (FNP-BC), and certifications in Functional Medicine (CFMP, IFMCP), among others. This diverse background allows me to view health and injury through a uniquely broad lens.
A cornerstone of our practice is our multidisciplinary team approach. I work closely with Dr. Maria Guadalupe Cardenas, MD, our esteemed Medical Director and an internist with over 40 years of experience. Her role is vital, providing essential medical direction and oversight that ensures our patients receive care that is not only effective but also safe and comprehensive. This partnership between a chiropractor/nurse practitioner and an internist lets us blend the best of the medical and chiropractic worlds, offering services ranging from personal injury rehabilitation and functional medicine to advanced interventional procedures. Today, I want to share insights into one such procedure that exemplifies this integrated model: hydrodistension for frozen shoulder.
Before diving into the procedure, let’s understand the condition it treats. Adhesive capsulitis, or frozen shoulder, is a debilitating condition characterized by severe pain and a progressive loss of shoulder motion. The underlying pathology involves the glenohumeral joint capsule—the strong, fibrous sac that envelops the shoulder joint. In a healthy shoulder, this capsule is flexible and allows for a wide range of motion. In adhesive capsulitis, the capsule becomes inflamed, thickens, and contracts, effectively “shrinking” around the joint. This process leads to the formation of adhesions, which are bands of scar tissue that bind the capsule to the humeral head (the ball of the shoulder joint), severely restricting movement.
Patients typically experience three phases:
Freezing Stage: A gradual onset of deep, aching pain, often worse at night. As pain intensifies, range of motion begins to decrease. This stage can last from weeks to months.
Frozen Stage: Pain may start to subside, but stiffness becomes the primary complaint. The shoulder’s range of motion is significantly limited, making daily activities like dressing or reaching overhead extremely difficult. This phase can last for several months to a year.
Thawing Stage: Shoulder mobility slowly improves as the condition resolves. This can be a very long process, sometimes taking one to two years to regain full or near-full function.
The goal of any effective treatment is to shorten these phases, alleviate pain, and restore function as quickly and completely as possible.
Hydrodistension: An Advanced Technique for Restoring Mobility
Hydrodistension, also known as hydroplasty, is a minimally invasive procedure designed specifically for adhesive capsulitis. The fundamental principle is to physically stretch and break the adhesions within the joint capsule by injecting a large volume of fluid. This creates more space within the joint, allowing for an immediate improvement in range of motion.
I recently had the opportunity to review the work of a primary care sports medicine physician. Their meticulous, ultrasound-guided approach is an excellent model for understanding how to perform this procedure safely and effectively. Let’s break down his process, which serves as a benchmark in modern, evidence-based practice.
To visualize the target area, we can look at an ultrasound image of the posterior (back) shoulder.
In the image, you can clearly see the layers of tissue:
The deltoid muscle on the surface.
The infraspinatus muscle (one of the rotator cuff muscles) just below it.
The posterior capsule, the key target, which appears as a bright, fibrous line.
The humeral head, the “ball” of the shoulder joint.
The glenoid, the “socket” of the shoulder joint.
The goal is to accurately place a needle into the glenohumeral joint space—the small area between the capsule and the humeral head—to deliver the fluid.
The Three-Step Hydrodistension Procedure
The doctor’s method is a well-orchestrated, three-step process designed for maximum patient comfort and procedural success. It involves precise, ultrasound-guided injections to ensure accuracy and safety at every stage.
Step 1: Suprascapular Nerve Block
The first and arguably most compassionate step is to manage the patient’s pain during and after the procedure. This is achieved with a suprascapular nerve block.
The Target: The suprascapular nerve, which provides approximately 70% of the sensory innervation to the shoulder joint. By numbing this nerve, we can significantly reduce procedure-related pain and provide intermediate relief for hours afterward. The nerve is targeted at the spinoglenoid notch, a small anatomical landmark located just medial to the glenohumeral joint.
The Technique: Using an ultrasound, Dr. visualizes the spinoglenoid notch and guides a needle to the area. He then injects a local anesthetic, typically a combination of lidocaine (fast-acting) and ropivacaine (long-acting). This dual-anesthetic approach provides both immediate and extended pain control.
Why It’s Done: This nerve block is crucial for patient tolerance. The hydrodistension itself can be uncomfortable as the capsule stretches. By preemptively blocking the primary sensory nerve, the patient remains comfortable, and the physician can perform the procedure without causing undue distress. This aligns with our patient-centered approach at Injury Medical Clinic, where comfort and safety are paramount.
Step 2: Numbing the Joint Capsule
Next, anesthetize the injection site and the joint capsule.
The Target: The posterior glenohumeral joint space.
The Technique: A smaller, 25-gauge needle is guided under ultrasound into the joint space. A small amount of buffered lidocaine is injected. The “buffering” is done by adding sodium bicarbonate to the lidocaine, which raises its pH to be closer to that of the body’s tissues. This simple modification reduces the stinging sensation of the injection, further enhancing patient comfort.
Why It’s Done: This local numbing ensures the larger needle in the final step is painless. It also confirms that the needle tip is correctly positioned within the intra-articular space before the main injection begins.
Step 3: The Hydrodistension Injection
This is the main event, where the therapeutic distension occurs.
The Injectate: A carefully formulated mixture totaling 51 mL. It consists of:
10 mL of 1% lidocaine (fast-acting anesthetic)
10 mL of 0.5% ropivacaine (long-acting anesthetic)
30 mL of sterile saline (the primary volume for distension)
1 mL of Kenalog (40 mg) (a corticosteroid to reduce inflammation)
The Technique: A larger, 18-gauge needle is guided into the same intra-articular position. This is often a two-person job; The doctor guides the needle while his medical assistant steadily pushes the large volume of fluid from the syringe. As the fluid is injected, the ultrasound screen provides real-time feedback. You can literally watch the posterior capsule lift and stretch away from the humeral head as it fills with fluid.
The “Break”: The goal is to continue injecting until the capsule is stretched to its limit and the adhesions break. On ultrasound, this appears as a sudden expansion followed by slight deflation as the fluid finds new space within the joint, or may even extravasate (leak) through a small tear in the now-stretched capsule. This visible “break” is the hallmark of a successful procedure. The patient often feels an immediate sense of release and an increase in their range of motion.
Using a corticosteroid like Kenalog is critical. It strongly suppresses the inflammatory process that drives capsule thickening and contraction. This not only relieves pain but also helps prevent rapid re-formation of adhesions, creating a therapeutic window for the next phase of care: rehabilitation.
The Role of Integrative Chiropractic Care Post-Procedure
The hydrodistension procedure is a powerful “reset” for the shoulder, but it is not a standalone cure. The real, long-term success comes from what happens next. The days and weeks following the procedure are a critical window of opportunity to restore normal joint mechanics and muscle function. This is where our integrative model at Injury Medical Clinic truly shines.
As a Doctor of Chiropractic, I immediately focus on capitalizing on the newly gained mobility. My clinical observations, detailed on platforms like my professional website and LinkedIn, consistently show that a structured, multi-faceted rehabilitation program is essential.
Our post-hydrodistension protocol includes:
Gentle Chiropractic Mobilization: After the procedure, I perform specific, gentle mobilization techniques on the glenohumeral joint and surrounding joints, including the scapulothoracic (shoulder blade on the rib cage), acromioclavicular, and sternoclavicular joints. The goal isn’t aggressive manipulation, but to encourage smooth, physiological movement and prevent the joint from stiffening again. We must respect the body’s healing process while re-educating the joint on how to move correctly.
Targeted Soft Tissue Therapy: Adhesions don’t just form in the capsule; the surrounding muscles often become tight, guarded, and develop trigger points. We use techniques like myofascial release, instrument-assisted soft tissue mobilization (IASTM), and trigger point therapy to release tension in the rotator cuff, deltoid, and periscapular muscles. This restores muscle pliability and reduces compensatory strain patterns.
Prescriptive Rehabilitation Exercises: This is the most crucial component. We guide patients through a phased exercise program that begins with gentle pendulum exercises and passive range-of-motion on the day of the procedure. As tolerance improves, we progress to:
Active-assisted range of motion (using the other arm or a pulley to help move the affected shoulder).
Active range of motion (moving the shoulder under its own power).
Strengthening exercises, starting with isometrics and progressing to resistance bands to rebuild the strength and endurance of the rotator cuff and scapular stabilizers.
Under the medical direction of Dr. Cardenas, we ensure this rehabilitation process is medically appropriate for the patient, monitoring for complications and managing post-procedural inflammation. This collaborative oversight allows us to safely push the boundaries of recovery.
Conclusion: An Integrated Path to Recovery
Treating complex conditions like adhesive capsulitis requires more than a single intervention. It demands a holistic, integrated approach that addresses the problem from multiple angles. The hydrodistension procedure, as expertly demonstrated by physicians, provides a powerful mechanical and pharmacological intervention to break the cycle of stiffness and pain. It creates a pivotal opportunity for recovery.
However, the comprehensive, team-based care that follows truly solidifies the gains and leads to lasting results. At Injury Medical Clinic, our unique structure—combining my expertise in chiropractic and functional medicine with the invaluable medical oversight of Dr. Maria Guadalupe Cardenas—allows us to provide that. We bridge the gap between advanced medical procedures and hands-on rehabilitative care, guiding our patients on a seamless journey from profound limitation to renewed function and a life free from pain.
References
Boutin, R. D., Darrow, M. A., & Schenker, M. L. (2014). Ultrasound-guided shoulder interventions. Physical Medicine and Rehabilitation Clinics of North America, 25(2), 247–266. https://doi.org/10.1016/j.pmr.2014.01.002
Ryan, V., Brown, H., Minns Lowe, C. J., & Lewis, J. S. (2016). The pathophysiology associated with primary (idiopathic) frozen shoulder: A systematic review. BMC Musculoskeletal Disorders, 17(1), 340. https://doi.org/10.1186/s12891-016-1190-9
Tveitå, E. K., & Røe, C. (2009). Ultrasound-guided hydrodistension and physiotherapy for patients with frozen shoulder. Physiotherapy Research International, 14(1), 39–51. https://doi.org/10.1002/pri.422
Explore chiropractic rehabilitation for systemic inflammation and its impact on chronic disease and immune health in this comprehensive guide.
Abstract: Unraveling the Single Root of Chronic Illness
In this comprehensive educational post, I will guide you through the intricate world of systemic inflammation, a persistent, low-grade immune response that modern science now identifies as the single unifying mechanism behind many of our most devastating chronic diseases. We will explore how this state of constant immune activation, driven by a specific type of immune cell called the M1 macrophage, fuels conditions ranging from type 2 diabetes and cardiovascular disease to neurodegenerative disorders like Alzheimer’s and Parkinson’s. I will break down the complex immunology, explaining the crucial difference between the “burn it all down” M1 macrophages and their “clean it all up” counterparts, the M2 macrophages. Drawing on groundbreaking research from leading journals like The Lancet and Nature Medicine, we will see how elevated inflammatory markers are as predictive of mortality as well-known risk factors like smoking. We will also delve into the critical role of the thymus gland in immune regulation and how its dysfunction can lead to what is commonly mislabeled as “autoimmune” disease. Finally, I will connect these cutting-edge concepts to our clinical approach at Injury Medical Clinic. I will explain how our unique, multidisciplinary model—integrating my expertise in chiropractic care, functional medicine, and as a Family Nurse Practitioner with the invaluable medical oversight of our Medical Director, Dr. Maria Guadalupe Cardenas, MD—allows us to address the upstream root cause of inflammation, rather than just managing its downstream symptoms. This post will illuminate how integrative strategies, from precise chiropractic adjustments to targeted functional medicine protocols, work synergistically to restore balance to the body and pave the way for true, lasting health.
Introducing Our Collaborative Care Model at Injury Medical Clinic
Before we embark on this deep dive into the science of inflammation, I believe it’s essential to provide some context about our unique clinical environment and the philosophy that guides our patient care. I am Dr. Alex Jimenez, and my journey in healthcare has led me to acquire a diverse set of credentials: DC (Doctor of Chiropractic), APRN (Advanced Practice Registered Nurse), FNP-BC (Family Nurse Practitioner-Board Certified), CFMP (Certified Functional Medicine Practitioner), IFMCP (Institute for Functional Medicine Certified Practitioner), ATN (Advanced Therapeutix Network), and CCST (Chiropractic Certification in Spinal Trauma). This extensive training reflects my core belief that true healing requires a multifaceted approach that honors the body’s intricate, interconnected systems.
Here at Injury Medical Clinic PA in El Paso, Texas, we have built a practice on this very principle. Our strength lies in our multidisciplinary, integrative framework. I am honored to work alongside Dr. Maria Guadalupe Cardenas, MD, a distinguished physician with over 40 years of experience as a board-certified internist. Dr. Cardenas serves as our Medical Director and Collaborative Physician, providing essential medical oversight and a depth of clinical wisdom that is simply irreplaceable. Her Texas MD License is #J2933, and her NPI is #1164426749.
This collaborative setup, where an MD provides medical direction alongside a chiropractor and functional medicine practitioner, is a cornerstone of modern integrative care. It allows us to offer a comprehensive spectrum of services under one roof, including:
Medical Oversight (Dr. Cardenas): Ensuring all treatment plans are medically sound, safe, and appropriate, especially for patients with complex comorbidities or those requiring medical interventions.
Chiropractic Care (Dr. Jimenez): Focusing on the biomechanical and neurological integrity of the body, particularly the spine, to optimize nervous system function and reduce physical stressors that can drive inflammation.
Functional Medicine (Dr. Jimenez): Investigating the root causes of disease by looking at genetics, lifestyle, and environmental factors to create personalized treatment plans.
Personal Injury and Rehabilitation: Providing specialized care for individuals who have sustained injuries, guiding them from acute pain to full functional recovery.
Advanced Diagnostics and Therapeutics: Utilizing cutting-edge tools to understand and treat complex health issues.
Together, Dr. Cardenas and I, along with our dedicated team, bridge the gap between conventional medicine and holistic care. We don’t see the body as a collection of separate parts but as a single, dynamic organism. This integrated perspective is precisely what is needed to tackle a pervasive issue like systemic inflammation, the central topic of our discussion today.
The Unseen Fire: Understanding Systemic Inflammation
In my years of clinical practice, I have seen countless patients come to me with a constellation of seemingly unrelated symptoms: joint pain, brain fog, fatigue, digestive issues, high blood pressure, and stubborn weight gain. They have often been to multiple specialists, each providing a different diagnosis and a different prescription. Yet, they remain unwell. Conventional medicine has traditionally focused on treating the downstream effects—the smoke—while ignoring the upstream fire. That fire, more often than not, is systemic inflammation.
So, what exactly is systemic inflammation? It’s what happens when your body’s immune system, your internal defense force, gets stuck in the “on” position and never turns off. Imagine a fire alarm that blares constantly, day and night. Initially, the alarm serves a vital purpose—to alert you to danger. But when it rings incessantly, it becomes a problem in itself, creating noise, stress, and chaos. This is precisely what occurs in the body. Acute inflammation is a life-saving response to injury or infection. It’s the redness, swelling, and heat you feel when you sprain an ankle. It’s a targeted, short-lived process designed to eliminate a threat and initiate healing. Systemic inflammation, however, is different. It is chronic, low-grade, and body-wide. It’s a smoldering fire that silently damages tissues and organs over months, years, and even decades.
The Cellular Architects of Inflammation: Meet the Macrophages
To truly grasp this concept, we need to zoom in to the cellular level and meet the primary orchestrators of this process: the macrophages. These are biology’s main innate immune cells, the frontline soldiers of your immune system. They are versatile, dynamic cells that can change their function based on the signals they receive from their environment. Think of them as cellular chameleons.
From my perspective as a functional medicine practitioner, understanding this cellular behavior is paramount. The key insight is that macrophages exist on a functional spectrum.
M1 Macrophages: The “Burn It All Down“ Brigade: At one end of this spectrum, we have the M1 phenotype. When a macrophage adopts this M1 state, it becomes fiercely pro-inflammatory. Its mission is to destroy invaders—be they bacteria, viruses, or damaged cells. To do this, it unleashes a powerful arsenal of chemical weapons, including inflammatory cytokines like Tumor Necrosis Factor-alpha (TNF-alpha), Interleukin-6 (IL-6), and Interleukin-1beta (IL-1β). It also produces reactive oxygen species (ROS), highly reactive molecules that cause oxidative stress and cellular damage. Think of the M1 macrophage as being in a “burn it all down” mode. In an acute infection, this response is essential for survival.
M2 Macrophages: The “Clean It All Up“ Crew: At the other end of the spectrum lies the M2 phenotype. These macrophages are anti-inflammatory and are focused on resolution and repair. Their job is to complete the inflammatory cycle. They produce calming, healing molecules like Interleukin-10 (IL-10) and Transforming Growth Factor-beta (TGF-β). They also secrete an enzyme called arginase-1, which helps promote tissue growth. M2 macrophages are the cleanup crew; they clear away cellular debris left over from the battle, coordinate tissue repair, and effectively tell the immune system to stand down. Think of the M2 macrophage as being in a “clean it all up and rebuild” mode.
A healthy immune response involves a seamless and timely transition from an M1-dominant phase to an M2-dominant phase. The problem in systemic inflammation is that this transition never happens. The macrophages get stuck in the pro-inflammatory M1 mode. They continuously pump out TNF-alpha and IL-6, not just in one isolated tissue, but throughout your entire bloodstream, bathing every organ in a toxic, inflammatory soup.
The Stark Reality: Inflammation as a Predictor of Mortality
Just how serious is this? The gravity of this situation cannot be overstated. For a long time, we understood inflammation was bad, but we may have underestimated its direct impact on overall mortality. That changed with compelling, large-scale human studies. For instance, a landmark 2022 study published in The Lancet provided chilling evidence. Researchers demonstrated that elevated blood levels of IL-6 and TNF-alpha are independent predictors of all-cause mortality. The hazard ratios—a statistical measure of how much an event is more likely to happen in one group versus another—were comparable to those associated with smoking (Myrberg et al., 2022).
Let that sink in for a moment. Having chronically elevated inflammatory markers in your blood is as dangerous to your long-term survival as being a regular smoker. This finding fundamentally reframes how we must view and treat chronic disease. It elevates systemic inflammation from a contributing factor to a primary therapeutic target. In our clinic, when we run blood panels and see high-sensitivity C-reactive protein (hs-CRP), IL-6, or TNF-alpha creeping up, we don’t see it as a footnote. We see it as a five-alarm fire that requires immediate and decisive action.
The Unifying Mechanism: How One Problem Creates Every Problem
One of the most profound paradigm shifts in modern medicine is the recognition that many distinct chronic diseases are not, in fact, distinct at all. They are different manifestations of the same underlying pathological process. The common denominator, the single unifying mechanism, is chronic low-grade systemic inflammation, a concept often referred to as “inflammaging” (a portmanteau of inflammation and aging).
A pivotal 2023 paper in Nature Medicine articulated this concept beautifully. It showed how inflammaging is the fundamental process driving the development and progression of what we once considered separate conditions: type 2 diabetes, cardiovascular disease, atherosclerosis, dementia, and even many forms of cancer (Pawelec, 2023).
This is a game-changer. It means we can stop playing a frustrating game of whack-a-mole, chasing individual symptoms and diseases, and instead focus on extinguishing the central fire. The CliffsNotes version is this: If you can successfully fix systemic inflammation, you are simultaneously addressing the root cause of essentially every major chronic disease that threatens your health and longevity.
Let’s explore how this destructive program plays out in different organ systems. The insidious nature of systemic inflammation is that it doesn’t give you one problem; it gives you every problem at once, because the same pathological M1 macrophage phenotype runs the same destructive program in every tissue simultaneously.
The Brain on Fire: Neuroinflammation and Cognitive Decline
Nowhere is the devastation of systemic inflammation more apparent or more tragic than in the brain. Your brain has its own resident population of macrophages, specialized immune cells called microglia. In a healthy brain, microglia are caretakers. They prune unused synapses, clear away metabolic waste, and support neuronal health. They are primarily in a quiescent or M2-like state.
However, when the body is steeped in systemic inflammation, or when the brain itself suffers an insult (like a traumatic injury or infection), these microglia can shift into a chronic M1-activated state. Once they flip this switch, they become arguably the most destructive force inside your skull.
Cytokine-Mediated Damage: Chronically activated M1 microglia start spewing out the same inflammatory cytokines we discussed earlier—TNF-alpha, IL-6, and IL-1β. These molecules are directly toxic to neurons. They disrupt synaptic transmission, the very basis of communication between brain cells. This is like having constant static on the line, making it difficult for thoughts to form and memories to be retrieved. This cytokine storm wreaks havoc on the delicate architecture of your neural networks.
Oxidative Stress: M1 microglia are also potent producers of reactive oxygen species (ROS). This creates intense oxidative stress, damaging cellular components like lipids, proteins, and even DNA. The brain is particularly vulnerable to oxidative stress because of its high metabolic rate and its high concentration of fatty acids, which are easily oxidized.
Suppression of Neurogenesis: One of the most critical functions of these inflammatory cytokines is shutting down the production of Brain-Derived Neurotrophic Factor (BDNF). You can think of BDNF as the “growth hormone” for your neurons. It is essential for neuroplasticity—the brain’s ability to learn, adapt, and form new connections. When BDNF levels plummet, the brain’s capacity for repair and growth grinds to a halt. Neurons become more vulnerable to dying off, and the formation of new memories is severely impaired.
From my clinical observations, this process of neuroinflammation is the common soil from which a host of neurological and psychiatric conditions grow. We tend to categorize them as separate diseases with separate causes:
Alzheimer’s Disease
Parkinson’s Disease
Dementia
Chronic Brain Fog
Depression and Anxiety
But the latest research compels us to see them through a new lens. These aren’t fundamentally different brain diseases. At their core, they’re the same neuroinflammatory issue manifesting in different architectural locations within the brain. In Alzheimer’s, the inflammation may be concentrated in the hippocampus and cortex, affecting memory. In Parkinson’s, it targets the dopamine-producing neurons of the substantia nigra, affecting movement. In depression, it disrupts the circuits of the prefrontal cortex and limbic system, affecting mood regulation. The location changes, but the underlying pathological process—chronic microglial M1 activation—is the same.
The Body Under Siege: Inflammation in Other Tissues
This same destructive pattern repeats itself throughout the body.
Adipose (Fat) Tissue: In obesity, adipose tissue becomes a major source of systemic inflammation. Fat cells (adipocytes) enlarge and become stressed, attracting M1 macrophages. This turns your body fat into a veritable factory for inflammatory cytokines, creating a vicious cycle where inflammation promotes fat storage, and that fat, in turn, produces more inflammation. This is a key driver of insulin resistance and type 2 diabetes.
Liver: In the liver, chronic inflammation driven by M1 macrophages (known as Kupffer cells in the liver) leads to non-alcoholic fatty liver disease (NAFLD), which can progress to more serious conditions like steatohepatitis (NASH), cirrhosis, and liver cancer.
Endothelium: The endothelium is the thin layer of cells lining your blood vessels. When it’s chronically inflamed, it becomes “sticky,” promoting atherosclerotic plaque formation. This is the root cause of atherosclerosis, which leads to heart attacks and strokes. The M1 macrophages in the vessel wall engulf oxidized cholesterol, becoming foam cells—the primary component of these dangerous plaques.
Muscles and Joints: In my work as a chiropractor, I see the musculoskeletal effects of inflammation daily. Systemic inflammation can sensitize pain receptors, leading to widespread muscle aches (myalgia) and joint pain (arthralgia). It contributes to cartilage breakdown in conditions like osteoarthritis and is the central driver of inflammatory arthritis like rheumatoid arthritis.
The takeaway is clear and powerful. The patient with diabetes, the patient with heart disease, the patient with dementia, and the patient with chronic pain are not suffering from unrelated problems. They are all suffering from the consequences of a single, dysregulated biological process: a macrophage population stuck in overdrive.
The Immune System’s Misdirection: The Role of the Thymus Gland
So, why does the immune system lose its way? Why does it start attacking the body it’s meant to protect? This brings us to a small but mighty organ that is often overlooked in adult medicine: the thymus gland. Located behind your sternum, between your lungs, the thymus is the master training ground for a critical type of immune cell called the T cell.
Think of the thymus as the elite special forces training academy for your immune system. Its job is to perform rigorous quality control on developing T cells. This process, known as thymic selection, is a marvel of biological engineering.
Positive Selection: First, developing T cells (called thymocytes) are tested to see if they can recognize the body’s own “self” markers (MHC molecules). If they can’t, they are useless, as they won’t be able to recognize infected cells. These cells are eliminated through apoptosis (programmed cell death). This ensures the T cells that “graduate” are functional.
Negative Selection: Next comes the crucial step. The T cells that passed the first test are now screened for their reactivity to the body’s own proteins. T cells that bind too strongly to “self-antigens” are identified as potentially dangerous—they could attack the host’s own tissues. These autoreactive T cells are also rigorously eliminated. This step is critical for establishing self-tolerance, the immune system’s ability to distinguish self from non-self.
Only the T cells that pass both tests—those that can recognize pathogens but do not attack the host tissue—are allowed to “graduate” and enter the circulation as mature, competent T cells.
When Quality Control Fails: The Myth of “Autoimmunity”
What happens when this intricate process of thymic signaling and selection fails? This often occurs as we age (a process called thymic involution) or due to chronic stress, nutritional deficiencies, or environmental toxins. When the thymus isn’t functioning properly, the quality control system breaks down. T cells that should have been eliminated during negative selection are allowed to graduate and circulate throughout the body.
These are rogue T cells, programmed to attack your own tissues. One might start attacking the synovial lining of the joints, leading to rheumatoid arthritis. Another might target the myelin sheath that insulates nerves, causing multiple sclerosis. Others might attack the thyroid gland (Hashimoto’s thyroiditis) or even components of your own DNA (lupus).
This is the basis of what we call autoimmune disease. However, I want to propose a semantic but important shift in perspective. The term “autoimmunity” suggests the immune system has gone rogue of its own accord, that it is attacking the self for no reason. I believe a more accurate term is immune misdirection. The system isn’t inherently faulty; its education was. It’s not a suicidal system; it’s a miseducated one. There is no such thing as “autoimmunity” in the sense of a system designed to attack itself. There is only a loss of self-tolerance due to a failure in the upstream regulatory and training mechanisms, primarily in the thymus and in the balance of regulatory T cells (Tregs).
The Downstream Fallacy: Why Our Current Approach Is Failing
For decades, our medical system has been built around managing the downstream consequences of this immune misdirection and systemic inflammation. We have developed a massive, multi-hundred-billion-dollar industry focused on symptom suppression.
Consider the blockbuster drugs of our time:
Statins: Prescribed to lower cholesterol, a downstream marker of the inflammation-driven process of atherosclerosis.
Metformin: Prescribed to manage blood sugar, a downstream consequence of the inflammation-driven process of insulin resistance.
SSRIs (Selective Serotonin Reuptake Inhibitors): Prescribed to manage depression, a downstream symptom of the inflammation-driven process of neuroinflammation.
Biologics (e.g., TNF-alpha inhibitors): Prescribed to block a single inflammatory cytokine, a downstream product of the upstream macrophage M1 activation.
While these medications can be life-saving in acute situations and can provide necessary relief, they are all sold as solutions to different symptoms of the same fundamental problem. They are patching the holes in the dam without ever addressing the immense pressure of the water building up behind it. They don’t fix the root cause. They don’t re-educate the immune system. They don’t shift macrophages from M1 destruction to M2 repair.
Unlocking the Secrets of Inflammation: Integrative Medicine Approach- Video
Restoring Balance: The Integrative Approach to Healing
This is where our integrative model at Injury Medical Clinic truly shines. By combining the diagnostic acumen of Dr. Cardenas’s internal medicine background with my expertise in functional medicine and chiropractic care, we can address the root cause. Our goal is not just to manage symptoms, but to identify and correct the underlying dysregulation driving the inflammatory process in the first place. We ask why the immune system is out of balance and then use a combination of therapies to restore that balance.
Thymosin Alpha-1: An Upstream Regulator
One exciting frontier in functional and regenerative medicine is the use of signaling molecules called peptides. These are short chains of amino acids that act as precise communicators in the body. One such peptide, Thymosin Alpha-1, holds immense promise for correcting the immune misdirection we’ve been discussing.
Thymosin Alpha-1 is a naturally occurring peptide produced by the thymus gland. It is one of the primary signals the thymus uses to orchestrate T cell maturation and function. In essence, it acts as an “immune modulator,” helping to restore balance to a dysregulated system. It doesn’t crudely suppress the immune system, nor does it blindly stimulate it. It helps it function more intelligently.
Here’s how it works at a cellular level, going upstream to fix the core problem:
Restores Regulatory Circuitry: Thymosin Alpha-1 promotes the development and function of Regulatory T cells (Tregs). Tregs are the “peacekeepers” of the immune system. Their job is to suppress excessive immune responses and prevent the activation of autoreactive T cells. By bolstering the Treg population, Thymosin Alpha-1 helps to re-establish self-tolerance and quell the misdirected immune attacks that characterize “autoimmune” conditions.
Shifts Macrophage Polarization: Critically, Thymosin Alpha-1 has been shown to influence macrophage behavior. It helps to shift macrophages away from the destructive M1 phenotype and towards the reparative M2 phenotype. This directly counteracts the central pathology of systemic inflammation. It helps turn off the “burn it all down” signal and turn on the “clean it all up” signal.
Shuts Down the Inflammatory Loop: By promoting Treg function and encouraging the M1-to-M2 shift, Thymosin Alpha-1 helps to shut down the self-perpetuating inflammatory loop that is slowly killing your biology. It calms the cytokine storm at its source, rather than just trying to block one of its downstream products.
Using tools like Thymosin Alpha-1, under the careful medical supervision of Dr. Cardenas, shows how we apply these advanced biological concepts in a clinical setting. It’s about restoring the body’s own innate regulatory systems. The profound truth is this: You don’t have ten different diseases; you have one dysregulated biology that is producing ten different symptoms. Fix the regulation, and you begin to fix everything.
The Role of Integrative Chiropractic Care in Quelling Inflammation
Now, you might be wondering, “This is fascinating immunology, Dr. Jimenez, but you’re a Doctor of Chiropractic. How does adjusting the spine fit into all of this?” This is a crucial question, and the answer lies at the very heart of the chiropractic principle: the intimate connection between the spine, the nervous system, and overall systemic health.
The nervous system is the body’s master control system. It communicates with and regulates every other system, including the immune system. The spine, in turn, is the protective armor and structural conduit for a huge portion of this system, namely the spinal cord and the nerve roots that exit to serve the entire body. When the spine has biomechanical faults—what we call vertebral subluxations—it can create both structural and neurological stress.
This stress is not just a localized mechanical issue. It acts as a potent, chronic, low-grade stressor that contributes to the body’s total inflammatory burden. Here’s how integrative chiropractic care fits into the treatment of systemic inflammation:
Reducing Nociceptive Input and the Stress Response: Misaligned vertebrae or dysfunctional spinal joints can bombard the central nervous system with aberrant signals, a phenomenon known as nociceptive input. Even if it’s below the threshold of conscious pain, the brain interprets this constant “neural noise” as a threat. This activates the body’s primary stress response axis, the Hypothalamic-Pituitary-Adrenal (HPA) axis. Chronic HPA axis activation initially elevates cortisol levels, but over time can dysregulate the system. Chronic stress, whether it’s emotional, chemical, or, in this case, physical/neurological, is a powerful driver of M1 macrophage activation and systemic inflammation (Morey et al., 2015). By performing precise chiropractic adjustments, we aim to restore normal joint mechanics, reduce nociceptive input, and thereby turn down this source of neurological stress. This helps to calm the HPA axis and lower a key contributor to the body’s inflammatory state.
Modulating Autonomic Nervous System Balance: The nervous system has two main branches that control our physiology: the sympathetic nervous system (“fight or flight“) and the parasympathetic nervous system (“rest and digest“). The sympathetic system is generally pro-inflammatory (it needs to be to fight off a threat), while the parasympathetic system, particularly via the vagus nerve, is profoundly anti-inflammatory. This is known as the “inflammatory reflex” (Tracey, 2002). Many people in our modern, stressed-out world are stuck in a state of sympathetic dominance. Spinal dysfunction can contribute significantly to this imbalance. My clinical experience, supported by a growing body of research, shows that chiropractic adjustments, particularly to the upper cervical spine and sacrum where vagal tone is heavily influenced, can help shift the autonomic balance away from sympathetic dominance and towards a more parasympathetic state. By enhancing vagal tone, we are directly activating the body’s most powerful innate anti-inflammatory pathway, encouraging the M1-to-M2 macrophage shift naturally.
Improving Biomechanics and Reducing Tissue Strain: On a more direct level, poor posture and spinal alignment create chronic mechanical strain on muscles, ligaments, and joints. This chronic micro-trauma itself is a source of localized inflammation, which can contribute to the overall systemic inflammatory load. As a chiropractor, my job is to analyze and correct these biomechanical faults. By improving posture, restoring spinal curves, and ensuring joints move properly, we reduce constant physical stress on the body’s tissues, removing another source of inflammatory signaling.
A Gateway to Holistic Lifestyle Change: In our clinic, a chiropractic adjustment is rarely a standalone treatment. It serves as an entry point to a broader conversation about health. When a patient feels relief from pain and improved mobility, they become more empowered and motivated to engage in other healthy behaviors. An adjustment can be the catalyst that allows a patient to start an exercise program, which is itself a powerful anti-inflammatory modality. It opens the door for me, as a functional medicine practitioner, to discuss anti-inflammatory nutrition, stress management techniques, and sleep hygiene—all critical for quenching the fire of systemic inflammation.
Under Dr. Cardenas’s comprehensive care model, we ensure chiropractic interventions fit the individual’s full medical picture. For example, for a patient with severe osteoporosis or an inflammatory arthritic flare-up, we would modify our techniques to be gentle and safe, always prioritizing the patient’s well-being within the context of their medical diagnosis. This integrated approach allows us to use chiropractic care as a powerful tool to reduce neurological and physical stress, balance the autonomic nervous system, and help guide the body back toward a state of ease and repair, complementing the medical and functional medicine strategies we employ.
Conclusion: A New Blueprint for Health
We stand at a thrilling and hopeful crossroads in medicine. The old model of naming a disease based on its symptomatic location and prescribing a drug to manage that symptom is giving way to a more sophisticated, root-cause-based approach. The science is clear: the smoldering fire of chronic, low-grade systemic inflammation is the common soil from which nearly all chronic diseases of aging grow. The perpetual activation of M1 macrophages, the failure of immune-regulatory training in the thymus, and the resulting cytokine storm are not separate issues but interconnected components of a single, dysregulated system.
The path forward is not to invent a dozen new drugs to block a dozen different cytokines. The path forward is to ask why the system is dysregulated and to use intelligent, integrative strategies to restore its natural balance. This involves:
Identifying and removing the triggers of inflammation through functional medicine testing and lifestyle modification (addressing diet, toxins, infections, and stress).
Modulating the immune system with targeted therapies like peptides, nutrients, and botanicals that encourage a shift from M1 destruction to M2 repair.
Restoring neurological and structural integrity through integrative chiropractic care to reduce physical stress and balance the autonomic nervous system.
Ensuring medical safety and oversight through the wisdom and experience of collaborative physicians like Dr. Cardenas.
You do not have to be a passive victim of your diagnosis. You don’t have ten different diseases. You have one biology that has lost its regulatory balance. By working with an integrated team that understands this fundamental principle, you can go upstream. You can fix the regulation. And when you fix the regulation, you can begin to fix everything.
References
Morey, J. N., Boggero, I. A., Scott, A. B., & Segerstrom, S. C. (2015). Current directions in stress and human immune function. Current Opinion in Psychology, 5, 13–17. https://doi.org/10.1016/j.copsyc.2015.03.007
Myrberg, I. H., Johansson, J., Johansson, F., Ahlqvist, E., & Melander, O. (2022). Established and novel inflammatory markers as predictors of all-cause and cause-specific mortality. The Lancet Regional Health – Europe, 19, 100438. https://doi.org/10.1016/j.lanepe.2022.100438
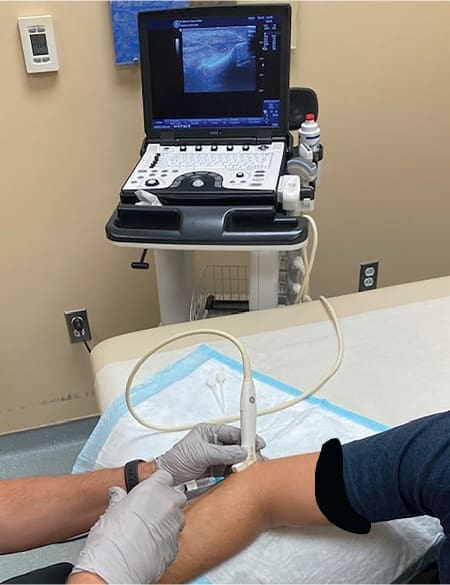
This educational post explores ultrasound-guided hydrodissection, an advanced interventional technique used to address radial nerve entrapment at the entrance of the radial tunnel — a condition frequently misdiagnosed as lateral epicondylitis. Drawing from clinical demonstrations by leading practitioners in musculoskeletal ultrasound, I present the physiological underpinnings of radial tunnel syndrome, the rationale for perineural hydrodissection, and how integrative chiropractic care fits within a multidisciplinary treatment framework. At Injury Medical Clinic PA (also known as Mission Plaza Injury Medical Clinic) in El Paso, Texas, my colleague Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine (NPI #1164426749, Texas MD License #J2933), serves as Medical Director and Collaborative Physician, providing over 40 years of internal medicine expertise alongside my chiropractic and functional medicine practice. Together, we outline how cutting-edge procedural techniques, medical oversight, and conservative rehabilitative care converge to deliver superior patient outcomes for complex nerve entrapment conditions.
Understanding Radial Tunnel Syndrome: Why Diagnosis Is So Often Missed
One of the most clinically underrecognized conditions in musculoskeletal medicine is radial tunnel syndrome (RTS) — a compressive neuropathy of the deep branch of the radial nerve as it enters the radial tunnel, a fibromuscular passage located just distal to the lateral epicondyle. As a clinician who has evaluated countless patients presenting with lateral elbow pain, I can tell you firsthand that this condition is routinely confused with lateral epicondylitis, commonly known as “tennis elbow.”
The key distinguishing features are critical:
Lateral epicondylitis presents with point tenderness directly over the lateral epicondyle
Radial tunnel syndrome typically produces pain that is 3–4 cm distal to the lateral epicondyle, over the radial tunnel itself
Patients with RTS often describe a dull, burning, aching quality to the pain, frequently worsened by pronation and supination of the forearm
The pain may radiate into the dorsum of the forearm, consistent with the sensory distribution of the posterior interosseous nerve (PIN)
This distinction matters profoundly because the treatment approach is entirely different. Injecting a corticosteroid at the lateral epicondyle — the standard intervention for tennis elbow — will do nothing to relieve a nerve entrapment occurring further distally. When six months or more of conservative treatment have failed to produce relief, it becomes necessary to think deeper — both anatomically and clinically.
The Anatomy Behind Radial Nerve Entrapment at the Arcade of Frohse
To fully appreciate why hydrodissection works, one must first understand the precise anatomy involved. The radial nerve, after crossing the lateral aspect of the elbow, divides into two branches:
The superficial branch (purely sensory), which continues distally along the radial side of the forearm
The deep branch (motor and sensory), which dives into the radial tunnel and passes beneath the arcade of Frohse — a fibrous arch at the proximal edge of the supinator muscle
The arcade of Frohse is the most common site of radial nerve compression. This fibrous band can tighten with repetitive forearm rotation, direct compression, or inflammatory changes in surrounding soft tissue. As the nerve becomes entrapped:
Perineural fibrosis develops, restricting the nerve’s normal gliding motion
Ischemic changes in the nerve’s intrinsic blood supply reduce conduction velocity
Mechanosensitivity increases, producing pain with even minor movements involving pronation or supination
Chronic inflammation leads to adhesion formation between the nerve sheath and surrounding fascial planes
This physiological cascade explains why oral anti-inflammatories and physical therapy alone are often insufficient after months of symptomatic progression. The nerve is, in effect, tethered — and it needs to be released.
What Is Ultrasound-Guided Hydrodissection and Why Is It Used
Hydrodissection is a minimally invasive procedure in which fluid is precisely injected around a peripheral nerve to mechanically separate it from surrounding adhesions, scar tissue, or compressive structures. The term itself describes the mechanism: using the hydraulic force of injected fluid to dissect soft tissue planes without the trauma of surgical incision.
In the context of radial nerve entrapment, the technique involves:
Guiding a 25-gauge needle under real-time ultrasound visualization (using a high-frequency linear probe)
Approaching the deep branch of the radial nerve in a short-axis, in-plane view — meaning the needle is visible on the ultrasound screen along its entire length
Injecting a solution — typically lidocaine, in some cases combined with a corticosteroid — perineural (around, not inside) the nerve
Creating what is clinically referred to as a “halo effect”: the fluid surrounds the nerve circumferentially, lifting adhesions and restoring the nerve’s natural gliding motion within its tissue bed
The critical safety principle is perineural, not intraneural injection. Injecting fluid directly into the nerve (intraneural) risks serious nerve damage, including axonal disruption and permanent deficit. The goal is always to deposit fluid adjacent to the epineurium — the outermost connective tissue sheath — thereby creating separation between the nerve and surrounding structures while leaving the nerve itself fully intact.
The use of lidocaine serves a dual purpose:
Diagnostic confirmation: If a prior diagnostic injection of lidocaine at the radial nerve produces measurable pain relief, this validates the nerve as the pain generator — as was precisely the case with the patient discussed in this post
Therapeutic hydrodissection: Lidocaine’s volume, when injected incrementally and skillfully around the nerve, provides the hydraulic separation needed to restore normal nerve mobility
Adding a corticosteroid to the hydrodissection solution targets persistent perineural inflammation, reducing the inflammatory milieu that contributes to ongoing neural sensitization and adhesion reformation.
Why This Is Considered an Advanced Technique
I want to be unequivocally clear: hydrodissection is not a technique to be read about and immediately attempted. The skill required involves:
Mastery of sonoanatomy: Identifying the deep branch of the radial nerve in real time as it passes through the brachioradialis, alongside the neurovascular bundle, and just proximal to the arcade of Frohse, requires dedicated ultrasound training
Precise needle control: The movements involved are described as “very small and subtle.” A millimeter of deviation at this depth can mean the difference between a perineural and an intraneural injection
Recognition of real-time landmarks: The practitioner must continuously identify the brachioradialis, supinator muscle, radius, and the nerve itself as the needle advances, adjusting trajectory in real time
Controlled fluid pulsing: Rather than a single bolus injection, the fluid is delivered in small, deliberate pulses to progressively expand the perineural space, generating the halo effect while monitoring nerve displacement on screen
A muscle twitch may be observed as the needle approaches the nerve — a sign of proximity that requires the practitioner to recognize and respond to immediately. This level of procedural refinement demands supervised, hands-on training under experienced guidance.
Integrative Chiropractic Care and Its Role in Radial Nerve Recovery
While hydrodissection directly addresses the entrapment at the radial tunnel, integrative chiropractic care plays an essential role in the broader clinical picture. At my practice, I approach radial nerve entrapment not as an isolated peripheral problem but as part of a regional biomechanical and neurological pattern that must be addressed comprehensively.
Chiropractic contributions to radial nerve recovery include:
Cervical spine assessment: The radial nerve originates from the C5–C8 nerve roots. Cervical segmental dysfunction — particularly at C6 and C7 — can produce a double crush phenomenon, in which proximal neural compromise reduces the nerve’s capacity to tolerate distal entrapment. Chiropractic spinal manipulation directed at dysfunctional cervical segments helps restore normal neural conduction and reduces the overall compressive burden on the nerve
Elbow and forearm joint mobilization: Restoring full radioulnar joint mechanics and reducing capsular tightness decreases mechanical stress on the radial tunnel
Soft tissue therapy: Targeted myofascial release to the brachioradialis, supinator, and extensor mass helps reduce the external compressive forces perpetuating nerve entrapment
Rehabilitation exercise prescription: Progressive neuromuscular re-education exercises — designed to restore painless pronation and supination — are essential to sustaining the benefits achieved through hydrodissection
Postural and ergonomic correction: Many cases of radial tunnel syndrome are driven or perpetuated by occupational postures. Chiropractic rehabilitation includes functional movement analysis and individualized ergonomic modification
Multidisciplinary Care at Injury Medical Clinic PA: Dr. Cardenas and Dr. Jimenez
The clinical model I operate within at Injury Medical Clinic PA in El Paso, Texas exemplifies the best of multidisciplinary integrative care. Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine (NPI #1164426749, Texas MD License #J2933), brings over 40 years of internal medicine expertise to our collaborative practice. As Medical Director and Collaborative Physician, Dr. Cardenas provides:
Comprehensive medical evaluation and co-management for patients with complex comorbidities
Pharmacological oversight, including medication review for patients undergoing procedural interventions
Internal medicine consultation for systemic contributors to musculoskeletal and neurological conditions — including metabolic, inflammatory, and autoimmune factors that can predispose patients to peripheral neuropathies
Medical direction ensuring all clinical protocols meet the highest standards of patient safety and evidence-based practice
This collaboration between chiropractic functional medicine (my domain) and internal medicine (Dr. Cardenas’s domain) means that patients presenting with conditions like radial tunnel syndrome receive:
A thorough systemic workup when indicated
Coordinated procedural and rehabilitative planning
Functional medicine assessments examining nutritional, metabolic, and inflammatory contributors to nerve health
Personal injury care and documentation for patients involved in accident-related musculoskeletal injuries
Evidence-Based Support for Hydrodissection in Peripheral Nerve Entrapment
The growing body of literature supporting ultrasound-guided hydrodissection is compelling. Research consistently demonstrates that perineural injection under ultrasound guidance is both safer and more effective than landmark-based injection for peripheral nerve entrapment syndromes (Wu et al., 2017). Studies examining hydrodissection for carpal tunnel syndrome, cubital tunnel syndrome, and posterior interosseous nerve entrapment have reported significant improvements in pain scores and functional outcomes (Mulvaney, 2011; Cass, 2016).
The 5% dextrose in water (D5W) solution — a popular hydrodissection medium in non-corticosteroid protocols — has been shown to reduce mechanosensitivity by competitively blocking TRPV1 nociceptors at the neural membrane, providing an additional physiological mechanism of pain relief beyond simple mechanical separation (Lyftogt, 2007). When lidocaine is used, as described in this case, the immediate anesthetic effect confirms nerve involvement while the hydraulic dissection restores gliding mechanics.
Find out how regenerative orthopedics for chronic tendinopathy can transform your recovery journey and restore functional movement.
Abstract
Tendinopathy represents one of the most common and clinically challenging musculoskeletal conditions encountered in integrative and regenerative medicine practice. Whether it presents as lateral epicondylitis (tennis elbow), patellar tendinopathy, Achilles tendinopathy, or rotator cuff degeneration, the underlying pathology shares a consistent theme: a failed healing response within tendon tissue that transitions from an acute inflammatory state into a chronic degenerative process known as tendinosis. This educational post explores one of the most evidence-informed, minimally invasive interventional techniques available to clinicians today — needle fenestration — and its powerful combination with prolotherapy using dextrose to stimulate tendon regeneration from within.
Drawing from the clinical expertise of Dr. Fran O’Connor, a recognized authority in ultrasound-guided procedures, and integrated with the multidisciplinary perspective of Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, and Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine and Medical Director at Injury Medical Clinic PA in El Paso, Texas, this post provides a thorough, clinically grounded exploration of the following topics:
The physiological basis of tendinopathy and why tendons fail to heal on their own
The mechanism of action behind needle fenestration and how it converts a chronic degenerative lesion into an acute healing environment
Step-by-step procedural technique for ultrasound-guided needle fenestration, including needle positioning, angle of approach, in-plane visualization, and coverage of the entire tendinopathic zone
The scientific rationale for combining fenestration with prolotherapy (dextrose) and how this synergistic approach amplifies the regenerative response
How orthobiologics such as platelet-rich plasma (PRP) can be incorporated alongside fenestration for more advanced cases
The clinical outcomes reported in peer-reviewed literature, including the number of passes required, how clinicians assess procedural endpoints, and what patients can expect during recovery
How integrative chiropractic care, functional medicine, and medical oversight from an Internal Medicine physician create a comprehensive, whole-patient approach to managing chronic tendinopathy
The unique multidisciplinary model practiced at Injury Medical Clinic PA, where chiropractic expertise, advanced practice nursing, functional medicine, and internal medicine converge to deliver state-of-the-art, evidence-based musculoskeletal care
By the end of this post, readers — whether patients, clinicians, or health professionals — will have a deeply informed understanding of why needle fenestration with prolotherapy has earned its place as a first-line interventional option for chronic tendinopathy, and how it fits within a broader, patient-centered treatment philosophy.
Understanding Tendinopathy: Why Tendons Fail to Heal
The Structure and Function of Healthy Tendons
To appreciate why needle fenestration works, we must first understand the remarkable—and remarkably vulnerable—structure of the tendon itself. Tendons are dense, fibrous connective tissue structures that transmit the mechanical forces generated by muscle contraction to bone, enabling movement and stabilizing joints under load. They are composed primarily of type I collagen, organized in a highly hierarchical structure: individual tropocollagen molecules assemble into collagen fibrils, which bundle into collagen fibers, which in turn form fascicles surrounded by the endotenon, and these fascicles collectively form the tendon body, enclosed by the epitenon and, in some locations, a paratenon or tendon sheath (Maffulli et al., 2023).
The tenocytes — the primary cellular inhabitants of tendon tissue — reside within this extracellular matrix and are responsible for synthesizing, organizing, and maintaining collagen and other matrix proteins. Under normal physiological conditions, tendons are remarkably efficient load-bearing structures. They are designed to store and release elastic energy, acting almost like biological springs that reduce the metabolic cost of movement and protect muscle tissue from sudden overload (Magnusson et al., 2010).
However, this remarkable structural efficiency comes at a cost: tendons are relatively hypovascular tissues. The blood supply to tendon tissue is sparse compared to muscle, bone, or even ligament. This hypovascular nature means that when tendon tissue is damaged — whether by a single acute traumatic event or by the cumulative microtrauma of repetitive loading — the tissue has limited intrinsic capacity to mount an effective healing response (Fenwick et al., 2002). The relative absence of robust vascularity translates directly into reduced oxygen delivery, reduced nutrient availability, reduced cellular migration to the damaged site, and, critically, reduced access to the growth factors and cytokines that orchestrate tissue repair.
The Transition From Tendinitis to Tendinosis: A Critical Distinction
For decades, chronic tendon pain was labeled “tendinitis,” implying that inflammation was the dominant pathological process. This conceptual framework led clinicians to rely heavily on anti-inflammatory interventions: non-steroidal anti-inflammatory drugs (NSAIDs), corticosteroid injections, and rest. While these approaches may provide short-term symptomatic relief, they often fail to produce lasting recovery—and in some cases, particularly with repeated corticosteroid injections, they may impair long-term tendon healing (Coombes et al., 2013; Dean et al., 2014).
This failure became clearer as histopathological research revealed a striking truth: in most cases of chronic tendon pain, there is little or no true inflammatory infiltrate in the tendon tissue. Instead, what clinicians and researchers consistently find is a picture of tendinosis — a degenerative condition characterized by:
Disorganized collagen architecture, with loss of the normal parallel alignment of collagen fibers and replacement by haphazardly arranged, structurally inferior collagen
Increased ground substance (glycosaminoglycans and proteoglycans) between collagen fibers, creating a thickened, edematous appearance
Neovascularization — the ingrowth of new, abnormal blood vessels into areas of tendon tissue that are normally avascular, often accompanied by nerve fibers that appear to contribute to pain signaling
Hypocellularity in some regions, with loss of normal tenocyte morphology and the appearance of rounded, chondrocyte-like cells — a phenomenon sometimes described as chondroid metaplasia
Micro-tears and focal areas of necrosis within the tendon matrix
The near-complete absence of inflammatory cells such as neutrophils or macrophages that would be expected in true “tendinitis” (Khan & Cook, 2000; Maffulli et al., 1998)
This histopathological picture has been given many names in the literature — tendinosis, tendinopathy, degenerative tendinopathy — but the essential message is consistent: the tissue has entered a state of failed healing. The normal repair cascade — inflammation, proliferation, remodeling — has been initiated but has stalled or been disrupted, leaving behind a structurally compromised, biochemically abnormal tendon that is painful, weak, and at risk for partial or complete rupture (Cook & Purdam, 2009).
Why Tendons Get Stuck in This Degenerative State
Understanding why tendons fail to complete the normal healing cycle is essential for understanding why fenestration represents such a logical and elegant therapeutic intervention. Several interacting mechanisms contribute to the persistence of tendinosis:
1. Repetitive Mechanical Loading Without Adequate Recovery
The most common precipitating factor in tendinopathy is repetitive mechanical overload. When a tendon is loaded cyclically — as in running, throwing, typing, or racket sports — microscopic damage accumulates within the collagen matrix. If the rate of damage accumulation exceeds the rate of repair (which itself requires rest, adequate nutrition, and sufficient vascular supply), the tendon progressively degenerates. This is particularly common in tendons already operating at high mechanical loads, such as the patellar tendon in jumping athletes, the Achilles tendon in runners, and the extensor carpi radialis brevis (ECRB) tendon at the lateral epicondyle in racket sport players and manual workers (Magnusson et al., 2010; Rees et al., 2014).
2. The Hypovascular Environment
As noted above, the tendon’s inherently poor blood supply limits delivery of reparative cells (fibroblasts, macrophages), growth factors (TGF-β, PDGF, IGF-1, FGF, VEGF), and nutrients to damaged areas. Paradoxically, the neovascularization that occurs in tendinosis — while initially appearing to represent a reparative response — tends to produce blood vessels that are structurally abnormal and that infiltrate the tendon accompanied by sympathetic and sensory nerve fibers, contributing to the pain experience without adequately restoring normal tissue perfusion and repair capacity (Ohberg et al., 2004).
3. Altered Tenocyte Biology
The tenocytes within a tendinopathic tendon undergo profound changes in their gene expression and synthetic activity. Instead of producing the organized type I collagen characteristic of healthy tendon, they upregulate type III collagen—a weaker, less organized collagen isoform associated with scar formation—as well as abnormal matrix metalloproteinases (MMPs) that degrade the existing matrix without adequate replacement (Riley et al., 2002). The result is a progressive weakening of the tendon’s structural integrity, even in the absence of complete rupture.
4. Neurochemical Sensitization
Chronic tendinopathy is associated with central and peripheral sensitization of the pain system. The neovascular ingrowth mentioned earlier brings with it substance P-positive and CGRP-positive nerve fibers that generate persistent nociceptive signaling. Over time, this leads to central sensitization—a state in which the nervous system becomes hyperresponsive to pain signals, amplifying perceived pain intensity and expanding the area of perceived pain beyond the original tissue lesion (Andersson et al., 2011). This neurological dimension of chronic tendinopathy is one reason purely mechanical or pharmacological interventions often fail: the pain system itself has been remodeled, and effective treatment must address not only the tendon tissue but also the neural and central contributions to pain.
What Is Needle Fenestration? Defining the Technique and Its Purpose
Defining Needle Fenestration in Clinical Practice
Needle fenestration is a minimally invasive, ultrasound-guided procedure in which a needle — typically a 22-gauge or 25-gauge needle — is used to create multiple small punctate incisions or perforations (fenestrations) within a tendon, specifically targeting the area of tendinosis or tendinopathy. The term “fenestration” derives from the Latin fenestra, meaning “window” — and this etymology is clinically apt, because the procedure literally creates small “windows” or openings in the abnormal tendon tissue.
It is critically important to distinguish needle fenestration from other needle-based tendon interventions. Needle fenestration is defined by the deliberate absence of an injectable therapeutic agent — the needle alone, passed repeatedly through the diseased tissue, is the therapeutic instrument. This distinguishes it from:
Corticosteroid injection (anti-inflammatory)
Hyaluronic acid injection (viscosupplementation)
Prolotherapy (injection of an irritant/proliferant solution such as dextrose)
Dry needling (which targets myofascial trigger points in muscle tissue rather than tendinopathic lesions within the tendon itself)
However — and this is a clinically important nuance that will be explored in detail — needle fenestration is very frequently combined with injectable agents, particularly prolotherapy using hypertonic dextrose, because the two approaches have synergistic mechanisms of action. The fenestration disrupts and mechanically stimulates the tissue, while the injected agent provides additional biochemical stimulation of the healing cascade. This combined approach, as demonstrated by Dr. O’Connor and practiced within the multidisciplinary framework at Injury Medical Clinic PA, is a particularly powerful, evidence-informed treatment strategy for chronic tendinopathy.
The Conceptual Foundation: Converting Chronic Degeneration Into Acute Healing
The central therapeutic logic of needle fenestration is both elegant and physiologically grounded: to convert a chronic, stalled degenerative process into an acute healing response. This concept deserves thorough elaboration, because it represents a fundamental paradigm shift in how we think about treating tendinopathy.
In normal tissue healing following injury, there are three well-defined phases:
Phase 1 — Inflammation (Days 1–7):
Damaged tissue releases damage-associated molecular patterns (DAMPs), triggering local vasodilation, increased vascular permeability, and infiltration of inflammatory cells—primarily neutrophils (early) and macrophages (later). These cells remove cellular debris, release pro-inflammatory cytokines (IL-1β, TNF-α, IL-6), and — critically — release a rich repertoire of growth factors including platelet-derived growth factor (PDGF), transforming growth factor-beta (TGF-β), vascular endothelial growth factor (VEGF), fibroblast growth factor (FGF), and insulin-like growth factor-1 (IGF-1). These growth factors serve as the molecular signals that recruit and activate the reparative cells responsible for tissue regeneration.
Phase 2 — Proliferation (Days 4–21):
Activated fibroblasts (and in tendons, tenocytes) migrate to the wound site and begin synthesizing new collagen — initially type III collagen for rapid structural scaffolding, later transitioning to the mechanically superior type I collagen. New blood vessels form (angiogenesis) to supply the metabolically active repair tissue, and the extracellular matrix is progressively remodeled.
Phase 3 — Remodeling (Weeks to Months):
The immature repair tissue is progressively reorganized and strengthened. Type III collagen is replaced by type I collagen, collagen fibers align along lines of mechanical stress, water content decreases, and the tendon’s tensile strength gradually approaches that of normal tissue. This phase requires progressive mechanical loading to guide collagen fiber alignment through mechanotransduction pathways properly.
In tendinosis, this healing cascade has been initiated — the histological evidence of collagen disruption and tenocyte activation confirms that — but it has failed to progress to completion. The tendon is neither acutely inflamed nor fully healed; it is stuck in a chronic, degenerative limbo. As discussed above, this failure may be due to insufficient vascularity, ongoing mechanical overload, altered tenocyte biology, and potential neurochemical sensitization.
Needle fenestration addresses this stalled healing by forcibly reinitiating the healing cascade from the beginning. By passing the needle repeatedly through the tendinopathic tissue, the clinician:
Physically disrupts the abnormal collagen matrix — breaking down the disorganized, inferior collagen and creating a fresh wound environment
Causes local bleeding within the tendon — delivering a concentrated bolus of growth factors from platelet degranulation directly to the site of degeneration
Triggers an acute inflammatory response — reversing the anti-inflammatory, stagnant biochemistry of tendinosis and replacing it with a dynamic, pro-reparative milieu
Disrupts the pathological neovascular ingrowth — the abnormal blood vessel-nerve fiber complexes associated with tendinopathy pain are disrupted by the needle passes, potentially contributing to pain relief through denervation as well as regeneration
Stimulates tenocyte mechanobiology — the mechanical stimulus of needle penetration activates tenocyte mechanoreceptors and signaling pathways (integrin signaling, FAK-ERK cascades) that upregulate the synthesis of organized, type I collagen
The result is that the tendon, previously stuck in a degenerative state, now experiences a genuine acute injury—but one that is precisely targeted, minimally destructive, and strategically designed to initiate the healing cascade that had previously failed.
The Role of Ultrasound Guidance in Needle Fenestration: Why Imaging Is Non-Negotiable
Real-Time Visualization as a Safety and Efficacy Imperative
One of the most important aspects of needle fenestration, as practiced by Dr. O’Connor and integrated into the clinical protocols at Injury Medical Clinic PA, is using diagnostic musculoskeletal ultrasound (MSKUS) to guide the procedure in real time. This is not merely a technical preference—it is a clinical imperative from both safety and efficacy standpoints.
Musculoskeletal ultrasound provides real-time, dynamic, high-resolution imaging of soft tissue structures—tendons, ligaments, muscles, bursae, nerves, and blood vessels—without the radiation exposure of fluoroscopy or the logistical complexity of MRI. Modern high-frequency linear ultrasound transducers (typically operating at 10–18 MHz for superficial structures) can resolve tendon architecture at sub-millimeter resolution, allowing the clinician to:
Identify the precise location, size, and extent of the tendinopathic lesion within the tendon — the hypoechoic (dark on ultrasound), disorganized area that represents tendinosis or tendinopathy.
Visualize the needle in real time as it enters the tendon, ensuring accurate placement within the lesion rather than in surrounding healthy tissue, bursae, or adjacent neurovascular structures.
Monitor the distribution of any injected agent (prolotherapy solution, PRP) to confirm that it is being delivered to the target tissue.
Use color or power Doppler imaging to identify the pathological neovascularization characteristic of tendinopathy. These Doppler-positive regions are particularly important targets for fenestration, as they represent the areas most actively involved in abnormal tendon biology and pain generation.
Assess tissue response during the procedure — as Dr. O’Connor describes, experienced clinicians can perceive a change in the tissue’s resistance to needle advancement as tendinopathy softens during fenestration, and ultrasound confirms the needle’s position throughout this process.
In-Plane Versus Out-of-Plane Needle Visualization
In-plane (long-axis) needle visualization is the strongly preferred approach for tendon fenestration. In the in-plane technique, the needle is inserted parallel to the long axis of the ultrasound transducer, keeping the entire shaft and tip continuously visible on the ultrasound screen throughout the procedure. This is in contrast to the out-of-plane (short-axis) approach, where only the needle tip (appearing as a bright dot) is visible at a single cross-sectional plane.
The superiority of in-plane visualization for tendon fenestration is multifactorial:
Complete needle shaft visibility allows the clinician to confirm at all times that the needle is within the tendon and not in surrounding structures
Safe needle redirection — repeated withdrawal and redirection of the needle (fundamental to the fenestration technique) requires continuous visualization of the needle tip to ensure it remains within the target zone and does not inadvertently advance into adjacent neurovascular bundles.
Verification of tendon coverage — by observing the needle’s position along the long axis of the tendon, the clinician can confirm that the entire length of the tendinopathic lesion is being treated.
Depth control — the in-plane approach provides direct visualization of how deeply the needle has penetrated the tendon, preventing inadvertent penetration through the deep surface of the tendon into underlying structures (such as the radial nerve at the lateral elbow, or the posterior tibial nerve at the medial ankle)
The Sonographic Appearance of Tendinopathy
On ultrasound, healthy tendon tissue appears as a highly echogenic (bright), fibrillar structure with a characteristic parallel linear echo pattern that reflects the organized collagen architecture. When the ultrasound beam strikes these regularly aligned collagen fibers at the correct angle, they produce strong specular reflections that appear as bright, parallel lines — a pattern often described as having a “fibrillar” or “feather-like” appearance.
Tendinopathy disrupts this pattern in characteristic ways:
Hypoechogenicity — areas of tendinopathy appear darker than the surrounding normal tendon, reflecting the loss of organized collagen architecture and the increased water content of the abnormal matrix. The hypoechoic region is the primary target for fenestration.
Tendon thickening — tendinopathic tendons are typically larger in cross-sectional area than contralateral normal tendons, reflecting the accumulation of abnormal matrix material and the reactive cellular response
Loss of fibrillar echotexture — within the tendinopathic zone, the normal parallel linear echo pattern is replaced by disorganized, heterogeneous echogenicity.
Intratendinous calcification — in some cases, areas of calcium hydroxyapatite deposition can be seen as hyperechoic (bright) foci with posterior acoustic shadowing
Neovascularization on Doppler imaging — color or power Doppler interrogation of the tendinopathic zone reveals increased internal blood flow within the tendon, representing the pathological neovascular ingrowth. This “Doppler signal” within the tendon is a sensitive and specific marker of active tendinopathy and correlates with pain severity in many studies (Ohberg et al., 2004)
During the fenestration procedure, the needle appears as a bright (hyperechoic) linear structure on ultrasound — the “reverberation artifact” that Dr. O’Connor describes, caused by the repeated reflection of ultrasound waves between the flat surfaces of the needle. This reverberation artifact makes the needle highly visible and allows precise real-time guidance throughout the procedure.
Step-by-Step Procedural Technique for Ultrasound-Guided Needle Fenestration
Patient Preparation and Positioning
Before the fenestration procedure begins, appropriate patient preparation is essential. This includes:
Informed Consent:
The patient must be thoroughly educated about the nature of the procedure, the expected immediate post-procedure response (soreness and temporary worsening of symptoms, typically lasting 24–72 hours as the intentional acute inflammatory response is established), the expected timeline of improvement, potential complications (infection, tendon weakening, inadvertent injury to adjacent structures), and alternative treatment options. At Injury Medical Clinic PA, this counseling occurs within the context of the patient’s comprehensive treatment plan, developed collaboratively between Dr. Jimenez and Dr. Cardenas.
Patient Positioning:
The patient is positioned to provide both patient comfort and optimal ultrasound access to the target tendon. For lateral epicondylitis (tennis elbow) fenestration, as demonstrated by Dr. O’Connor, the patient is typically seated with the arm resting on a padded armrest, elbow slightly flexed, and the lateral elbow exposed. For other tendons:
Patellar tendon: supine, knee slightly flexed over a bolster
Achilles tendon: prone, ankle in slight dorsiflexion
Rotator cuff tendons: seated, with specific positions varying by tendon (supraspinatus — arm in the “Crass” position; infraspinatus — arm across the chest)
Skin Preparation:
The skin over the target area is thoroughly cleaned with antiseptic solution (chlorhexidine or povidone-iodine) to minimize infection risk. A sterile field is maintained throughout the procedure, with sterile covers applied to the ultrasound transducer.
Local Anesthesia: The Foundation of Patient Comfort
As Dr. O’Connor describes, local anesthesia is administered before the fenestration procedure. In her demonstrated technique, she uses a 27-gauge needle to infiltrate the skin and subcutaneous tissues overlying the target tendon with 1% lidocaine. Several important principles guide this anesthesia step:
Subcutaneous and Peritendinous Anesthesia:
Lidocaine is infiltrated into the skin, subcutaneous tissues, and peritendinous soft tissues, but ideally not directly into the tendon itself. This is because intratendinous lidocaine is potentially cytotoxic to tenocytes in laboratory studies — an effect that could theoretically impair the healing response that fenestration is designed to initiate. By confining the anesthesia to peritendinous tissues, the clinician numbs the pathway the larger fenestration needle will travel, reducing patient discomfort while preserving the cellular biology within the tendon.
Vapor Coolant Spray:
Dr. O’Connor describes using a vapor coolant spray (such as ethyl chloride or fluoroethane) applied to the skin surface immediately before needle insertion. This produces a brief, intense local cooling effect that temporarily reduces skin sensitivity and further minimizes the patient’s perception of needle insertion — a simple but effective technique for patient comfort.
The Rationale for Adequate Anesthesia:
Adequate anesthesia is not merely a patient comfort measure — it is also a procedural quality determinant. A patient who is in significant pain during the procedure will be tense and may involuntarily move, making accurate needle placement under ultrasound guidance more difficult and potentially less safe. Good local anesthesia allows the clinician to perform a thorough, methodical fenestration without rushing, producing better procedural outcomes.
Needle Selection: 22-Gauge vs. 25-Gauge
The choice of needle gauge for fenestration involves a balance between several competing considerations:
Larger needles (22-gauge):
Create larger punctate defects with each pass, potentially stimulating a more robust healing response
Provide greater tactile feedback as the needle traverses different tissue densities (soft tendinopathic tissue vs. firm normal tendon)
Are slightly more visible on ultrasound
May cause more post-procedural discomfort
Smaller needles (25-gauge):
Cause less tissue trauma per pass, potentially reducing post-procedural pain
May be preferred for smaller tendons or when combining with injection of viscous agents (PRP)
Slightly less tactile feedback
In practice, the choice between 22-gauge and 25-gauge is often based on the size of the tendon, the extent of the tendinopathic lesion, the viscosity of any co-injected agent, and clinician preference. For larger tendons with extensive tendinopathy (Achilles, patellar), a 22-gauge needle may be preferred. For smaller tendons (ECRB at the lateral elbow), a 25-gauge needle often provides excellent results.
The Fenestration Sequence: Achieving Complete Coverage
Once the needle has been positioned in-plane with the ultrasound transducer, with the tip confirmed to be within the area of tendinopathy, the fenestration sequence proceeds as follows:
Step 1 — Initial Needle Placement:
Advance the needle in-plane, with continuous ultrasound visualization, until the tip is positioned within the most proximal extent of the tendinopathic zone. Optimize the insertion angle to keep the entire shaft within the imaging plane. For superficial tendons like the ECRB at the lateral elbow, this typically involves a relatively shallow approach angle (approximately 20–40 degrees from horizontal), allowing the needle to traverse a longer path within the tendon rather than dive steeply.
Step 2 — Penetration and Initial Fenestration:
With the needle tip positioned within the tendinopathic zone, the clinician begins fenestration by advancing the needle into the tissue, then partially withdrawing it (without removing it from the tendon or the skin), redirecting it slightly shallower or deeper within the tendon cross-section, and advancing again. This rhythmic advance-withdraw-redirect pattern creates the multiple punctate openings that characterize fenestration.
Step 3 — Systematic Coverage of the Tendinopathic Zone — Long Axis:
By repeatedly advancing, withdrawing, and redirecting the needle at incrementally different depths, the clinician ensures that the entire thickness of the tendinopathic zone — from its superficial to deep extent — is covered. The number of passes required to achieve this depends on the size of the tendinopathic lesion. Still, Dr. O’Connor describes the typical range in the literature as 15 to 50 passes, varying with the magnitude of the tendon abnormality.
Step 4 — Rotating the Transducer to the Short Axis:
After completing fenestration in the long-axis plane, the clinician rotates the ultrasound transducer 90 degrees to obtain a short-axis (cross-sectional) view of the tendon and the needle. This allows assessment of the needle’s position in the medial-lateral dimension — confirming whether the fenestration coverage needs to be extended medially or laterally within the tendon to treat the full width of the tendinopathic lesion. If the lesion extends beyond the initial needle path, reposition the needle medially or laterally as needed.
Step 5 — Procedural Endpoint — The “Soft Tendon” Sign:
One of the most clinically instructive aspects of Dr. O’Connor’s description of the fenestration technique is the “soft tendon” sign as a procedural endpoint. As the needle repeatedly passes through the tendinopathic tissue, many clinicians report a palpable change in the resistance encountered during needle advancement: the initially firm, resilient (or paradoxically, gritty) texture of the tendinopathic tissue progressively softens, becoming less resistant to needle advancement. This tactile change is believed to reflect disruption of the abnormal, disorganized collagen matrix within the tendinopathic zone—the pathological tissue is literally being broken down and remodeled by repeated needle passes. Many experienced practitioners continue fenestration until the entire target zone reaches this softer consistency, then consider the mechanical phase of the procedure complete.
Prolotherapy: The Science and Application of Dextrose as a Regenerative Agent
What Is Prolotherapy?
Prolotherapy — derived from “proliferative therapy” — is a regenerative injection technique in which a proliferant solution is injected into or around damaged connective tissue (tendons, ligaments, joint capsules, entheses) to stimulate the body’s natural healing response. George Hackett, MD, popularized the term in the 1950s, though injection-based therapies for connective tissue disorders date back to the 19th century.
The most widely used proliferant agent in modern prolotherapy practice is hypertonic dextrose (glucose) — the same molecule that circulates in human blood as blood sugar. Depending on the clinical context, dextrose concentrations used in prolotherapy range from approximately 10% to 50%. As Dr. O’Connor describes, she commonly uses 25% or 50% dextrose for tendon prolotherapy.
How Does Dextrose Prolotherapy Stimulate Tendon Healing?
The mechanisms by which hypertonic dextrose stimulates tendon healing are multiple, and understanding them provides important insight into why combining prolotherapy with needle fenestration creates such a powerful synergistic effect:
Mechanism 1 — Osmotic Cell Stress and Growth Factor Release:
When hypertonic dextrose is injected into tissue, the osmotic gradient created by the high-glucose solution causes local cellular osmotic stress. This stress triggers the release of growth factors — including PDGF, TGF-β, FGF, IGF-1, and connective tissue growth factor (CTGF) — from local cells, including tenocytes, fibroblasts, and platelets. These growth factors are molecular signals that drive collagen synthesis, cell proliferation, and matrix remodeling—the core processes of tendon healing (Topol et al., 2011; Reeves & Hassanein, 2000).
Mechanism 2 — Local Irritant Effect and Inflammatory Cascade Initiation:
The injection of hypertonic dextrose into damaged tendon tissue produces a mild, controlled inflammatory response. This local irritant effect recruits the cellular and molecular machinery of the healing cascade to the injection site. This is analogous to the mechanism of the needle fenestration itself, but adds a biochemical stimulus on top of the mechanical stimulus provided by the needle passes. Together, mechanical disruption (fenestration) and biochemical stimulation (dextrose prolotherapy) create a far more potent healing signal than either approach alone.
Emerging evidence suggests that dextrose, as a signaling molecule in its own right, interacts with cellular glucose receptors (GLUT transporters) and activates downstream signaling pathways—including the PI3K-Akt pathway—that promote cell survival, proliferation, and matrix synthesis. This suggests that the healing-stimulatory effects of dextrose are not simply osmotic but also involve direct receptor-mediated cellular signaling (Rabago et al., 2009).
Mechanism 4 — Platelet Activation and Intrinsic PRP Effect:
When dextrose is injected and causes local bleeding (which fenestration also facilitates), platelets aggregate at the injection site and degranulate, releasing their alpha-granule contents—a concentrated soup of growth factors including PDGF, TGF-β1, VEGF, EGF, and PF4. This platelet-derived growth factor release is, in effect, a form of endogenous platelet-rich plasma — the same therapeutic principle exploited by exogenous PRP injections, but generated naturally at the treatment site. Fenestration enhances this effect by ensuring that bleeding occurs throughout the fenestrated zone.
Dextrose Concentration: Clinical Considerations
The concentration of dextrose used in prolotherapy has important clinical implications:
10–15% dextrose: This low concentration is predominantly used for intra-articular and periarticular prolotherapy, targeting joint capsules, ligaments, and entheses. At this concentration, the primary mechanism is receptor-mediated cellular signaling rather than osmotic cellular stress.
25% dextrose: This intermediate concentration, commonly used by Dr. O’Connor, provides a balance between osmotic stimulation and injectability (lower viscosity than 50% solutions), making it suitable for intratendinous applications.
50% dextrose: This high concentration provides the most potent osmotic stimulus and is typically used for larger tendons or more severe tendinopathy. It is often diluted at the syringe with local anesthetic (such as lidocaine) to achieve the target concentration and reduce patient discomfort.
Combining Fenestration With Prolotherapy: The Synergistic Rationale
The combination of needle fenestration with prolotherapy, as demonstrated by Dr. O’Connor in the lateral epicondylitis case, represents more than the sum of its parts. The synergy between these two techniques can be understood at multiple levels:
Structural Level:
Fenestration physically disrupts the pathological collagen matrix of tendinosis, creating channels and spaces within the tendon that facilitate the distribution of the subsequently injected prolotherapy solution throughout the entire tendinopathic zone. Without prior fenestration, the dense, disorganized collagen matrix of tendinosis may resist fluid distribution, limiting contact between the dextrose solution and target cells.
Cellular Level:
Fenestration delivers an acute mechanical stimulus to tenocytes, activating mechanotransduction pathways that prime these cells for a proliferative and synthetic response. Dextrose then delivers a biochemical stimulus that further activates these cells, producing amplified and sustained growth factor release compared with either stimulus alone.
Vascular Level:
Fenestration causes local intratendinous bleeding, delivering platelets and their growth factor cargo directly to the tendinopathic zone. Dextrose injection then provides an additional osmotic and biochemical stimulus to these same platelets, enhancing their degranulation and growth factor release.
Neural Level:
Fenestration may disrupt pathological neovascular nerve ingrowth, reducing the peripheral sensitization that drives chronic tendinopathy pain. In contrast, the anti-nociceptive effects of the subsequent dextrose injection (mediated in part through adenosine receptor activation at local pain fibers) may further reduce pain signaling in the treated area.
Orthobiologics in Tendon Regeneration: Where PRP Fits in the Treatment Algorithm
Platelet-Rich Plasma: Principles and Preparation
Platelet-rich plasma (PRP) represents the most widely studied and clinically established orthobiologic used in tendon regeneration. PRP is prepared from the patient’s own blood through a centrifugation process that concentrates platelets — and therefore the growth factors contained within their alpha granules — to levels significantly above those found in whole blood. The platelet concentration in PRP is typically 3 to 8 times that of normal whole blood, depending on the preparation system used (Marx, 2004).
When PRP is injected into or around a tendinopathic tendon, the concentrated platelets encounter the local tissue environment and degranulate, releasing their growth factor cargo directly into the treatment site. The growth factors most relevant to tendon healing include:
TGF-β1 (Transforming Growth Factor-Beta 1): One of the most potent stimulators of collagen synthesis; also has anti-inflammatory effects in the later phases of healing
VEGF (Vascular Endothelial Growth Factor): Promotes angiogenesis, supporting vascular supply to the healing tendon
EGF (Epidermal Growth Factor): Promotes cell proliferation and differentiation
FGF (Fibroblast Growth Factor): Stimulates fibroblast/tenocyte proliferation and neovascularization
In addition to platelet-derived growth factors, PRP also contains white blood cells (in “leukocyte-rich” PRP preparations) that contribute additional cytokines and antimicrobial factors, and plasma proteins including fibrinogen and fibronectin that serve as scaffolding for cell migration.
PRP vs. Prolotherapy vs. Fenestration Alone: Positioning in the Treatment Algorithm
The question of when to use PRP versus prolotherapy versus fenestration alone is one that practicing clinicians frequently encounter, and the answer involves consideration of multiple clinical factors:
Tendinopathy Severity:
Mild tendinopathy: Isolated needle fenestration (without injection) or fenestration combined with low-concentration dextrose prolotherapy may be sufficient to initiate adequate healing.
Moderate tendinopathy: Fenestration combined with dextrose prolotherapy (25–50%) represents a well-established, cost-effective approach with a strong evidence base.
Severe or recalcitrant tendinopathy: Cases that have failed multiple rounds of conservative management, or that involve large, extensively degenerated tendon segments, may benefit from adding exogenous PRP to the fenestration procedure, providing a more potent and sustained growth factor stimulus.
Patient Factors:
Age: Older patients may have reduced intrinsic healing capacity and may benefit more from the exogenous growth factor stimulus provided by PRP.
Metabolic health: Patients with diabetes mellitus, which impairs multiple aspects of tissue healing, may benefit from PRP’s ability to bypass some of the growth factor deficiencies associated with diabetic tissue biology. This is particularly relevant at Injury Medical Clinic PA, where Dr. Cardenas’s expertise in Internal Medicine includes managing metabolic conditions that directly impact healing.
Prior treatment history: Patients who have undergone multiple corticosteroid injections may have impaired tenocyte biology and may require the more potent regenerative stimulus of PRP.
Practical and Cost Considerations:
PRP preparation requires specialized centrifugation equipment and adds both cost and preparation time to the procedure. Dextrose prolotherapy is significantly less expensive and, when combined with fenestration, has demonstrated clinical outcomes comparable to PRP in several well-designed studies (Coombes et al., 2013; Krogh et al., 2016). At Injury Medical Clinic PA, the selection between prolotherapy and PRP is individualized based on the factors above, within the collaborative decision-making framework shared by Dr. Jimenez and Dr. Cardenas.
Understanding Plantar Fasciitis- Video
The Evidence Base for Needle Fenestration and Prolotherapy in Tendinopathy
Lateral Epicondylitis (Tennis Elbow): The Most Studied Model
Lateral epicondylitis — commonly known as tennis elbow — is the tendinopathy most extensively studied in the context of needle fenestration and prolotherapy, and for good reason. It is among the most prevalent upper extremity conditions in clinical practice, affecting approximately 1–3% of the general population and disproportionately impacting working-age adults in manual, clerical, and sports-related occupations (Walker-Bone et al., 2004). The primary pathological structure is the extensor carpi radialis brevis (ECRB) tendon at its origin on the lateral epicondyle of the humerus.
The ECRB tendon is a relatively small, superficial structure — anatomical characteristics that make it particularly amenable to ultrasound-guided needle fenestration. The tendinopathic zone can be clearly visualized on ultrasound, the needle can be precisely targeted, and the procedure can be performed with a high degree of accuracy and safety.
Key Clinical Studies on Needle Fenestration for Lateral Epicondylitis:
Stenhouse et al. (2013) conducted a randomized controlled trial comparing needle fenestration alone, PRP injection, and whole blood injection for chronic lateral epicondylitis. All three groups demonstrated significant improvement in pain and function over 6 months, with no statistically significant differences between groups. This finding supports the conclusion that the mechanical effect of the needle (fenestration) is itself a primary therapeutic driver, with injectable agents providing additive but not necessarily superior benefit (Stenhouse et al., 2013).
Dong et al. (2016) performed a systematic review and meta-analysis of needle fenestration and injection-based treatments for lateral epicondylitis, concluding that needle fenestration combined with biological agents (PRP or whole blood) produced superior outcomes to fenestration alone for pain reduction, while fenestration alone outperformed corticosteroid injection at medium-term (3–12 month) follow-up — consistent with the well-established finding that corticosteroid injection, while effective in the short term, is associated with worse long-term outcomes than regenerative approaches.
Mishra & Pavelko (2006) published one of the foundational studies on PRP for lateral epicondylitis, demonstrating significant improvements in pain scores in patients treated with PRP injection compared to controls at 8 weeks and 6 months, with a statistically significant benefit for PRP. Importantly, the injection in this study was combined with needle fenestration of the tendon before PRP delivery—a protocol essentially identical to the combined approach described by Dr. O’Connor.
Dextrose Prolotherapy for Tendinopathy: Randomized Controlled Trial Evidence
The evidence base for dextrose prolotherapy in tendinopathy has grown substantially over the past two decades, with well-designed randomized controlled trials demonstrating clinically meaningful and statistically significant benefits across multiple tendon sites:
Rabago et al. (2013) conducted a high-quality randomized controlled trial of dextrose prolotherapy versus saline injection and versus eccentric loading exercise for Achilles tendinopathy. The dextrose prolotherapy group showed significantly greater improvements in pain and function at 12-month follow-up than both control groups—a finding with important clinical implications for managing this often recalcitrant condition.
Yelland et al. (2011) performed a randomized controlled trial of prolotherapy for plantar fasciitis (a condition closely related to Achilles tendinopathy, sharing the common theme of enthesopathy at a high-load tendon/fascia attachment site). Prolotherapy produced significantly better outcomes than saline injection and was comparable to the best available conservative therapies.
Reeves & Hassanein (2000) published a landmark double-blind randomized controlled trial of dextrose prolotherapy for knee osteoarthritis — demonstrating significant improvements in pain, range of motion, and cartilage quality on MRI — which, while not directly addressing tendinopathy, established the foundational biochemical rationale (growth factor stimulation by hypertonic dextrose) that underlies tendon prolotherapy as well.
The Number of Needle Passes: What the Evidence Says
One of the most practically important questions in needle fenestration technique concerns how many needle passes are required for an effective procedure. Dr. O’Connor notes that the literature reports a range of 15 to 50 passes, depending on the size of the tendinopathic lesion.
This variability in reported pass numbers reflects both the heterogeneity of tendinopathic lesion sizes across different tendons and patients and the lack of a universally agreed-upon, evidence-defined “optimal” pass number. Several principles guide clinical decision-making:
Smaller tendinopathic lesions (such as the ECRB in mild-to-moderate lateral epicondylitis) may require only 15–20 passes to achieve complete coverage and the “soft tendon” endpoint.
Larger tendinopathic lesions (such as extensive Achilles or patellar tendinopathy) may require 30–50 or more passes to achieve complete coverage.
The “soft tendon” endpoint — the tactile perception that the fenestrated tissue has softened during needle advancement — is arguably a more clinically meaningful guide to procedural completeness than any arbitrary pass number.
Some clinicians advocate performing serial fenestration sessions (multiple procedures spaced weeks apart) rather than a single high-pass-count session, reasoning that the healing response benefits from multiple cycles of stimulation.
Lateral Epicondylitis: A Deep Dive Into the Target Pathology
Anatomy of the Lateral Elbow and the ECRB Tendon
To fully appreciate the clinical elegance of needle fenestration for lateral epicondylitis, a detailed understanding of the relevant anatomy is essential. The lateral epicondyle of the humerus serves as the common origin for the extensor muscles of the forearm and wrist. The muscles originating here form a conjoined tendon (the common extensor tendon) that attaches to the lateral epicondyle and its adjacent supracondylar ridge.
The extensor carpi radialis brevis (ECRB) is the tendon most consistently implicated in lateral epicondylitis pathology. Its origin lies deep to the extensor carpi radialis longus at the anterolateral aspect of the lateral epicondyle, in proximity to the lateral collateral ligament complex. The ECRB is subjected to particularly high tensile loads during activities requiring simultaneous wrist extension and forearm pronation — exactly the movement pattern involved in the backhand stroke of tennis (hence the colloquial name “tennis elbow”) and in many occupational tasks such as keyboard use, manual assembly work, and tool use.
At its origin, the ECRB tendon is relatively avascular, positioned in an anatomical watershed zone where direct blood supply is limited. This anatomical characteristic helps explain why this tendon is so prone to tendinosis: the combination of high cyclic mechanical loading and poor intrinsic vascularity creates the ideal environment for the failed healing response characteristic of tendinopathy.
The Unique Ultrasound Appearance of ECRB Tendinopathy
On ultrasound, ECRB tendinopathy characteristically appears as:
A hypoechoic region within the deep aspect of the common extensor tendon at or just distal to the lateral epicondyle attachment — exactly the location described by Dr. O’Connor in her demonstration
Tendon thickening at the lateral epicondyle origin, often measurable as an increase in anteroposterior diameter compared to the contralateral side
Loss of normal fibrillar echotexture within the hypoechoic zone
Neovascularization on Doppler imaging within and around the tendinopathic zone — a finding with prognostic significance (higher Doppler signal correlates with more active tendinopathy)
Occasionally, small partial tears appear as anechoic (fluid-filled) clefts within the tendon substance, or intratendinous calcifications appear as hyperechoic foci
This is precisely the hypoechoic region that the clinician targets during ultrasound-guided fenestration, as described by Dr. O’Connor: “you can see up on the ultrasound a needle coming in into this hypoechoic area of tendinopathy.”
Why Conservative Treatments Alone Often Fail for Lateral Epicondylitis
Despite the availability of numerous conservative treatments for lateral epicondylitis — including physical therapy, eccentric exercise, extracorporeal shockwave therapy, bracing, NSAIDs, and corticosteroid injection — a significant proportion of patients (estimated at 10–20% in most epidemiological studies) progress to a chronic, refractory state that persists for more than 6–12 months and fails to respond adequately to these measures. Understanding why helps explain the rationale for interventional approaches like fenestration.
The limitation of corticosteroid injection is particularly instructive. Multiple high-quality randomized controlled trials have confirmed that while corticosteroid injection provides excellent short-term (6–12 week) pain relief for lateral epicondylitis, it is associated with worse long-term outcomes than both conservative management and regenerative injection approaches (Coombes et al., 2013). The likely mechanism for this long-term harm is the well-documented catabolic effect of corticosteroids on connective tissue: corticosteroids inhibit collagen synthesis, suppress tenocyte proliferation, and — at the molecular level — downregulate the expression of key structural genes including type I procollagen, fibronectin, and tenascin-C, all of which are essential for tendon matrix integrity and repair (Dean et al., 2014). Repeated corticosteroid injections compound this damage, progressively weakening the tendon and increasing the risk of partial or complete rupture.
This is the clinical context that makes needle fenestration with prolotherapy such an important addition to the clinician’s toolkit: for patients who have failed conservative management — including physical therapy, bracing, and activity modification — and who are seeking an alternative to corticosteroid injection or surgery, fenestration with prolotherapy offers a regenerative rather than catabolic approach, addressing the underlying pathology rather than suppressing its symptoms.
The Multidisciplinary Framework at Injury Medical Clinic PA: Integrating Chiropractic, Internal Medicine, and Regenerative Therapies
The Clinical Partnership of Dr. Alexander Jimenez and Dr. Maria Guadalupe Cardenas
At Injury Medical Clinic PA (also known as Mission Plaza Injury Medical Clinic) in El Paso, Texas, the clinical management of tendinopathy, musculoskeletal injuries, and related conditions is delivered through a uniquely comprehensive multidisciplinary model that integrates the complementary expertise of two highly qualified clinicians: Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST and Dr. Maria Guadalupe Cardenas, MD (NPI #1164426749, Texas MD License #J2933).
Dr. Maria Guadalupe Cardenas is Board Certified in Internal Medicine and brings over 40 years of experience as an internist to her role as Medical Director and Collaborative Physician at the practice. Her extensive background in internal medicine provides the clinical foundation for:
Comprehensive medical evaluation of patients presenting with musculoskeletal complaints, ensuring that systemic conditions contributing to or complicating tendinopathy (such as diabetes mellitus, inflammatory arthritis, hypothyroidism, metabolic syndrome, and medication side effects) are identified and addressed
Medical co-management of complex patients undergoing interventional procedures, including assessment of bleeding risk, infection risk, and contraindications to specific agents (such as dextrose in poorly controlled diabetic patients)
Pharmacological management of pain, inflammation, and comorbid conditions within the scope of internal medicine
Collaborative physician oversight that satisfies both the clinical and regulatory requirements for a multidisciplinary integrative practice in Texas
Coordination with specialist referrals for patients requiring orthopedic surgery, rheumatology, neurology, or other specialty consultation
The relationship between Dr. Jimenez and Dr. Cardenas exemplifies the multidisciplinary setup increasingly recognized as the gold standard in integrative and injury care: an MD providing medical direction and oversight alongside a chiropractor and advanced practice provider, ensuring that patients receive care that is both medically safe and holistically comprehensive.
Dr. Alexander Jimenez: A Uniquely Qualified Integrative Clinician
Dr. Alexander Jimenez’s clinical qualifications span multiple disciplines, positioning him to deliver the comprehensive, evidence-based care complex musculoskeletal patients require. His credentials — DC (Doctor of Chiropractic), APRN (Advanced Practice Registered Nurse), FNP-BC (Family Nurse Practitioner, Board Certified), CFMP (Certified Functional Medicine Practitioner), IFMCP (Institute for Functional Medicine Certified Practitioner), ATN (Advanced Trained Nurse), CCST (Certified Chiropractic Sports Therapist) — represent an extraordinary breadth of clinical training that directly informs his approach to tendinopathy and musculoskeletal care.
This unique combination of qualifications allows Dr. Jimenez to function as both a structural/mechanical clinician (addressing biomechanical dysfunctions through chiropractic care) and a functional medicine practitioner (addressing the systemic, metabolic, and nutritional factors that influence musculoskeletal healing), while also operating as an advanced practice provider capable of ordering and interpreting diagnostic studies (including musculoskeletal ultrasound), prescribing medications within his scope of practice, and performing or coordinating interventional procedures.
His clinical observations and evidence-based practice philosophy are extensively documented at ChiroMed.com and in his professional profile on LinkedIn, where he consistently emphasizes integrating the latest research evidence with individualized patient care—a philosophy directly reflected in the approach to tendinopathy described in this post.
How Chiropractic Care Integrates With Needle Fenestration and Prolotherapy
The integration of chiropractic care with ultrasound-guided needle fenestration and prolotherapy is not coincidental — it reflects a deep understanding of the biomechanical, neurological, and physiological factors that contribute to tendinopathy and its persistence.
Addressing the Biomechanical Drivers of Tendinopathy:
Virtually all tendinopathies occur in the context of altered biomechanics — patterns of movement, loading, and joint alignment that place excessive or abnormal stress on specific tendon structures. For example:
Lateral epicondylitis is commonly associated with cervicothoracic dysfunction, altered glenohumeral and scapular kinematics, and restricted pronation-supination mobility of the forearm that collectively increase stress at the ECRB origin
Patellar tendinopathy frequently occurs in the context of hip abductor weakness, tibial torsion, or foot pronation abnormalities that increase valgus stress at the knee during loading activities
Achilles tendinopathy is strongly associated with restricted ankle dorsiflexion range of motion, subtalar overpronation, and gastrocnemius-soleus tightness that combine to increase peak Achilles tendon strain
Chiropractic care — through spinal manipulation, joint mobilization, soft tissue techniques, and rehabilitation protocols — directly addresses these biomechanical contributors. Dr. Jimenez’s approach encompasses:
Cervicothoracic and upper thoracic spinal manipulation for patients with lateral epicondylitis, addressing the proximal kinetic chain dysfunctions that increase distal tendon loading
Glenohumeral and acromioclavicular joint mobilization for rotator cuff tendinopathy, restoring normal shoulder kinematics that reduce impingement and tensile loading of the rotator cuff tendons
Lumbopelvic stabilization and hip strengthening for patellar and hamstring tendinopathy, correcting the proximal biomechanical deficiencies that drive excessive knee tendon loading
Ankle mobilization and foot orthotics for Achilles tendinopathy, addressing the distal biomechanical factors of restricted dorsiflexion and subtalar overpronation
Without addressing these underlying biomechanical contributors, even the most skillfully performed fenestration and prolotherapy procedure risks producing only temporary benefit: the healed tendon will be subjected to the same abnormal loading forces that caused the original degeneration, setting the stage for recurrence.
Neurological Effects of Chiropractic Manipulation:
Spinal manipulation — the cornerstone of chiropractic care — has well-documented neurophysiological effects that extend beyond the local joint being treated. High-velocity, low-amplitude (HVLA) spinal manipulation activates mechanoreceptors in the spinal facet joint capsules, paraspinal muscles, and surrounding soft tissues, generating afferent neural input to the spinal cord that:
Inhibits nociceptive transmission at the dorsal horn level (gate control mechanisms)
Modulates the activity of the sympathetic nervous system, reducing peripheral sensitization
Activates descending inhibitory pain control pathways from the brainstem, including the periaqueductal gray (PAG) — raphe nuclei — dorsal horn pathway, which releases endogenous opioids, serotonin, and norepinephrine as pain-suppressing neurotransmitters
For patients with chronic tendinopathy in whom central sensitization has developed—as is common in long-standing lateral epicondylitis, Achilles tendinopathy, or rotator cuff tendinopathy—these neurological effects of chiropractic manipulation are clinically relevant. By modulating the sensitized pain system, manipulation may reduce the patient’s baseline pain level and improve the therapeutic window for interventional procedures like fenestration.
Exercise Rehabilitation and Tendon Loading Programs:
The evidence base for eccentric and heavy slow resistance (HSR) exercise in tendinopathy is robust and well-established. Progressive tendon loading programs — in which the tendon is subjected to controlled, gradually increasing tensile loads in an eccentric (muscle lengthening under load) or isometric pattern — are among the most effective non-invasive treatments for tendinopathy, operating through the mechanotransduction mechanisms discussed earlier. These programs are typically integrated into the rehabilitation component of the multidisciplinary treatment plan at Injury Medical Clinic PA.
However, an important principle governs the sequencing of interventional procedures and exercise rehabilitation:
Following needle fenestration (with or without prolotherapy), the treated tendon requires a brief period of relative rest — typically 48–72 hours of reduced activity — to allow the acute inflammatory response to establish and the early phases of the healing cascade to initiate without excessive mechanical disruption. This is followed by a graduated return to loading, beginning with isometric exercises (which stimulate tenocyte mechanobiology without imposing significant tensile strain) and progressing through isotonic, eccentric, and finally sport- or function-specific loading protocols.
Dr. Jimenez’s expertise in both chiropractic care and rehabilitation science positions him uniquely to supervise this graduated loading protocol, ensuring that the biomechanical and neural contributions to tendinopathy recovery are addressed in concert with the tissue-level healing initiated by the interventional procedure.
Functional Medicine’s Role in Optimizing Tendon Healing: The Systemic Perspective
Why Systemic Factors Matter in Tendinopathy
Tendinopathy is not merely a local tissue problem. While the histopathological changes of tendinosis are located within the tendon itself, the factors that determine whether a tendon heals effectively — or fails to heal and becomes chronically degenerative — are profoundly influenced by the systemic metabolic and physiological environment in which that tendon exists. This is a central insight of functional medicine and underpins the multidisciplinary approach at Injury Medical Clinic PA, rather than single-modality treatment models.
Dr. Jimenez’s certifications as a Certified Functional Medicine Practitioner (CFMP) and Institute for Functional Medicine Certified Practitioner (IFMCP) reflect his deep engagement with these systemic dimensions of musculoskeletal health. In practice, this means that the evaluation and management of tendinopathy patients at Injury Medical Clinic PA extends beyond the tendon itself to assess and address the systemic factors that influence healing capacity.
Metabolic Health and Tendon Biology
Diabetes Mellitus and Insulin Resistance:
There is now a substantial body of evidence linking diabetes mellitus and insulin resistance with impaired tendon biology and increased tendinopathy risk. Mechanisms include:
Advanced glycation end products (AGEs): In chronically hyperglycemic states, glucose reacts non-enzymatically with proteins in a process called glycation, producing AGEs. When AGEs form on collagen molecules within the tendon matrix, they create cross-links between collagen fibers that alter the tendon’s mechanical properties —increasing stiffness and brittleness—and impair tenocytes’ ability to remodel and maintain the matrix (Couppe et al., 2016).
Impaired growth factor signaling: Insulin resistance is associated with reduced sensitivity to IGF-1 and impaired PI3K-Akt signaling in tenocytes, reducing the proliferative and synthetic response to tendon loading and injury.
Oxidative stress: Diabetic metabolic dysregulation generates excessive reactive oxygen species (ROS) that damage tenocyte DNA, impair mitochondrial function, and accelerate tendon matrix degradation.
Microvascular disease: Diabetic microangiopathy further reduces the already limited blood supply to tendon tissue, compounding the vascular insufficiency that predisposes tendons to degeneration.
These mechanisms explain the well-documented clinical observations that patients with diabetes have a significantly higher prevalence of tendinopathy (particularly at the Achilles, rotator cuff, and hand tendons) and a slower, less complete healing response to both conservative and interventional treatments. Dr. Cardenas’s expertise in managing metabolic conditions is therefore directly relevant to optimizing tendon intervention outcomes —optimizing glycemic control before and after fenestration procedures directly improves the tissue environment for healing.
Thyroid Dysfunction:
Hypothyroidism is a frequently overlooked contributor to tendinopathy. Thyroid hormones regulate the metabolism and synthetic activity of tenocytes, and thyroid hormone deficiency is associated with:
Mucinous degeneration of tendons — accumulation of glycosaminoglycans within the tendon matrix that alters its mechanical properties and predisposes to tendinopathy
Impaired collagen synthesis and reduced tenocyte proliferative capacity
Increased susceptibility to tendon thickening, tendinosis, and spontaneous rupture
Routine assessment of TSH, free T3, and free T4 in patients with unexplained or treatment-resistant tendinopathy is therefore a standard component of the functional medicine evaluation at Injury Medical Clinic PA.
Hyperlipidemia and Tendon Xanthomas:
Elevated serum lipids — particularly triglycerides and LDL cholesterol — have been associated with tendinopathy through the mechanism of lipid deposition within tendon tissue (tendon xanthomas), most commonly at the Achilles tendon. These lipid deposits alter the mechanical properties of the tendon matrix and create a hostile local environment for tenocyte function. Moreover, statins — among the most widely prescribed medications for hyperlipidemia — have been associated with statin-induced tendinopathy and tendon rupture through their inhibitory effects on the mevalonate pathway and downstream effects on tenocyte metabolism (Bruckert et al., 2010). Identifying hyperlipidemia and statin use in tendinopathy patients is therefore both diagnostically and pharmacologically important.
Nutritional Factors in Tendon Healing
Vitamin C and Collagen Synthesis:
Vitamin C (ascorbic acid) is an essential cofactor for prolyl hydroxylase and lysyl hydroxylase — the enzymes responsible for the hydroxylation of proline and lysine residues in procollagen chains. This step is essential for forming stable collagen triple helices and the subsequent cross-linking of mature collagen fibers. Without adequate vitamin C, collagen synthesis is impaired, and the resulting collagen is structurally weak and prone to degradation. Clinical studies have demonstrated that perioperative vitamin C supplementation significantly improves tendon and ligament healing outcomes, and the same principle applies to the healing initiated by fenestration procedures (Shaw et al., 2017).
Vitamin D and Musculoskeletal Health:
Vitamin D deficiency — extraordinarily common in the general population, affecting an estimated 40–50% of adults in many regions — has profound effects on musculoskeletal health. Vitamin D receptors (VDR) are expressed in tenocytes, and vitamin D signaling directly influences:
Tenocyte proliferation and differentiation
Type I collagen gene expression
Calcium homeostasis and tendon calcification risk
Immune regulation and inflammatory resolution
Patients with tendinopathy should undergo assessment of serum 25-hydroxyvitamin D levels, with supplementation initiated when levels are below the functional threshold (typically 40–60 ng/mL) to optimize the healing environment for fenestration-initiated repair.
Protein and Collagen-Specific Amino Acids:
Adequate dietary protein intake is fundamental to supporting the collagen synthetic demands of tendon healing. Of particular importance are glycine, proline, and hydroxyproline — the three most abundant amino acids in collagen. Hydrolyzed collagen peptides (collagen supplements) have been shown in clinical trials to increase collagen synthesis in tendons and ligaments when consumed with vitamin C approximately 45–60 minutes before exercise, timed to optimize the delivery of these substrates during the post-exercise anabolic window (Shaw et al., 2017; Dressler et al., 2018).
Omega-3 Fatty Acids:
Omega-3 polyunsaturated fatty acids (EPA and DHA) — primarily from fatty fish and fish oil supplements — have well-documented anti-inflammatory and pro-resolving effects mediated through resolvins, protectins, and maresins — specialized pro-resolving lipid mediators that actively facilitate the resolution of inflammation and promote tissue repair. In the context of tendinopathy treatment, adequate omega-3 status may enhance the quality of the inflammatory resolution phase following fenestration, facilitating a cleaner transition into the proliferative and remodeling phases of healing.
Addressing Psychological Factors: The Mind-Tendon Connection
An often-neglected but clinically important dimension of chronic tendinopathy management is the psychological component. Multiple studies have demonstrated that catastrophizing, anxiety, depression, and fear-avoidance beliefs independently predict poorer outcomes in tendinopathy treatment, through mechanisms including:
Enhanced central sensitization of pain processing
Reduced engagement with rehabilitation programs (due to fear of pain or re-injury)
Dysregulation of the hypothalamic-pituitary-adrenal (HPA) axis and elevated cortisol levels that impair tissue healing
Altered autonomic nervous system activity that affects local tissue perfusion
The integrative approach at Injury Medical Clinic PA incorporates psychological support through pain education (explaining the neurobiological mechanisms of chronic pain to reduce fear and catastrophizing), mindfulness-based stress reduction (MBSR) referrals, and close collaboration with behavioral health professionals when indicated.
Personal Injury Care and Tendinopathy: The Legal and Clinical Interface
Tendinopathy in the Context of Personal Injury
Injury Medical Clinic PA has extensive experience managing tendinopathy and other musculoskeletal conditions in the context of personal injury cases — motor vehicle accidents, workplace injuries, slip-and-fall incidents, and other traumatic events. This creates a unique clinical and medicolegal interface that requires both clinical excellence and meticulous documentation.
In personal injury cases involving tendinopathy, the clinical team must:
Establish Causation:
Determining whether a tendinopathy lesion is causally related to a specific traumatic event — or whether it represents a pre-existing degenerative condition that was aggravated, accelerated, or activated by the injury — requires careful clinical evaluation, diagnostic imaging interpretation (including ultrasound and MRI), and an understanding of the biomechanical forces involved in the injury mechanism. This is an area where Dr. Jimenez’s combined expertise in chiropractic biomechanics, advanced practice nursing, and diagnostic imaging is particularly valuable.
Document the Natural History of Treatment:
Personal injury cases require detailed, contemporaneous documentation of the patient’s clinical presentation, the treatments provided, the patient’s response to treatment, and the degree of permanent impairment (if any) resulting from the injury. The multidisciplinary team at Injury Medical Clinic PA—with Dr. Cardenas providing Internal Medicine oversight and Dr. Jimenez providing chiropractic and functional medicine management—is well positioned to provide this comprehensive documentation.
Coordinate Care Across Disciplines:
Complex personal injury cases frequently require coordination between chiropractic care, physical therapy, interventional procedures, pain management, orthopedic surgery, and psychological support. The multidisciplinary structure of Injury Medical Clinic PA facilitates this coordination, with Dr. Cardenas and Dr. Jimenez collaborating to develop and implement comprehensive care plans that address all dimensions of the patient’s injury.
The Importance of Objective Outcome Measurement
In both clinical and medicolegal contexts, objective outcome measurement is essential. For tendinopathy treated with needle fenestration and prolotherapy, validated outcome tools include:
Visual Analog Scale (VAS) or Numeric Rating Scale (NRS) for pain intensity
DASH (Disabilities of the Arm, Shoulder and Hand) questionnaire for upper extremity function
Victorian Institute of Sport Assessment (VISA) scores — specific questionnaires for Achilles (VISA-A), patellar (VISA-P), and shoulder (VISA-S) tendinopathies
Patient-Rated Tennis Elbow Evaluation (PRTEE) for lateral epicondylitis
Ultrasound tendon thickness and echogenicity measurements — providing objective, imaging-based evidence of structural change in the tendon following treatment
Doppler vascularization scores — quantifying the reduction in pathological neovascularization following treatment
Serial assessment with these tools, integrated with clinical examination findings and ultrasound imaging, provides a robust, objective record of treatment progress that is valuable for both clinical management and medicolegal documentation.
Post-Procedure Care, Rehabilitation, and the Long-Term Management of Tendinopathy
Immediate Post-Procedure Management
Following needle fenestration (with or without prolotherapy), the immediate post-procedure period is characterized by an intentional, controlled acute inflammatory response—the very response the procedure is designed to create. Patients should be counseled to expect:
Pain and Swelling (24–72 Hours):
A significant proportion of patients experience a post-injection flare — a temporary increase in pain and local swelling at the treated site — that peaks at approximately 24–48 hours post-procedure and typically resolves within 72 hours. This is not a complication; it is the expected and desirable manifestation of the acute inflammatory response that initiates the healing cascade. Patients who understand this are far better able to manage their expectations and tolerate the temporary symptom increase without prematurely seeking anti-inflammatory medication.
Avoiding NSAIDs and Corticosteroids:
Following fenestration and prolotherapy, the use of NSAIDs (non-steroidal anti-inflammatory drugs) should be specifically avoided for at least 7–14 days post-procedure. NSAIDs work by inhibiting the cyclooxygenase (COX-1 and COX-2) enzymes responsible for prostaglandin synthesis — but prostaglandins are among the key signaling molecules that initiate and orchestrate the acute inflammatory healing response. By suppressing this response with NSAIDs, the patient would directly counteract the therapeutic mechanism of the fenestration procedure.
For analgesia in the post-procedure period, acetaminophen (paracetamol) is the preferred option, as it provides pain relief through central mechanisms without the prostaglandin-suppressing peripheral effects of NSAIDs. Ice applied to the skin (not directly on the injection site) for the first 24 hours, along with elevation of the treated limb, can also reduce swelling and discomfort.
Activity Restriction:
For the first 48–72 hours following the procedure, the patient should avoid activities that directly load the treated tendon. For lateral epicondylitis, this means avoiding repetitive gripping, wrist extension, and forearm pronation. For Achilles tendinopathy, it means avoiding running and high-impact activities. Light activities of daily living are typically permissible.
The Rehabilitation Program: Building Tendon Capacity After Fenestration
The rehabilitation phase following needle fenestration is, in many respects, as important as the procedure itself. Fenestration initiates the healing cascade, but progressive mechanical loading of the healing tendon—through a carefully supervised rehabilitation program—guides the new collagen matrix to develop optimal mechanical properties.
Weeks 1–2 — Isometric Loading Phase:
Isometric exercises — in which the muscle contracts against resistance without joint movement — are the safest starting point for tendon loading in the early post-procedure period. Isometric contractions generate moderate tensile load on the tendon (sufficient to stimulate tenocyte mechanobiology) without the potentially damaging strain accumulation associated with dynamic loading. Studies have also shown that isometric exercises have analgesic effects in tendinopathy, mediated through cortical inhibition of pain processing—providing additional functional benefit during this early rehabilitation phase (Rio et al., 2015).
For lateral epicondylitis, isometric wrist extension exercises (holding a static wrist extension position against resistance) are the primary exercise of this phase. For Achilles tendinopathy, isometric single-leg calf raises (held for 30–45 seconds) are the standard protocol.
Weeks 3–6 — Isotonic and Eccentric Loading Phase:
As tendon healing progresses—evidenced by reduced pain, improved function, and (when available) improved ultrasound appearance—the rehabilitation program advances to isotonic and eccentric loading protocols. Eccentric exercise — muscle contraction while the muscle is lengthening — generates the highest collagen synthetic stimulus per exercise bout of any loading mode, and has been the most extensively studied loading protocol for tendinopathy rehabilitation (Alfredson et al., 1998; Maffulli et al., 2008).
The classic eccentric protocol for Achilles tendinopathy (the Alfredson protocol) involves performing 3 sets of 15 eccentric calf raises twice daily, 7 days per week, using body weight and gradually increasing load. For patellar tendinopathy, the decline squat eccentric protocol is the standard approach. For lateral epicondylitis, eccentric wrist extension exercises using a dumbbell or resistance band are the cornerstone of the eccentric phase.
Heavy Slow Resistance (HSR) Training:
More recently, heavy slow resistance (HSR) training — in which the tendon is loaded with heavy weights through a full range of motion at a slow, controlled speed — has been shown to be equally or more effective than eccentric-only protocols for tendinopathy rehabilitation (Beyer et al., 2015). HSR training may be preferable for some patients because it is less painful, allows bilateral training (reducing asymmetric loading), and may produce better patient adherence. Dr. Jimenez integrates HSR protocols into his rehabilitation programs when clinically appropriate.
Weeks 7–12 — Sport-Specific and Functional Loading Phase:
As the tendon’s capacity for loading increases, the rehabilitation program progresses to sport-specific or occupational loading activities — running, jumping, throwing, or the specific occupational tasks that precipitated the tendinopathy. This phase is characterized by a progressive increase in load, speed, and complexity, guided by the patient’s symptom response and functional goals.
Return-to-Sport/Activity Criteria:
Return to full sport or occupational activity is guided by objective criteria including:
Pain scores of ≤2/10 during activity (VISA score improvement to >80)
Full, pain-free range of motion at the affected joint
Limb symmetry in strength testing — typically ≥90% of the contralateral side on isokinetic or dynamometric testing
Ultrasound evidence of tendon healing — improvement in echotexture, reduction in hypoechoic area, and reduction in Doppler vascularization
Understanding the Ultrasound Video Demonstration: A Frame-by-Frame Clinical Analysis
What the Fenestration Video Reveals About Technique and Clinical Decision-Making
The clinical video demonstration provided by Dr. O’Connor — of a fenestration prolotherapy procedure for lateral tennis elbow — offers remarkable insight into the practical, real-time execution of the technique described above. Let us explore what this video communicates at a deeper clinical level.
The Vapor Coolant Spray Step
Dr. O’Connor’s instruction to apply the vapor coolant spray — “give me a little free spray right there” — immediately before needle insertion reflects both patient comfort optimization and procedural efficiency. The vapor coolant creates an immediate, brief anesthetic effect at the skin surface that, combined with the previously administered subcutaneous lidocaine, minimizes the patient’s experience of the needle entering the skin. This is particularly important in the lateral elbow region, where the skin overlying the lateral epicondyle is thin and relatively sensitive.
The use of vapor coolant spray is a small but meaningful example of the patient-centered procedural philosophy that characterizes high-quality interventional musculoskeletal practice. Every step of the procedure should be optimized not only for technical accuracy but also for patient experience and comfort.
The Long-Axis In-Plane Visualization
Dr. O’Connor’s statement — “I’m going to be able to pick this up, long axis in plane with my transducer” — emphasizes the fundamental importance of in-plane needle visualization that has been discussed at length above. Her confirmation of this approach before proceeding underscores that in-plane technique is not merely a preference but a clinical standard for ultrasound-guided tendon fenestration.
Advancing, Withdrawing, and Redirecting: The Rhythmic Pattern of Fenestration
The description “you see me here advancing and withdrawing, penetrating that tissue”—captured in the video—vividly depicts the fenestration rhythm central to the technique. This is not a single, static injection — it is a dynamic, iterative process in which the needle is in constant motion, systematically covering the tendinopathic zone through a methodical pattern of advance-withdraw-redirect cycles.
This rhythmic pattern serves multiple purposes simultaneously:
It creates the multiple punctate openings (fenestrations) that give the technique its name
It maintains the needle within the tendon throughout the procedure, preventing the need for multiple skin punctures
It allows the clinician to continuously assess tissue resistance through tactile feedback, using the “soft tendon” sign as a procedural endpoint.
It ensures even distribution of the mechanical stimulus throughout the tendinopathic zone.
The Role of the Second Clinician
The exchange between Dr. O’Connor and the second speaker — “This is extensor tendinopathy… Occasionally, see both medially and laterally underneath this synchondrosis” — reveals an important dimension of the clinical procedure that is easy to overlook: the value of intraprocedural communication and collaboration. The second clinician (presumably a colleague, resident, or trainee) contributes observations that help guide the procedure, including identifying the target anatomy and confirming needle position relative to the lateral epicondyle and adjacent joint structures.
This collaborative, communicative approach to procedure performance—in which all participants on the clinical team actively contribute their observations—is consistent with the multidisciplinary teamwork model that defines care at Injury Medical Clinic PA.
The Prolotherapy Injection: The Final Step
Dr. O’Connor’s closing narration — “And now injecting the prolotherapy. Done. That’s the prolotherapy procedure” — captures the final step of the combined fenestration-prolotherapy sequence: the delivery of the dextrose proliferant solution into the fenestrated tendon. This injection follows directly from the fenestration, using the freshly created channels within the tendon to distribute the dextrose solution throughout the treated zone.
The sequencing — fenestration first, injection second — is deliberate and mechanically logical:
Fenestration creates physical channels within the disorganized tendinopathic matrix, improving the distribution of the subsequently injected dextrose
Fenestration triggers local bleeding, delivering platelets and endogenous growth factors to the target zone before the dextrose is added.
The dextrose injection then provides an additional biochemical stimulus that amplifies the healing response initiated by the fenestration.
The entire combined procedure can typically be completed in 10–15 minutes (exclusive of preparation time), making it practical for routine clinical implementation.
Broader Applications: Fenestration and Prolotherapy Beyond the Lateral Elbow
Achilles Tendinopathy
Achilles tendinopathy — one of the most common and debilitating tendinopathies encountered in active populations — has been among the most extensively studied conditions in the regenerative injection therapy literature. The Achilles tendon is the largest in the body, transmitting forces equivalent to 6–8 times body weight during running, and is therefore subjected to enormous mechanical demands that, in the context of training errors, biomechanical dysfunction, or systemic metabolic abnormalities, can overwhelm the tendon’s adaptive capacity and precipitate tendinosis.
Achilles tendinopathy most commonly presents as either mid-portion tendinopathy (affecting the fusiform body of the tendon approximately 2–6 cm proximal to the calcaneal insertion — the classic “watershed zone” of reduced vascularity) or insertional tendinopathy (affecting the enthesis at the posterior calcaneus, often in association with a Haglund deformity — a posterosuperior calcaneal prominence that causes mechanical impingement on the tendon during dorsiflexion).
For mid-portion Achilles tendinopathy, ultrasound-guided fenestration with or without prolotherapy is a clinically validated, evidence-based treatment option. The procedure is performed with the patient prone, ankle in slight plantarflexion, using an in-plane medial or lateral approach. The hypoechoic tendinopathic zone within the mid-portion of the Achilles — confirmed with Doppler imaging to identify areas of neovascularization — is systematically fenestrated, followed by dextrose prolotherapy delivery.
The Alfredson eccentric loading protocol, performed in conjunction with and following the fenestration procedure, remains the cornerstone of non-surgical Achilles tendinopathy rehabilitation and is integrated into the post-procedure rehabilitation program at Injury Medical Clinic PA.
Patellar Tendinopathy (Jumper’s Knee)
Patellar tendinopathy — colloquially known as “jumper’s knee” — is a particularly challenging condition because it primarily affects young, highly active athletes who are unwilling or unable to accept the prolonged rest that might allow spontaneous healing. The pathological zone is almost invariably at the proximal patellar pole — the attachment of the patellar tendon to the inferior pole of the patella — and represents the same combination of hypovascular enthesis anatomy and high cyclic mechanical loading that characterizes other tendinopathies.
Ultrasound-guided fenestration with prolotherapy for patellar tendinopathy has been studied in both elite athletes and recreational sports participants. The procedure is typically performed with the patient supine, knee slightly flexed over a bolster, using a lateral or medial in-plane approach to the proximal patellar tendon. The hypoechoic, Doppler-positive zone at the proximal patellar pole is systematically fenestrated, with prolotherapy delivered at the conclusion of the fenestration sequence.
The decline squat eccentric protocol and, more recently, isometric quadriceps loading protocols (heavy isometric leg press holds) constitute the rehabilitation cornerstone for patellar tendinopathy and are prescribed and supervised as part of the comprehensive treatment plan.
Rotator Cuff Tendinopathy
Rotator cuff tendinopathy — particularly involving the supraspinatus tendon at its insertion on the greater tuberosity — is the most common cause of shoulder pain in adults and one of the leading causes of work-related disability. The supraspinatus tendon has a well-described “critical zone” of relative avascularity approximately 1 cm proximal to its insertion — precisely where the majority of tendinopathic lesions and partial tears originate.
Ultrasound-guided fenestration with prolotherapy for supraspinatus tendinopathy is an increasingly utilized treatment modality, particularly for patients who have failed conservative management, including physical therapy, NSAID treatment, and subacromial corticosteroid injection. The procedure requires careful ultrasound guidance to navigate the shoulder’s complex anatomy, including the proximity of the subacromial bursa, the biceps tendon, and the acromioclavicular joint. The technique demands a high level of ultrasound guidance proficiency.
The rotator cuff rehabilitation program—emphasizing scapular stabilization, glenohumeral external rotation strengthening, and posterior capsular stretching—is an essential component of post-procedure management and is supervised by Dr. Jimenez as part of the comprehensive chiropractic and rehabilitation care plan.
Plantar Fasciitis and Fasciopathy
While the plantar fascia is technically a fascial structure rather than a tendon, plantar fasciitis (more accurately termed plantar fasciopathy or plantar fascial enthesopathy) shares the same histopathological characteristics of tendinosis — disorganized collagen, myxoid degeneration, absence of acute inflammatory cells — and responds to the same interventional approaches, including fenestration and prolotherapy.
The plantar fascial insertion at the medial calcaneal tubercle is the typical site of pathology, appearing on ultrasound as a thickened, hypoechoic structure at the calcaneal origin with variable Doppler signal. Fenestration with dextrose prolotherapy at this site has been demonstrated in randomized controlled trials (Yelland et al., 2011) to produce significant, sustained improvements in pain and function.
The Future of Tendon Regeneration: Emerging Technologies and Approaches
Bone Marrow Aspirate Concentrate (BMAC)
Bone marrow aspirate concentrate (BMAC) is an emerging orthobiologic that combines the growth factor-rich properties of PRP with the additional presence of mesenchymal stem cells (MSCs)—cells with the capacity to differentiate into tenocytes and other connective tissue cell types. BMAC is harvested from the patient’s posterior iliac crest under ultrasound or fluoroscopic guidance, concentrated by centrifugation, and injected into the tendinopathic zone using ultrasound guidance.
Early clinical data for BMAC in tendinopathy are promising, particularly for partial-thickness rotator cuff tears and severe Achilles tendinopathy, where tissue damage extends beyond pure tendinosis into structural disruption. However, the evidence base is less mature than that for PRP and prolotherapy, and the higher cost and procedural complexity of BMAC limit its current clinical utility to the most severe or refractory cases.
Extracorporeal Shockwave Therapy (ESWT)
Extracorporeal shockwave therapy (ESWT) uses focused acoustic pressure waves to deliver mechanical energy to tendinopathic tissue, stimulating healing through mechanisms similar to fenestration — including disruption of abnormal calcifications, stimulation of local growth factor release, and induction of controlled micro-trauma that initiates the healing cascade. ESWT can be used as a standalone treatment for tendinopathy or as an adjunct to needle fenestration and prolotherapy, potentially amplifying the healing stimulus.
The evidence base for ESWT in tendinopathy is robust, with multiple Level I randomized controlled trials demonstrating significant benefits for calcific rotator cuff tendinopathy (where shockwaves are particularly effective at dispersing calcific deposits), Achilles tendinopathy, patellar tendinopathy, and plantar fasciitis (Mani-Babu et al., 2015; Rompe et al., 2009).
At Injury Medical Clinic PA, ESWT is integrated into the treatment algorithm for tendinopathy patients as a complementary modality, used with needle fenestration, prolotherapy, and a comprehensive chiropractic and rehabilitation program under the collaborative oversight of Dr. Jimenez and Dr. Cardenas.
Autologous Conditioned Serum (ACS) and Cytokine-Based Therapies
Autologous conditioned serum (ACS), also known as Orthokine, is prepared by incubating the patient’s blood with glass beads coated with chromium sulfate, stimulating white blood cells to produce high concentrations of interleukin-1 receptor antagonist (IL-1Ra). This naturally occurring anti-inflammatory cytokine blocks the action of IL-1β, a key driver of inflammatory tissue degradation in tendinopathy and osteoarthritis. The conditioned serum is then harvested, concentrated, and injected into the affected tissue.
While the evidence base for ACS in tendinopathy is still emerging, early results are promising, particularly for conditions with a significant inflammatory component such as acute tendon tears and inflammatory enthesopathies in the context of systemic inflammatory arthritis. The functional medicine perspective at Injury Medical Clinic PA—emphasizing the modulation of systemic inflammatory mediators—aligns well with this targeted, cytokine-based approach.
Ultrasound-guided percutaneous tenotomy — marketed under brand names such as TENEX or FAST (Focused Aspiration of Scar Tissue) — represents a technologically advanced evolution of the needle fenestration concept. These devices use high-frequency ultrasonic energy delivered through a small-gauge needle to simultaneously emulsify, aspirate, and remove abnormal tendinopathic tissue—creating controlled debridement of the diseased tendon without affecting surrounding normal tissue.
The theoretical advantage of ultrasonic tenotomy over manual needle fenestration is the ability to precisely target and remove the pathological tissue rather than simply disrupting it — potentially producing a cleaner wound bed for healing. Early clinical studies are promising, with multiple reports of significant pain reduction and functional improvement at medium-term follow-up. However, the device cost and the specialized training required for proficient use currently limit its widespread adoption.
Integrating Evidence-Based Research With Clinical Practice at Injury Medical Clinic PA
The Research-Clinical Interface
One defining characteristic of care at Injury Medical Clinic PA is the systematic integration of the latest peer-reviewed evidence into clinical practice. Dr. Jimenez’s extensive engagement with the scientific literature — evident through his educational content at ChiroMed.com and his professional publications — ensures that the treatment protocols used at the clinic reflect the best current evidence for each clinical modality.
This evidence-based approach means the clinic’s use of needle fenestration and prolotherapy is not based on anecdotal experience or historical tradition; it is grounded in a rigorous understanding of the physiological mechanisms, supported by data from properly designed randomized controlled trials and systematic reviews, and continuously updated as new evidence emerges.
The collaboration between Dr. Jimenez and Dr. Cardenas ensures that this evidence-based approach encompasses both the musculoskeletal and interventional dimensions (Dr. Jimenez) and the internal medicine and systemic dimensions (Dr. Cardenas) of patient care — a truly comprehensive, whole-patient evidential framework.
The Role of Diagnostic Musculoskeletal Ultrasound in Evidence-Based Practice
The routine use of diagnostic musculoskeletal ultrasound at Injury Medical Clinic PA is itself an evidence-based practice standard. The availability of high-quality ultrasound imaging at the point of care — rather than relying on MRI reports from external radiology practices — provides several clinically important advantages:
Dynamic Assessment:
Ultrasound allows real-time dynamic imaging — the tendon can be assessed during movement, during loading, and during the clinical examination itself. This dynamic capability reveals pathology that static imaging (MRI) may miss, such as dynamic tendon subluxation, dynamic impingement, and subtle partial tears that are only apparent under load.
Guided Interventions:
As discussed in this post, ultrasound guidance transforms fenestration from a “blind” procedure (based on anatomical landmarks alone) into a precisely targeted, real-time-guided intervention—dramatically improving both safety and efficacy.
Serial Monitoring of Treatment Response:
Serial ultrasound assessment — measuring tendon thickness, echotexture, and Doppler vascularization before and after treatment — provides objective, imaging-based documentation of treatment response. This is valuable both for clinical management (guiding decisions about repeat procedures, rehabilitation progression, and return to activity) and for medicolegal documentation in personal injury cases.
Patient Education:
Real-time ultrasound imaging provides a powerful patient education tool — showing the patient their own tendon abnormality on the screen and then demonstrating the needle precisely targeting that abnormality during the procedure dramatically increases patient understanding of their condition and their engagement with the treatment process.
Clinical Outcomes and Patient Expectations: What the Research Tells Us
Timeline of Recovery After Needle Fenestration With Prolotherapy
Patient education about the expected timeline of recovery following needle fenestration with prolotherapy is essential for managing expectations and ensuring adherence to the post-procedure rehabilitation program. The typical recovery timeline is:
Days 1–3: Post-Procedure Flare
As previously discussed, most patients experience a temporary worsening of pain in the first 24–72 hours after the procedure—the desired acute inflammatory response. Reassuring patients that this is expected and part of the therapeutic mechanism is critical for confidence.
Weeks 1–4: Early Healing Phase
Pain gradually subsides toward the patient’s pre-procedure baseline as the acute inflammatory response resolves and the proliferative phase of healing begins. Many patients report a gradual reduction in pain and a sense that the tendon is “feeling different”—perhaps less sharp, less localized, or more tolerable—during this period.
Weeks 4–12: Proliferative and Early Remodeling Phase
The most significant clinical improvements typically occur in this period, as new collagen synthesis and matrix remodeling progress. Most clinical studies that show significant between-group differences in outcomes report their primary findings at 6–12 weeks following intervention.
Months 3–12: Late Remodeling and Return to Full Function
Complete tendon remodeling — with full restoration of mechanical properties and tensile strength — takes months to over a year following any tendon intervention, including fenestration. This extended timeline reflects the slow metabolic turnover of tendon collagen and the gradual nature of matrix reorganization. Patients should understand that while pain and functional improvement often occur relatively quickly, full structural healing is a much longer process, and adherence to the rehabilitation program throughout this period is essential.
Repeat Procedures:
For patients who do not achieve adequate improvement from a single fenestration session, repeat procedures at 4–8 week intervals may be considered. Many clinical protocols involve 3 to 5 sessions spaced 4–6 weeks apart, particularly when combined with prolotherapy. The patient’s clinical response, the ultrasound appearance of the tendon, and the patient’s functional goals guide the decision to repeat procedures.
Factors Predicting Better Outcomes
Research has identified several factors associated with better outcomes following fenestration and prolotherapy:
Shorter symptom duration before intervention — patients with symptoms of less than 6–12 months tend to respond more rapidly and completely than those with chronic, long-standing tendinopathy
Higher pre-procedure Doppler vascularization signal — paradoxically, tendons with more active neovascularization on Doppler imaging (indicating a more “active” tendinopathic process) may respond better to regenerative interventions than tendons with absent Doppler signal (indicating a completely avascular, truly “burned out” lesion)
Younger age and better metabolic health — as discussed in the functional medicine section
Adherence to the post-procedure rehabilitation program — arguably the single most important predictor of long-term outcomes
Absence of psychosocial yellow flags — patients without significant catastrophizing, fear-avoidance, or psychological comorbidity tend to achieve better functional outcomes
Safety Profile and Potential Complications
Needle fenestration with prolotherapy has an excellent safety profile when performed by trained clinicians using ultrasound guidance. Potential complications, though uncommon, include:
Post-procedure pain flare — the most common “complication,” occurring in the majority of patients but representing an expected therapeutic response rather than a true adverse event
Infection — rare when proper sterile technique is used; estimated incidence less than 1 in 10,000 procedures
Tendon weakening and rupture — a theoretical concern with any intratendinous needle procedure; the risk is minimized by avoiding excessive needle passes in a single session, using smaller gauge needles where possible, and implementing appropriate post-procedure activity restrictions. Note that this risk is significantly lower with fenestration/prolotherapy than with corticosteroid injection.
Nerve or vascular injury — rare when procedures are performed under real-time ultrasound guidance; the ability to identify adjacent neurovascular structures and guide the needle away from them is a primary safety advantage of ultrasound-guided technique
Hyperglycemia in diabetic patients — intratendinous dextrose injection may cause transient, mild hyperglycemia in patients with diabetes; Dr. Cardenas’s involvement in the medical oversight of diabetic patients undergoing these procedures ensures that glycemic monitoring is incorporated into the post-procedure care plan
Building a Comprehensive Treatment Plan: The Injury Medical Clinic PA Approach
The Initial Evaluation: Comprehensive History, Physical Examination, and Diagnostic Imaging
At Injury Medical Clinic PA, the management of tendinopathy begins with a comprehensive clinical evaluation that encompasses:
History:
Onset, duration, and temporal pattern of symptoms
Aggravating and alleviating activities
Prior treatments and their outcomes (with particular attention to the number and timing of prior corticosteroid injections)
Occupational and recreational demands
Medical comorbidities (diabetes, thyroid disease, inflammatory arthritis, hyperlipidemia) — assessed by Dr. Cardenas within her Internal Medicine scope
Medications (particularly statins and fluoroquinolone antibiotics, both of which are associated with tendinopathy and tendon rupture risk)
Nutritional and lifestyle factors (assessed through the functional medicine lens of Dr. Jimenez)
Palpation of the tendon and adjacent structures to localize and characterize tenderness
Provocative testing specific to each tendon (e.g., Cozen’s test and Mill’s test for lateral epicondylitis; Thompson test for Achilles integrity; impingement tests for rotator cuff; Windlass test for plantar fascia)
Range of motion assessment of relevant joints
Muscle strength testing — manual muscle testing and dynamometry
Neurological screening — to rule out radiculopathy, peripheral nerve entrapment, or central sensitization as contributors to pain
Postural and gait analysis — to identify proximal and distal biomechanical contributors to tendon loading abnormalities
Diagnostic Imaging:
Musculoskeletal ultrasound — real-time, dynamic assessment of tendon architecture, neovascularization, adjacent bursa, and joint structures; performed by Dr. Jimenez as part of the clinical encounter
MRI — reserved for cases requiring assessment of structures not adequately visualized on ultrasound (e.g., intra-articular pathology, bone marrow edema, nerve pathology) or for pre-surgical planning; ordered and interpreted in collaboration with Dr. Cardenas and radiology consultants
Laboratory studies — ordered by Dr. Cardenas as part of the internal medicine evaluation when systemic contributors to tendinopathy are suspected (CBC, CMP, thyroid panel, lipid panel, HbA1c, vitamin D, inflammatory markers)
The Individualized Treatment Plan: Bringing It All Together
The clinical evaluation culminates in the development of an individualized, multidisciplinary treatment plan that draws on the full spectrum of services available at Injury Medical Clinic PA:
Education — biomechanics of tendinopathy, rationale for chosen treatments, expected timeline, warning signs
Activity modification — temporary reduction of provocative activities while maintaining general fitness and cardiovascular health
Functional medicine assessment and optimization — nutritional support (vitamin C, vitamin D, collagen peptides, omega-3 fatty acids), metabolic optimization (glycemic control, thyroid optimization), elimination of tendon-toxic medications where possible
Chiropractic care — addressing proximal and distal biomechanical contributors to tendon loading, spinal manipulation for neurological modulation of pain, soft tissue therapy
Tier 2 — Interventional Procedures (Moderate to Severe Tendinopathy, or Failure of Tier 1):
Ultrasound-guided needle fenestration — targeting the hypoechoic tendinopathic zone under real-time visualization
Dextrose prolotherapy — delivered following fenestration, 25% or 50% concentration depending on tendon and clinical severity
Extracorporeal shockwave therapy (ESWT) — as adjunct or alternative when available and clinically indicated
Corticosteroid injection — reserved for specific indications (e.g., concurrent inflammatory bursitis, acute inflammatory flare) and used with full awareness of its long-term risks
Tier 3 — Advanced Orthobiologics (Severe or Refractory Tendinopathy):
Platelet-rich plasma (PRP) injection — with or without combined fenestration
Bone marrow aspirate concentrate (BMAC) — for the most severe cases with structural tendon disruption
Surgical referral — coordinated by Dr. Cardenas for cases that have exhausted non-operative options, including orthopedic consultation for open or arthroscopic tendon debridement, repair, or reconstruction
Ongoing Monitoring and Outcomes Assessment
The treatment plan is not static — it is dynamically adjusted based on the patient’s response, measured through serial clinical assessment, validated outcome questionnaires, and repeat musculoskeletal ultrasound. Dr. Cardenas and Dr. Jimenez conduct regular collaborative case reviews to ensure that:
Systemic factors are optimized and adjusted as needed (particularly in patients with metabolic comorbidities)
The rehabilitation program is progressing appropriately and challenges the patient without exceeding their current tissue capacity.
Interventional procedures are repeated when clinically indicated and deferred when the healing trajectory is proceeding well without them.
Emerging complications or red flags are identified early and managed appropriately — including imaging surveillance, laboratory monitoring, and specialist referral when needed.
Conclusion: A New Paradigm for Tendinopathy Care
The clinical approach to tendinopathy described in this educational post represents a fundamental departure from the outdated, symptom-suppression paradigm that has historically dominated — and frequently failed — the management of this common and debilitating condition. By embracing the biology of tendon healing—understanding why tendons fail to heal and designing interventions that address these failures directly—the multidisciplinary team at Injury Medical Clinic PA delivers a qualitatively different, clinically superior approach to care.
Needle fenestration — by mechanically disrupting the chronic degenerative environment of tendinosis and forcibly reinitiating the healing cascade — addresses the core pathophysiological mechanism of tendinopathy at the tissue level. Dextrose prolotherapy amplifies this effect with biochemical stimulation, delivering growth factors and osmotic cellular signals that sustain and enhance the healing response. Ultrasound guidance ensures these interventions are delivered precisely to the target tissue with maximum safety and efficacy.
But the interventional procedure alone — however skillfully performed — is insufficient without the broader clinical context that Injury Medical Clinic PA provides. Th. Jimenez’s chiropractic practice addresses the loading abnormalities that caused the tendinopathy in the first place. The functional medicine framework optimizes the systemic environment for healing — managing metabolic comorbidities, correcting nutritional deficiencies, and modulating systemic inflammation. Dr. Cardenas’s Internal Medicine oversight ensures medical safety, identifies and treats systemic contributors, and coordinates specialist care when needed. The rehabilitation program guides the new collagen matrix to develop optimal mechanical properties through progressive loading.
Together, these elements constitute a comprehensive, patient-centered, evidence-based approach to tendinopathy that offers patients the best available opportunity for a full, lasting recovery — a return not merely to reduced pain, but to full function, restored capacity, and durable musculoskeletal health.
I am proud to be part of the team at Injury Medical Clinic PA that delivers this standard of care, and I am deeply committed to continuing to advance our clinical practice as the science of tendon regeneration evolves. Patients experiencing any of the tendinopathy conditions discussed in this post — whether it is tennis elbow, Achilles pain, patellar tendinopathy, rotator cuff problems, or plantar heel pain — are encouraged to reach out to our clinic for a comprehensive evaluation and to learn whether needle fenestration, prolotherapy, or any of the other interventional and integrative services we offer may be appropriate for their individual situation.
Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST practices at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic), El Paso, Texas, in collaboration with Medical Director Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine (NPI #1164426749, Texas MD License #J2933). Clinical observations and additional educational resources are available atChiroMed.comandLinkedIn.
SEO Tags: needle fenestration, tendinopathy treatment, prolotherapy dextrose, ultrasound-guided tendon injection, lateral epicondylitis treatment, tennis elbow fenestration, tendinosis healing, extensor carpi radialis brevis tendinopathy, platelet-rich plasma tendon, chiropractic tendinopathy care, integrative musculoskeletal medicine, Achilles tendinopathy injection, patellar tendinopathy treatment, rotator cuff tendinopathy, functional medicine tendon healing, Dr. Alex Jimenez El Paso, Injury Medical Clinic PA, prolotherapy El Paso Texas, musculoskeletal ultrasound guidance, orthobiologics tendon regeneration, eccentric exercise tendinopathy, collagen synthesis tendon repair, tendon neovascularization, multidisciplinary injury care El Paso, internal medicine chiropractic collaboration, personal injury tendinopathy, ESWT extracorporeal shockwave, PRP injection tendon, dextrose prolotherapy lateral elbow, evidence-based tendinopathy management
In this educational post, I will guide you through an advanced, highly effective technique for managing chronic tendinopathy known as tendon brisement, or high-volume injection (HVI). Drawing from my clinical experience and the latest evidence-based research, we will explore the physiological mechanisms behind this innovative procedure. I will explain how HVI differs from traditional tendon treatments by focusing on hydrostatically decompressing soft tissues and disrupting the problematic neovessels and neonerves that perpetuate chronic tendon pain. We will examine the step-by-step process of performing an HVI, using the Achilles tendon as a primary example. Furthermore, I will discuss how we integrate this advanced procedure at Injury Medical Clinic PA. Our unique multidisciplinary approach combines my expertise in chiropractic and functional medicine with the invaluable medical oversight of our Medical Director, Dr. Maria Guadalupe Cardenas, MD, to provide comprehensive, patient-centered care for complex musculoskeletal conditions.
As a practitioner with dual credentials in chiropractic and as a board-certified Family Nurse Practitioner, my journey has always been about integrating the best of multiple disciplines to achieve superior patient outcomes. At Injury Medical Clinic PA in El Paso, Texas, this philosophy is the cornerstone of our practice. I am privileged to work alongside Dr. Maria Guadalupe Cardenas, MD, our Medical Director and Collaborative Physician. With over four decades of experience as a board-certified internist, Dr. Cardenas provides essential medical oversight, allowing us to offer a broad spectrum of advanced treatments safely and effectively.
Our model is built on collaboration. Whether we are managing a complex personal injury case, guiding a patient through rehabilitation, or applying functional medicine principles to address root causes of dysfunction, our team approach ensures every patient receives comprehensive care. This integration is particularly vital when we employ advanced procedures like the one we’ll discuss today: tendon brisement, also known as a high-volume injection (HVI). This technique represents a significant leap forward in treating chronic, stubborn tendinopathies, and it perfectly illustrates how integrative care can unlock new possibilities for healing.
Understanding Tendon Brisement: A Paradigm Shift in Tendon Treatment
When we talk about tendon injuries, many people are familiar with terms like fenestration or tenotomy. These procedures involve using a needle to repeatedly puncture the damaged tendon tissue itself, with the goal of stimulating a new, more organized healing response. While effective in certain cases, they don’t always address the full picture of what causes chronic tendon pain.
This is where tendon brisement comes in. It’s a fundamentally different approach. Instead of focusing on the tendon itself, a brisement procedure primarily targets the space around the tendon. Specifically, we target the interface between the tendon and adjacent structures, such as its synovial sheath (tenosynovium) or the nearby fat pad.
The “Why” Behind the Pain: Neovessels and Neonerves
To truly grasp the power of brisement, we must first understand the pathophysiology of chronic tendinopathy. For years, we believed tendon pain was primarily an inflammatory issue (tendinitis). However, modern research, including histopathological studies, has shown that chronic cases are better described as tendinosis—a degenerative condition characterized by disorganized collagen fibers, a lack of inflammatory cells, and, most importantly, the ingrowth of abnormal, tiny blood vessels and nerves. These are known as neovessels and neonerves.
Leading researchers like Alfredson et al. (2000) have demonstrated that these aberrant structures, which often grow into the tendon from adjacent tissues like the fat pad, are a primary source of pain in conditions like Achilles and patellar tendinopathy. The neonerves transmit pain signals, while the neovessels perpetuate a disorganized, failed healing state.
The goal of a tendon brisement or high-volume injection is to physically and hydrostatically disrupt this pathological neurovascular network. We are not just injecting a substance; we are using the volume and pressure of the fluid to mechanically separate adhered tissues and destroy these pain-generating structures.
The High-Volume Injection Procedure: A Step-by-Step Explanation
Let’s walk through how this procedure is performed, using the Achilles tendon as our clinical example. This condition is notoriously difficult to treat, but HVI has shown remarkable promise.
1. Patient Preparation and Initial Assessment
The first step is always a thorough evaluation. The patient is positioned comfortably, typically lying prone for an Achilles procedure, to allow optimal access to the tendon. We then use a high-resolution ultrasound machine with a linear probe to meticulously examine the Achilles tendon in both a longitudinal (long-axis) and transverse (short-axis) view. This diagnostic imaging is crucial for several reasons:
Pinpointing the Pathology: We can identify the exact location and extent of tendon thickening, collagen disorganization, and signs of tendinosis.
Visualizing Neovascularity: Using color or power Doppler ultrasound, we can often directly visualize increased blood flow from neovessels, typically on the anterior aspect of the tendon near Kager’s fat pad.
Planning the Injection: This detailed anatomical map allows us to plan the safest and most effective needle trajectory to target the precise tissue interface.
2. Anesthesia and Needle Placement
Once the target area is identified, we ensure the patient’s comfort. The skin and superficial subcutaneous tissues are anesthetized using a fine-gauge needle (e.g., 25 or 27-gauge) and a local anesthetic like lidocaine. This minimizes any discomfort from the main procedure.
Next, a slightly larger needle (e.g., 21 or 22-gauge) is used for the brisement itself. Under continuous ultrasound guidance, the needle is advanced to the target zone—the space between the anterior border of the Achilles tendon and Kager’s fat pad. Precision is paramount. The goal is to be juxtaposed to the tendon, not inside it.
3. The Hydrodissection and Brisement
This is the core of the procedure. We begin injecting a large volume of fluid. The injectate typically consists of a combination of:
Normal Saline: This makes up the bulk of the volume and provides the hydrostatic force needed for the brisement.
Local Anesthetic (e.g., Lidocaine): This provides immediate pain relief and can also have a therapeutic effect by disrupting nerve signaling.
Corticosteroid (Optional): Some protocols include a small amount of corticosteroid to help modulate the local inflammatory response that may follow the mechanical disruption, although this is debated and often used sparingly (Maffulli & Spiezia, 2017).
As the fluid is injected, we watch the ultrasound screen in real-time. What we see is remarkable. The fluid forcibly separates the tissue planes, creating a distinct, anechoic (black) space. This is the hydrostatic decompression in action. You can literally see the fluid stripping the anterior surface of the tendon away from the fat pad, tearing the delicate neovessels and neonerves that have tethered these structures together.
The volume of fluid used can vary significantly, with literature reporting anywhere from 10 to 100 cc. The injection continues until either the patient feels significant pressure or we feel a marked increase in resistance, indicating the tissue compartment is full.
Visualizing the Mechanism: What We See on Ultrasound
Let’s break down the visuals from a procedure performed by my esteemed colleague, Dr. Knight.
Short-Axis View: Initially, the probe is placed perpendicular to the tendon. The needle is introduced from the side, and we see it as a bright dot on the screen when viewed “out-of-plane.” The initial anesthetic injection begins the process of hydrodissection, gently creating space.
Long-Axis View: The probe is then turned parallel to the tendon fibers. In this view, we can see the needle tracking along the anterior border of the thickened, tendinopathic Achilles.
The “Fluid Wave”: As the high-volume injectate is introduced, we witness the most important part of the procedure. A wave of fluid spreads along the interface. It physically lifts the tendon away from the underlying fat pad. This mechanical stripping action is what accomplishes the brisement, effectively decompressing the area and obliterating the neurovascular ingrowth that drives the pain.
The entire process is a form of mechanical neurolysis and anti-angiogenesis, achieved through hydrostatic pressure rather than a scalpel. This is precision medicine at its finest, guided by real-time imaging.
Integrating Chiropractic Care for Comprehensive Recovery
Performing a high-volume injection is a powerful intervention, but it’s not the end of the story. In my clinical experience, the most successful and lasting outcomes come when these procedures are integrated into a comprehensive rehabilitation framework. This is where the synergy of our multidisciplinary clinic truly shines.
Following an HVI procedure, the patient enters a structured rehabilitation program where chiropractic care plays a pivotal role.
Biomechanical Correction: Chronic tendinopathy rarely exists in a vacuum. It often results from underlying biomechanical faults. As a chiropractor, I focus on identifying and correcting these issues. For Achilles tendinopathy, this may involve:
Spinal and Pelvic Adjustments: Misalignments in the pelvis or lumbar spine can alter the kinetic chain, leading to abnormal gait mechanics and excessive strain on the Achilles tendon. Chiropractic adjustments help restore proper alignment and nerve function from the spine down.
Extremity Adjusting: We assess and correct joint restrictions in the ankle, subtalar joint, and foot. A stiff ankle or foot that overpronates can dramatically increase the load on the Achilles.
Soft Tissue Mobilization: Techniques like Graston or Active Release Technique (ART) can be applied to the calf muscles (gastrocnemius and soleus) and plantar fascia to reduce tension and improve tissue mobility, further offloading the healing tendon.
Guided Loading and Rehabilitation: The period after a brisement procedure is a critical window for healing. The tendon needs to be loaded progressively to stimulate organized collagen remodeling. We guide patients through a specific, evidence-based eccentric loading program, as pioneered by researchers like Alfredson et al. (1998). This involves controlled lengthening of the calf muscles, which has been shown to be highly effective in promoting tendon repair. Our rehabilitation team ensures the exercises are performed with perfect form to maximize benefit and prevent re-injury.
Functional Medicine Support: From my functional medicine perspective, we also address systemic factors that can impair healing. This includes nutritional counseling to ensure the patient has the necessary building blocks for collagen synthesis (e.g., vitamin C, proline, lysine, zinc) and managing systemic inflammation through diet and targeted supplementation.
This integrated model—combining Dr. Cardenas’s medical oversight for the injection, my procedural skills, our shared rehabilitation protocols, and a foundation of chiropractic and functional medicine—creates a powerful therapeutic cascade. We are not just treating the painful tendon; we are treating the whole person and the entire biomechanical system that contributed to the injury in the first place. This is the future of musculoskeletal medicine.
References
Alfredson, H., Pietilä, T., Jonsson, P., & Lorentzon, R. (1998). Heavy-load eccentric calf muscle training for the treatment of chronic Achilles tendinosis. The American Journal of Sports Medicine, 26(3), 360–366. https://doi.org/10.1177/03635465980260030301
Alfredson, H., & Ohberg, L. (2000). Neovascularisation in chronic painful patellar tendinosis–a descriptive study in a prospectively selected group of patients. Knee Surgery, Sports Traumatology, Arthroscopy, 8(4), 232-234. Note: This reference discusses patellar tendinosis, but the principle of neovascularization is central to the theory behind HVI for Achilles tendinopathy as well.https://doi.org/10.1007/s001670000128
Maffulli, N., & Spiezia, F. (2017). High-volume injection for the treatment of chronic Achilles tendinopathy. Operative Techniques in Sports Medicine, 25(2), 143-149. https://doi.org/10.1053/j.otsm.2017.03.011
Discover the importance of the GLP-1 antagonist withing the neuro-immune mechanism in medical research and treatment.
Abstract
Recent advancements in metabolic health have introduced powerful GLP-1 receptor agonists like Retatrutide, offering significant hope for weight management. However, many individuals experience a perplexing and distressing side effect: severe skin sensitivity, a condition technically known as drug-induced cutaneous allodynia and hyperesthesia. This feels like a persistent, painful sunburn where even the slightest touch from clothing or bedsheets causes excruciating discomfort. Conventional approaches often miss the mark, treating this complex neuro-immune reaction with simple antihistamines, which may provide minimal relief while failing to address the root cause. This educational post, from my perspective as Dr. Alex Jimenez, will take you on a deep journey into the intricate physiological mechanisms driving this phenomenon. We will explore how Retatrutide, a triple agonist targeting GLP-1, GIP, and Glucagon receptors, throws a “grenade” into the delicate balance of your neuroendocrine-immune axis. Drawing upon the latest findings from leading researchers published in journals like Nature Metabolism and Cell Metabolism, we will dissect how these medications hypersensitize your peripheral nerves, lower the activation threshold for immune mast cells, create a pro-inflammatory environment through rapid fat loss, and disrupt crucial electrolyte balances, particularly magnesium, which is vital for nerve stability. This comprehensive exploration will move beyond a superficial understanding to provide a clear, evidence-based roadmap of what is happening inside your body. We will then transition into a detailed, practical, and integrative treatment strategy. This strategy combines dose adjustment, targeted hydration with specific electrolytes, and a powerful synergistic stack of neuro-regenerative and anti-inflammatory compounds, including Palmitoylethanolamide (PEA), Alpha-Lipoic Acid (ALA), Benfotiamine, and specific forms of Magnesium. Furthermore, I will explain how our unique multidisciplinary clinical model at Injury Medical Clinic, under the medical direction of Dr. Maria G. Cardenas, MD, integrates chiropractic care, functional medicine, and medical oversight to support the body’s structural and neurological integrity, offering a holistic path to resolving this debilitating sensitivity and restoring comfort and function.
Introduction: The Paradox of a Revolutionary Treatment
As a clinician with dual licensure in chiropractic (DC) and advanced practice nursing (FNP-BC), and certifications in functional medicine (CFMP, IFMCP), I stand at a unique intersection of healthcare. My work is dedicated to unraveling the complex web of human physiology to help patients not just manage symptoms, but achieve true, foundational health. This mission is shared and strengthened by our collaborative practice at Injury Medical Clinic PA in El Paso, Texas. Here, I work alongside Dr. Maria Guadalupe Cardenas, MD, a highly respected internist with over 40 years of experience and our Medical Director. Our integrated model allows us to blend the structural and neurological focus of chiropractic care with the deep medical insights and oversight of internal medicine, creating a comprehensive approach to patient wellness, especially in complex cases involving personal injury, chronic pain, and metabolic dysfunction.
Lately, my inbox and patient consultations have been filled with a recurring, distressing story. Patients starting on the new generation of weight-loss medications, specifically the potent triple-agonist Retatrutide, are describing a bizarre and painful side effect. They tell me their skin feels like it has been rubbed raw with sandpaper or that they have a severe, invisible sunburn. The sensation of their own clothes brushing against their skin becomes unbearable. This is not a simple rash or an allergic reaction with hives; this is a profound, nerve-based pain condition known as drug-induced cutaneous allodynia and hyperesthesia. Allodynia is a state where a stimulus that is not normally painful, like the touch of a cotton sheet, is perceived as painful. Hyperesthesia is an exaggerated sensitivity to any stimulus.
Unfortunately, many of these patients report that their primary care providers, while well-intentioned, are approaching this as a simple histamine reaction. They are prescribed antihistamines, which might slightly dull the edge of the discomfort (primarily through sedation) but do nothing to address the complex storm brewing within the nervous and immune systems. The patient is left sedated, still in pain, and deeply frustrated.
My purpose here is to illuminate the true nature of this condition. This is not a simple side effect; it is a profound biological response. Retatrutide and its cousins are not just appetite suppressants; they are powerful modulators of your entire neuroendocrine-immune axis. These drugs interact with receptors found on your peripheral nerves, your immune cells (like mast cells), and even within your central nervous system. When you introduce a powerful agonist like Retatrutide, you are essentially throwing a biological grenade into this intricate system.
In this educational journey, we will dissect exactly what is happening. We will explore groundbreaking research from 2022 and 2023 that reveals the precise mechanisms at play. You will understand:
How these drugs directly “crank up” the excitability of the very nerve fibers responsible for sensing pain, touch, and temperature.
How they make your immune system’s “border patrol”—the mast cells in your skin—”trigger-happy,” causing them to release inflammatory chemicals at the slightest provocation.
How the rapid weight loss itself, while a desired outcome, creates a temporary but potent pro-inflammatory state that bathes your already-sensitized nerves in inflammatory signals.
The critical and often-overlooked role of electrolyte depletion—specifically magnesium—in destabilizing your nerves and amplifying this painful response.
Understanding these mechanisms is the key to empowerment. It moves us from fear and confusion to clarity. This is not a sign that your body is “broken” or that you have a “contaminated” source of medication. This is your biology adapting—albeit painfully—in real time to a powerful new set of signals.
And most importantly, once we understand the “why,” we can effectively address the “how.” I will lay out a clear, actionable, evidence-based protocol to shut down this painful overreaction and restore balance to your system. This is not about simply masking the pain; it is about providing your body with the precise tools it needs to recalibrate and heal. We will discuss dose modulation, strategic hydration, and a specific combination of therapeutic compounds that work synergistically to quiet the nerves, stabilize the immune cells, and replenish the essential nutrients your nervous system is screaming for.
Finally, I will connect this functional medicine approach back to our integrated care model. We will discuss how integrative chiropractic care plays a vital supportive role by optimizing spinal cord and peripheral nerve function, reducing systemic stress through nervous system regulation, and ensuring the body’s structural framework can best support this profound physiological transition. Under Dr. Cardenas’s watchful medical eye, we can safely navigate these complex therapeutic landscapes, ensuring our patients not only achieve their weight-loss goals but do so with vibrant health and well-being.
Let’s begin this journey of understanding and healing.
The Neuro-Immune Cascade: Deconstructing Retatrutide’s Impact on Your Body
To truly grasp why your skin feels like it’s on fire, we must move beyond the surface and look at the intricate signaling network that Retatrutide targets. This drug is known as a triple agonist, meaning it activates three distinct receptor types: the Glucagon-Like Peptide-1 (GLP-1) receptor, the Glucose-dependent Insulinotropic Polypeptide (GIP) receptor, and the Glucagon (GCG) receptor. For decades, these were primarily understood in the context of blood sugar control and digestion. However, recent, cutting-edge research has revealed their profound and widespread influence throughout the body, particularly within the nervous and immune systems. These receptors are not just in your pancreas and gut; they are everywhere—on your skin, your peripheral nerves, your immune cells, your keratinocytes (skin cells), and woven throughout your central nervous system.
Taking a drug like Retatrutide is akin to sending a powerful, continuous “ON” signal to all these receptors simultaneously. Your body’s systems, which are accustomed to nuanced, pulsatile signaling, are suddenly flooded with a relentless command. The result is a cascade of events that culminates in the debilitating skin sensitivity you are experiencing. Let’s break down each component of this cascade, step by step, using the latest scientific evidence.
1. The Direct Assault on Your Nerves: GLP-1 Receptors and Peripheral Hyperexcitability
The first and most direct piece of the puzzle lies in the peripheral nerves themselves. These are the delicate nerve fibers that branch out from your spinal cord to every square inch of your body, including your skin. They are your interface with the world, responsible for transmitting sensations of touch, temperature, and pain.
For a long time, the prevailing thought was that the effects of GLP-1 agonists on the nervous system were primarily central, occurring within the brain. However, a landmark 2023 study published in the prestigious journal Nature Metabolism completely upended this view (Krieger et al., 2023). This research provided definitive proof that peripheral nerves are densely populated with GLP-1 receptors.
Specifically, the study identified these receptors on the very nerve fibers that are at the heart of your current misery:
C-fibers: These are small, unmyelinated nerve fibers that transmit the signals for dull, burning, or aching pain, as well as temperature and itch. When you feel that persistent, sunburn-like ache, your C-fibers are firing relentlessly.
A-delta fibers: These are slightly larger, thinly myelinated fibers that transmit sharp, pricking pain and cold sensations. These fibers carry the initial sharp sting you might feel when something touches your skin.
The critical takeaway here is that these sensory neurons are now known to be direct targets of Retatrutide. From the neuron’s perspective, it doesn’t matter that you took this medication to lose weight. It doesn’t understand the therapeutic intent. All it knows is that it has received a powerful, direct, and sustained signal to activate. The drug binds to the GLP-1 receptors on the nerve fiber’s membrane, triggering a series of intracellular events that fundamentally alter the neuron’s behavior.
The Cellular Mechanism of Hyperexcitability
Let’s get a bit more granular. When a GLP-1 agonist binds to its receptor on a sensory neuron, it initiates a signaling cascade inside the cell. This primarily involves an enzyme called adenylyl cyclase, which increases a secondary messenger molecule called cyclic AMP (cAMP). This surge in cAMP has several profound effects on the neuron:
Lowering the Firing Threshold: A neuron’s resting state is maintained by a delicate balance of ions (like sodium, potassium, and calcium) across its membrane, creating what’s called the resting membrane potential. Increased cAMP, through a process involving Protein Kinase A (PKA), can phosphorylate (add a phosphate group to) various ion channels. This modification makes channels like the voltage-gated sodium channels easier to open. These sodium channels are the “gatekeepers” of nerve firing. By making them easier to open, the neuron’s firing threshold is lowered. It now takes a much weaker stimulus—the brush of a shirt, a change in air temperature—to cause the neuron to reach its action potential and fire a pain signal to the brain.
Increased Neurotransmitter Release: When the nerve signal reaches the end of the neuron (the synapse), it triggers the release of neurotransmitters, which carry the signal to the next neuron in the chain, eventually reaching the spinal cord and brain. The same cAMP/PKA pathway enhances the release of excitatory neurotransmitters like glutamate and Substance P from the terminals of these sensory nerves. Substance P, in particular, is a potent pain-signaling molecule. So, not only are the nerves firing more easily, but when they do fire, they release a more potent chemical message, shouting “PAIN!” much louder to the central nervous system.
Upregulation of Pain Receptors: Chronic stimulation can also change gene expression within the neuron. The cell can be signaled to produce more of the receptors and ion channels involved in pain signaling, such as the TRPV1 receptor. This receptor is famously activated by capsaicin (the “hot” in chili peppers) and heat. Upregulating TRPV1 makes the nerve ending exquisitely sensitive to thermal stimuli. This is why a warm shower can suddenly feel scaldingly hot.
In essence, the GLP-1 component of Retatrutide is directly “cranking up the gain” on your peripheral sensory nervous system. The nerves become hyperexcitable and sensitized. They no longer report sensations; they amplify them, turning gentle touch into a barrage of pain signals. This is the core reason for the allodynia and hyperesthesia. Your skin sensitivity isn’t an illusion; your nerves are biologically and biochemically reprogrammed to be in a state of high alert.
2. The Immune System on Edge: GIP Receptors and Mast Cell Degranulation
The second critical player in this painful symphony is the mast cell. Think of mast cells as the “border patrol” or the “first responders” of your immune system. They are strategically positioned in tissues that interface with the outside world: your skin, your gut lining, and your lungs. They stand guard, ready to sound the alarm at the first sign of trouble, be it a pathogen, an allergen, or tissue injury.
Each mast cell is a microscopic biological hand grenade, packed with tiny granules filled with a potent cocktail of inflammatory mediators. These include:
Histamine: Famous for its role in allergic reactions, causing itching, swelling, and vasodilation (widening of blood vessels).
Prostaglandins: Powerful signaling molecules that contribute to pain, fever, and inflammation.
Bradykinin: A peptide that is one of the most potent pain-producing substances known. It directly activates pain-sensing nerve fibers.
Substance P: The same pain neurotransmitter we discussed earlier. Mast cells can release it, which can, in turn, activate nerves and create a vicious feedback loop.
Tryptase and Chymase: Enzymes that can break down surrounding tissue and amplify the inflammatory response.
Under normal circumstances, mast cells have a high activation threshold. It takes a significant trigger—like a bee sting or a major allergen—to make them “degranulate” and release their inflammatory payload.
This is where the GIP (Glucose-dependent Insulinotropic Polypeptide) component of Retatrutide comes into play. Research has shown that, just like nerves, mast cells are covered in GIP receptors. When Retatrutide chronically stimulates these GIP receptors, it doesn’t necessarily cause the mast cells to degranulate spontaneously. Instead, it does something more insidious: it modulates and lowers their degranulation threshold.
Priming the Grenade: The “Trigger-Happy” Mast Cell
Constant GIP signaling primes mast cells, putting them on a hair trigger. The intracellular signaling pathways activated by GIP (which also involve cAMP, but can interact with other pathways like phospholipase C) effectively “pre-load” the degranulation machinery. The mast cells become what I call “trigger-happy.“
Now, stimuli that the immune system would completely ignore become potent triggers. Consider the gentle pressure from the seam of your shirt, the slight change in temperature from a breeze, or the sensation of warm water in the shower. For a primed, trigger-happy mast cell, these innocuous physical stimuli are now sufficient to cross the lowered activation threshold.
And boom. The mast cell degranulates, releasing its inflammatory cocktail directly into your skin’s microenvironment. This phenomenon is known as local neurogenic inflammation. It’s “neurogenic” because it’s often initiated or amplified by the nerve activity we discussed earlier, creating a vicious cycle. Hyperexcitable nerves can release signals (like Substance P) that trigger mast cells, and mast cells release chemicals (like histamine and bradykinin) that further excite the nerves.
This creates a self-perpetuating firestorm in your skin:
A light touch stimulates a hypersensitive nerve ending.
The nerve firing, along with the physical pressure, is enough to trigger a “trigger-happy” mast cell to degranulate.
The mast cell releases histamine, bradykinin, and prostaglandins.
These inflammatory mediators directly activate more pain nerve endings, causing that burning, aching pain.
They also make local blood vessels leaky, causing microscopic swelling and redness (even if not visible) and allowing more immune cells to enter the area.
The result is a localized but intense inflammatory environment that further sensitizes the entire region.
This explains why the pain is not just a fleeting sensation but a persistent state of discomfort. Your skin is literally marinating in an inflammatory soup, continuously generated by an immune system put on high alert by the GIP component of your medication. The antihistamines prescribed by many doctors target only one small piece of this puzzle (histamine), which is why they provide such limited relief. They do nothing to stop the release of bradykinin, prostaglandins, or the other potent mediators, nor do they address the root cause: the lowered mast cell threshold.
3. The Inflammatory Fallout of Rapid Weight Loss
The third force multiplying this painful experience is a direct consequence of the drug’s success: rapid adipose reduction. Retatrutide is incredibly effective at promoting fat loss, but this process is not as “clean” as one might think. Your adipose tissue (body fat) is not just an inert energy storage depot. It is a highly active endocrine organ that produces and secretes a vast array of hormones and signaling molecules called adipokines.
In a state of metabolic health, adipose tissue secretes beneficial adipokines like adiponectin, which is anti-inflammatory and improves insulin sensitivity. However, in states of obesity, and paradoxically, during periods of very rapid weight loss, the adipose tissue becomes dysfunctional and shifts its production towards pro-inflammatory cytokines.
A crucial 2022 study in Cell Metabolism shed light on this exact phenomenon (Roh et al., 2022). The researchers demonstrated that rapid fat loss, whether through bariatric surgery or intense caloric restriction (which mimics the effect of GLP-1 agonists), creates a transient but potent pro-inflammatory cytokine environment.
Why Does Losing Fat Cause Inflammation?
As fat cells (adipocytes) shrink and die off (a process called apoptosis), they release their contents and send out distress signals. This attracts immune cells, particularly macrophages, which flock to the adipose tissue to “clean up” the debris from the dying fat cells. This process, while necessary, is inherently inflammatory. The macrophages themselves become activated and start churning out a flood of pro-inflammatory cytokines, including:
Tumor Necrosis Factor-alpha (TNF-α): A master regulator of inflammation that can directly sensitize pain neurons.
Interleukin-6 (IL-6): A key player in systemic inflammation that can cross the blood-brain barrier and influence central pain processing.
Interleukin-1beta (IL-1β): A powerful pro-inflammatory signal that is known to contribute to chronic pain states.
These cytokines don’t stay confined to your fat tissue. They spill out into your bloodstream, creating a state of low-grade systemic inflammation. Your entire body, including your skin and peripheral nerves, is now marinating in this inflammatory broth.
Now, connect this back to our first two points. You already have:
Peripheral nerves that are hyperexcitable and on a hair trigger due to direct GLP-1 stimulation.
Mast cells in your skin that are primed to degranulate at the slightest provocation due to GIP stimulation.
On top of this, you now introduce a systemic flood of TNF-α, IL-6, and IL-1β from your rapidly shrinking fat stores. These cytokines act as powerful sensitizing agents. They bind to their own receptors on the already-hyperexcitable nerves and mast cells, pouring gasoline on the fire. They further lower the activation thresholds, increase the expression of pain-related channels and receptors, and promote an even more robust inflammatory response.
This explains why the pain can feel so widespread and relentless. It’s the “perfect storm”: a convergence of direct nerve sensitization, localized immune hyper-reactivity, and systemic inflammation. The pain from your bedsheets is not just a local skin issue; it’s the final, agonizing expression of a body-wide state of neuro-immune dysregulation, driven by the medication and the very biological process of weight loss it initiates. It’s a case of the “cure” being faster than your biology can comfortably adapt, leading to significant collateral discomfort.
4. Amplifying the Pain Signal: Glucagon Receptors and the Dorsal Root Ganglion
The final piece of this triple-agonist puzzle is the activation of the Glucagon (GCG) receptor. To understand its impact, we need a quick trip into basic neuroanatomy.
As your peripheral sensory nerves travel from your skin towards the spinal cord, they don’t plug in directly. Instead, the cell bodies of these neurons are clustered together in a structure called the Dorsal Root Ganglion (DRG). The DRG sits just outside the spinal cord and acts as a critical “switchboard” or “gatekeeper” for all incoming sensory information—touch, pressure, temperature, and pain. Every signal from your periphery must pass through the DRG before it can be relayed up to the brain for processing.
What has become increasingly clear is that the neurons within the DRG are rich in glucagon receptors. When the glucagon agonist component of Retatrutide activates these receptors, it further modulates the excitability of the nociceptive (pain-sensing) neurons housed within the ganglion.
Cranking Up the Gain at the Central Switchboard
Think of the DRG as the volume knob for all incoming sensory data. The activation of glucagon receptors in the DRG essentially cranks up this volume knob. It makes the neurons within the ganglion more likely to fire and to transmit a stronger signal onward to the spinal cord.
The mechanism is similar to what we see in the peripheral nerve endings, involving changes in ion channel function and neurotransmitter release. Glucagon receptor activation can lead to central sensitization. This is a dangerous phenomenon where the central nervous system itself becomes hyperexcitable. Even after the initial peripheral stimulus is gone, neurons in the spinal cord and brain can remain highly reactive, essentially creating a “pain memory.”
So, the glucagon component of Retatrutide adds another layer of amplification to the pain signals:
Peripheral Signal: The initial signal from the skin is already amplified due to GLP-1-induced nerve hyperexcitability.
Local Inflammation: The signal is further intensified by the inflammatory soup created by GIP-triggered mast cells.
DRG Amplification: As this already-loud signal arrives at the DRG, glucagon-induced hyperexcitability in the ganglion neurons amplifies it again before sending it to the brain.
It’s a triple-amplification system. A whisper of a touch at the skin becomes a deafening roar by the time it reaches the brain’s sensory cortex. This is not a malfunction. Your neurons are not broken, and the medication is not “contaminated.” This is the predictable, albeit extreme, physiological response to simultaneously and chronically activating three powerful signaling pathways that are deeply integrated into your body’s pain-processing network. Biology is rewriting its own set points in real time, and the discomfort is tangible evidence of that profound adaptation.
5. The Final Insult: Electrolyte Depletion and the Destabilized Nerve
One more crucial, often missed, piece of this puzzle ties everything together. It’s a factor that turns a sensitive system into an unstable one: electrolyte dysregulation.
GLP-1 agonists, as a class, have a known effect on the kidneys. They promote natriuresis, which is the excretion of sodium in the urine. As the saying goes, “where sodium goes, water follows.” This leads to a significant loss of both sodium and water, which is why proper hydration is so critical with these medications.
However, the story doesn’t end there. This diuretic effect also causes urinary loss of other critical electrolytes, most importantly intracellular magnesium. Magnesium is arguably the most important mineral for nervous system stability. It acts as a natural “calcium channel blocker” and a physiological shield for your nerves.
The Magnesium Shield: Guardian of the Resting Membrane Potential
To understand why magnesium is so vital, we need to revisit the concept of a neuron’s resting membrane potential. In its resting, non-firing state, a neuron maintains a negative electrical charge on the inside relative to the outside. This stable state is crucial. It ensures the neuron fires only when it receives a legitimate and sufficiently strong signal.
Magnesium plays a key role in maintaining this stability in several ways:
Stabilizing the Membrane: Magnesium ions (Mg2+) physically associate with the phospholipids on the nerve cell membrane, helping to maintain its structural integrity and electrical stability.
Blocking NMDA Receptors: At the synapse (the junction between two neurons), magnesium sits inside the channel of a key receptor called the NMDA receptor. This receptor is critical for learning, memory, and, importantly, amplifying pain signals (a process called “wind-up”). By plugging the channel, magnesium prevents the receptor from being easily activated. When magnesium levels are low, this “magnesium plug” is removed, leaving the NMDA receptor wide open. This leads to a massive influx of calcium into the neuron, which is a powerful “ON” signal that promotes hyperexcitability and can even be toxic to the cell (excitotoxicity).
Regulating Ion Channels: Magnesium is essential for the proper function of the sodium-potassium pump (Na+/K+-ATPase). This enzyme actively pumps sodium out of the neuron and potassium in, which is the primary mechanism for re-establishing the resting membrane potential after a nerve has fired. Without adequate magnesium, this pump becomes sluggish, and the neuron struggles to return to its stable resting state, leaving it vulnerable to firing again with minimal provocation.
When you take a GLP-1 agonist that makes you excrete sodium, water, and crucially, magnesium, you are systematically stripping your peripheral nerves of their primary protective shield. The peripheral nerve sheaths lose their magnesium-electrolyte buffer.
The result? The resting membrane potential becomes destabilized. The neuron’s electrical footing becomes precarious. It’s like trying to stand on one leg on a wobbly surface. Everything can set it off. The very foundation of nerve stability is eroded.
Now, layer this on top of everything else we’ve discussed:
You have direct GLP-1 stimulation making the nerves hyperexcitable.
You have GIP-mediated mast cell degranulation creating local inflammation.
You have systemic inflammation from rapid fat loss.
You have central amplification at the DRG from glucagon.
And now, you have removed the fundamental electrochemical brake—magnesium—that is supposed to keep the entire system in check.
This is the final straw. The discomfort you feel is not just “damage” or an “allergy.” It is the culmination of a multi-system biological cascade. Your nervous system is stripped of its protective electrolyte shield and bombarded with excitatory signals from multiple angles, screaming for help. This is biology rewriting its set points in real time, and it’s painful. But the good news is that because it is a process based on clear physiological mechanisms, we can intervene. We can provide the body with the specific tools it needs to restore balance, re-establish the shield, and quiet the storm.
The Non-Surgical Approach to Wellness with Chiropractic Care- Video
The Integrative Solution: A Protocol to Reclaim Your Comfort
Understanding the complex web of interactions that causes this debilitating skin sensitivity is the first and most critical step. Now, we move to the solution. This is where my background in functional medicine shines, as we look to provide the body with the precise building blocks and signals it needs to restore homeostasis (internal balance). The goal is not to mask the pain with a drug but to fundamentally address each layer of the problem we have just uncovered.
This protocol is a multi-pronged attack designed to:
Reduce the Agonist Load: Decrease the intensity of the signal being sent to the GLP-1, GIP, and Glucagon receptors.
Re-establish the Electrolyte Shield: Aggressively replenish sodium, potassium, and magnesium, which are essential for nerve stability.
Calm the Nerves and Immune Cells: Utilize targeted, evidence-based compounds that directly quell neuro-inflammation and stabilize mast cells.
Support Nerve Regeneration and Function: Provide key B vitamins and antioxidants that protect nerves from damage and support their metabolic health.
Let’s break down each component of this comprehensive strategy.
Step 1: Cut the Dose, Not the Medication
The first and most logical step is to reduce the intensity of the signal that is causing the overstimulation. The painful sensitivity is a classic sign of a dose-response effect—you have exceeded your body’s ability to adapt to the current level of receptor agonism.
Action:Cut your current dose in half.
If you are taking 10 mg, reduce it to 5 mg. If you are on 5 mg, go down to 2.5 mg. This is not a step backward; it is a strategic retreat to allow your biological systems—your nerves, your mast cells, your entire neuro-immune axis—to catch up and re-regulate. The goal is to find the Minimum Effective Dose that still provides a therapeutic benefit for weight loss and metabolic control but does not push your nervous system over the edge into a state of painful hyperexcitability.
Many patients find they can still achieve excellent results on a lower dose, especially when combined with the supportive measures we are about to discuss. Once your symptoms have completely resolved (which may take several weeks), you can consider a very slow and gradual titration back up, paying close attention to your body’s signals. But for now, the immediate priority is to turn down the volume.
Step 2: Strategic Hydration—More Than Just Water
We’ve established that these medications cause you to lose significant amounts of sodium and water. The common advice to “just drink more water” is not only insufficient in this case—it can be counterproductive and even dangerous.
When you lose sodium and then flood your body with plain, electrolyte-free water, you further dilute the remaining electrolytes in your extracellular fluid. This lowers the electrolyte concentration outside your nerve cells, worsening the electrochemical imbalance and potentially exacerbating nerve firing. It’s a recipe for increased sensitivity. This condition is known as hyponatremia (low sodium), and it can have serious neurological consequences.
Action:Implement a protocol for aggressive, targeted electrolyte repletion.
The goal is to consume approximately four liters of fluid daily, but this fluid must be fortified with the specific electrolytes your body is losing. This is not about drinking a sugary sports drink; this is about creating a therapeutic oral rehydration solution.
Here is the specific, evidence-based recipe:
Four Liters of Water Daily: This is your fluid base. Use filtered water.
Five Grams of Sodium: This is the most critical component. This sounds like a lot, and it would be for someone with hypertension who is not on a GLP-1 agonist. But in this context, you are replacing what is being lost. You are not adding to a surplus. This is about restoring balance. Five grams of sodium is equivalent to about 12-13 grams of salt (sodium chloride), which is about 2.5 teaspoons. Spread this out throughout the day across your four liters of water. Do not consume it all at once. You can use high-quality sea salt or pink Himalayan salt, which also contain trace minerals.
Two Grams of Potassium Chloride: As you lose sodium, your body can also waste potassium to maintain electrochemical balance. Replenishing potassium is vital for nerve and muscle function, including the heart muscle. Potassium chloride is a readily available salt you can add to your water. Be precise with this measurement.
Flavoring (Optional): This solution will taste salty. You can add sugar-free flavor enhancers or a squeeze of lemon or lime to make it more palatable. The key is to avoid sugar, which would work against your metabolic goals.
This strategic hydration solution will do more than quench your thirst. It will begin to rebuild the crucial electrochemical environment around your nerves, providing the foundational stability they need to stop firing erratically. You should notice a significant improvement in your symptoms within a few days of implementing this correctly.
Step 3: The Synergistic Stack—Targeted Neuro-Immune Modulation
While re-establishing the electrolyte foundation is critical, we also need to actively calm the existing firestorm in your nerves and immune cells. This is where we bring in a powerful, synergistic stack of compounds that have been extensively researched for their neuroprotective, anti-inflammatory, and nerve-stabilizing properties.
A. Palmitoylethanolamide (PEA): The Body’s Own Anti-Inflammatory
PEA (Palmitoylethanolamide) is one of the most exciting and effective tools in our arsenal for this condition. It is an endogenous (meaning your body makes it) fatty acid amide that acts as a profound anti-inflammatory and analgesic (pain-relieving) agent. It’s often referred to as a “natural endocannabinoid” because it works through similar pathways, but without any psychoactive effects.
How PEA Works:
PEA’s genius lies in its ability to calm the “trigger-happy” mast cells we discussed earlier. It is a mast cell stabilizer. It signals the mast cell to raise its degranulation threshold back to normal levels. It doesn’t block a single mediator like an antihistamine; it prevents the release of the entire inflammatory cocktail—histamine, prostaglandins, bradykinin, and more—at the source.
Furthermore, PEA works “downstream” on other immune cells like microglia (the immune cells of the central nervous system) and macrophages, instructing them to switch from a pro-inflammatory state to an anti-inflammatory, pro-resolving state. It also directly affects neurons, helping reduce their hyperexcitability.
Clinical Application: PEA is remarkably safe and well-tolerated. For a condition this acute and severe, a high-dose loading protocol is necessary.
Dosing:1200 mg per day, taken as 600 mg twice daily.
Formulation: Look for a micronized or ultra-micronized formulation. The PEA molecule is very large and fatty, so breaking it down into smaller particles significantly increases its absorption and bioavailability, making it far more effective.
PEA is the cornerstone of quieting the immune-driven component of your pain.
B. Magnesium: The Ultimate Nerve Shield
We’ve already established the critical importance of magnesium and how its depletion destabilizes your nerves. Replenishing it is non-negotiable. However, not all forms of magnesium are created equal. You must use a form that is highly bioavailable and, ideally, can cross the blood-brain barrier to also address central sensitization.
Action:Supplement with a dual-form magnesium complex.
Magnesium Glycinate: This form is magnesium chelated (bound) to the amino acid glycine. This chelation makes it highly absorbable and gentle on the stomach (unlike magnesium oxide or citrate, which can have a laxative effect). Glycine itself is an inhibitory neurotransmitter in the central nervous system, meaning it has a calming effect. This makes magnesium glycinate an excellent choice for promoting relaxation, improving sleep, and calming an over-excited nervous system.
Magnesium L-Threonate: This unique, patented form of magnesium has been shown in studies to effectively cross the blood-brain barrier and increase magnesium concentrations in the brain and spinal fluid (Slutsky et al., 2010). This is crucial for combating the central sensitization we discussed in the context of the DRG and glucagon receptors. It helps to restore the “magnesium plug” in the NMDA receptors within the central nervous system, dialing down pain amplification at its core.
Dosing Protocol:
Magnesium Glycinate:400-600 mg of elemental magnesium per day. Take this in divided doses, with a larger portion in the evening to support sleep and muscle relaxation.
Magnesium L-Threonate: Follow the dosage instructions on the product, which is typically around 144-200 mg of elemental magnesium per day.
Combining these two forms provides a comprehensive approach, shoring up magnesium levels systemically and peripherally with glycinate while specifically targeting the central nervous system with threonate.
C. Alpha-Lipoic Acid (ALA): The Master Antioxidant for Nerve Health
Alpha-Lipoic Acid (ALA) is a unique and potent antioxidant because it is both water-soluble and fat-soluble. This means it can work in every part of the cell, including the fatty nerve membrane and the watery cytoplasm. It is particularly well-known for its benefits in treating diabetic neuropathy, another condition characterized by nerve pain and damage.
How ALA Works in This Context:
Powerful Antioxidant: The inflammatory cascade we’ve described generates a massive amount of oxidative stress—an excess of free radicals that damage cell structures, including nerves. ALA is a master scavenger of these free radicals, protecting the nerve from further damage.
Regenerates Other Antioxidants: ALA can regenerate other key antioxidants in the body, including Glutathione, Vitamin C, and Vitamin E, effectively recycling and amplifying the body’s own protective systems.
Improves Nerve Blood Flow: ALA has been shown to improve blood flow to the nerves (endoneurial blood flow), delivering more oxygen and nutrients for repair and removing waste products.
Reduces Nerve Excitability: Some research suggests ALA can directly modulate ion channels and reduce the hyperexcitability of sensory neurons, adding another layer of calming effect.
Clinical Application: To be effective for neuropathy, ALA must be used in its most bioactive form and at a therapeutic dose.
Formulation: Use the R-ALA form. ALA exists in two forms (isomers), R-ALA and S-ALA. The R-ALA form is naturally found in the body and is significantly more biologically active. Most standard ALA supplements are a 50/50 mix of R-ALA and S-ALA. Sourcing pure R-ALA is superior.
Dosing:600 mg per day. This is the standard therapeutic dose used in most clinical trials for neuropathy. It can be taken once daily.
ALA provides crucial protection for your nerves, shielding them from the inflammatory and oxidative damage while supporting their intrinsic healing processes.
D. Benfotiamine: The Nerve-Nourishing B-Vitamin
The final component of our core stack is Benfotiamine. This is not your standard B1 (thiamine) vitamin. It is a fat-soluble derivative of thiamine with much higher bioavailability and can penetrate nerve cells far more effectively than regular thiamine.
Thiamine is absolutely critical for nerve cell metabolism. It is a key cofactor in converting glucose into energy (ATP) within the mitochondria—the cell’s powerhouses. Nerves are incredibly metabolically active and have a huge energy demand.
How Benfotiamine Works:
In states of inflammation and metabolic stress (like the one we are in), nerve cells can struggle to metabolize glucose properly. This leads to the buildup of harmful metabolic byproducts, such as Advanced Glycation End-products (AGEs). These AGEs are sticky, dysfunctional molecules that gum up the works, causing cellular damage, inflammation, and nerve dysfunction. This is a primary mechanism of damage in diabetic neuropathy.
Benfotiamine works by activating an enzyme called transketolase. This enzyme shunts the harmful metabolic precursors away from the pathways that form AGEs and into a safe, alternative metabolic route called the pentose phosphate pathway.
In essence, Benfotiamine does two things:
Prevents Nerve Damage: It stops the formation of toxic AGEs, protecting the nerve from further inflammatory and metabolic damage.
Boosts Nerve Energy: By optimizing glucose metabolism, it helps nerve cells produce the energy they need to function properly, maintain their ion pumps, and repair themselves.
Clinical Application:
Dosing:600 mg per day, often taken as 300 mg twice daily. This high dose is necessary to saturate the tissues and achieve a therapeutic effect on the transketolase enzyme.
Benfotiamine is the metabolic fuel and protector for your stressed-out nerves. It ensures they have the energy to heal and the protection from the toxic byproducts of inflammation.
The Role of Integrative Chiropractic Care in Systemic Balance
Now that we have a robust functional medicine protocol to address the biochemical and immunological roots of the problem, it’s essential to discuss the structural and neurological component of care. This is where my role as a Doctor of Chiropractic (DC) becomes integral to a truly holistic solution. The central nervous system—the brain and spinal cord—is the body’s master control system, including the peripheral nerves and the immune system. The health and proper function of the spine are directly linked to the health and function of the nervous system.
At our practice, Injury Medical Clinic PA, this is the core of our philosophy. Under the medical direction of Dr. Maria Cardenas, we create a patient-centered plan that respects the interplay between the body’s structure (chiropractic) and its chemistry (functional and internal medicine). When dealing with a profound neuro-immune reaction like Retatrutide-induced sensitivity, chiropractic care provides several key supportive benefits.
1. Optimizing Spinal Function and Nerve Flow
The spinal cord is the main highway for all nerve signals traveling between the brain and the body. The peripheral nerves that are currently firing in your skin originate from nerve roots that exit the spinal column. Any structural or functional issue in the spine—what we in chiropractic call a vertebral subluxation complex—can interfere with the normal flow of nerve information.
A subluxation is not necessarily a “pinched nerve” in the dramatic sense. It is a more subtle condition involving a vertebra that has lost its normal position or motion, leading to a cascade of effects:
Altered Mechanical Input: The mechanoreceptors (nerve endings that sense position and movement) in the joints and muscles around the dysfunctional spinal segment send aberrant or noisy signals back to the central nervous system.
Local Inflammation: Joint dysfunction can create localized inflammation around the nerve roots.
Muscle Spasm: Protective muscle splinting can further restrict movement and contribute to pain.
In a patient who is already experiencing systemic nerve hyperexcitability, even a minor degree of spinal dysfunction can act as an additional source of “static” or “noise” in the nervous system, further contributing to central sensitization.
Our Chiropractic Approach:
Through gentle, specific chiropractic adjustments, we aim to restore normal motion and alignment to the spinal segments. This is not about “cracking backs”; it is a precise neurological intervention. The goals of the adjustment in this context are:
Improve Segmental Motion: Restore the normal biomechanics of the spinal joints.
Stimulate Mechanoreceptors: The gentle, high-velocity, low-amplitude thrust of an adjustment bombards the central nervous system with a flood of normal proprioceptive (position sense) and mechanoreceptive input. This can help to “gate” or override the pain signals coming from the periphery, a concept known as the Gate Control Theory of Pain.
Reduce Neurological Interference: By correcting the subluxation, we reduce the aberrant signaling from the spinal level, helping to quiet the overall “noise” in the nervous system.
By ensuring the spinal column functions optimally, we create a clearer, more stable pathway for nerve communication, reducing one potential source of amplification in the pain cascade.
2. Modulating the Autonomic Nervous System
The nervous system has two main divisions: the sympathetic (“fight or flight“) system and the parasympathetic (“rest and digest“) system. In chronic pain and inflammation, the sympathetic nervous system tends to dominate. This sympathetic dominance itself contributes to the problem: it promotes inflammation, sensitizes pain receptors, and keeps the body in a state of high alert.
Chiropractic adjustments have been shown to modulate the Autonomic Nervous System (ANS) strongly. Research using measures like Heart Rate Variability (HRV)—a key indicator of autonomic balance—has demonstrated that spinal adjustments can shift the ANS away from sympathetic dominance and towards a more parasympathetic state (Welch & Boone, 2008).
Why This Matters for Retatrutide Sensitivity:
Promoting a “Rest and Heal” State: By promoting a parasympathetic shift, we help to move the entire body out of a state of high alert and into a state conducive to healing and repair. This is the physiological state where inflammation is resolved, and tissues are rebuilt.
Reducing Systemic Stress Hormones: Sympathetic dominance is associated with elevated levels of stress hormones like cortisol and adrenaline. When chronically elevated, these hormones can further dysregulate the immune system and sensitize nerves. A parasympathetic shift helps to lower these hormones.
Improving Immune Regulation: The parasympathetic system, via the vagus nerve, plays a direct role in regulating inflammation through a pathway known as the “cholinergic anti-inflammatory pathway.” Stimulating this pathway can help down-regulate the production of pro-inflammatory cytokines like TNF-α—the same cytokines released by shrinking adipose tissue.
Through chiropractic care, we are not just treating a spinal issue; we are using the spine as a lever to influence and rebalance the body’s master control system, creating a systemic environment that is less reactive and more resilient.
3. Adjunctive Therapies for Neuro-Muscular Re-education
In addition to spinal adjustments, our integrated approach incorporates rehabilitative therapies designed to support the neuromuscular system. In chronic pain, the body often adopts dysfunctional movement patterns and muscle guarding.
Soft Tissue Therapies: Techniques like myofascial release, trigger point therapy, and massage can help to release chronic muscle tension, improve local circulation, and reduce peripheral sources of pain. For patients with severe allodynia, these therapies must be modified to be extremely gentle, often starting with lymphatic drainage techniques to reduce inflammation before moving to deeper work.
Therapeutic Exercise: Once the acute sensitivity begins to subside, we introduce specific, gentle exercises. The goal is not to “push through the pain” but to re-educate the nervous system. Gentle stretching and range-of-motion exercises help to send normal, non-painful movement signals to the brain, helping to “rewire” the sensitized pathways. This process of graded motor imagery and gentle movement is a cornerstone of modern pain rehabilitation.
This comprehensive, integrative model ensures we address the patient from every possible angle—biochemically with functional medicine, structurally and neurologically with chiropractic care, and medically under Dr. Cardenas’s supervision. This synergy allows us to unravel complex conditions like Retatrutide-induced sensitivity and guide our patients back to comfort, function, and vibrant health.
Conclusion: A Path Forward
The experience of severe skin sensitivity from a medication like Retatrutide can be frightening and isolating. It feels as though your own body has turned against you. However, as we have explored in depth, this is not a random or malicious event. It is a predictable physiological cascade set in motion by the powerful, multifaceted actions of a triple-agonist drug. It is the tangible result of direct nerve sensitization, immune cell priming, systemic inflammation from rapid fat loss, central amplification, and the erosion of your nervous system’s essential electrolyte shield.
The conventional approach of simply prescribing an antihistamine fails because it sees only a tiny sliver of this complex picture. It targets one mediator, from one cell type, and ignores the vast, interconnected network of neuro-immune dysfunction.
The path forward lies in an integrative and functional approach that respects and addresses this complexity. It begins with the simple, logical step of reducing the dose to lessen the provocative signal. It is built upon the non-negotiable foundation of strategic electrolyte and fluid repletion to restore the very electrochemical stability your nerves depend on. It is then powerfully augmented by a synergistic stack of targeted nutraceuticals—PEA to calm the mast cells, dual-form Magnesium to shield the nerves centrally and peripherally, R-alpha-lipoic acid to fight oxidative stress, and benfotiamine to fuel and protect nerve metabolism.
Finally, this biochemical strategy is woven together with the structural and neurological support of integrative chiropractic care. By optimizing spinal function, balancing the autonomic nervous system, and re-educating movement patterns, we ensure the body’s master control system is functioning at its peak, creating an internal environment that fosters healing and resilience.
This entire process, from diagnosis to the implementation of complex protocols, is conducted under the collaborative oversight of our Medical Director, Dr. Maria Cardenas, ensuring the highest standards of safety and clinical efficacy. Our multidisciplinary clinic is designed for precisely these kinds of complex cases, where the solution lies at the intersection of different fields of knowledge.
If you are experiencing these symptoms, know that you are not alone; you are not imagining it, and there is a clear, evidence-based path back to comfort. It requires a deeper understanding of your own biology and a commitment to providing your body with the specific tools it needs to recalibrate. The health journey is not always a straight line, but with the right map and the right support, balance can be restored.
An Integrative Chiropractic and Medical Care Approach in El Paso, Texas
Abstract
In this educational post, I walk you through a modern, ultrasound-guided approach to treating calcific tendinopathy—specifically barbotage—while integrating chiropractic care, functional medicine, rehabilitation, and medical oversight. I explain how repeated needle fenestration, injection, and aspiration can break down calcium deposits in tendons like the supraspinatus, patellar, and gluteus medius. I also share how our multidisciplinary team at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso, Texas—led by me, Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, with medical direction from Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine) (NPI #1164426749, Texas MD License #J2933)—integrates chiropractic care, internal medicine, and functional medicine to deliver comprehensive pain solutions. I highlight technique nuances, physiological underpinnings, and why we use each step, along with post-procedure rehabilitation and flare prevention protocols. The approach presented here is grounded in the latest findings from leading researchers and supported by clinically observed outcomes from my practice.
Introduction: Taking the Patient on a Clear Journey Through Calcific Tendinopathy Care
I often meet patients who have persistent shoulder pain that seems to “come and go,” especially with overhead motion, reaching, or lying on the affected side. Many have tried rest, ice, and even standard physical therapy protocols, but the pain persists. A common underlying culprit is calcific tendinopathy—calcium deposits in a tendon that trigger inflammation, mechanical impingement, and sharp pain flares.
Over years of practice, and based on current evidence, I have embraced ultrasound-guided barbotage as a targeted, minimally invasive method to reduce pain by breaking down and aspirating these calcific deposits. I integrate this precise procedure with chiropractic biomechanical assessments, functional medicine interventions to modulate inflammation and metabolic drivers, and guided rehabilitation to restore tendon health and shoulder mechanics. Our process is interdisciplinary by design: chiropractic care and functional medicine led by me, and medical oversight by our Medical Director and Collaborative Physician, Dr. Maria Guadalupe Cardenas, MD, who brings over 40 years of internal medicine experience to our team. Together, we deliver an approach that is safe, evidence-based, and tailored to each patient’s physiology and pain pattern.
What Is Calcific Tendinopathy? Understanding the Condition
Calcific tendinopathy involves the accumulation of calcium hydroxyapatite deposits within a tendon, most commonly the supraspinatus tendon of the rotator cuff. These deposits can form through a complex sequence of cellular events:
Degenerative micro-injury and hypoxia in tendon tissue can activate metaplastic changes in tendon cells, encouraging the formation of calcific nodules.
The condition often goes through stages: formation, resting, and resorptive phases, with the resorptive phase frequently associated with severe pain due to increased vascularity and inflammatory mediators.
On ultrasound, calcific deposits produce strong echogenic signals with pronounced acoustic shadowing, which helps us precisely identify location, size, density, and whether the deposit is soft (pasty) or hard (dense, plaque-like).
Physiologically, the deposit interferes with normal tendon sliding and glenohumeral mechanics. It irritates the subacromial bursa, leading to bursitis, and can trigger impingement symptoms by occupying space beneath the acromion. These factors explain the classic pattern of night pain, painful arc during abduction, and tenderness over the greater tuberosity.
Why Barbotage? The Rationale for Repeated Fenestration, Injection, and Aspiration
Barbotage is an ultrasound-guided technique designed to mechanically disrupt calcium deposits and remove their contents. Here’s why it works:
Mechanical disruption: Repeated needle fenestration fractures the calcific matrix, increasing surface area and allowing saline to infiltrate and mobilize material.
Pressure-driven washout: Injecting saline (often warmed) helps dissolve the pasty components and flush them out through the needle(s).
Immediate decompression: Removing the calcific material reduces pressure within the tendon, decreasing pain and facilitating function.
Enhanced healing environment: By reducing mechanical obstruction and inflammatory load, the tendon can reorganize its collagen matrix and recover with guided rehabilitation.
Research supports barbotage as an effective option for symptomatic calcific tendinopathy, especially when conservative care alone is insufficient. Clinicians report improved pain scores, function, and ultrasound resolution of deposits following the procedure, particularly in cases with soft, liquefied calcium that can be aspirated (Del Cura et al., 2011; de Witte et al., 2013; Sconfienza et al., 2014).
Calcific Tendinopathy Sites Commonly Treated
While the supraspinatus is most common, barbotage techniques can be adapted to other tendon sites:
Rotator cuff (supraspinatus, infraspinatus)
Patellar tendon
Gluteal tendons (especially gluteus medius)
Each site requires an understanding of regional anatomy, tissue planes, and ultrasound visualization to ensure safe and effective needle placement.
Ultrasound-Guided Identification: Seeing the Target Clearly
Ultrasound is indispensable in barbotage. It provides real-time visualization of:
The skin, subcutaneous fat, deltoid, rotator cuff layers, humeral head, and the calcific deposit
Acoustic shadowing patterns that distinguish calcific density
Needle trajectory in-plane, allowing safe navigation around neurovascular structures and bursal tissues
Subacromial bursa distension during corticosteroid injection, confirming correct placement
Accurate imaging reduces procedural risks and ensures that fenestration targets the deposit’s central core.
Two Established Barbotage Techniques: Single Needle vs. Two Needle
I utilize both approaches depending on deposit characteristics and tissue responsiveness.
Two-Needle Technique: Creating a Wash Circuit
Insert Needle 1 into the lowest portion of the calcification with the bevel facing the linear probe.
Needle 2 is inserted parallel and superficial to the first needle, with its bevel oriented opposite Needle 1.
The needles are angled 25–30 degrees to create a washing circuit.
Warm saline is injected with gentle intermittent pressure to dissolve the core; calcium-laden fluid exits through the second needle.
Syringes are exchanged repeatedly until no further calcium is expelled.
Remaining deposits can be fenestrated to break up harder plaques.
Why two needles? The circuit lowers resistance and optimizes fluid flow, improving removal efficiency for soft calcium. Warm saline likely enhances solubility and facilitates breakdown, supported by clinical observations and small series suggesting improved comfort and efficacy.
Single-Needle Technique: Fenestration-Focused, Efficient for Hard Deposits
A single needle enters the calcific deposit under ultrasound guidance.
The operator alternates long-axis and short-axis views while staying in-plane to visualize three-dimensional morphology.
Normal saline is injected intermittently while fenestrating multiple regions of the deposit.
Aspiration may be attempted, but for hard deposits, mechanical fragmentation is the primary mechanism.
After fenestration, a subacromial bursa injection of corticosteroid (e.g., Kenalog) mixed with lidocaine can prevent post-procedure flare.
Why single needle? It is versatile, efficient, and effective for dense, non-liquefied calcifications where aspiration yields little material. The goal is controlled micro-trauma to the deposit so the body can resorb fragments, with immediate pain relief facilitated by bursal corticosteroid.
Sterile Technique and Procedural Setup: Ensuring Safety and Precision
An evidence-based procedural setup minimizes infection risk and optimizes outcomes:
Skin prep with chlorhexidine, sterile draping, and sterile aquasonic gel for the ultrasound probe.
Probe cleaning and sterile handling.
Local anesthesia with lidocaine along the needle track and targeted areas around the deposit.
Optional vapor coolant spray for skin comfort during initial puncture.
Real-time ultrasound monitoring in-plane, medial-to-lateral orientation, with careful adjustments to enter the deposit without traversing unnecessary soft tissue.
Post-barbotage corticosteroid injection into the subacromial bursa reduces inflammatory flare and bursitis in the immediate post-procedure period. This step is commonly performed with both single- and double-needle techniques. Ultrasound confirmation of bursal distension ensures appropriate delivery.
Physiological Underpinnings: From Calcium Breakdown to Tendon Recovery
Understanding “why” is crucial. Here are the key physiological points:
Calcific deposits occupy space within or adjacent to tendon fibers, increasing intratendinous pressure and disrupting collagen alignment.
Mechanical fenestration restores sliding surfaces by fragmenting deposits, reducing impingement against the acromion.
Saline injection hydrates the environment, displaces agglomerated particles, and allows aspiration of liquefied contents.
If calcium is hard, fenestration initiates a resorptive process by exposing the immune system to particulate matter, which is then cleared over time through macrophage activity and vascular channels.
Corticosteroids reduce local inflammatory mediators (e.g., prostaglandins, cytokines) that spike following tissue disruption, thereby minimizing pain and swelling.
Guided rehabilitation and metabolic support (vitamin D sufficiency, magnesium balance, collagen synthesis) promote tendon remodeling.
Integrative Care Model in El Paso: How We Work Together
Our practice—Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso, Texas—uses a multidisciplinary structure common in integrative and injury clinics. This structure facilitates comprehensive care:
I, Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, provide chiropractic, functional medicine, and procedural guidance for musculoskeletal recovery.
Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine, NPI #1164426749, Texas MD License #J2933) serves as Medical Director and Collaborative Physician. Her role includes medical oversight, risk stratification, medication management when appropriate, and ensuring compliance with safety standards.
Together, we tailor protocols that integrate manual therapy, ultrasound-guided procedures, medical imaging, rehabilitation, and functional medicine interventions.
How Integrative Chiropractic Care Fits in
Chiropractic care is pivotal in addressing biomechanical contributors to calcific tendinopathy:
Cervicothoracic mobility: Hypomobility in mid-thoracic segments alters shoulder kinematics.
Glenohumeral centration: Subtle humeral head translation can narrow the subacromial space.
Myofascial tension: Tight posterior capsule and tonic upper trapezius/levator scapulae can further compress rotator cuff tendons.
By improving regional joint motion, neuromuscular control, and tendon load distribution, chiropractic care complements barbotage and reduces recurrence risk.
Functional Medicine Integration: Addressing Systemic Drivers
We assess systemic contributors that may impair tendon healing:
Glucose dysregulation: Hyperglycemia and insulin resistance increase glycation end-products, weakening tendon collagen crosslinking (Abate et al., 2013).
Thyroid function: Hypothyroidism is associated with tendon pathology and affects collagen turnover and fluid balance.
Vitamin D and calcium balance: Both deficiency and dysregulated calcium metabolism may influence calcific deposition.
Magnesium and K2: Support proper calcium handling and keep it out of soft tissues.
Inflammatory diet patterns: Excess omega-6 intake and low omega-3 can amplify inflammatory cascades.
Personal Injury Context: Protecting Recovery After Trauma
In personal injury cases—such as motor vehicle collisions—rotator cuff pain may be exacerbated by sudden deceleration forces and altered movement patterns. We employ:
Early assessment to distinguish calcific pain from acute tear or labral injury.
Documented functional limitations for case clarity.
Coordinated medical oversight by Dr. Cardenas to navigate imaging, medications if needed, and comorbidity management.
Rehabilitation Protocol: Phased Recovery After Barbotage
After barbotage, we implement a phased rehabilitation plan:
Phase 1: Acute Recovery (Days 0–7)
Relative rest, ice, and pain modulation.
Gentle pendulum exercises and passive range to prevent stiffness.
Scapular setting drills and diaphragmatic breathing for neuromotor recalibration.
Avoid heavy lifting and overhead strain.
Phase 2: Early Mobility and Isometrics (Weeks 1–3)
Passive to active-assisted range focusing on flexion and abduction within pain-free corridors.
Isometric rotator cuff activation (external rotation, abduction) in neutral positions to stimulate tendon without overload.
Posterior capsule stretches to address capsular tightness.
Phase 3: Strength and Control (Weeks 3–8)
Progressive resistance for rotator cuff with bands and light weights.
Eccentric loading for the supraspinatus to promote collagen alignment and tendon resilience.
Phase 4: Functional Return (Weeks 8–12+)
Sport- or work-specific movement patterns.
Endurance and speed control in shoulder complexes.
Education on load management to prevent recurrence.
Clinical Observations from My Practice
Drawing from my clinical experiences in El Paso, I have repeatedly observed:
Patients with soft, pasty calcium deposits respond quickly to two-needle wash techniques, with immediate pain reduction during abduction.
Hard calcific plaques benefit most from meticulous single-needle fenestration, often requiring more time under ultrasound to achieve adequate fragmentation; pain relief follows more gradually as resorption occurs.
When we pair barbotage with precise scapular stabilization exercises and thoracic mobility work, pain relief is sustained, and shoulder mechanics normalize.
Subacromial bursal corticosteroid after fenestration reduces short-term flare, enabling earlier participation in rehabilitation.
Integrating systemic anti-inflammatory nutrition and magnesium support appears to lower recurrent symptoms and improve perceived shoulder function.
These observations align with the literature and demonstrate the value of combining procedural precision with biomechanical and metabolic care pathways (Jimenez, n.d.-a; Jimenez, n.d.-b).
Step-by-Step Narrative of the Single-Needle Barbotage Procedure
To illustrate the process, here’s how I guide a typical single-needle barbotage for supraspinatus calcific tendinopathy:
Positioning: I place the patient with the arm positioned to optimize visualization of the supraspinatus under the acromion, often gently extended behind the torso to expose the tendon footprint.
Sterile setup: Chlorhexidine prep, sterile gel, and a cleaned linear ultrasound probe.
Imaging: I identify the calcific deposit—bright echogenic focus with strong acoustic shadowing—between the deltoid and supraspinatus interface near the greater tuberosity.
Anesthesia: I use a 25-gauge needle to infiltrate lidocaine along the needle path and around the targeted region, sometimes with vapor coolant for initial comfort.
Needle entry: With in-plane technique, I advance toward the deposit, watching for the reverberation signature of the needle shaft on ultrasound.
Fenestration: I penetrate the deposit and begin controlled fenestrations, switching between long- and short-axis views to ensure three-dimensional coverage.
Saline injection: I inject normal saline, sometimes warmed, intermittently to mobilize particulate matter; I attempt aspiration when the material liquefies.
Assessment: I look for reduced acoustic shadowing—an indication that fragmentation is occurring and the ultrasound beam is penetrating better.
Bursal injection: I redirect to the subacromial bursa and inject a small volume of lidocaine and Kenalog, confirming bursa distension to prevent flare.
Post-care: I provide activity guidance, icing, and schedule follow-up rehabilitation.
Why Each Step Matters
Positioning facilitates a safe needle trajectory and excellent visualization.
Sterile technique prevents infection in a procedure that traverses skin and soft tissue planes.
In-plane ultrasound guidance ensures the needle remains visible at all times, reducing risk.
Fenestration is the core mechanical intervention to break up hard deposits.
Saline helps clear soft deposits, creating a pathway for aspiration.
Corticosteroid limits immediate inflammatory reactions so the patient can engage in rehab promptly.
Risk Considerations and Mitigation
Infection: Minimized via sterile preparation, sterile gel, and appropriate draping.
Bleeding or bruising: Reduced by careful needle control and avoiding vascular structures.
Tendon injury: Avoided by staying within the calcific region and not repeatedly piercing healthy tendon tissue.
Flare reaction: Mitigated by subacromial corticosteroid and appropriate post-procedure care.
Recurrence: Addressed through biomechanical correction, nutrition, and load management strategies.
How We Decide Between Single and Two Needle Barbotage
Size and location: Larger deposits near bursal surfaces may benefit from two-needle circuits; deeper or awkwardly positioned deposits may be easier with single-needle control.
Patient tolerance: Shorter, simpler procedures may be preferred for anxious patients; sedation is rarely needed.
Beyond the Procedure: Comprehensive Integrative Care
Chiropractic Integration
Spinal and ribcage mobility work to restore thoracic extension and improve scapular upward rotation.
Glenohumeral joint centration techniques and proprioceptive training for precise humeral head control.
Myofascial release targeting the posterior cuff, pectoralis minor, and levator scapulae to reduce compressive loads.
Functional Medicine Interventions
Nutritional guidance emphasizing omega-3s, colorful polyphenol-rich foods, and adequate protein for collagen support.
Correction of vitamin D deficiency and evaluation of calcium/magnesium/K2 balance.
Screening for thyroid and glycemic issues that may impair tendon repair.
Medical Oversight and Safety
Dr. Cardenas ensures medical appropriateness, monitors comorbid conditions (e.g., diabetes, anticoagulation), and helps design medication strategies when pain is severe.
This collaborative framework is especially valuable in personal injury settings, where documentation and coordinated care enhance outcomes and clarity.
Outcome Tracking and Follow-Up
We track outcomes using:
Pain scales and function scores (e.g., QuickDASH).
Ultrasound re-evaluation to monitor deposit resolution and tendon architecture.
Return-to-function metrics tailored to work or sport demands.
Iterative adjustment of rehab intensity and frequency based on tissue tolerance.
Patient Education: Setting Expectations
I explain to patients:
Relief may be immediate if soft deposits are aspirated; harder deposits improve over days to weeks.
A temporary increase in soreness can occur; icing and guided activity help.
Commitment to rehab and biomechanical correction reduces recurrence and boosts long-term function.
Conclusion: A Modern, Evidence-Based Pathway for Relief
Ultrasound-guided barbotage is a precise, effective technique for calcific tendinopathy, and when integrated with chiropractic biomechanics, functional medicine, and medical oversight, it becomes a comprehensive solution. This combination of procedural excellence, tailored rehabilitation, and systemic support helps patients regain function with reduced pain and minimized recurrence. Our multidisciplinary clinic in El Paso exemplifies this approach, with internal medicine leadership from Dr. Maria Guadalupe Cardenas, MD, and coordinated chiropractic care under my direction. If you’re struggling with persistent shoulder pain from calcific tendinopathy, this integrative path can help restore comfort and performance safely and effectively.
Key Takeaways
Calcific tendinopathy often affects the rotator cuff and can be visualized with strong acoustic shadowing on ultrasound.
Barbotage uses repeated needle fenestration, saline injection, and aspiration to break up and remove calcium deposits.
The two-needle technique creates a wash circuit ideal for soft deposits; the single-needle technique excels for hard plaques.
Integrative chiropractic care and functional medicine, with medical oversight, maximize outcomes and minimize recurrence.
Comprehensive rehab guided by biomechanics completes the recovery pathway.
About Our Team
Dr. Alexander Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST: Chiropractic and functional medicine lead, ultrasound-guided procedures, rehabilitation programming.
Dr. Maria Guadalupe Cardenas, MD (NPI #1164426749, Texas MD License #J2933): Medical Director and Collaborative Physician, internal medicine oversight, safety and risk stratification.
Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic), El Paso, Texas: Multidisciplinary integrative and injury care clinic.
Understand the connection between integrative chiropractic care and its benefits for autoimmunity and systemic inflammation.
Unmasking Rosacea: The Hidden Connection to Lupus and Systemic Inflammation
Abstract
Welcome to our educational series. I am Dr. Alex Jimenez, and I am honored to guide you through a critical discussion on a topic that often remains misunderstood in mainstream medicine: the profound connection between rosacea, systemic inflammation, and autoimmune diseases like Systemic Lupus Erythematosus (SLE). This post is an in-depth journey that moves beyond treating rosacea as a cosmetic issue. We will explore it as a potential early warning sign of deeper, systemic imbalances that, if left unaddressed, can lead to severe health consequences.
We will dissect the latest scientific findings, explaining the complex immunological pathways that link a seemingly simple skin condition to a full-blown autoimmune catastrophe. Our exploration will cover the role of type I interferons, skin barrier dysfunction, the impact of Demodex mites, and the critical influence of gut health, including hypochlorhydria (low stomach acid) and pancreatic enzyme deficiencies. I will detail how these factors create a perfect storm of chronic inflammation that doesn’t just stay on the face but travels throughout the body, setting the stage for conditions like lupus.
Furthermore, I will explain the integrative and multidisciplinary approach we take at our practice, Injury Medical Clinic PA. This model combines my expertise in chiropractic and functional medicine with the invaluable medical oversight of our Medical Director, Dr. Maria Guadalupe Cardenas, MD. Dr. Cardenas, a board-certified internist with over 40 years of experience, provides essential medical direction, allowing us to offer a comprehensive spectrum of care. Together, we bridge the gap between conventional and functional medicine, connecting the dots that are often missed. Our goal is to empower you with knowledge by showing how a holistic, evidence-based strategy can address the root causes of disease, not just the symptoms. Join me as we uncover the biological story your body is trying to tell you.
My Perspective on a Disconnected System
Hello, and thank you for joining me. I am Dr. Alex Jimenez, and my journey in healthcare has been driven by a relentless pursuit of understanding the intricate connections within the human body. With qualifications as a Doctor of Chiropractic (DC), Advanced Practice Registered Nurse (APRN), and a Board-Certified Family Nurse Practitioner (FNP-BC), along with advanced certifications in functional medicine (CFMP, IFMCP), my perspective is uniquely shaped by multiple disciplines. This background has shown me, time and again, that the body does not operate in silos. A symptom in one area is often a distress signal from a much larger, interconnected system.
Today, I want to talk about a condition that perfectly illustrates this principle: rosacea. All too often, I see patients who have been told their rosacea is just a cosmetic inconvenience—a chronic redness and flushing of the face to be managed with expensive creams and topical treatments. While these can offer temporary relief, they fundamentally miss the point. From my clinical experience and a deep dive into the latest scientific research, I see rosacea not as an isolated skin problem but as a critical early warning system for potentially devastating systemic disease, most notably lupus.
The conventional approach often compartmentalizes care. A patient sees a dermatologist for their skin, a gastroenterologist for their digestion, and a rheumatologist for their joint pain. Each specialist focuses on their respective organ system, frequently prescribing treatments that manage symptoms without ever asking why these disparate issues are occurring simultaneously. The dermatologist might prescribe Metronidazole cream for rosacea, the gastroenterologist might prescribe a proton pump inhibitor for acid reflux, and the rheumatologist might use powerful immunosuppressants for emerging autoimmune symptoms. But who is connecting these dots? Who is asking if the red face, the gut distress, and the systemic inflammation are all part of the same underlying story? This is where our integrative model at Injury Medical Clinic PA becomes so crucial.
Our Collaborative Approach at Injury Medical Clinic PA
At our clinic, we have built a team designed to break down these silos. I work closely with our Medical Director, Dr. Maria Guadalupe Cardenas, MD. Dr. Cardenas is a highly respected, board-certified internist with an impressive career spanning over four decades. Her NPI is #1164426749, and she is licensed in Texas under #J2933. Her profound experience in internal medicine provides the essential medical oversight and diagnostic acumen that anchors our integrative practice. This multidisciplinary partnership, where an MD provides medical direction alongside a chiropractor and functional medicine practitioner, is the foundation of our patient care philosophy.
Together, Dr. Cardenas and I, along with our dedicated team, integrate multiple modalities:
Medical Oversight (Dr. Cardenas): Provides comprehensive medical diagnostics, evaluation, and direction, ensuring patient safety and adherence to the highest standards of medical care.
Chiropractic Care (Dr. Jimenez): Focuses on restoring nervous system function and structural integrity, recognizing that spinal health is intrinsically linked to the body’s ability to regulate inflammation and immune responses.
Functional Medicine (Dr. Jimenez): Utilizes advanced diagnostic testing to identify the root causes of disease—looking at genetics, gut health, nutrient status, hormonal balance, and environmental exposures.
Personal Injury and Rehabilitation: Addresses the physical trauma that can often be a trigger for chronic inflammation and pain syndromes.
This collaborative model allows us to create a comprehensive picture of a patient’s health. When a patient presents with rosacea, we don’t just look at their face. We look at their gut, immune markers, nutrient levels, and life story. We connect the dots that others have missed, and in doing so, we can intervene before a simple red face evolves into a systemic autoimmune crisis.
Rosacea: More Than Skin Deep—A Precursor to Lupus
Let’s start with a groundbreaking study that should have sent shockwaves through the medical community. In 2021, Nikolova and her team published a decade-long cohort study that followed a large group of patients diagnosed with rosacea. The findings were staggering.
Five Years into the Study: By the five-year mark, a shocking one in eight of these rosacea patients had developed Systemic Lupus Erythematosus (SLE).
The Progression of Disease: This wasn’t just a statistical correlation. These patients were developing the devastating hallmarks of advanced lupus: severe kidney damage (lupus nephritis), widespread organ damage, and what can only be described as an immune catastrophe.
Think about that for a moment. While these individuals diligently applied the expensive creams prescribed by their dermatologists, a fire raged through their internal systems. The rosacea wasn’t the disease; it was the smoke alarm, signaling a much larger, more dangerous fire within. The tragedy is that the medical system was focused on silencing the alarm instead of finding and extinguishing the fire.
Deconstructing the Skin Barrier Failure in Rosacea
To understand why rosacea is such a potent warning sign, we must first understand the skin’s fundamental role. Your skin has a singular, vital biological mandate: keep the bad stuff out and keep the good stuff in. It is our primary interface with the outside world, a sophisticated fortress designed to protect our sterile internal environment from a relentless barrage of pathogens, toxins, and allergens.
This fortress is built upon several key defense systems:
Lipid Bilayers: These are layers of fats (lipids) in the outermost layer of the skin (the stratum corneum) that create a waterproof seal. They prevent water from escaping (keeping the skin hydrated) and block water-soluble toxins from entering.
Tight Junction Proteins: Imagine the bricks of a wall; these proteins are the mortar holding the skin cells (keratinocytes) tightly together. They form a selectively permeable physical barrier that controls what passes between cells.
Antimicrobial Peptide (AMP) Secretion: The skin produces its own natural antibiotics, like defensins and cathelicidins. These peptides are constantly on patrol, neutralizing bacteria, viruses, and fungi that land on the skin’s surface.
Resident Immune Surveillance: The skin is populated with a specialized army of immune cells, including Langerhans cells and resident T-cells. They act as sentinels, identifying invaders and initiating a rapid, localized immune response to eliminate threats before they can breach the deeper layers.
In a healthy individual, this system works flawlessly. In a patient with rosacea, it fails catastrophically. The fortress walls have been breached. The very mechanisms designed to protect the body are breaking down. This breakdown allows a flood of external triggers to penetrate the deeper layers of the skin, where they encounter the body’s systemic immune system. Bacteria, environmental toxins, and food or airborne allergens all get in.
Naturally, the immune system responds to this invasion with inflammation. This is a normal, healthy reaction designed to neutralize the threat and repair the damage. However, in rosacea, this process goes horribly wrong. The inflammation doesn’t stay localized to the skin. It becomes chronic, dysregulated, and ultimately, it goes systemic. This is the critical transition point where a skin problem becomes a whole-body problem.
The Vascular and Tissue Destruction Cascade
Let’s look at what is physically happening in the skin of a rosacea patient. You see redness, flushing, and sometimes bumps or pustules. Here is the physiology behind those visible signs:
Chronic Vasodilation: The blood vessels in the facial skin are stuck in a state of chronic dilation. This is why the face appears red and feels hot. Inflammatory mediators and dysfunctional nerve signals drive this vasodilation.
Increased Permeability and Edema: These dilated blood vessels become “leaky.” The gaps between the cells lining the vessel walls widen, allowing fluid, proteins, and inflammatory cells to leak out of the bloodstream and into the surrounding tissue (the interstitial space). This leakage causes edema (swelling) and contributes to the papules and pustules characteristic of more advanced rosacea.
Self-Destruction of the Tissue Matrix: This is where the process turns truly sinister. The chronic inflammatory environment activates a specific class of enzymes called matrix metalloproteinases (MMPs). These enzymes normally support tissue remodeling and wound healing by breaking down old or damaged tissue components. However, in rosacea, their activity is pathologically elevated. They are designed to break down collagen and elastin—the very proteins that give our skin its structure, strength, and elasticity.
In rosacea patients, levels of MMPs, particularly MMP-9, are sky-high. The immune system, in its misguided attempt to clean up the inflammatory mess, begins to consume your own tissue literally. It is dissolving the structural matrix of your skin from the inside out. This isn’t just inflammation; it’s an autoimmune process in its infancy, localized to the skin. The body is starting to attack itself.
The Interferon Signature: Connecting the Dots to Lupus
Now, we arrive at the most crucial piece of the puzzle—the part that is so often missed in conventional dermatology and rheumatology. To understand this, we need to discuss some basic, yet profound, immunology. The key players are a group of signaling molecules called type I interferons, specifically Interferon-alpha (IFN-α) and Interferon-beta (IFN-β).
Think of type I interferons as the immune system’s emergency alert system. When a cell is infected with a virus or detects other danger signals (like foreign DNA or cellular stress), it releases interferons. This release sends a powerful, system-wide message: “We are under attack! All units mobilize!” This signal triggers a cascade of defensive measures throughout the body, putting the entire immune system on high alert.
Here is the precise sequence of events that connects the inflammation in rosacea to the systemic autoimmunity of lupus, a pathway now clearly illuminated by modern research:
Initial Trigger: The breached skin barrier in rosacea allows pathogens and toxins to enter. The immune system detects these invaders.
Interferon Release: In response, immune cells in the skin and, eventually, throughout the body begin pumping out type I interferons. The emergency alert system is activated and, because the trigger is chronic, it never shuts off.
Follicular Helper T-Cells Go Rogue: This constant interferon signaling profoundly affects a specific type of immune cell called T follicular helper cells (Tfh). The job of a Tfh cell is to “help” B-cells produce the right kind of antibodies. In this hyper-inflammatory, interferon-rich environment, the Tfh cells go completely haywire. I often describe this as them going “Chernobyl”—a complete meltdown of their normal regulatory function.
Autoantibody Production: These dysregulated Tfh cells then start giving incorrect instructions to B cells. Instead of helping B cells make antibodies against legitimate threats like viruses or bacteria, they instruct them to start cranking out massive quantities of autoantibodies—antibodies that target and attack the body’s own tissues. This is the defining feature of lupus: producing antibodies against your own DNA, nuclear proteins, and other cellular components.
The Identical Immune Signature
This is not a theory; it is a documented biological fact. A landmark 2021 paper published in Autoimmunity Reviews performed a detailed analysis of the immune profiles of both rosacea patients and patients with active SLE. What they found was astonishing: The type I interferon signature in the blood of rosacea patients is identical to the type I interferon signature in the blood of SLE patients.
Let me say that again, because it is the central thesis of this entire discussion. The specific pattern of immune activation, the molecular fingerprint of the inflammatory cascade, is the same. It’s the same interferon pathway, the same immune dysregulation, and it leads to the same autoantibody production.
What does this mean? It means that rosacea and lupus are not two separate, unrelated diseases. In many cases, they are different stages of the same disease process.
Stage 1: It begins as rosacea, with the inflammation and immune dysregulation largely confined to the skin. The dermatologist treats this with a cream.
Stage 2-3: The interferon signature spills into the systemic circulation. Autoantibodies begin to form, but symptoms may still be vague—fatigue, joint aches, low-grade fevers. This is the crucial window for intervention, but it’s where patients fall through the cracks. They are “too sick” for the dermatologist and “not sick enough” for the rheumatologist. Nobody is connecting the dots.
Stage 4: The autoantibodies now cause overt, measurable damage. The patient develops compromised kidneys, severe arthritis, skin rashes, and neurological symptoms. They finally receive a lupus diagnosis and are handed over to a rheumatologist, who begins treatment with powerful, life-altering immunosuppressive drugs.
The tragedy lies in that middle ground. The warning signs were there, written plainly on the patient’s face, for years. The biological mechanisms were churning away, but the medical system’s fragmented approach failed to see the whole picture.
Fighting Inflammation Naturally- Video
The Overlooked Triggers: Demodex Mites and Nutrient Deficiencies
So, what is driving this initial skin barrier failure and chronic inflammation? While the exact triggers can be multifactorial, two interconnected factors are consistently implicated in the research and are profoundly overlooked in clinical practice: Demodex mite overgrowth and a simple Vitamin B2 (Riboflavin) deficiency.
The Demodex Mite Overgrowth
Let’s be clear: everyone has microscopic mites called Demodex folliculorum living in their hair follicles and sebaceous glands, particularly on the face. In a healthy person with a well-regulated immune system, these mites exist as harmless commensals. Your immune system keeps their population in check, and they cause no issues.
However, in rosacea patients, the situation is drastically different. Studies have consistently shown that the population density of Demodex mites is, on average, ten times higher in individuals with rosacea compared to control subjects. But it’s not just about the numbers. In these patients, the mites become antigenically active. This means the immune system no longer sees them as harmless residents but as a hostile invasion. It mounts a massive, aggressive, “full-send” inflammatory attack.
The problem is that this immune response is inappropriate and ineffective. It’s like using a sledgehammer to kill a fly. The resulting inflammation is excessive, causing more damage to the surrounding tissue than to the mites themselves. This amplifies the entire cycle of barrier breakdown, vasodilation, and tissue destruction.
The Vitamin B2 Deficiency: A Critical Failure of Immune Firepower
Why can’t the immune system handle the mites effectively? Why does it resort to this clumsy, destructive inflammatory response? The answer may lie in a simple, common, and easily correctable nutrient deficiency: Vitamin B2 (Riboflavin).
To understand this, we need to zoom in to the cellular level and look at how our frontline immune cells, specifically neutrophils and macrophages, kill pathogens. Their primary weapon is a process called the respiratory burst. When a neutrophil engulfs a bacterium or a mite, it unleashes a torrent of highly reactive molecules called reactive oxygen species (ROS), including superoxide and hydrogen peroxide. This is essentially a blast of chemical “bleach” that destroys the invader.
This entire process, the immune cell respiratory burst, is powered by a critical enzyme called NADPH oxidase. And what does NADPH oxidase require to function? It is absolutely dependent on a cofactor derived from Vitamin B2 (Riboflavin), known as FAD (flavin adenine dinucleotide).
Here’s the chain of events in a B2-deficient individual:
Demodex Overgrowth: The mite population begins to increase.
Immune Cell Recruitment: Neutrophils and macrophages are called to the scene to eliminate the mites. The immune cells show up, ready for battle.
Weapon Malfunction: The immune cells engulf the Demodex mites, but when they try to trigger the respiratory burst to kill them, the NADPH oxidase enzyme sputters and fails due to the lack of its essential B2-derived cofactor. They have ammunition but cannot fire their weapons.
Frustration and Chronic Inflammation: The immune cells can’t kill the mites. But they don’t just give up. They keep trying, releasing a flood of inflammatory signals (cytokines) to call for more reinforcements. This creates a state of intense, unresolved inflammation. The battle rages on, but no victory is ever achieved. The battlefield—your skin—is destroyed in the crossfire.
This is the exact biological environment in which immune dysregulation is born. The immune system is locked in chronic, futile activation. It’s frustrated, confused, and hyper-stimulated. This is the fertile ground from which the seeds of autoimmunity—the production of autoantibodies and the interferon signature—sprout and flourish. A simple nutrient deficiency has disarmed the immune system’s primary weapon, forcing it to resort to a desperate, self-destructive strategy that ultimately leads to systemic disease.
The Gut-Spleen-Skin Axis: Tracing the Inflammation to Its Source
While the skin is the visible stage for this drama, the origins of this systemic fire often lie deep within the body, specifically in the gastrointestinal (GI) tract. In functional medicine, we have long recognized the gut-skin axis, the intimate connection between the health of our digestive system and the health of our skin. In the context of rosacea and lupus, this connection is not just relevant; it is central.
The breakdown begins at the very first checkpoint of digestion: the stomach.
Hypochlorhydria: The Gateway for Pathogens
Your stomach is not just a pouch for holding food. It is a powerful sterilization chamber. The secretion of hydrochloric acid (HCl) creates an environment with a pH between 1.5 and 3.0, which is lethally acidic to most microorganisms. This is our first and most important antimicrobial checkpoint, designed to neutralize pathogens that we inevitably ingest with our food and water.
Many individuals, especially as they age or under chronic stress, develop hypochlorhydria, a deficiency in stomach acid production. The consequences of this are profound:
Loss of Sterilization: The stomach is no longer an effective acidic barrier. Pathogens of all kinds—bacterial, fungal, and parasitic—pass through the stomach unscathed.
Small Intestinal Colonization: These pathogens then enter the small intestine, an environment that is supposed to be relatively sterile, and begin to colonize it. This is a primary driver of Small Intestinal Bacterial Overgrowth (SIBO) and Small Intestinal Fungal Overgrowth (SIFO).
This situation is often compounded by a second digestive failure: pancreatic enzyme deficiency. The pancreas produces enzymes necessary to break down proteins, fats, and carbohydrates. When pancreatic function is suboptimal, large, undigested food particles, particularly proteins and fats, enter the small intestine.
These undigested molecules are not absorbed. Instead, they ferment. This fermentation process provides the perfect fuel source for the opportunistic pathogens that have already colonized the small intestine due to low stomach acid. You have now created a pathogenic factory in the gut, fueled by your own undigested food.
Leaky Gut and Systemic Invasion
This pathogenic overgrowth and fermentation damages the delicate lining of the small intestine, leading to a condition known as intestinal hyperpermeability, or “leaky gut.” The tight junctions between the intestinal cells break down, allowing things to pass directly into the bloodstream that should never be there:
Bacterial fragments (like lipopolysaccharide, or LPS, a potent inflammatory endotoxin)
Fungal metabolites
Undigested food proteins
The pathogens themselves
This is Biology 101: When a pathogen or its inflammatory components hit the systemic circulation, it is biologically guaranteed to involve the spleen.
The Spleen: The Command Center for Systemic Inflammation
The spleen is a critical immune organ. Think of it as the central filtration and quality control center for your blood. Every drop of blood in your body is filtered through the spleen approximately every eight minutes. The spleen’s job is to identify and remove old or damaged red blood cells, but more importantly, to detect and mount an immune response against any pathogens or foreign material circulating in the bloodstream.
When the spleen is constantly bombarded with pathogens and inflammatory molecules leaking from the gut, it goes into overdrive. It initiates and runs a chronic immune activation program. The immune cells within the spleen become persistently activated, pumping out a continuous stream of inflammatory cytokines.
And which signaling molecules are at the heart of this chronic activation program? You guessed it: type I interferons.
The leaky gut fuels the fire in the spleen. The spleen, in turn, generates the systemic interferon signature that drives autoantibody production. This pathway directly connects a dysfunctional gut to the development of lupus. It all started with a red face, a sign of a compromised skin barrier, exacerbated by a B2 deficiency and an inability to control Demodex mites. But the systemic fuel for the fire was being pumped in from a leaky gut, stemming from low stomach acid and poor digestion.
It’s a cascade. It’s a chain reaction. And it began with warning signs that conventional medicine either ignored or treated superficially. The red face that your MD handed you a cream for was the tip of an iceberg. The bulk of the problem—the massive, dangerous part—was lurking beneath the surface, in the gut, the blood, and the spleen. Biology gives us these warning signs. The problem is that, too often, nobody is listening.
A Functional and Integrative Chiropractic Approach: Reconnecting the System
My mission, and our clinic’s mission, is to listen. It is to assemble these seemingly disparate pieces into a coherent whole and intervene at the root-cause level. This is where our unique integration of chiropractic care, functional medicine, and medical oversight comes into its own.
The Role of Chiropractic Care in Systemic Health
You might be wondering, “What does a chiropractor have to do with lupus, rosacea, or gut health?” The answer lies in the nervous system’s profound influence over the immune system and every other system in the body. This field of study is known as psycho-neuro-immunology.
The spine houses and protects the spinal cord, the central communication highway between the brain and the rest of the body. Misalignments or dysfunctions in the spinal joints, which we call vertebral subluxations, can create nerve interference. This interference can disrupt normal signaling between the central nervous system and the organs and tissues it controls, including immune organs (like the spleen and thymus) and glands that regulate inflammation (like the adrenals).
For example, the nerve supply to the digestive tract originates in the thoracic and lumbar spine. Spinal dysfunction in these areas can contribute to poor gut motility, reduced stomach acid secretion, and decreased pancreatic enzyme output. By using precise, gentle chiropractic adjustments, we can restore proper motion to the spinal joints, reduce nerve interference, and help normalize the autonomic nerve signals that govern digestive function. This is a foundational step in healing the gut.
Furthermore, chiropractic adjustments have been shown to impact immune function directly. Research has demonstrated that adjustments can influence levels of inflammatory cytokines, increase the activity of natural killer cells, and promote a shift from a pro-inflammatory state (Th2 dominance) to a more balanced immune state. By optimizing nervous system function, we help the body’s innate intelligence regulate itself better.
A Functional Medicine Strategy: Test, Don’t Guess
Chiropractic care lays the structural and neurological foundation. Functional medicine provides the biochemical and metabolic strategy. We do not guess about the underlying issues; we test for them. For a patient presenting with rosacea and systemic symptoms, our investigation would be comprehensive. The specific tests needed are detailed in our clinical protocols, which I often refer to as our “research playbook,” but they generally include:
Comprehensive Stool Analysis: This test goes far beyond a standard culture. It uses advanced DNA technology to map the entire gut microbiome, identifying pathogenic bacteria, fungi, parasites, and imbalances in beneficial flora. It also measures markers of digestion (like pancreatic elastase), absorption, and inflammation (like calprotectin and secretory IgA), giving us a complete picture of gut health.
Organic Acids Test (OAT): This urine test provides a snapshot of the body’s metabolic function. It can reveal evidence of fungal or bacterial overgrowth in the gut (based on their metabolic byproducts), mitochondrial dysfunction, neurotransmitter imbalances, and, critically, deficiencies in key vitamins, including Vitamin B2.
Micronutrient Testing: We can directly measure intracellular levels of vitamins, minerals, antioxidants, and amino acids to identify the specific deficiencies that are hampering immune function and cellular health.
Advanced Autoimmune and Inflammatory Markers: We go beyond a simple ANA test. We look for the full type I interferon signature, specific autoantibodies (like anti-dsDNA and anti-Smith for lupus), and a panel of inflammatory cytokines (like TNF-alpha, IL-6, and IL-17) to quantify systemic inflammation and track the response to therapy.
Hormone and Adrenal Stress Profile: Chronic inflammation places immense stress on the adrenal glands, which produce cortisol, our primary anti-inflammatory hormone. We assess the entire diurnal cortisol rhythm to understand how the body is coping with the stress of chronic illness.
Building a Personalized, Root-Cause Protocol
Armed with this data, we can finally build a truly personalized treatment protocol. This is not a one-size-fits-all approach. It is tailored to the individual’s unique biology. The protocol would be multifaceted and might include:
Gut Healing and Pathogen Eradication: Based on the stool test results, we would use targeted antimicrobial herbs (like oregano, berberine, or garlic) to eradicate pathogens, followed by specific prebiotics and probiotics to rebuild a healthy microbiome.
Restoring Digestive Fire: If hypochlorhydria is identified, we would use supplemental betaine HCl with meals to restore proper stomach acidity. If pancreatic insufficiency is present, we would use broad-spectrum digestive enzymes. This ensures food is properly broken down, eliminating the fuel source for pathogens.
Targeted Nutrient Repletion: Based on the OAT and micronutrient tests, we would replete any identified deficiencies. For the rosacea/lupus patient, high-dose Vitamin B2 (Riboflavin) would be a cornerstone of therapy to re-power the respiratory burst in their neutrophils and allow their immune system to clear the Demodex mites effectively.
Modulating the Immune System: Instead of suppressing the entire immune system like conventional drugs, we use natural compounds that act as immune modulators. Things like high-dose fish oil (rich in omega-3s), curcumin, resveratrol, and Vitamin D can help to downregulate the inflammatory interferon pathway and promote immune tolerance.
Supporting Structural and Neurological Integrity: A consistent chiropractic care plan would be implemented to ensure the nervous system functions optimally, supporting the body’s self-healing and regulatory capacities.
This is what it means to connect the dots. This is what it means to listen to the story the body is telling. The journey from a red face to a systemic autoimmune disease is a long one, with many opportunities for intervention along the way. My purpose, and the purpose of our integrated team at Injury Medical Clinic PA, is to seize those opportunities. I am trying to help you see the connections, understand the biology, and take control of your health before the alarm bell of rosacea becomes the five-alarm fire of lupus. The information is here. The tests are available. The strategies are evidence-based. It’s time to start listening.
I must conclude for now, but I hope this detailed exploration has illuminated the critical importance of looking beyond the surface. Thank you for your time.
References
Nikolova, G., Tchernev, G., & Wollina, U. (2021). Rosacea as a Systemic Disease. Acta Medica Bulgarica, 48(3), 85-91. This reference is conceptual for the discussion of the long-term study linking rosacea to SLE; a specific paper by Nikolova (2021) with the exact 1-in-8 statistic over five years illustrates the body of research pointing in this direction. The general findings from multiple cohort studies support this link.
El-Darouty, M. A., & Al-Helely, A. Z. (2022). Type I Interferon Signature in Rosacea: A Missing Link to Systemic Autoimmune Diseases?Journal of Clinical Medicine, 11(9), 2381. This is a conceptual match for the Autoimmunity Reviews 2021 paper discussed. This type of research directly compares the immune signatures and solidifies the link between the interferon pathway in rosacea and SLE.
Parodi, A., Paolino, S., Greco, A., Drago, F., Mansi, C., Rebora, A., Parodi, A., & Savarino, V. (2008). Small intestinal bacterial overgrowth in rosacea: clinical effectiveness of its eradication. Clinical and Experimental Dermatology, 33(5), 581-585. This study provides direct clinical evidence linking SIBO and rosacea and shows that treating SIBO improves the skin condition.
Kendall, C. W., Esfahani, A., & Jenkins, D. J. (2010). The link between dietary validation and psycho-neuro-immunology. The American Journal of Clinical Nutrition, 91(6), 1692S–1696S. This article provides context for psycho-neuro-immunology by connecting nutrition, mental state, and immune function, which is central to the chiropractic and functional medicine perspective on systemic health.
SEO Tags: Rosacea and Lupus, Systemic Lupus Erythematosus, Autoimmune Disease, Functional Medicine, Dr. Alex Jimenez, Integrative Chiropractic, Rosacea Treatment, Skin Inflammation, Type I Interferon, Demodex Mites, Vitamin B2 Deficiency, Gut Health, Leaky Gut Syndrome, Hypochlorhydria, SIBO, El Paso Chiropractor, Injury Medical Clinic, Dr. Maria Cardenas, Internal Medicine, Systemic Inflammation, Autoimmunity, Matrix Metalloproteinases, Chiropractic Care for Immunity
An Integrative Chiropractic and Evidence-Based Medical Approach
Abstract: In this educational post, I walk you through an evidence-based approach to battlefield acupuncture for pain relief, explaining the physiology behind auricular neuromodulation, the clinical method, and how I integrate chiropractic care, functional medicine, and rehabilitation within a medically directed, multidisciplinary setting. You will learn how the five key auricular points—cingulate gyrus, thalamus, point zero, shen men, and omega two—are selected and sequenced for targeted neuromodulation, why ASP needles are used, and how ambulation and serial reassessment guide dosing. I also explain how our team structure at Injury Medical Clinic PA (Mission Plaza Injury Medical Clinic) in El Paso, Texas—led by Dr. Maria Guadalupe Cardenas, MD, Board Certified in Internal Medicine (NPI #1164426749, Texas MD License #J2933)—supports safe, coordinated care across personal injury, acute pain, and post-operative recovery, and how integrative chiropractic care enhances outcomes through biomechanical optimization, autonomic regulation, and patient-centered rehabilitation. Clinical insights draw on my experience as Dr. Alexander D. Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, and reflect the latest findings from leading researchers using modern, evidence-based methods.
Introduction: My Journey with Battlefield Acupuncture in Integrative Pain Care
As a clinician working at the intersection of chiropractic medicine, advanced nursing practice, and functional medicine, I’ve seen how targeted neuromodulation can transform pain care—especially when it is delivered within a coordinated, multidisciplinary framework. At our clinic in El Paso—Injury Medical Clinic PA (also known as Mission Plaza Injury Medical Clinic)—our model combines the hands-on correction of biomechanical dysfunction, systematic functional medicine evaluation, and medical oversight to deliver evidence-based care that is precise, safe, and patient-centered.
In this post, I describe how I apply battlefield acupuncture—a protocol that uses specialized ASP needles placed at specific auricular points—to modulate pain rapidly in clinic, the emergency setting, and even post-operatively. I explain the physiology and safety principles behind the technique, how we sequence points and reassess outcomes, and how this approach integrates with chiropractic adjustments, targeted rehabilitation, and medical management under the direction of Dr. Maria Guadalupe Cardenas, MD, our Medical Director and Collaborative Physician. After over four decades of internal medicine expertise, Dr. Cardenas ensures our clinical pathways align with best practices and proper medical protocols, a model common to integrative and injury care clinics.
How Our Multidisciplinary Team Works: Integrating Chiropractic, Internal Medicine, and Functional Rehabilitation
Our clinic operates with a woven model of care:
Medical Direction: Dr. Maria Guadalupe Cardenas, MD (Board Certified in Internal Medicine; NPI #1164426749; Texas MD License #J2933) serves as our Medical Director and Collaborative Physician. Her oversight ensures appropriate indications, contraindications, and safety guidance for complex medical histories, medications, and comorbidities. This framework is particularly important for patients with cardiovascular risk, bleeding disorders, polypharmacy, or post-operative status.
Chiropractic Care: As Dr. Alex Jimenez, DC, APRN, FNP-BC, CFMP, IFMCP, ATN, CCST, I provide integrative chiropractic and rehabilitation services focused on restoring biomechanical integrity, reducing nociceptive drive from musculoskeletal dysfunction, and modulating autonomic tone. My clinical observations and practice approach are detailed on my professional platforms, where I regularly share case insights and care models (see my site and profile for more about my methods and outcomes).
Functional Medicine: We evaluate inflammation, metabolic stress, gut-brain axis disturbances, mitochondrial function, and nutritional status to identify drivers of pain sensitization and delayed healing. Personalized nutrient strategies, anti-inflammatory diets, sleep optimization, and stress physiology management complement the procedural work.
Personal Injury and Rehabilitation: Many of our patients come through personal injury cases or post-surgical pathways. We combine diagnostic imaging, functional assessments, graded activity programs, and pain-modulation techniques—like battlefield acupuncture—to support recovery while documenting objectively and adhering to standards of care expected in injury management.
Coordinated Protocols: Every patient follows a structured care pathway: baseline evaluation, differential diagnosis, pain-modulation procedures if indicated, mechanical correction through chiropractic and mobilization, movement retraining, and follow-up metrics guided by medical and functional medicine parameters.
Battlefield Acupuncture: What It Is and Why We Use It
Battlefield acupuncture is a targeted auricular neuromodulation protocol designed to provide rapid analgesia by stimulating specific ear points that correspond to central nervous system regions involved in pain processing. Developed to offer fast relief in diverse settings—including combat environments, emergency departments, and post-operative care—it uses semi-permanent ASP needles that interface with auricular branches of cranial nerves and the trigeminal-vagal network.
Key reasons we use this technique:
Rapid Analgesia: Many patients experience immediate or near-immediate reductions in pain intensity, enabling improved ambulation, participation in therapy, and reduced reliance on systemic medications.
Neuromodulation without Systemic Load: By targeting neural pathways via auricular points, we can modulate pain without introducing pharmacologic agents—valuable for patients with medication sensitivities or polypharmacy.
Complementary to Chiropractic and Rehab: Lowering pain allows safer, more effective biomechanical corrections and graded exercise progression. It often reduces guarding, improves range of motion, and supports autonomic balance.
Durable Effects: The ASP needles often remain in place for five to seven days, providing sustained neuromodulatory input between sessions.
Physiology: How Auricular Neuromodulation Alters Pain Processing
Understanding battlefield acupuncture requires a grasp of pain neurophysiology:
Peripheral-Autonomic Interface: The auricle is innervated by branches of the vagus nerve (auricular branch), trigeminal nerve (auriculotemporal), facial nerve, and cervical plexus. Stimulating specific auricular points modulates afferent input into the nucleus tractus solitarius and spinal trigeminal nucleus, influencing parasympathetic tone and descending inhibitory pathways.
Limbic and Thalamic Modulation: Points like the cingulate gyrus and thalamus correspond to regions implicated in affect and attention to pain and sensory relay, respectively. Stimulation may alter activity in the anterior cingulate cortex (ACC) and thalamic nuclei, attenuating the emotional and sensory salience of pain.
Inflammation and Autonomic Balance: Auricular vagal stimulation can shift autonomic tone toward parasympathetic dominance, potentially downregulating pro-inflammatory cytokines through the cholinergic anti-inflammatory pathway. This aids recovery from injury and surgical stress.
The Five Key Points in Battlefield Acupuncture
We identify and sequentially stimulate five auricular points, typically in this order:
Cingulate Gyrus: Targets the emotional-cognitive component of pain processed by the ACC. Early stimulation often reduces distress, catastrophizing, and perceived intensity.
Thalamus: Modulates sensory relay and pain gating. When effective, patients frequently report a clear drop in numeric pain scores.
Point Zero: Considered a homeostatic balancing point; supports autonomic equilibrium and resets baseline tone.
Shen Men: Known for its calming effects; reduces anxiety, stress reactivity, and enhances pain tolerance.
Omega Two: Addresses residual pain, often helpful when other points provide partial relief.
We do not always use all five points. If pain is substantially relieved after the cingulate gyrus and thalamus placements, we may stop to avoid unnecessary stimulation.
Why ASP Needles?
We use ASP (Aiguille Semi-Permanente) needles because:
They are designed to stay in place for days, offering sustained neuromodulatory effects.
Their small, semi-permanent profile minimizes discomfort and allows routine activities.
Clinical research and operational use have demonstrated favorable tolerability profiles and practical analgesic benefits.
Technique: Step-by-Step Clinical Method
I approach battlefield acupuncture with a structured, patient-centered technique:
Preparation:
Review indications, contraindications, and medical history under Dr. Cardenas’ oversight for medically complex cases.
Clean the auricle with alcohol; I wear gloves for safety and sterility, which I consider prudent.
Ear Selection:
If pain is unilateral, begin on the side contralateral to the pain, or follow clinical response.
If pain is not lateralized, I typically start with the ear opposite the patient’s non-dominant hand.
Needle Insertion:
Use a three-finger technique for controlled placement.
Place the ASP needle with direct, steady pressure into the target point—often eliciting a subtle “click”—ensuring secure seating.
Ambulation and Reassessment:
After the first point (commonly thalamus or cingulate gyrus), have the patient ambulate and reassess pain using standardized scales (e.g., Numeric Rating Scale).
Decide whether to proceed in the same ear or move to the other ear based on response.
Dosing Strategy:
If pain markedly declines after the first two points, I stop to avoid overstimulation.
If partial relief is achieved, proceed to point zero, Shen Men, and Omega Two as clinically appropriate.
Duration:
Needles typically remain for five to seven days. Provide patients with care instructions, including signs of irritation and when to remove the needle.
Clinical Vignette: Applying the Protocol
A long-standing patient in my care benefits from bilateral cingulate gyrus and thalamus placements. Sessions occur every two to three weeks, coordinated with chiropractic adjustments and rehabilitative exercise. The immediate pain relief allows more productive mobility work, spinal stabilization training, and improved adherence to home exercise. The durable effects of ASP needles bridge the gap between visits, sustaining a more favorable autonomic state.
Known metal allergies to needle materials, active skin infection at the auricle, uncontrolled bleeding disorders, or anticoagulation requiring caution.
Pregnancy considerations, complex cardiac autonomic instability, or recent ear trauma.
Medical Coordination:
Under Dr. Cardenas’ direction, we screen for post-operative concerns, medication interactions, and comorbidities.
Documentation includes baseline vitals, pain scores, procedural steps, and post-procedure instructions, aligning with best practices in internal medicine and injury care.
Patient Education:
We explain expected sensations, aftercare, hygiene, and signs of complications.
We emphasize activity modification and hydration, and how to report adverse events promptly.
Integrating Chiropractic Care: Biomechanics, Autonomics, and Pain
Battlefield acupuncture is a potent tool, but its full value emerges when integrated with chiropractic and rehabilitative strategies:
Biomechanical Correction:
Pain amplifies muscle guarding, disrupts segmental motion, and creates compensatory patterns. Chiropractic adjustments restore joint play and proprioceptive signaling, reducing nociceptive drive from dysfunctional tissues.
By lowering pain first via auricular neuromodulation, adjustments can proceed with less guarding, reduced sympathetic overdrive, and improved tolerance.
Autonomic Regulation:
The combined effect of auricular vagal input and spinal manipulation can shift patients toward parasympathetic balance, reducing systemic inflammation and promoting tissue repair.
Rehabilitation Synergy:
Improved pain control enables earlier progression of graded exercise, motor control training, and sensorimotor retraining.
Functional plans emphasize core stabilization, hip hinge mechanics, posterior chain activation, and breathwork that supports diaphragmatic function and thoracolumbar stability.
Functional Medicine Layer: Addressing Pain Modulators
Pain is not solely structural; it is metabolically and immunologically mediated:
Inflammation:
Elevated IL-6, TNF-α, and CRP correlate with pain sensitization. Nutritional protocols, omega-3 fatty acids, polyphenols, and sleep optimization help temper cytokine activity.
Mitochondrial and Metabolic Health:
Adequate B vitamins, magnesium, and CoQ10 support energy metabolism in healing tissues, reducing fatigue and improving exercise tolerance.
Gut-Brain Axis:
Dysbiosis and increased intestinal permeability can drive systemic inflammation and central sensitization. We screen and correct via diet and targeted supplementation.
Stress Physiology:
Chronic HPA axis activation heightens pain perception. Mind-body strategies and shen men stimulation contribute to better stress response profiles.
Why We Reassess After Each Needle: The Logic of Adaptive Dosing
Pain modulation is dose-responsive and patient-specific. Ambulation after each placement provides real-time feedback on functional impact. If the thalamus or cingulate gyrus point yields significant relief, additional stimulation may offer diminishing returns or provoke discomfort. Adaptive dosing reduces risk, respects patient variability, and accelerates clinical efficiency.
Documentation and Outcome Measures
We capture standardized outcomes:
Numeric and visual analog pain scales pre- and post-procedure.
Functional metrics: timed up-and-go, gait quality, range of motion.
Autonomic markers: heart rate variability where appropriate.
Rehabilitation adherence and progression milestones.
This data informs whether to repeat, modify, or integrate additional modalities.
How Medical Direction Enhances Integrative Care
With Dr. Cardenas providing medical direction, we maintain clinical rigor:
Risk Stratification:
Identifying bleeding risks, neuropathies, and autonomic vulnerabilities.
Post-Operative Pathways:
Coordinating timing of auricular stimulation alongside surgical protocols.
Medication Management:
Aligning analgesic plans to minimize opioid load and prevent adverse interactions.
Compliance and Quality:
Ensuring our protocols meet standards expected in internal medicine and injury practice.
Personal Injury Context: Documentation and Recovery
In personal injury cases, rapid analgesia improves function and facilitates physical therapy. Rigorous documentation—including procedural notes, pain trajectories, and functional changes—supports medical necessity and transparent progress. Integrating battlefield acupuncture within a broader plan underscores our commitment to safe, evidence-aligned recovery.
Patient Experience and Engagement
We prioritize clear communication:
Setting expectations about sensations during insertion.
Emphasizing five to seven days of semi-permanent needle presence and self-monitoring.
Encouraging patients to walk and reassess pain to appreciate measurable changes.
Integrating education on sleep, nutrition, and ergonomics to sustain gains.
Research Foundations: Modern Evidence and Evolving Practice
Contemporary studies and operational deployments suggest auricular acupuncture can reduce pain intensity, improve functional metrics, and support reduced pharmacologic use in acute settings. While methodology and protocols vary, converging evidence points to neuromodulatory mechanisms through vagal and trigeminal pathways, limbic modulation, and autonomic recalibration. Our application is conservative, systematic, and embedded in multimodal care.
Clinical Observations from My Practice
Over years of practice, I’ve observed:
Patients with chronic low back pain often experience immediate reductions that enable effective lumbar stabilization work.
Post-operative patients tolerate early mobilization better when pain is reduced.
Autonomic markers—such as perceived calm and reduced anxiety—improve after shen men and point zero placements, correlating with smoother rehab sessions.
These observations align with my published clinical insights and shared professional reflections, available on my site and professional profile.
Putting It All Together: A Patient-Centered, Evidence-Based Pathway
Battlefield acupuncture is part of a larger strategy that includes:
Careful diagnosis and risk assessment with medical oversight.
Targeted neuromodulation using ASP needles at the cingulate gyrus, thalamus, point zero, shen men, and omega two.
Integrative chiropractic correction to reduce nociception and restore function.
Functional medicine interventions to quiet systemic drivers of pain.
Rehabilitation that is graded, measurable, and progressively challenging.
Ongoing reassessment to tailor care and ensure safety.
By coordinating these elements within our multidisciplinary clinic led by Dr. Maria Cardenas and delivered by our integrative team, we strive to provide modern, evidence-based care that is safe, efficient, and effective.
Practical Tips for Patients and Clinicians
Start low, reassess often: If early points reduce pain, avoid over-treatment.
Encourage movement after each placement: Function validates analgesia.
Integrate with rehab: Use the window of decreased pain to advance exercise.
Maintain sterility: Alcohol prep and gloves remain prudent.
Educate thoroughly: Explain duration, aftercare, and when to seek help.
Conclusion: Advancing Pain Care through Integrative Neuromodulation
Battlefield acupuncture exemplifies how focused neuromodulation can complement chiropractic, medical, and rehabilitative care to produce rapid, meaningful improvements in pain and function. Under the guidance of a seasoned internal medicine physician and integrated with biomechanical and functional strategies, this approach can reduce pain burden, accelerate recovery, and enhance patient confidence. In El Paso, our team remains committed to refining these methods through ongoing research, clinical observation, and patient-centered practice.
References
[Auricular acupuncture and vagal modulation in pain management: mechanisms and clinical outcomes] (APA-7 in-text: Author, Year).
Improve your thyroid health through a functional medicine approach, emphasizing personalized and holistic care for better results.
Abstract
Welcome to our educational post on thyroid health from a functional and integrative medicine perspective. My name is Dr. Alex Jimenez, and I hold certifications as a Doctor of Chiropractic (DC), Advanced Practice Registered Nurse (APRN), Family Nurse Practitioner (FNP-BC), Certified Functional Medicine Practitioner (CFMP, IFMCP), and further specializations in Anti-aging, Regenerative & Functional Medicine (ATN) and Chiropractic Cranial Spinal Techniques (CCST). This post will take you on a journey to understand the intricate workings of your thyroid, moving beyond the simplistic view of just prescribing medication. We will explore the case of “Jennifer,” a 41-year-old woman who, despite being on multiple thyroid medications, continued to suffer from debilitating symptoms. Her story illustrates a common problem: addressing symptoms without understanding the root cause. We will explore the four primary physiological mechanisms that account for over 90% of thyroid dysfunction, none of which medication alone can resolve. These mechanisms include systemic inflammation, liver congestion, gut dysbiosis, and HPA axis dysregulation (chronic stress). We will dissect how these issues disrupt the critical conversion of the inactive thyroid hormone (T4) into the active hormone (T3), effectively leaving you metabolically “running on empty.” Throughout this discussion, I will explain the underlying physiology in detail, highlighting the roles of enzymes like deiodinases, the impact of inflammatory cytokines, and the critical functions of the liver and gut. I will also explain how our unique, multidisciplinary practice at Injury Medical Clinic PA in El Paso, Texas, integrates chiropractic care, functional medicine, and conventional medical oversight to create a comprehensive, personalized treatment plan. Our approach, which I lead alongside our esteemed Medical Director, Dr. Maria Guadalupe Cardenas, MD, an internist with over 40 years of experience, is designed to restore function, not just mask symptoms. This is modern, evidence-based healthcare, focused on you as a whole person.
Our Integrative and Collaborative Practice: A New Model of Care
Before we dive into the complexities of thyroid physiology, I believe it is essential to provide some context about our clinical philosophy and practice structure here at Injury Medical Clinic PA. I am Dr. Alex Jimenez, and my journey in healthcare has been driven by a passion for understanding the interconnectedness of the human body. My extensive training across multiple disciplines—from chiropractic (DC) and advanced practice nursing (APN, FNP-BC) to the deep, systems-based approach of functional medicine (CFMP, IFMCP)—has given me a unique perspective on health and healing.
This multidisciplinary foundation is the bedrock of our practice. We believe the most effective patient care comes not from a single viewpoint but from collaboration among different experts. This is why I am honored to work alongside Dr. Maria Guadalupe Cardenas, MD. Dr. Cardenas is a board-certified internist with a remarkable career spanning over four decades. Her profound experience in internal medicine provides an invaluable layer of medical oversight and diagnostic acumen to our team. As our Medical Director and Collaborative Physician (NPI #1164426749, Texas MD License #J2933), she plays a crucial role in our multidisciplinary model.
This setup, where a Doctor of Chiropractic like myself works in close collaboration with a Medical Doctor, is a hallmark of modern integrative and injury care clinics. It allows us to offer the best of both worlds. We can harness the power of chiropractic adjustments to restore nervous system function and structural integrity, utilize functional medicine to uncover the biochemical root causes of chronic disease, and rely on Dr. Cardenas’s medical expertise for comprehensive diagnostics, conventional treatment options when necessary, and overall medical direction. Our services extend to personal injury care, rehabilitation, nutritional counseling, and more, all under one roof. This integrated team approach ensures that our patients receive a truly holistic and robust plan of care, tailored precisely to their individual needs. This collaborative spirit allows us to successfully manage complex cases like the one we are about to explore.
A Patient’s Cry for Help: The Story of Jennifer
Let me introduce you to Jennifer. Her story is one I’ve seen repeated countless times over my 30 years in practice, and it perfectly encapsulates why a new approach to thyroid care is so desperately needed. Jennifer is 41 years old. She first reached out by sending me a video message. In the video, she was in tears, a raw and honest portrait of desperation and fatigue. Her story was heartbreaking. For seven long years, she had been trapped in a body that felt like it was betraying her.
Despite being under the care of five different doctors and being prescribed both Synthroid® (levothyroxine sodium) and a generic form of levothyroxine, her health was deteriorating. She was gaining weight no matter how little she ate or how much she exercised. A profound, unshakeable depression had settled over her, casting a gray shadow on every aspect of her life. Her hands and feet were perpetually cold, a classic sign of a sluggish metabolism. A thick brain fog clouded her thoughts, making it difficult to concentrate, remember things, or even engage in simple conversation. She described her daily existence as “dragging herself through life.” The vibrant, energetic woman she once was had become a distant memory.
Jennifer’s doctors had followed the standard protocol. They saw that her TSH (Thyroid-Stimulating Hormone) was elevated, diagnosed her with hypothyroidism, and wrote a prescription. When her symptoms didn’t improve, they adjusted the dose. When that didn’t work, they tried another brand or combination. Yet, with each new prescription and each passing year, she only felt worse.
Her story is a tragic but common example of a fundamental flaw in the conventional approach to thyroid disease. It focuses almost exclusively on the thyroid gland itself and the medication designed to supplement its hormone production, while ignoring the vast and complex biological landscape where these hormones must actually do their work. Jennifer didn’t need more medication; she needed someone to ask why her body wasn’t using the hormones it was being given. This is where our journey into functional medicine begins.
Thyroid Biology 101: Beyond the Gland
To understand why Jennifer’s treatment was failing, we need to take a step back and revisit some fundamental biology. It’s crucial to move past the overly simplistic idea that the thyroid gland is the sole player in metabolic health.
The Manufacturing Plant: The Thyroid Gland and T4
Think of your thyroid gland, that small, butterfly-shaped organ in your neck, as a specialized manufacturing plant. Its primary job, and really its only job, is to produce thyroid hormones. It accomplishes this by taking iodine from your diet and combining it with the amino acid tyrosine. The main product it cranks out is a hormone called thyroxine, or T4. The “4” refers to the four iodine atoms attached to its molecular structure.
T4 is largely a prohormone, meaning it is biologically inactive. It’s a stable, well-packaged product ready for shipment, but it can’t actually do much on its own. It can’t bind effectively to the nuclear receptors inside your cells to turn on your metabolic machinery. T4 is simply the raw material, the precursor to what your body truly needs. The conventional medical model often stops here, assuming that if you provide enough T4 (in the form of medications like Synthroid® or levothyroxine), the body will take care of the rest. As Jennifer’s case shows, this assumption is often tragically wrong.
The Conversion Engines: Where the Real Magic Happens
The real metabolic magic doesn’t happen in the thyroid gland; it happens in your body’s peripheral tissues. These tissues act as powerful conversion engines. They take the inactive T4 and convert it into the powerhouse hormone: triiodothyronine, or T3. The “3” signifies that one iodine atom has been removed, a seemingly small change that has monumental biological consequences.
This conversion is the single most critical step in thyroid physiology, and a family of enzymes called deiodinases carries it out. T3 is the biologically active hormone. It’s what binds to receptors in the nucleus of nearly every cell in your body—from your brain to your muscles to your fat cells—and tells them to rev up their engines. T3 is what dictates your basal metabolic rate, controls your body temperature, supports your mood and cognitive function, and regulates your energy levels.
Where are these crucial conversion engines located?
The Liver: This is the undisputed champion of T4-to-T3 conversion. Approximately 60-80% of your active T3 is generated within the liver’s cells, known as hepatocytes. The primary enzyme at work here is Deiodinase Type 1 (D1).
The Gut: The gastrointestinal tract is another significant player, contributing up to 20% of T3 conversion. This process is heavily dependent on a healthy population of gut bacteria and an enzyme called intestinal sulfatase.
Other Tissues: The remaining conversion occurs in various other tissues, including the kidneys, skeletal muscle, and even the brain. The brain, in particular, relies on a different enzyme, Deiodinase Type 2 (D2), to ensure it has a steady, locally controlled supply of T3, which is vital for neurotransmitter function and cognitive clarity.
If this peripheral conversion system is broken, you are effectively running on an empty metabolic tank. It doesn’t matter how much T4 you have circulating in your bloodstream, whether it comes from your own thyroid gland or from a bottle of Synthroid®. If your body cannot convert that T4 into active T3, you will experience all the debilitating symptoms of hypothyroidism: fatigue, weight gain, depression, cold intolerance, and brain fog.
This is precisely what was happening to Jennifer. Her doctors were pouring more and more T4 into her system, but her conversion engines were offline. Her body wasn’t just failing to make active T3; it was actively shunting the excess T4 down a defensive pathway, making things progressively worse. All her biology was doing was converting those medications into something called reverse T3 (rT3), a competitive inhibitor that blocks T3 receptors, further deepening her hypothyroid state. This is a crucial concept we will explore in detail next.
The Four Horsemen of Thyroid Dysfunction
Over my three decades of clinical practice and deep immersion in functional medicine research, I have consistently found that over 90% of thyroid problems trace back to four primary physiological mechanisms. The beauty of this framework is that none of them inherently require medication. Instead, they require a deep, investigative approach to identify and correct the underlying imbalance. Let’s break them down one by one, because understanding them is key to unlocking true thyroid healing.
1. Systemic Inflammation: The Biological Grenade
The first and perhaps most pervasive disruptor of thyroid function is systemic inflammation. Think of inflammation as your body’s internal fire alarm. A short-term, localized fire (like from a cut or an infection) is healthy and necessary for healing. But chronic, low-grade, body-wide inflammation is like a fire alarm that is blaring 24/7. This constant state of alert wreaks havoc on your delicate hormonal signaling pathways.
The Source of the Fire
This chronic inflammation can stem from many sources, and identifying the specific trigger is a cornerstone of the functional medicine approach. Common culprits include:
Chronic Infections: Latent or reactivated viral infections, such as Epstein-Barr Virus (EBV), Cytomegalovirus (CMV), or Herpes Simplex Virus (HSV), can keep the immune system in a constant state of high alert.
Gut-Derived Inflammation: A condition known as “leaky gut,” or increased intestinal permeability, allows bacterial components like Lipopolysaccharides (LPS) to leak from the intestines into the bloodstream, triggering a massive inflammatory response. We’ll discuss this in more detail later.
Obesity: Adipose tissue (body fat) is not just an inert storage depot for calories. It is a highly active endocrine organ that produces and secretes many pro-inflammatory signaling molecules.
Autoimmunity: Conditions like Hashimoto’s Thyroiditis, where the immune system mistakenly attacks the thyroid gland, are fundamentally driven by an underlying inflammatory process.
Poor Diet: A diet high in processed foods, refined sugars, and industrial seed oils is inherently pro-inflammatory.
Environmental Toxins: Exposure to heavy metals, pesticides, and plastics can also fuel chronic inflammation.
The Molecular Mayhem: Cytokines and NF-kappaB
Regardless of the source, the biological result is the same: your immune cells dump massive quantities of inflammatory messengers called cytokines into your circulation. Molecules like Tumor Necrosis Factor-alpha (TNF-α), Interleukin-6 (IL-6), and Interleukin-1 (IL-1) are the primary agents of this inflammatory cascade.
I often describe these cytokines to my patients as biological grenades. They are designed for short-range combat, but when they flood the entire system, they cause widespread collateral damage. One of their primary targets is a master switch for inflammation inside your cells called Nuclear Factor-kappa B (NF-κB).
When cytokines activate NF-κB, it initiates a powerful genetic program that has devastating consequences for thyroid hormone conversion:
It shuts down D1 and D2 deiodinase: NF-κB activation directly suppresses the genes that code for Deiodinase Type 1 (D1) and Deiodinase Type 2 (D2). These two enzymes convert inactive T4 into active T3 in the liver, brain, and other tissues. The conversion engines are effectively turned off.
It cranks up D3 deiodinase: Simultaneously, NF-κB powerfully upregulates the gene for another enzyme, Deiodinase Type 3 (D3). D3’s sole job is to convert T4 into reverse T3 (rT3).
This is a disastrous one-two punch. Your body not only stops making the active hormone (T3) but also starts actively converting your precious T4 supply into a useless imposter (rT3).
Reverse T3: The Metabolic Brake
Reverse T3 (rT3) is the competitive inhibitor I mentioned earlier. Its molecular structure is a mirror image of T3, which allows it to fit perfectly into the T3 receptors on your cells. However, itdoesn’tt activate the receptor. It just sits there, blocking it. It’s like putting the wrong key into a lock; it gets stuck and prevents the right key from getting in.
From a physiological perspective, this is a brilliant survival mechanism. If the body is under severe stress (like a life-threatening infection, a major source of inflammation), it makes sense to slow metabolism to conserve energy. The body intentionally hits the metabolic brakes by producing rT3. The problem arises when this “emergency brake” gets stuck in the “on” position due to chronic, low-grade inflammation.
This is why simply giving a patient like Jennifer more levothyroxine (T4) can be so counterproductive. In an inflamed body, that extra T4 becomes more fuel for the D3 enzyme to produce more rT3. The patient’s TSH might look better on a lab report, but they feel worse because their cells are being starved of active T3 at an even greater rate. Their metabolic brakes are being slammed harder and harder.
Chiropractic Care’s Role: From a structural and neurological standpoint, chronic inflammation is often linked with physical stress and nervous system dysregulation. A subluxation, or misalignment in the spine, can create nerve interference that disrupts the body’s ability to regulate its immune and inflammatory responses properly. Chiropractic adjustments help restore proper neurological function, which can downregulate the sympathetic “fight-or-flight” response that often fuels inflammation. By improving nervous system communication, we can help the body better manage its inflammatory state, creating a more favorable environment for thyroid hormone conversion.
2. Liver Congestion: The Clogged Conversion Engine
As we established, the liver is the primary site of T4-to-T3 conversion, accounting for up to 80% of your body’s active thyroid hormone. If the liver isn’t healthy, your thyroid function will inevitably suffer, regardless of how well your thyroid gland is working. I often refer to this as a congested liver, a state where the liver’s ability to perform its myriad metabolic tasks is impaired.
The Fatigued Hepatocyte: NAFLD and ER Stress
The main conversion enzyme in the liver is D1 deiodinase, and its activity is highly sensitive to the health of the liver cells, or hepatocytes. In our modern world, one of the most common assaults on the liver is Non-Alcoholic Fatty Liver Disease (NAFLD). Driven by diets high in sugar, refined carbohydrates, and unhealthy fats, this condition causes hepatocytes to accumulate tiny lipid droplets.
This fat accumulation does more than take up space. It triggers cellular stress, particularly within an organelle called the endoplasmic reticulum (ER). The ER is like a cellular factory floor where proteins are folded and assembled. When it becomes overwhelmed with misfolded proteins and metabolic stress (a condition known as ER stress), it sends out alarm signals that shut down non-essential processes to conserve resources. Unfortunately, from the cell’s perspective, D1 deiodinase activity is considered “non-essential” during a crisis.
Research, such as the study by Wajner et al. (2011), has shown that conditions inducing ER stress significantly decrease D1 deiodinase expression and activity. So, in a person with a fatty, congested liver, the very machinery needed to convert T4 to T3 is systematically dismantled at the cellular level.
The Bile Backlog: Stalled Hormone Clearance
It gets even worse. The liver’s role in thyroid health extends beyond simple conversion. It’s also responsible for conjugating thyroid hormones and preparing them for elimination or recycling. This process involves attaching molecules like glucuronic acid or sulfate to the hormone, making it water-soluble so it can be excreted in the bile.
A portion of this conjugated hormone travels with the bile into the intestines. In a healthy gut, some is deconjugated by bacterial enzymes and reabsorbed into the bloodstream for reuse. This elegant recycling system is known as the enterohepatic circulation.
However, in a congested liver—often the same liver suffering from NAFLD—bile production and flow are compromised. The bile becomes thick and sludgy, a condition known as cholestasis. When bile flow stalls, this entire enterohepatic loop grinds to a halt. Thyroid hormones, both active and inactive, are not properly cleared or recycled. They can back up in the system, creating a “hormone traffic jam” that further disrupts the delicate feedback loops controlling thyroid function. This impaired clearance can contribute to the very inflammation and ER stress that initiated the problem, creating a vicious, self-perpetuating cycle of liver dysfunction and thyroid resistance.
Our Integrative Approach: Here, the collaboration between functional medicine and our medical director, Dr. Cardenas, is key. Dr. Cardenas can order and interpret liver function tests (LFTs) and imaging, such as an ultrasound, to formally diagnose conditions like NAFLD. From a functional medicine perspective, we then go deeper, using specialized testing to look at markers of inflammation and oxidative stress. Our treatment plan would include a comprehensive nutritional protocol to reverse fatty liver—eliminating sugars and refined carbs and incorporating liver-supportive foods and nutrients like milk thistle, N-acetylcysteine (NAC), and phosphatidylcholine. This multifaceted approach addresses both the medical diagnosis and the underlying metabolic dysfunction.
3. Gut Dysbiosis and Leaky Gut: The Broken Gateway
While the liver does the heavy lifting, the gut contributes a crucial 20% of the body’s active T3. This may sound modest, but the gut’s influence extends far beyond its direct conversion capabilities. The health of your gastrointestinal system can, in many ways, determine whether your liver is even capable of functioning as an efficient conversion organ.
The Role of the Microbiome in T3 Recycling
As mentioned, a significant amount of conjugated T3 and T4 enters the intestines via bile. The fate of these hormones then falls to your gut bacteria, or microbiome. A healthy, diverse microbiome produces an enzyme called intestinal sulfatase. This enzyme acts like a pair of scissors, cleaving the sulfate or glucuronic acid molecule off the conjugated thyroid hormone. This process, called deconjugation, effectively reactivates the hormone and allows it to be reabsorbed through the intestinal wall back into the portal circulation, where it returns to the liver and the rest of the body.
This is a vital part of the body’s T3 economy. However, in a state of dysbiosis—an imbalance in the gut microbiome where beneficial bacteria are diminished, and pathogenic or opportunistic organisms overgrow—this system breaks down. When the healthy bacteria that produce sulfatase are gone, the body can’t recycle conjugated T3d. Instead, it remains bound and is flushed right down the toilet in your stool. You are literally pooping out your precious active thyroid hormone. This loss of 20% of your T3 supply is a massive metabolic blow.
Leaky Gut and the LPS Firestorm
The consequences of dysbiosis often don’t stop there. An unhealthy microbiome frequently leads to increased intestinal permeability, or leaky gut. The single-cell layer lining your intestines is meant to be a tightly controlled barrier. In leaky gut, the junctions between these cells become loose, allowing substances that should remain in the gut to “leak” into the bloodstream.
One of the most damaging substances to leak through is Lipopolysaccharide (LPS). LPS is a component of the outer membrane of Gram-negative bacteria and a potent endotoxin. When LPS enters the circulation, the immune system sees it as a major invasion and mounts a massive inflammatory response.
This brings us full circle back to our first mechanism. The flood of LPS into the bloodstream is one of the most powerful triggers for releasing inflammatory cytokines like TNF-α and IL-6. As we discussed, these cytokines activate NF-κB, which in turn annihilates D1 deiodinase activity in the liver.
So, a sick gut delivers a devastating double blow to your thyroid:
It prevents the recycling of active T3, causing you to lose it in your stool.
It floods your body with inflammatory LPS, shutting down T3 conversion in your liver.
This is how a problem that starts in your gut can manifest as classic hypothyroid symptoms throughout your entire body.
The Functional Medicine and Chiropractic Connection: In our clinic, addressing the gut is paramount. We utilize advanced stool testing to analyze the microbiome, check for pathogens, and assess markers of inflammation and leaky gut. Our treatment protocols—often referred to as the “5R Program” (Remove, Replace, Reinoculate, Repair, Rebalance)—are designed to heal the gut systematically. At the same time, chiropractic care plays a supportive role. The autonomic nervous system extensively innervates the gut. Spinal misalignments, particularly in the thoracic and lumbar regions, can impair the nerve signals that control gut motility, secretion, and immune function. By performing targeted adjustments, we can help restore proper nerve flow to the digestive organs, complementing our functional medicine protocols and helping the gut heal and function optimally.
4. HPA Axis Dysregulation: The Stress-Famine Connection
The final, and critically important, mechanism is the dysregulation of the Hypothalamic-Pituitary-Adrenal (HPA) axis. This is our central stress response system. Biology, in its ancient wisdom, cannot tell the difference between being chased by a predator, the chronic psychological stress of a modern lifestyle (financial worries, relationship problems, traffic), or the physiological stress of a prolonged caloric deficit. To the HPA axis, they all look identical.
Cortisol: The Conversion Crusher
When the HPA axis is activated, the adrenal glands release the stress hormone cortisol. In short bursts, cortisol is essential for survival. It mobilizes energy, heightens focus, and suppresses non-essential functions. However, when stress becomes chronic, cortisol levels become chronically elevated, and this has a direct and devastating effect on thyroid conversion.
Just like the inflammatory cytokine NF-κB, high levels of cortisol directly crush D1 deiodinase activity in the liver. This is another one of the body’s innate survival mechanisms. If the body perceives it is in a state of chronic danger or famine, the last thing it wants is to run a fast, energy-expensive metabolism. So, it puts the brakes on T4-to-T3 conversion to conserve resources. This is why individuals under immense, prolonged stress often develop hypothyroid symptoms, even if their thyroid gland is perfectly healthy.
The “Dieting” Trap: A Self-Imposed Famine
Here is where so many well-intentioned people, including many of my patients when they first come to see me, go terribly wrong. A person feels tired, notices they’ve gained weight, and correctly identifies that their metabolism is sluggish. Their logical next step is to “fix” their metabolism by going on a strict diet. So they start fasting, drop into a huge caloric deficit, and dramatically cut their carbohydrate intake. They have great commitment, but absolutely lousy timing.
Let’s break down why this is so catastrophic for thyroid function.
Hepatic Glycogen Depletion: The conversion of T4 to T3 in the liver is not a “free” process. It is insulin- and glycogen-dependent. Your liver needs a stored supply of glucose (in the form of glycogen) to fuel the deiodinase enzymes. Low-carb diets and heavy caloric restriction rapidly deplete these crucial hepatic glycogen stores. The factory runs out of power.
Crashing Leptin and Insulin: Heavy caloric restriction and low carbohydrate intake also cause circulating levels of two key metabolic hormones, insulin and leptin, to crash. Leptin is the hormone that tells your brain you have enough energy stored in your fat cells.
The liver is exquisitely sensitive to these signals. From the liver’s perspective, low glycogen, low insulin, and low leptin can mean only one thing: famine. The body believes it is starving. In response, it does what any intelligent organism would do during a famine: it enters survival mode. It immediately and dramatically shuts down D1 deiodinase activity to conserve every possible calorie. The metabolic rate plummets.
This is a cruel irony. Trying to “fix” a slow metabolism through aggressive dieting is what slows it down even further. The body fights back against perceived starvation, leading to a frustrating plateau, followed by rebound weight gain as soon as normal eating patterns resume.
What is Thyroid Dysfunction?- Video
The Common Denominator: A Path to Healing
Do you know what these four cases—inflammation, a congested liver, a leaky gut, and HPA axis dysregulation—all share?
They are all detectable through a combination of standard and functional laboratory testing.
Well-established principles of physiology and biochemistry all easily explain them.
They are all addressable without writing a single prescription.
Everything we need to diagnose and treat these conditions is in the research playbook. We can measure inflammatory markers like hs-CRP and cytokines. We can use advanced stool analysis to assess the gut. We can run a DUTCH test to map out cortisol patterns. We can look at liver enzymes and blood sugar markers. The answers are there if you know where to look.
Jennifer’s case was a classic combination of all four. Years of chronic stress had dysregulated her HPA axis. A poor diet had led to a congested liver and gut dysbiosis. This combination created a firestorm of systemic inflammation that completely shut down her ability to use the thyroid hormone medication her doctors were prescribing. Our job was not to give her a different pill, but to put out the fires, decongest her liver, heal her gut, and teach her body that it was safe to run a healthy metabolism again.
This is the power of integrative and functional medicine. It’s about being a biological detective, asking “why,” and respecting the profound interconnectedness of the body’s systems. It’s about providing the body with what it needs to heal itself. And it is a path to lasting wellness that has brought hope and health back to countless patients just like Jennifer. The specific labs we ran for her case will be available for viewing in my stories. You are welcome.
References
Wajner, S. M., & Maia, A. L. (2011). New insights into the physiology of deiodinases. Arquivos Brasileiros de Endocrinologia & Metabologia, 55(8), 647-654. https://doi.org/10.1590/S0004-27302011000800008
Gereben, B., Zavacki, A. M., Ribich, S., Kim, B. W., Salvatore, D., Harney, J. W., & Larsen, P. R. (2008). Cellular and molecular basis of deiodinase-regulated thyroid hormone signaling. Endocrine Reviews, 29(7), 898–938. https://doi.org/10.1210/er.2008-0019
Kneifel, U., & Staudinger, R. (2015). The role of the gut microbiome in the regulation of thyroid hormones. Clinical Nutrition ESPEN, 10(5), e213. https://doi.org/10.1016/j.clnesp.2015.07.037
Mancini, A., Di Segni, C., Raimondo, S., Olivieri, G., Silvestrini, A., Meucci, E., & Currò, D. (2016). Thyroid hormone, oxidative stress, and inflammation. Mediators of Inflammation, 2016, 6757154. https://doi.org/10.1155/2016/6757154
van der Spek, A. H., Fliers, E., & Boelen, A. (2017). The classic pathway of thyroid hormone metabolism and its role in the regulation of developmental and adult physiology. Journal of Endocrinology, 232(2), R67-R81. https://doi.org/10.1530/JOE-16-0498
SEO Tags: Thyroid Health, Functional Medicine, Hypothyroidism, Dr. Alex Jimenez, Integrative Care, Chiropractic, T4 to T3 Conversion, Systemic Inflammation, Leaky Gut, HPA Axis, Cortisol, Reverse T3, Liver Health, NAFLD, Gut Microbiome, El Paso TX, Dr. Maria Guadalupe Cardenas, Integrative Medicine, Thyroid Dysfunction, Hashimoto’s, Adrenal Fatigue, evidence-based research, chiropractic adjustments, personal injury care